Archives

Vaccine Hesitancy: Rebooting Management Strategies for Pharmacy Teams

Learning Objectives

After completing this continuing education activity, pharmacists will be able to

1. DESCRIBE vaccine hesitancy and barriers to vaccination.
2. RECOGNIZE how determinants of vaccine hesitancy contribute to behavioral outcomes.
3. RECALL common anti-vaccine claims and evidence-based rebuttals.
4. DISCUSS situation-appropriate intervention strategies.

After completing this continuing education activity, pharmacy technicians will be able to

1. RECALL the benefits of vaccination.
2. RECOGNIZE determinants of vaccine hesitancy.
3. LIST ways to promote vaccine acceptance.

     Release Date

    Release Date: September 14, 2026

    Expiration Date: September 14, 2029

    Course Fee

    $7 Pharmacist

    $4 Pharmacy Technician

    There is no funding for this CE.

    ACPE UANs

    Pharmacist: 0009-0000-26-049-H06-P

    Pharmacy Technician: 0009-0000-26-049-H06-T

    Session Codes

    Pharmacist: 26YC49-DIM37

    Pharmacy Technician: 26YC49-MDI73

    Accreditation Hours

    2.0 hours of CE

    Accreditation Statements

    The University of Connecticut School of Pharmacy and Pharmaceutical Sciences is accredited by the Accreditation Council for Pharmacy Education as a provider of continuing pharmacy education.  Statements of credit for the online activity ACPE UAN 0009-0000-26-049-H06-P/T will be awarded when the post test and evaluation have been completed and passed with a 70% or better. Your CE credits will be uploaded to your CPE monitor profile within 2 weeks of completion of the program.


    Disclosure of Discussions of Off-label and Investigational Drug Use

    The material presented here does not necessarily reflect the views of The University of Connecticut School of Pharmacy and Pharmaceutical Sciences or its co-sponsor affiliates. These materials may discuss uses and dosages for therapeutic products, processes, procedures and inferred diagnoses that have not been approved by the United States Food and Drug Administration. A qualified health care professional should be consulted before using any therapeutic product discussed. All readers and continuing education participants should verify all information and data before treating patients or employing any therapies described in this continuing education activity.

    Faculty

    Katherine E. MacDonald PharmD

    Walgreens Pharmacy

    Jewett City, CT


    Faculty Disclosure

    In accordance with the Accreditation Council for Pharmacy Education (ACPE) Criteria for Quality and Interpretive Guidelines, The University of Connecticut School of Pharmacy and Pharmaceutical Sciences requires that faculty disclose any relationship that the faculty may have with commercial entities whose products or services may be mentioned in the activity.

    Katherine MacDonald has no relationships with ineligible companies.


    ABSTRACT

    Vaccines are responsible for reducing the incidence of vaccine-preventable diseases. While most people receive routine recommended vaccinations, a small portion of the population does not. Vaccine hesitancy and refusal are complex behaviors, and the consequences of choosing not to vaccinate jeopardize both individual and societal health and safety.

    Pharmacists and pharmacy technicians must know the determinants and factors that contribute to vaccine hesitancy before they address and manage it appropriately. A comprehensive understanding of such influences can help pharmacists and pharmacy technicians identify and communicate with hesitant individuals better. Pharmacists and technicians are also able to screen patients for missing immunizations, provide patient education and support, and offer guidance.

    CONTENT

    Content

    Pause & Ponder: Which strategies have you used in the past to address patients’ vaccine concerns and questions?


    Introduction


    Vaccines benefit both the individual and the public by preventing the spread and reducing the incidence of vaccine-preventable diseases within a population.1 In developed countries, vaccines are responsible for diminishing the threat of vaccine-preventable diseases,2,3 particularly vaccine-preventable diseases that once plagued infants and children.4,5 A successful vaccination program is contingent on the majority of the population receiving recommended vaccinations as scheduled to ensure both individual and community protection.1,6 This creates ‘herd immunity.’ The vaccination coverage needed for community protection varies by disease; for measles, approximately 95% two-dose coverage is needed to prevent outbreaks. To ensure community protection and patient safety, healthcare providers should see all visits that do not risk patient and provider exposure as opportunities for patients to catch up on missing or late vaccinations.  Pharmacy teams should use every appropriate encounter to assess immunization status and provide needed catch-up vaccination.


    Nonadherence to vaccine recommendations, such as vaccination delay or refusal, undermines individual and public health initiatives.2,7,8 Pharmacists and technicians must also be aware that researchers may not have tested the efficacy of alternative vaccine schedules; such schedules may not produce an adequate immune response. Vaccine-preventable disease outbreaks are a consequence of undervaccination and are a prevalent threat even in the United States.7,8,9 As of August 13, 2026, CDC reported 2,566 confirmed U.S. cases during 2026, with 94% associated with outbreaks.10 Although vaccine-related concerns are common even among vaccine acceptors,1,5,11 several factors still motivate a minority of the population to delay or decline vaccination.1,8,11


    What is Vaccine Hesitancy?


    A panel of World Health Organization (WHO) immunization experts describes vaccine hesitancy as the ‘delay in acceptance or refusal of vaccines despite availability of vaccination services. Vaccine hesitancy is complex and context-specific; that means it varies across time, place, and vaccines. It is influenced by factors such as complacency, convenience, and confidence.’12


    It is important to understand that this definition recognizes only reluctant individuals’ possible decisions. In reality, hesitancy exists on a continuum.13 It ranges from complete refusal of all vaccines to complete acceptance without any concern; in between are intermediate decisions such as refusal of some vaccines and acceptance of others, and full acceptance although the individual is unsure.1 The spectrum of possible outcomes implies that the process of reaching a decision is complicated and guided by external and internal components.11 Identifying the factors that influence an individual’s behavior is essential to understanding the reasons for vaccine hesitancy. Knowing the specifics also helps determine the most appropriate intervention.8,11,13


    Understanding Vaccine Hesitancy


    The terms complacency, convenience, and confidence used in the WHO definition of vaccine hesitancy are the foundation of the ‘3 Cs’ model described in Table 1.14


    Table 1. Definitions of the ‘3 Cs’15


    Confidence: Trust in vaccine effectiveness and safety; the system that delivers them, including the reliability and competence of health services and health professionals; and the motivations of policy makers who decide on the needed vaccines.
    Complacency: The perceived risks of vaccine preventable diseases are low, and vaccination is not deemed a necessary preventive action.
    Convenience: A significant factor when physical availability, affordability and willingness to pay, geographical accessibility, ability to understand (language and health literacy), and appeal of immunization services affect uptake.


    These components are interlinked and influenced by vaccine hesitancy’s determinants (e.g., specific factors that influence an individual’s behavior; see Table 2) to ultimately affect vaccine-related decisions.13 Clinicians can use the determinants of vaccine hesitancy to determine an individual’s beliefs and opinions regarding vaccines and vaccination.5


    WHO’s Behavioral and Social Drivers (BeSD) framework identifies four domains that influence vaccine uptake: thinking and feeling, social processes, motivation, and practical issues. Beliefs, emotions, perceived risks, social norms, and recommendations influence a person’s motivation to receive a vaccine; however, practical barriers such as cost, convenience, and access may prevent vaccination even when motivation is strong. The framework encourages programs to measure these drivers and use the findings to design, implement, and evaluate interventions tailored to specific populations.16


    Table 2. Determinants of Vaccine Hesitancy13


    Influence Category Source of Influence Determinants (factors that affect outcome)
    Contextual influences Influences arising due to historic, socio-cultural, environmental, health system/institutional, economic or political factors §  Communication and media environment

    §  Influential leaders, immunization program gatekeepers and anti- or pro-vaccination lobbies

    §  Historic influences

    §  Religion/culture/gender/socio-economic

    §  Politics/policies

    §  Geographic barriers

    §  Perception of the pharmaceutical industry

    Individual and group influences Influences arising from personal perception of the vaccine or influences of the social/peer environment §  Personal, family, and/or community members' experience with vaccination, including pain

    §  Beliefs, attitudes about health and prevention

    §  Knowledge/awareness

    §  Health system and providers (trust and personal experience)

    §  Risk/benefit (perceived, heuristic [meaning learned from one’s own experiences])

    §  Immunization as a social norm vs. not needed/harmful

    Vaccine/vaccination-specific issues Directly related to vaccine or vaccinations §  Risk/benefit (epidemiological and scientific evidence)

    §  Introduction of a new vaccine , a new formulation, or a new recommendation for an existing vaccine

    §  Mode of administration

    §  Design of vaccination program/mode of delivery (e.g., routine program or mass vaccination campaign)

    §  Reliability and/or source of supply of vaccine and/or vaccination equipment

    §  Vaccination schedule

    §  Costs

    §  The strength of the recommendation and/or healthcare professionals’ knowledge base and/or attitudes


    Pause & Ponder: Which determinants have the most influence over an individual’s decisions? Which have the least?


    Contextual Influences


    Communication and Media Environment. The three most commonly referenced sources for vaccine-related information are healthcare providers, friends and family, and the media (primarily the Internet).5 Although healthcare providers encourage patients to seek knowledge about vaccines from reputable sources when making vaccine-related decisions, misinformation regarding vaccines is prevalent.17 Unfortunately, the widespread presence of incorrect information and universal use of the Internet and social media outlets can result in pervasive transmission of anti-vaccine messages.17 The pharmacy team also needs to repeat vaccine-promoting messages even if they perceive that the patient or parent is well educated; across the United States, areas of highly educated individuals include vaccine refusers.


    Exposure to anti-vaccine ideals can contribute to vaccine hesitancy through confirmation bias.17,18 Confirmation bias occurs when individuals accept only information that supports and validates what they already believe, perpetuating underlying bias.17 For example, if a person believes that all vaccines contain mercury, the person will preferentially read or listen to messages that confirm that incorrect information. (Routine childhood vaccines do not contain thimerosal as a preservative, except for certain multidose influenza vaccine formulations that always list thimerosal on the label.). The consequences of misinformation are twofold: misinformation contributes to how individuals and groups make vaccine-related decisions11,17 and provokes distrust of healthcare providers.2,9,17


    Religion. Faith and religion can have a profound impact on health-related behaviors, with pig (pork or porcine) consumption a particularly important consideration for people who are members of faiths that prohibit pork.19 (Some vegetarians and vegans also have concerns.) This belief does not impede many interventions, as pharmacists and other healthcare providers can recommend an alternative that does not contain porcine derivatives, and many individuals will accept it.19


    A few manufacturers use porcine gelatin as a stabilizer in some vaccine formulations (listed in Table 3).20 Its presence may be the sole reason that members of some religions refuse certain vaccines.19 If an appropriate substitute vaccine is available, pharmacy immunizers should offer this option.


    Table 3. US Vaccines Containing Porcine Gelatin20,21


    Porcine gelatin-containing vaccines Protects against Approximate gelatin per dose
    FluMist* Influenza 2 mg
    MMR-II** Measles, mumps, rubella 14.5 mg
    ProQuad***


    Measles, mumps, rubella, varicella 11mg
    Varivax**** Varicella 8.3–12 mg
    YF-VAX**** Yellow fever Not specified in current U.S. information
    Always check the current package insert/excipient information.

    * Injectable influenza vaccines provide alternatives to FluMist.

    ** PRIORIX is a gelatin-free alternative to M-M-R II.

    *** The United States currently has no gelatin-free varicella vaccine, so replacing ProQuad with PRIORIX plus Varivax does not entirely avoid gelatin.

    **** No alternative yellow fever vaccine is currently licensed in the United States.


    Individual and Group Influences


    Health system and providers: trust and personal experience. The patient-provider relationship is a central element of the vaccine decision-making process for many individuals.22,23 Patients hold healthcare providers—as educators and trusted health authorities—responsible for the outcomes of vaccine hesitancy and refusal-related conversations. The provider’s approach often influences the patient’s decision to vaccinate.


    If the relationship between patient and provider is built on cooperation, trust, and respect, patients are more likely to consider the provider a dependable resource and consider the provider’s behavior an example of best health practices.11 This dynamic permits healthcare professionals to engage in constructive discussion when approached with concerns, or to clarify misinformation that may obstruct the patient’s perspective on vaccines.24 From this vantage point, providers can advocate for vaccination acceptance while maintaining a patient-centered dialogue.5,11


    Conversely, an interaction’s outcome may instead be detrimental to the patient-provider relationship. Examples include when a provider assumes a patient’s reasons for hesitancy, or if a provider’s response does not meet the patient’s expectations.22 Misguided interventions often have the patient’s best interest in mind, yet neglecting a patient-centered approach will fall short of encouraging a reciprocal patient-provider relationship. Such an outcome can occur when a provider’s response to reluctance is providing information and education without first listening to the patient’s concerns (see the section on motivational interviewing below).22 For example, providers who do not ask patients why they refuse vaccines and simply present evidence-based information immediately come across as authoritarian and inflexible. Providers should not consider vaccine acceptance because the patient feels pressured or bullied to be a successful intervention. Other outcomes are also possible. The patient may misinterpret the provider’s efforts as patronizing and, in turn, dismiss the provider’s recommendations.25 Alternatively, patients may become distrustful. If they feel pressured by the provider to accept vaccination or believe the provider ignored or dismissed their concerns, they may consequently avoid future communication and possibly vaccination.22


    Perceived risk/benefit. Vaccine hesitancy is not only specific to vaccines—it also includes disease-specific concerns.8 If individuals believe that they are at risk for contracting a disease, they are more likely to seek and accept a vaccine to prevent that disease.1,8,11 However, this same risk/benefit analysis can produce the opposite outcome if the perceived risk of vaccination is greater than that of disease. It is critical to explain how dangerous vaccine-preventable diseases are.


    Vaccines are responsible for minimizing the incidence of many once-common vaccine-preventable diseases, which has altered many peoples’ perception of their disease susceptibility. That is, people think that now-rare diseases are unlikely to circulate.1,8 This unintended consequence has masked the risks and complications of many debilitating diseases, such as measles. In turn, some people have transferred the fears they previously held toward the disease to concerns regarding vaccine safety and the need for vaccines.1,2,8,9,22 A vaccine’s potential adverse health events may present a greater perceived risk than the disease, contributing to vaccine-hesitant beliefs and behaviors.1


    Knowledge/awareness. Although research confirms that vaccines are safe and effective,26 anti-vaccine sentiments take a variety of forms, as described in Table 4.


    Table 4. Common Anti-Vaccine Sentiments2,11,26,27

    Anti-vaccine claim Pro-vaccine rebuttal
    ‘Hot lots’ of vaccines are responsible for more serious adverse outcomes. Some people believe that some vaccine lots cause more side effects or vaccine injuries than other lots. People who perpetuate this myth apply data from the Vaccine Adverse Event Reporting System (VAERS) inappropriately.


    Members of the pharmacy team should explain that expected vaccine side effects—such as injection-site pain, fatigue, or a mild fever—differ from adverse events reported after vaccination. An adverse event is any health problem occurring after vaccination, whether mild or serious and whether or not the vaccine caused it. A VAERS report alone cannot establish causation; CDC and FDA use reports to identify signals that require further investigation.
    Antigenic overload occurs in children because their immune systems are unable to manage the number of antigens that vaccines introduce adequately, or antigenic overload causes a ‘cytokine storm’ that predisposes children to adverse events and vaccine-induced complications.


    No scientific evidence supports this claim. Additionally, children are exposed to significantly more antigens at birth than through vaccines. In a 2017 CDC comparison, vaccines used approximately 305 antigens to protect children against 14 diseases by age 2, compared with approximately 3,000 antigens used to protect against eight diseases 30 years earlier.
    Natural immunity from an infection is safer than immunity from a vaccine. Infection-induced immunity may elicit a superior immune response. However, the risks and complications associated with infection are significantly greater than those of vaccines. Vaccine-induced immunity is able to prevent infection successfully. Measles can cause immune amnesia, reducing previously acquired immune protection for months to years.
    Vaccines are responsible for the development of autoimmune diseases such as type 1 diabetes mellitus, multiple sclerosis, and Guillain-Barre syndrome.

    ·       This argument is based on the theory that the immune system is unable to discriminate between intrinsic antigens and the vaccine’s antigens, causing antibodies to bind the intrinsic antigens selectively, eliciting an autoimmune response.

    Multiple efforts have reviewed this claim. A panel of experts from the Institute of Medicine reviewed more than 12,000 published reports and several high-quality studies; none established a connection between vaccines and autoimmune diseases.


    Pause & Ponder: How do misinformation and anti-vaccine sentiments circulate widely when the correct recommendations and evidence supporting vaccination are just as accessible?


    Intervention Strategies: A Personalized Approach


    Patients and healthcare professionals need to work together—that is, collaborate and share decision-making—to adhere to vaccination programs and can do so after they take certain steps13:


    • Understand the risks and benefits of vaccination
    • Explain the vaccine-preventable disease and the consequences of contracting it. Make evidence-based decisions (such as adhering to recommended vaccine schedules) for patients. This means accessing CDC patient websites if patients need more information than the healthcare provider can provide.
    • Accept accountability for the health and safety of individuals who are unable to be vaccinated; patients who are healthy and robust need to understand that their failure to ‘join the herd’ of vaccinated people puts others at risk.
    • Advocate for health equity (the concept that everyone should have a fair opportunity to attain their full health potential and that no one should be disadvantaged from achieving this potential) regarding access to vaccine-related resources and the elimination of barriers.


    Efforts that involve patients and providers working collaboratively—sharing evidence, understanding each other’s points of view, and working toward good health for our entire society, not just the individual—depend on two things. First, providers must consider vaccine-hesitant patients’ needs and how they affect public health and safety needs. Second, providers need to consider their other patients; some practices will not see patients who refuse vaccines because they would potentially expose other patients to vaccine-preventable disease.22 Although the laws surrounding patient dismissal in this situation are not straightforward, ethical concerns such as negligence can manifest as legal troubles or disciplinary actions from the provider’s regulatory authority.28


    Beliefs and behaviors that relate to vaccine hesitancy vary at an individual level; clinicians must individualize strategies to address these concerns and ideally increase vaccine acceptance.1,9,11,19 Interventions should prioritize the patient’s autonomy,29 recognize the influence of specific determinants (particularly context and individual determinants),9,13 and ameliorate any barriers that may be present.11


    Identify Questions And Concerns: Motivational Interviewing

    Immunizers should begin the vaccine discussion with a strong recommendation presented in a presumptive format; that means speaking as though vaccination is the expected, routine next step—not presenting it initially as an open-ended decision. If the patient or parent expresses hesitancy, immunizers can then use motivational interviewing to explore and address the person’s concerns.30 Motivational interviewing is a communication technique that directs constructive conversations between patient and provider. This approach gives patients the opportunity to address their concerns consciously while actively informing the patient’s decision-making process, which promotes behavioral change through self-realized motivation.22,31 Motivational interviewing is not intuitive, and pharmacists and technicians sometimes need help identifying the questions to ask. The process itself has five steps:

    1. Listen to the patient’s concerns and any possibility that the patient may change
    2. Reflect back your understanding
    3. Identify missing or incorrect information
    4. Invite the patient to reconsider
    5. Summarize and reiterate the next steps


    Motivational interviewing (and open-ended questions) can help patients resolve their hesitancy.32,33 Immunizers need to listen to patients’ thoughts about change and what they think change will require. Reflect your understanding (‘I know that you have many vaccine-related concerns.’) Then, identify missing or incorrect information, but do not do it in a confrontational or scolding manner. Ask if you can address an issue directly and do so only if the patient agrees. (‘May I tell you something about vaccination that I learned in a continuing education class recently?’) Invite patients to reconsider, then summarize and reiterate next steps. (‘You said that needle-induced pain is a concern, and we talked about two things that might help—breathing exercises and topical spray that numbs the area. Which of those approaches might you be able to try before giving up?’)34,35 Some parents refuse the HPV vaccine for their teens, and after discussion, you might say, ‘You said that vaccination for HPV would encourage your son to engage in unprotected sexual activity. We agreed that it would be even MORE dangerous if he has unprotected sex without being vaccinated. And we agreed that kids often make risky decisions, and we identified two possible courses of action. You might talk to him about the risks of unprotected sex and ask him what he has heard about HPV vaccination in health class. Which of those approaches might you be able to try before giving up?’


    Providers must maintain a welcoming and patient-centered environment by remaining attentive and empathetic to the patient’s concerns and questions.31 To ensure this dynamic and encourage a cooperative and honest patient-provider relationship, providers should ask for the patient’s permission before dispensing advice or information if possible.25,31 This helps providers direct their input toward specific issues and prevents overwhelming the patient with unsolicited information.31


    Confront misinformation: Debiasing

    If a patient expresses concerns that refer to vaccine misinformation, debiasing may help correct the misconception.36 (These techniques come from social sciences journals and are not terms with which most pharmacists or technicians are familiar; they are included because they help address misinformation.) Providers must first gain an accurate understanding of the patient’s beliefs, as they can use debiasing techniques only if the patient is receptive to the proposed correction.36 Table 5 defines the potential impact of misinformation and associated intervention strategies. Debiasing requires everyone who counsels vaccine-hesitant patients to be on the same page.  Healthcare organizations should establish and consistently enforce evidence-based employee immunization policies that protect patients. Regardless of their personal beliefs, employees who counsel patients must provide accurate, evidence-based vaccine information and must not undermine recommended immunization practices.36


    Table 5. Misinformation Debiasing Strategies 36,37,38,39,40


    Effect of misinformation Debiasing techniques
    Misinformation, regardless of a correction, has continued influence over beliefs and behaviors. Clinicians create an information gap when they simply correct a misconception; provide an alternative evidence-based explanation to fill the gap.


    Familiarity backfire occurs when repetition strengthens a false belief. In some cases, patients later remember the myth rather than the evidence that disproves it—meaning the provider’s efforts backfired. Start with the facts and introduce the misinformation only afterward. Before mentioning misinformation, explicitly state that it is false. Explain why it is misleading and why people may believe it. Correct misinformation immediately after mentioning it and provide a reasonable explanation to replace the myth. Avoid repeating misinformation and then merely saying it is not true; focus on the correct explanation instead.


    Overkill backfire occurs when misinformation is easier to understand than a complicated correction, making the truth seem unrealistic. Corrections can occasionally strengthen a mistaken belief, but recent research suggests that these backfire effects are uncommon and should not discourage healthcare professionals from correcting misinformation. Keep corrections straightforward and short—less is more. For example, if a patient believes childhood vaccination causes type 1 diabetes, an elaborate explanation of disease pathology may overcomplicate the correction. A short, clear statement that evidence has not established such a connection is more useful.


    Worldview backfire occurs when a personal belief is threatened by the truth and misinformation is reinforced Affirm worldview with corrections that support the individual’s values and concentrate on positive facts, such as benefits and opportunities.


    Persistent refusal: Standby Strategies. Patients and parents may be unresponsive to vaccine-promoting interventions. If an individual continues to refuse vaccination, it is most important to acknowledge and honor the right to decline.17,25 Immunizers should not discount these interactions or label them as failures, but instead consider them an opportunity to try again later. Providers should encourage future contact if the patient has more questions or changes their mind regarding vaccination.25,41


    Healthcare providers must maintain respect and provide direct clinical recommendations for vaccinations.25 Finally, healthcare providers should inform patients of their responsibilities and vaccine refusal’s potential consequences (see Resources for Pharmacy Staff below for the CDC document, ‘If You Choose Not to Vaccinate Your Child, Understand the Risks and Responsibilities,’ and links to vaccine refusal documentation forms).41


    Conclusion


    Vaccine hesitancy is a complicated and often emotional issue. Pharmacists and pharmacy staff can identify obstacles and barriers to vaccination and acceptance through education and support while also offering reliable access to vaccines.4 Pharmacies eliminate barriers that prevent access to vaccine delivery services and increase vaccination rates through pharmacist-driven interventions.4,42,43 This presence and resultant impact on public health testifies to the importance of pharmacists as trained and certified immunizers.4 To maintain the success of pharmacy-based vaccination services, pharmacists and pharmacy staff should have a comprehensive and functional understanding of vaccine hesitancy and the skills to confront it appropriately.


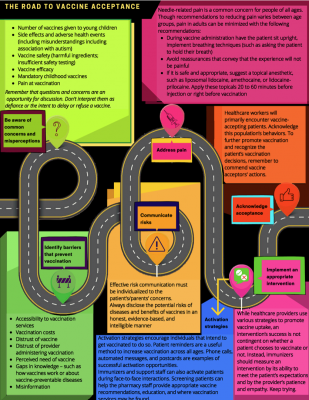
    Be aware of common patient/parental concerns/misperceptions1,5,18,7:

    • Number of vaccines given to young children
    • Side effects and adverse health events (including misunderstandings including associations with autism)
    • Vaccine safety (harmful ingredients; insufficient safety testing)
    • Vaccine efficacy
    • Mandatory childhood vaccines1
    • Pain at vaccination

    Remember that questions and concerns offer the opportunity for discussion and should not be interpreted as defiance or the intent to delay or refuse a vaccine.5


    Identify barriers that prevent vaccination38,9:

    • Accessibility to vaccination services
    • Vaccination costs
    • Distrust of vaccine
    • Distrust of provider administering vaccination
    • Perceived need of vaccine
    • Gaps in knowledge – such as how vaccines work or about VPDs
    • Misinformation


    Implement an appropriate intervention: While various strategies may be employed to promote vaccine uptake, an intervention’s success is not contingent on its outcome – whether a patient chooses to vaccinate or not. Instead, immunizers should measure an intervention by its ability to meet the patient’s expectations and by the provider’s patience and empathy.


    Communicate risks: Effective risk communication is dependent on the patient and must be individualized to the patient’s or parents concerns.22,34,35 Risk discussion should disclose the potential risks of diseases and benefits of vaccines, in an honest, evidence-based, and intelligible manner.34,35


    Activation Strategies: Activation strategies encourage individuals that intend to get vaccinated to do so.41 Patient reminders are a useful method to increase vaccination across all ages.42 Phone calls, automated messages, and postcards are examples of successful activation opportunities.44 Immunizers and support staff can also activate patients during face-to-face interactions. Screening patients can help the pharmacy staff provide appropriate vaccine recommendations, education, and where vaccination services may be found.4


    Address pain: Needle-related pain is a common concern for people of all ages.5,7 Though recommendations to reducing pain vary between age groups, pain in adults can be minimized with the following recommendations7:

    • During vaccine administration have the patient sit upright, implement breathing techniques (such as asking the patient to hold their breath)
    • Avoid reassurances that convey that the experience will not be painful
    • Suggest a topical anesthetic - liposomal lidocaine, amethocaine, or lidocaine-prilocaine are agents that may be applied 20 to 60 minutes before injection, or a topical vapocoolant may be used right before vaccination

    Road_to_Vaccine_Acceptance_REVISED
    infographic on various roadblocks and suggestions for overcoming them

    Resources for the Pharmacy Staff

    Centers for Disease Control and Prevention—Vaccine Excipient Summary: Excipients Included in U.S. Vaccines, by Vaccine https://www.cdc.gov/vaccines/pubs/pinkbook/downloads/appendices/b/excipient-table-2.pdf


    CDC – “If You Choose Not to Vaccinate Your Child, Understand the Risks and Responsibilities” https://stacks.cdc.gov/view/cdc/49075


    CDC – Current immunization schedules www.cdc.gov/vaccines/schedules/index.html

    Pharmacist Post Test (for viewing only)

    Vaccine Hesitancy: Rebooting Management Strategies for Pharmacy Teams

    26-049-H06-Pharmacist Post-test


    Pharmacist Learning Objectives:

    1. Describe vaccine hesitancy and barriers to vaccination
    2. Recognize how determinants of vaccine hesitancy contribute to behavioral outcomes
    3. Recall anti-vaccine claims and rebuttals
    4. Discuss situation-appropriate intervention strategies


    1. Which of the following MOST CLOSELY corresponds to the WHO definition of vaccine hesitancy?

    a. Simple vaccine refusal in any context including lack of available vaccination services

    b. Acceptance of any vaccine if the ability to access vaccination is convenient

    c. Delay in acceptance or refusal of vaccines despite availability of vaccination services


    *


    2. Select the influence category, source of influence, and determinants that are paired correctly.

    a. Contextual influence—peer environment--costs

    b. Vaccine-specific issues—specific vaccine—mode of administration

    c. Group influences—political factors—reliability of vaccine supply


    *


    3. A mother indicates she does not and will not vaccinate her children. You use motivational interviewing and learn that she believes natural immunity is safer than vaccine-induced immunity. What is an appropriate rebuttal if she consents to listen?

    a. Infection-induced immunity may elicit a superior immune response. However, the risks and complications associated with infection are significantly greater than those of vaccines

    b. A panel of experts from the Institute of Medicine reviewed more than 12,000 published reports and several high-quality studies; none indicate natural immunity is stronger

    c. The CDC’s system to track natural immunity vs. vaccine-induced immunity is called VAERS; you can examine the data in VAERS and see that your assumptions are wrong


    *


    4. Susan comes to the pharmacy and your technician reminds her she is due for her second HPV vaccination. Susan glances to the pharmacist’s workstation and quickly says, “Ummm, not today.” The technician gently says, “You’re here, and we’re not busy. Why don’t we get it done?” Susan replies, “No, not today. That guy gave me the last one and left a huge bruise. Not today.” What type of barrier is keeping Susan from her second shot?

    a. Vaccine accessibility

    b. Distrust of provider

    c. Gaps in knowledge


    *


    5. Dave arrives at the pharmacy to pick up his “sugar meds” and you notice that he hasn’t received his flu shot yet. After providing him with a clinical recommendation for the vaccine, Dave replies, “Why do I need to? I work from home and have never gotten the flu before. What’s the point?!” Which barrier is preventing Dave from getting the flu shot?

    a. Distrust of vaccine

    b. Misinformation

    c. Perceived need for vaccine


    *


    6. Manny is a regular customer who appears to be up to date on all of his vaccines except for the shingles vaccination. When you ask him why, he states that it’s for religious reasons, but says “I’d give it a try if there’s a shot without any pork in it.” Which intervention strategy would be most appropriate for Manny’s situation?

    a. Motivational interviewing about worldview

    b. Debiasing techniques to address overkill

    c. Offering Shingrix as an alternative


    Pharmacy Technician Post Test (for viewing only)

    Vaccine Hesitancy: Rebooting Management Strategies for Pharmacy Teams

    26-049 Pharmacy Technician Post-test


    Pharmacy Technician Objectives:

    1.Recall the benefits of vaccination

    2. Recognize the various determinants of vaccine hesitancy

    3. List ways to promote vaccine acceptance


    1. Which of the following is a benefit of vaccination?

    a. Vaccines reduce the incidence of some diseases

    b. Vaccines completely eradicate vaccine-preventable diseases

    c. Vaccines only benefit vaccinated infants and children


    *


    2. Which of the following vaccination patterns helps ensure the success of a vaccination program?

    a. Only high-risk people receive recommended vaccines

    b. Most people receive recommended vaccines on schedule

    c. Most infants and children receive some vaccines


    *


    3. Mary tells you that she has not been vaccinated because the only place that is covered by her insurance requires a subway ride and then a taxi ride. Which of the following is the most likely factor preventing Mary from receiving a vaccine?

    a. Geographic restrictions imposed by insurance

    b. Poor communication with her healthcare provider

    c. A bad attitude about necessary health care


    *


    4. Joe lives in a rural area, and your pharmacist suggests he receive a flu shot. Joe says that his own doctor said that flu shots are fine, but not necessary for healthy folks. (The doctor said he hasn’t gotten one, and isn’t worried about it.) Which of the following is the most likely influence category to explain Joe’s vaccine hesitancy?

    a. Vaccine/ vaccination-specific issues

    b. Individual and group influences

    c. Contextual influences


    *


    5. Which of the following is a way to promote vaccination in hesitant individuals?

    a. Ask the pharmacist to increase motivation using pressure

    b. Debunk any misinformation an individual may reference

    c. Listen to the individual’s concerns before taking action


    References

    Full List of References

    1. Salmon DA, Dudley MZ, Glanz JM, Omer SB. Vaccine hesitancy: Causes, consequences, and a call to action. Vaccine. 2015;33 Suppl 4:D66-D71. doi:10.1016/j.vaccine.2015.09.035
    2. Poland GA, Jacobson RM. The clinician's guide to the anti-vaccinationists' galaxy. Hum Immunol. 2012;73(8):859-866. doi:10.1016/j.humimm.2012.03.014
    3. Andre FE, Booy R, Bock HL, et al. Vaccination greatly reduces disease, disability, death and inequity worldwide. Bull World Health Organ. 2008;86(2):140-146. doi:10.2471/blt.07.040089
    4. Aruru M, Truong HA, Clark S. Pharmacy Emergency Preparedness and Response (PEPR): a proposed framework for expanding pharmacy professionals' contributions to emergency preparedness and response during the COVID-19 pandemic and beyond. Res Social Adm Pharm. 2020;S1551-7411(20)30323-5. doi:10.1016/j.sapharm.2020.04.002
    5. Kennedy A, Lavail K, Nowak G, et al. Confidence about vaccines in the United States: understanding parents' perceptions. Health Aff (Millwood). 2011;30(6):1151-1159. doi:10.1377/hlthaff.2011.0396
    6. Mallory ML, Lindesmith LC, Baric RS. Vaccination-induced herd immunity: Successes and challenges. J Allergy Clin Immunol. 2018;142(1):64-66. doi:10.1016/j.jaci.2018.05.007
    7. Taddio A, McMurtry CM, Shah V, et al. Reducing pain during vaccine injections: clinical practice guideline. CMAJ. 2015;187(13):975-982. doi:10.1503/cmaj.150391
    8. Omer SB, Orenstein WA, Koplan JP. Go big and go fast—vaccine refusal and disease eradication. N Engl J Med. 2013;368(15):1374-1376. doi:10.1056/NEJMp1300765
    9. Habersaat KB, Jackson C. Understanding vaccine acceptance and demand—and ways to increase them. Bundesgesundheitsblatt Gesundheitsforschung Gesundheitsschutz. 2020;63(1):32-39. doi:10.1007/s00103-019-03063-0
    10. Centers for Disease Control and Prevention. Measles cases and outbreaks. Accessed August 21, 2026. https://www.cdc.gov/measles/data-research/index.html
    11. Nour R. A systematic review of methods to improve attitudes towards childhood vaccinations. Cureus. 2019;11(7):e5067. doi:10.7759/cureus.5067
    12. Report of the SAGE Working Group on Vaccine Hesitancy. 2014. Accessed August 21, 2026. https://www.medbox.org/document/report-of-the-sage-working-group-on-vaccine-hesitancy
    13. Butler R, MacDonald NE; SAGE Working Group on Vaccine Hesitancy. Diagnosing the determinants of vaccine hesitancy in specific subgroups: The guide to Tailoring Immunization Programmes (TIP). Vaccine. 2015;33(34):4176-4179. doi:10.1016/j.vaccine.2015.04.038
    14. WHO EURO Working Group on Vaccine Communications. Istanbul, Turkey. October 13-14, 2011.
    15. MacDonald NE; SAGE Working Group on Vaccine Hesitancy. Vaccine hesitancy: Definition, scope and determinants. Vaccine. 2015;33(34):4161-4164. doi:10.1016/j.vaccine.2015.04.036
    16. World Health Organization. Behavioural and Social Drivers of Vaccination: Tools and Practical Guidance for Achieving High Uptake. World Health Organization; 2022. Accessed August 21, 2026. https://www.who.int/publications/i/item/9789240049680
    17. MacDonald NE, Dubé E. Promoting immunization resiliency in the digital information age. Can Commun Dis Rep. 2020;46(1):20-24. doi:10.14745/ccdr.v46i01a04
    18. Meppelink CS, Smit EG, Fransen ML, Diviani N. ‘I was right about vaccination’: Confirmation bias and health literacy in online health information seeking. J Health Commun. 2019;24(2):129-140. doi:10.1080/10810730.2019.1583701
    19. Paterson P, Chantler T, Larson HJ. Reasons for non-vaccination: Parental vaccine hesitancy and the childhood influenza vaccination school pilot programme in England. Vaccine. 2018;36(36):5397-5401. doi:10.1016/j.vaccine.2017.08.016
    20. U.S. Food and Drug Administration. Vaccines licensed for use in the US. Accessed August 20, 2026. https://www.fda.gov/vaccines-blood-biologics/vaccines/vaccines-licensed-use-united-states
    21. Children’s Hospital of Philadelphia Vaccine Education Center. Vaccine ingredients: gelatin. Updated June 18, 2026. Accessed August 21, 2026. https://www.chop.edu/vaccine-education-center/vaccine-safety/vaccine-ingredients/gelatin
    22. Leask J, Kinnersley P, Jackson C, et al. Communicating with parents about vaccination: a framework for health professionals. BMC Pediatr. 2012;12:154. doi:10.1186/1471-2431-12-154
    23. Paterson P, Meurice F, Stanberry LR, et al. Vaccine hesitancy and healthcare providers. Vaccine. 2016;34(52):6700-6706. doi:10.1016/j.vaccine.2016.10.042
    24. Gust DA, Darling N, Kennedy A, Schwartz B. Parents with doubts about vaccines: which vaccines and reasons why. Pediatrics. 2008;122(4):718-725. doi:10.1542/peds.2007-0538
    25. Fogarty CT, Crues L. How to talk to reluctant patients about the flu shot. Fam Pract Manag. 2017;24(5):6-8.
    26. Six common misconceptions about vaccination—and how to respond to them. Int J Trauma Nurs. 1998;4(3):109-112. doi:10.1016/S1075-4210(98)90079-7
    27. Centers for Disease Control and Prevention. How Vaccines Strengthen Your Baby’s Immune System. Published July 10, 2017. Accessed August 21, 2026. https://stacks.cdc.gov/view/cdc/143124
    28. Halperin B, Melnychuk R, Downie J, Macdonald N. When is it permissible to dismiss a family who refuses vaccines? Legal, ethical and public health perspectives. Paediatr Child Health. 2007;12(10):843-845. doi:10.1093/pch/12.10.843
    29. Tafuri S, Gallone MS, Cappelli MG, et al. Addressing the anti-vaccination movement and the role of HCWs. Vaccine. 2014;32(38):4860-4865. doi:10.1016/j.vaccine.2013.11.006
    30. O’Leary ST, Opel DJ, Cataldi JR, Hackell JM; Committee on Infectious Diseases; Committee on Practice and Ambulatory Medicine; Committee on Bioethics. Strategies for improving vaccine communication and uptake. Pediatrics. 2024;153(3):e2023065483. doi:10.1542/peds.2023-065483
    31. Gagneur A, Gosselin V, Dubé È. Motivational interviewing: A promising tool to address vaccine hesitancy. Vaccine. 2018;36(44):6553-6555.
    32. Wibowo E, Wassersug RJ, Robinson JW, et al. An educational program to help patients manage androgen deprivation therapy side effects: feasibility, acceptability, and preliminary outcomes. Am J Mens Health. 2020;14(1):1557988319898991. doi:10.1177/1557988319898991
    33. Spencer JC, Wheeler SB. A systematic review of motivational interviewing interventions in cancer patients and survivors. Patient Educ Couns. 2016;99(7):1099-1105. doi:10.1016/j.pec.2016.02.003
    34. Gong Z, Veuthey J, Han Z. What makes people intend to take protective measures against influenza? Perceived risk, efficacy, or trust in authorities. Am J Infect Control. 2020;S0196-6553(20)30755-0. doi:10.1016/j.ajic.2020.07.029
    35. Krueger BS, Hutchison ML, Bodo EC, et al. Science-based communication to decrease disparities in adult pneumococcal vaccination rates. J Am Pharm Assoc (2003). 2020;S1544-3191(20)30263-6. doi:10.1016/j.japh.2020.05.020
    36. Lewandowsky S, Ecker UKH, Seifert CM, et al. Misinformation and its correction: continued influence and successful debiasing. Psychol Sci Public Interest. 2012;13:106-131.
    37. Dubé E, Gagnon D, Vivion M. Optimizing communication material to address vaccine hesitancy. Can Commun Dis Rep. 2020;46(2-3):48-52. doi:10.14745/ccdr.v46i23a05
    38. Ecker UK, Lewandowsky S, Tang DT. Explicit warnings reduce but do not eliminate the continued influence of misinformation. Mem Cognit. 2010;38(8):1087-1100. doi:10.3758/MC.38.8.1087
    39. van der Linden S. Misinformation: susceptibility, spread, and interventions to immunize the public. Nat Med. 2022;28:460-467. doi:10.1038/s41591-022-01713-6
    40. Swire-Thompson B, DeGutis J, Lazer D. Searching for the backfire effect: measurement and design considerations. J Appl Res Mem Cogn. 2020;9(3):286-299. doi:10.1016/j.jarmac.2020.06.006
    41. MacDonald NE, Butler R, Dubé E. Addressing barriers to vaccine acceptance: an overview. Hum Vaccin Immunother. 2018;14(1):218-224. doi:10.1080/21645515.2017.1394533
    42. Drozd EM, Miller L, Johnsrud M. Impact of pharmacist immunization authority on seasonal influenza immunization rates across states. Clin Ther. 2017;39(8):1563-1580.e17. doi:10.1016/j.clinthera.2017.07.004
    43. Alsabbagh MW, Church D, Wenger L, et al. Pharmacy patron perspectives of community pharmacist administered influenza vaccinations. Res Social Adm Pharm. 2019;15(2):202-206. doi:10.1016/j.sapharm.2018.04.015
    44. Jacobsen Vann JC, Jacobson RM, Coyne-Beasley T, et al. Patient reminder and recall interventions to improve immunization rates. Cochrane Database Syst Rev. 2018;1:CD003941.

    Immunization: Our Best Shot – Tips and Tools to Vaccinate Older Adults – RECORDED WEBINAR

    About this Course

    This course is a recorded (home study version) of the 2024 CE Finale Encore Webinars.


    Learning Objectives

    Upon completion of this application based CE Activity, a pharmacist will be able to:

    1.     RECOGNIZE appropriate vaccine recommendations for the older adult population
    2.      IDENTIFY potential barriers to vaccinations
    3.     ANALYZE current methods used to improve vaccination rates
    4.     DISCUSS ways to improve vaccine compliance in your patient population

    Release and Expiration Dates

    Released:  December 13, 2024
    Expires:  December 13, 2027

    Course Fee

    $10 Pharmacist

    ACPE UAN

    0009-0000-24-047-H06-P

    Session Code

    24RW47-FXY23

    Accreditation Hours

    1.0 hours of CE

    Additional Information


    How to Complete Evaluation:  When you are ready to submit quiz answers, go to the BLUE take test/evaluation button.  Don't forget to use the session code above, or that was sent to you in your confirmation email NOT the one on the presentation!

    Accreditation Statement

    The University of Connecticut School of Pharmacy is accredited by the Accreditation Council for Pharmacy Education as a provider of continuing pharmacy education.

    Pharmacists and Pharmacy Technicians are eligible to participate in this application-based activity and will receive up to 1.0 CE Hours (or 0.1 CEUs)  for completing the activity ACPE UAN 0009-0000-24-047-H06-P, passing the quiz with a grade of 70% or better, and completing an online evaluation. Statements of credit are available via the CPE Monitor online system and your participation will be recorded with CPE Monitor within 72 hours of submission.

    Grant Funding

    There is no grant funding for this activity.

    Faculty

    Jack Vinciguerra, PharmD
    Express Scripts
    St Louis, MO

    Faculty Disclosure

    In accordance with the Accreditation Council for Pharmacy Education (ACPE) Criteria for Quality and Interpretive Guidelines, The University of Connecticut School of Pharmacy requires that faculty disclose any relationship that the faculty may have with commercial entities whose products or services may be mentioned in the activity.

    • Dr. Vinciguerra has no financial relationships with ineligible companies.

    Disclaimer

    The material presented here does not necessarily reflect the views of The University of Connecticut School of Pharmacy or its co-sponsor affiliates. These materials may discuss uses and dosages for therapeutic products, processes, procedures and inferred diagnoses that have not been approved by the United States Food and Drug Administration. A qualified health care professional should be consulted before using any therapeutic product discussed. All readers and continuing education participants should verify all information and data before treating patients or employing any therapies described in this continuing education activity.

    Content

    Handouts

    Post Test

    Immunization: Our Best Shot - Tips and Tools to Vaccinate Older Adults

    After completing this continuing education activity, pharmacists will be able to

    • Recognize appropriate vaccine recommendations for the older adult population
    • Identify potential barriers to vaccinations
    • Analyze current methods used to improve vaccination rates
    • Discuss ways to improve vaccine compliance in your patient population

    1. How many vaccines does the CDC strongly recommend for older adults?
    a. Just two: influenza and COVID
    b. Three: influenza, COVID, and RSV
    c. Six-ish!!! (It depends)

    2. New patient, ES, age 60, has recently moved to Connecticut from Ontario, Canada. The patient reports receiving Zostavax 1 month ago. Which of the following recommendations regarding the administration of Shingrix is correct?
    a. Shingrix is contraindicated in those who have received Zostavax.
    b. It is recommended to administer the Shingrix vaccine immediately.
    c. It is recommended to wait at least 8 weeks after receiving Zostavax.

    3. Which of the following situations might act as a barrier to vaccine uptake in older adults?
    a. The nearest pharmacy and healthcare facilities are miles away and not on a bus route.
    b. Other people at the senior center have had COVID, the flu, or shingles recently and been quite ill.
    c. Pharmacy staff asks pleasantly and often if they might be ready to be vaccinated.

    4. Which of the following is an example of a contextual influence as defined by the Vaccine Hesitancy Determinants Matrix?
    a. Personal experience with vaccinations
    b. Communication and media environment
    c. Mode of vaccine administration

    5. Which of these programs is a federal program that uses digital outreach, television, print, and radio to decrease vaccine hesitancy among older adults?
    a. Risk Less, Do More
    b. It’s a Sure Shot
    c. No Shot in the Dark

    6. You’re monitoring vaccine uptake in your community and it is alarmingly low. You decide to use the S-H-A-R-E method of encouraging vaccine uptake. What does the R stand for?
    a. Remind patients that getting a vaccine-preventable disease is costly
    b. Remind patients that vaccines protect them and their loved ones
    c. Remind patients that you have the vaccines they need in stock

    Share the tailored reasons why the recommended vaccine is right for the patient
    Highlight positive experiences with vaccines (anecdotal or in practice) to strengthen confidence
    Address patient questions and concerns about the vaccine
    Remind patients that vaccines protect them and their loved ones
    Explain the potential costs of getting the disease

    VIDEO

    Stop the Bite: Uncover the Answers to Malaria and Dengue Fever

    Learning Objectives


    After completing this knowledge-based continuing education activity, pharmacists will be able to

    • RECALL symptoms associated with dengue fever and malaria
    • DESCRIBE emerging information about dengue and malaria vaccines
    • ASSOCIATE dengue fever and malaria vaccines for specific patients

    After completing this knowledge-based continuing education activity, pharmacy technicians will be able to

    • RECALL symptoms associated with dengue fever and malaria
    • DESCRIBE emerging information about dengue and malaria vaccines
    • MATCH  dengue fever and malaria vaccines by storage requirements

    Cartoon representation of a mosquito.


    Release Date: February 28, 2026

    Expiration Date: February 28, 2029

    Course Fee

    Pharmacists: $4

    Pharmacy Technicians: $2

    There is no grant funding for this CE activity

    ACPE UANs

    Pharmacist: 0009-0000-26-007-H06-P

    Pharmacy Technician: 0009-0000-26-007-H06-T

    Session Codes

    Pharmacist:  23YC02-MTX44

    Pharmacy Technician:  23YC02-XTM62

    Accreditation Hours

    0.5 hours of CE

    Accreditation Statements

    The University of Connecticut School of Pharmacy is accredited by the Accreditation Council for Pharmacy Education as a provider of continuing pharmacy education.  Statements of credit for the online activity ACPE UAN 0009-0000-26-007-H06-P/T  will be awarded when the post test and evaluation have been completed and passed with a 70% or better. Your CE credits will be uploaded to your CPE monitor profile within 2 weeks of completion of the program.


    Disclosure of Discussions of Off-label and Investigational Drug Use

    The material presented here does not necessarily reflect the views of The University of Connecticut School of Pharmacy or its co-sponsor affiliates. These materials may discuss uses and dosages for therapeutic products, processes, procedures and inferred diagnoses that have not been approved by the United States Food and Drug Administration. A qualified health care professional should be consulted before using any therapeutic product discussed. All readers and continuing education participants should verify all information and data before treating patients or employing any therapies described in this continuing education activity.

    Faculty

    Jessica Bylyku, BS
    PharmD Candidate 2024
    UConn School of Pharmacy
    Storrs, CT


    Kelsey Giara, PharmD
    Freelance Medical Writer
    Pelham, NH


    Melody White
    PharmD Candidate 2025
    UConn School of Pharmacy
    Storrs, CT

    Faculty Disclosure

    In accordance with the Accreditation Council for Pharmacy Education (ACPE) Criteria for Quality and Interpretive Guidelines, The University of Connecticut School of Pharmacy requires that faculty disclose any relationship that the faculty may have with commercial entities whose products or services may be mentioned in the activity.

    Dr. Giara, Jessica Bykylu and Melody White do not have any relationships with ineligible companies and therefore have nothing to disclose.


    ABSTRACT

    Malaria and dengue (pronounced deng-ee) fever are not new diseases, but given the emergence of new vaccines, it is critical that pharmacists and pharmacy technicians increase their familiarity with them. These illnesses are both transmitted by mosquitos, but malaria is caused by Plasmodium parasites while dengue fever is a viral disease caused by dengue virus. The United States is not a malaria- or dengue-endemic country, but travel to other countries puts people at risk of these conditions. Pharmacy teams should be prepared to identify potential cases and refer patients for appropriate vaccination or treatment when appropriate.

    CONTENT

    Content

    INTRODUCTION

    Malaria cases in 2020 totaled an estimated 241 million, leading to more than 600,000 deaths, mostly in Africa.1 Direct costs of malaria prevention and treatment in the United States (U.S.) total about $12 billion annually, excluding the toll it takes on affected individuals and their families.1 The World Health Organization (WHO) reports that between 100 to 400 million people are infected with dengue fever each year.2 About 80% of cases are mild and asymptomatic, but dengue fever can progress to “severe dengue,” which is classified as a medical emergency requiring immediate medical care.2,3


    Mosquitos, Malaria, and Dengue – Oh My!

    Plasmodium parasites—common to tropical areas (e.g., Africa, South America, the Caribbean Islands, South Asia)—cause malaria.1 Most commonly, malaria is transmitted through the bite of infected mosquitoes, specifically the Anopheles species, during local outbreaks. There is also a term coined “airport malaria,” describing disease that is transported from an infected country to a non-infected country.4 Congenital malaria occurs when mothers infected with the disease transmit parasites to the child during pregnancy or birth.4 Although rare, prompt diagnosis is crucial to ensure infected neonates and infants survive. Transfusion-transmitted malaria is also possible where blood recipients can be infected with malaria accidently. There are no approved tests to screen blood donations for malaria, only questioning of prospective donors.4 Although rare in the U.S., complications are severe and organizations should take action to prevent potentially-infected individuals from donating.


    Patients with malaria generally present with fever, chills/sweating, headache, and weakness within 10 to 15 days of infection.5 Diarrhea, abdominal pain, and cough are also possible. As malaria progresses, patients develop a classic paroxysm (i.e., symptoms that come and go) comprising three stages6:

    1. 15-to-60-minute cold stage (shivering and feeling cold)
    2. 2-to-6-hour hot stage (fevers up to nearly 106°F; flushed, dry skin; and often headache, nausea, and vomiting)
    3. 2-to-4-hour sweating stage (rapid drop in fever and sweating)


    Missed or delayed malaria diagnosis can lead to potentially fatal complicated disease manifesting as severe anemia, renal failure, altered consciousness, and multisystem organ failure.6 Clinicians diagnose malaria via a blood smear test. Although rapid and polymerase chain reaction (PCR) tests are available, medical professionals confirm diagnosis through microscopic blood smear examination.7


    Dengue fever is a viral disease caused by mosquitos—mainly females from the Aedes aegypti and Ae. albopictus species—carrying dengue virus (also known as DENV).2 Four DENV serotypes exist, so it is possible to contract the disease four times. The virus can be transmitted through mosquito bite, from pregnant mother to child, and via infected blood products/organ donations and infusions. Transovarial transmission within mosquitoes (from parent to offspring) has also been noted.2


    Most dengue cases are asymptomatic or mild and fatalities are rare, but increasing severity can be life-threatening.2,3 Providers should suspect dengue when a high fever (104°F or greater) is accompanied by any two of the following symptoms2,3:

    • severe headache
    • pain behind the eyes
    • muscle/joint/bone pain
    • nausea/vomiting
    • swollen glands
    • rash


    This febrile phase lasts about 2 to 7 days, and most people recover after about a week.2,3 Severe dengue is a potentially fatal complication due to plasma leakage, fluid accumulation, respiratory distress, severe bleeding, or organ impairment.2 Patients are at risk of severe dengue symptoms about 3 to 7 days after initial symptoms appear.2 As fever drops to below 100°F, patients enter a “critical phase” for 24 to 48 hours. Warning signs to watch for during the critical phase include2

    • severe abdominal pain
    • rapid breathing
    • blood in vomit, stool, gums, or nose
    • persistent vomiting
    • restlessness/fatigue


    Clinicians use commercially available PCR or rapid diagnostic tests to confirm dengue diagnosis.2 Enzyme-linked immunosorbent assays are also available to confirm active or previous infections.


    Global Implications  

    Beyond clinical symptoms, malaria and dengue fever inflict social and financial loss for diagnosed individuals and the countries tasked with treating affected populations. Some examples of the indirect burden of these mosquito-borne diseases include1

    • expenses for traveling and receiving treatment
    • absences from work/school
    • burial expenses in cases of death
    • purchases of medication and supplies
    • public health interventions (e.g., insecticide spraying, bed nets)
    • opportunity loss for tourism


    Populations at increased risk of contracting malaria include infants, children younger than 5 years, pregnant women, immunosuppressed patients, and migrant workers or traveling populations.5 There is also concern that certain mosquitoes are resistant to insecticide, and by migrating throughout the world they can spread malaria to urban populations.8 Researchers have identified Anopheles gambiae mosquitoes, originally found in India and Iran, as insecticide-resistant. These are projected to put nearly 126 million people in African cities at risk for contracting malaria.8


    Populations most vulnerable to contracting dengue fever include pregnant women and children.3 Many asymptomatic or mild dengue cases go unreported. WHO reports most of the dengue burden occurs in Asia, and the number of cases has steadily increased to just over 5 million in 2019.2


    PREVENTION AND TREATMENT

    Following prevention and treatment guidelines are crucial to lower transmission rates of dengue fever and malaria.


    Dengue Fever

    WHO states that countries should be aware of community mosquito presence and develop active mosquito and virus surveillance to prevent further disease spread.2 They should also remain knowledgeable about the number of infected individuals.


    The dengue vaccine (Dengvaxia) has been licensed in other countries since 2015, but the U.S. Food and Drug Administration (FDA) approved the vaccine in 2019.2 WHO recommends people aged 9 to 45 years be vaccinated, but Dengvaxia is only FDA approved for patients 9 to 16 years old with a history of previous infection who live in high-risk areas. As a live-attenuated vaccine, it is contraindicated in individuals with severe immunodeficiency.2 Children receiving Dengvaxia need a 3-dose series administered subcutaneously with doses separated by 6 months.9 Providers should store the vaccine in the refrigerator.10 After reconstitution, it should be administered immediately or stored in the refrigerator and used within thirty minutes.


    WHO and the FDA only recommend Dengvaxia for patients with a history of dengue virus infection.10,11 This is based on clinical trial evidence that the vaccine is efficacious and safe in patients with a history of previous DENV infection because a subsequent infection is more serious and life-threatening than the first.11 They also advise countries using the vaccine to control viral spread to implement pre-vaccination screening to confirm previous infection.


    As no dengue-specific treatment is available, providers should treat infected patients symptomatically with acetaminophen, rest, and fluids.2 Patients with dengue fever should avoid non-steroidal anti-inflammatory drugs (e.g., ibuprofen, aspirin) because they thin the blood. Given the risk of hemorrhage in this disease, blood thinners may exacerbate the problem.2


    Malaria

    WHO recommends that countries engage in vector control and surveillance for the spread of malarial disease.5 Malaria vaccines have been in development for decades, but no malaria vaccine is available in the U.S.12 In 2021, however, WHO recommended a new malaria vaccine (Mosquirix) for children aged older than 5 months who live in areas with moderate to high transmission of P. falciparum.13 The vaccine is only recommended for children as malaria is one of the main killers of children younger than 5 years in countries with moderate or high rates of malaria.14 WHO also recommends giving the vaccine seasonally in countries where malaria transmission is high during certain seasons.13


    Initial Mosquirix pilot studies are ongoing, and more widespread vaccine rollout is expected in 2023. For now, people in the U.S. traveling to malaria-endemic countries continue to use oral medications as chemoprophylaxis (i.e., to prevent the disease), including atovaquone/proguanil, chloroquine, doxycycline, mefloquine, primaquine, and tafenoquine.15


    Clinicians administer Mosquirix as a 4-dose schedule.16 The vaccine’s adverse effects are pain and swelling at the injection site and fever.17 Providers should store the vaccine in the refrigerator. After reconstitution it should be administered immediately or stored in the refrigerator and used within 6 hours.16


    Malaria treatment involves the use of antimalarial drugs based on four main factors15:

    • Infection severity: Malaria infection is either considered uncomplicated (effectively treated with oral antimalarials) or severe (requiring aggressive intravenous antimalarial therapy).
    • Infecting Plasmodium species: P. falciparum and P. knowlesi infections can cause rapidly progressive severe illness or death, necessitating urgent therapy initiation, while other species are less likely to cause severe disease. P. vivax and P. ovale infections also require treatment for hypnozoites (parasites that lay dormant in the liver and then re-awaken to become active infectants).
    • Drug susceptibility: In addition to disease severity differences, Plasmodium species also have different drug susceptibilities, so providers select an antimalarial therapy based on the species of the infecting parasite. If the species cannot be determined, patients must initiate antimalarial treatment against chloroquine-resistant P. falciparum as soon as possible.
    • Previous antimalarial use: Patients using antimalarial medication as chemoprophylaxis, should not receive that same drug or drug combination to treat malaria infection unless no other options are available.


    CONCLUSION

    Pharmacists and pharmacy technicians should be familiar with the signs and symptoms of malaria and dengue fever to inform patients when these conditions are suspected and about their appropriate treatment. Pharmacy teams who suspect a case of malaria or dengue fever should refer patients for medical attention and contact their local or state health department.


    Pharmacist Post Test (for viewing only)

    PHARMACIST POSTTEST

    Learning Objectives
    ● RECALL symptoms associated with dengue fever and malaria
    ● DESCRIBE emerging information about dengue and malaria vaccines
    ● OPTIMIZE dengue fever and malaria vaccines for specific patients

    1. Which of the following is TRUE?
    A. Dengue fever symptoms are always severe and most patients die
    B. Malaria presents as a cold stage, hot stage, and sweating stage
    C. Pain behind the eyes is a warning sign for malaria

    2. Which of the following is TRUE regarding the malaria vaccine?
    A. WHO recommends it for children 5 months and older who live in endemic areas
    B. It is FDA approved for patients 9 to 16 years old with a history of previous infection
    C. Clinicians administer it as a 3-dose series with each dose separated by 6 months

    3. A patient comes to the pharmacy indicating she and her family are being transferred to a country where dengue is common. She wants to have her three children who are ages 3, 5, and 7 vaccinated for dengue before they move. What is the BEST thing to tell her?
    A. We should schedule your children to be vaccinated about six weeks before you plan to move so they develop antibodies before you actually relocate.
    B. We only vaccinate children who have already had dengue because a second infections is more serious and life-threatening than the first.
    C. Wait until you arrive in the country because they will want to do pre-vaccination screening to confirm your children have not been infected previously.

    Pharmacy Technician Post Test (for viewing only)

    PHARMACY TECHNICIAN POSTTEST

    Learning Objectives
    ● RECALL symptoms associated with dengue fever and malaria
    ● DESCRIBE emerging information about dengue and malaria vaccines
    ● CLASSIFY dengue fever and malaria vaccines by storage requirements

    1. Which of the following is TRUE?
    A. Dengue fever symptoms are always severe and most patients die
    B. Malaria presents as a cold stage, hot stage, and sweating stage
    C. Pain behind the eyes is a warning sign for malaria

    2. Which of the following is TRUE regarding the malaria vaccine?
    A. WHO recommends it for children 5 months and older who live in endemic areas
    B. It is FDA approved for patients 9 to 16 years old with a history of previous infection
    C. Clinicians administer it as a 3-dose series with each dose separated by 6 months

    3. A patient at your pharmacy is receiving the dengue fever vaccine. The patient’s mother asks you if they can use the restroom before the pharmacist administers the vaccine. You look over to see that the pharmacist has just finished reconstituting Dengvaxia for this patient. Which of the following is the BEST response?
    A. Advise the mother not to leave the pharmacy waiting area, as the pharmacist needs to administer this vaccine immediately or it will expire
    B. Advise the mother to take her daughter to the restroom, and the pharmacist can administer this vaccine within 6 hours as long as it’s refrigerated
    C. Advise the mother to take her daughter to the restroom but return within 30 minutes, and ensure the pharmacist refrigerates the reconstituted vaccine

    References

    Full List of References

    REFERENCES

    1. Centers for Disease Control and Prevention. Malaria’s Impact Worldwide. Updated December 16, 2021. Accessed November 30, 2022. https://www.cdc.gov/malaria/malaria_worldwide/impact.html
    2. World Health Organization. Dengue and severe dengue. Updated January 10, 2022. Accessed November 1, 2022. https://www.who.int/news-room/fact-sheets/detail/dengue-and-severe-dengue
    3. Centers for Disease Control and Prevention. Dengue. Updated August 3, 2022. Accessed November 1, 2022. https://www.cdc.gov/dengue/index.html
    4. Centers for Disease Control and Prevention. Parasites – Malaria. Updated August 19, 2022. Accessed November 1, 2022. https://www.cdc.gov/parasites/malaria/index.html
    5. World Health Organization. Malaria. Updated July 26, 2022. Accessed November 1, 2022. https://www.who.int/news-room/fact-sheets/detail/malaria
    6. Crutcher JM, Hoffman SL. Chapter 83: Malaria. In: Baron S, ed. Medical Microbiology. 4th ed. University of Texas Medical Branch at Galveston; 1996. Accessed November 1, 2022. https://www.ncbi.nlm.nih.gov/books/NBK8584/
    7. Stanford Health Care. Malaria diagnosis. Accessed November 1, 2022. https://stanfordhealthcare.org/medical-conditions/primary-care/malaria/diagnosis.html
    8. American Society of Tropical Medicine and Hygiene. Invasive mosquitos – Anopheles stephensi in Ethiopia. November 1, 2022. Accessed November 30, 2022. https://astmhpressroom.wordpress.com/annual-meeting-2022/anopheles-stephensi-in-ethiopia/
    9. Centers for Disease Control and Prevention. Dengue Vaccine VIS. Updated December 17, 2021. Accessed November 29, 2022. https://www.cdc.gov/vaccines/hcp/vis/vis-statements/dengue.html
    10. Dengvaxia [prescribing information]. Sanofi Pasteur; 2019.
    11. Ask the Experts: Dengue. Immunize.org. Updated February 16, 2022. Accessed November 21, 2022. https://www.immunize.org/askexperts/experts_dengue.asp
    12. Centers for Disease Control and Prevention. Malaria: Vaccines. Updated October 7, 2021. Accessed December 2, 2022. https://www.cdc.gov/malaria/malaria_worldwide/reduction/vaccine.html
    13. Q&A on RTS,S malaria vaccine. World Health Organization. Updated April 21, 2022. Accessed November 30, 2022. https://www.who.int/news-room/questions-and-answers/item/q-a-on-rts-s-malaria-vaccine
    14. UNICEF. Millions more children to benefit from malaria vaccine as UNICEF secures supply. August 16, 2022. Accessed November 22, 2022. https://www.unicef.org/press-releases/millions-more-children-benefit-malaria-vaccine-unicef-secures-supply
    15. Centers for Disease Control and Prevention. Treatment of Malaria: Guidelines for Clinicians (United States). Updated September 30, 2022. Accessed November 30, 2022 https://www.cdc.gov/malaria/diagnosis_treatment/clinicians1.html
    16. Mosquirix (Product Information). European Medicines Agency. Updated January 8, 2022. Accessed November 30, 2022. https://www.ema.europa.eu/en/documents/outside-eu-product-information/mosquirix-product-information_en.pdf
    17. World Health Organization. Malaria: The malaria vaccine implementation programme (MVIP). March 2, 2020. Accessed November 30, 2022. https://www.who.int/news-room/questions-and-answers/item/malaria-vaccine-implementation-programme


    Only Skin Deep: The Pharmacist’s Guide to Intradermal Vaccine Administration 2025

    Learning Objectives


    After completing this knowledge-based continuing education activity, pharmacists and pharmacy technicians  will be able to

    • DISCUSS the potential benefits of intradermal vaccine delivery
    • IDENTIFY how to administer intradermal injections


      Release Date: December 5, 2025

      Expiration Date: December 5, 2028

      Course Fee

      FREE

      There is no grant funding for this CE activity

      ACPE UANs

      Pharmacist: 0009-0000-25-073-H06-P

      Pharmacy Technician: 0009-0000-25-073-H06-T

      Session Codes

      Pharmacist: 22YC66-BXV44

      Pharmacy Technician:  22YC66-VBT84

      Accreditation Hours

      0.5 hours of CE

      Accreditation Statements

      The University of Connecticut School of Pharmacy is accredited by the Accreditation Council for Pharmacy Education as a provider of continuing pharmacy education.  Statements of credit for the online activity ACPE UAN 0009-0000-25-073-H06-P/T  will be awarded when the post test and evaluation have been completed and passed with a 70% or better. Your CE credits will be uploaded to your CPE monitor profile within 2 weeks of completion of the program.


      Disclosure of Discussions of Off-label and Investigational Drug Use

      The material presented here does not necessarily reflect the views of The University of Connecticut School of Pharmacy or its co-sponsor affiliates. These materials may discuss uses and dosages for therapeutic products, processes, procedures and inferred diagnoses that have not been approved by the United States Food and Drug Administration. A qualified health care professional should be consulted before using any therapeutic product discussed. All readers and continuing education participants should verify all information and data before treating patients or employing any therapies described in this continuing education activity.

      Faculty

      Kelsey Giara, PharmD
      Freelance Medical Writer
      Pelham, NH

      Faculty Disclosure

      In accordance with the Accreditation Council for Pharmacy Education (ACPE) Criteria for Quality and Interpretive Guidelines, The University of Connecticut School of Pharmacy requires that faculty disclose any relationship that the faculty may have with commercial entities whose products or services may be mentioned in the activity.

      Dr. Giara does not have any relationships with ineligible companies and therefore has nothing to disclose.


      ABSTRACT

      Researchers have studied intradermal vaccination for various diseases for over a decade, so it was only a matter of time before pharmacists would be asked to learn this route of administration. This is arguably the most challenging method of vaccine administration, and inaccurate technique could render an immunization ineffective. Given the need for intradermal administration of the monkeypox vaccine, pharmacists should be prepared to offer intradermal vaccination to eligible individuals to increase immunization rates, slow viral spread, and improve outcomes for affected individuals.

      CONTENT

      Content

      INTRODUCTION

      Major developments to vaccines and vaccine administration in recent years have demanded a great deal from pharmacists. The coronavirus disease-19 pandemic asked us to fight misinformation and vaccine hesitancy to educate the public about a new virus and new vaccine technology. We’ve been challenged to keep up with booster recommendations and the increased workflow that comes with vaccine administration. Many of us also taught our pharmacy technicians how to immunize.


      Now, with the emergence of monkeypox comes yet another new vaccine with an unfamiliar method of administration (see our FREE monkeypox activity for a more in-depth discussion about this virus). In August 2022, the United States (U.S.) declared monkeypox a public health emergency and ramped up efforts to vaccinate at-risk individuals subcutaneously (a method with which pharmacists are generally familiar).1 Shortly thereafter, the U.S. Food and Drug Administration (FDA) recognized that the country’s supply of monkeypox vaccine was unable to meet the current demand given the rapid spread of the virus.2 Administering the vaccine intradermally only requires one-fifth of the subcutaneous dose, so the FDA issued an emergency use authorization (EUA) allowing healthcare providers to use this method of administration. This effectively increased the total number of available doses by up to five-fold.2


      In September 2022, the U.S. Department of Health and Human Services authorized pharmacists, pharmacy interns, and pharmacy technicians, as appropriate, to administer monkeypox vaccines and therapeutics, under certain conditions.3 Pharmacists should be prepared to offer intradermal vaccination to eligible individuals to increase vaccination rates, slow viral spread, and improve outcomes both for this virus and any future viruses for which this applies.


      THE ROLE OF INTRADERMAL ADMINISTRATION

      Researchers have studied intradermal vaccination for a range of viral diseases, but only a few things are administered intradermally including4,5

      • tuberculosis skin testing
      • BCG (tuberculosis) vaccine
      • rabies vaccine
      • allergy skin testing


      Intradermal administration occurs in the dermis just below the epidermis (see Figure 1).4 The epidermis—the thinnest layer—is made up mostly of epithelial cells, but also contains melanocytes (pigment-producing cells), Merkel cells (for light-touch stimuli), and Langerhans cells (tissue-resident macrophages).5 The dermis is a thicker layer containing cells of the adaptive and innate immune systems including macrophages, mast cells, Langerhans cells, and dermal dendritic cells. Cells of the dermis are essential in processing incoming antigens to decide if they are harmful and activate the immune system accordingly.5


      Figure 1. Methods of Vaccine Administration


      High levels of antigen-presenting cells in the dermis induce a more potent immune response, making this an attractive (and potentially superior) vaccination site.5,6 This significant reactivity in the dermis also prompts a strong immune response to a smaller quantity of vaccine antigen—as little as one-fifth to one-tenth the dose—compared to intramuscular or subcutaneous administration.5,7 For this reason, intradermal administration is dose-sparing and potentially cost saving.5 Intradermal administration also avoids the rare risk of nerve, blood vessel, or joint space injury.7


      Clinical studies are evaluating intradermal delivery of other vaccines, but none are currently available in the U.S. aside from monkeypox under the recent EUA.5 In years past, an intradermal influenza vaccine was available, but the manufacturer stopped production after the 2017-2018 flu season for unknown reasons.8 Of all parenteral routes, intradermal injections have the longest absorption time due to the lack of blood vessels and muscle tissue in this area. This is attractive for sensitivity testing, as reactions are easier to visualize and assess for severity.4


      While intradermal administration is more efficient and cost-effective, it requires more skill and practice compared to subcutaneous or intramuscular administration.9 If incorrectly administered, the vaccine may enter the subcutaneous tissue instead and be ineffective because the dose is too small.


      INTRADERMAL ADMINISTRATION TECHNIQUE

      The most common intradermal injection sites are the volar aspect (inner surface) of the forearm and the upper back below the scapula (shoulder blade).4 Intradermal injection is not the best choice for every patient. Skin should be free of lesions, rashes, moles, or scars that could alter visual inspection of the injection site (or interpretation of test results, when applicable).4 In the case of the monkeypox vaccine, intradermal administration is only authorized for patients 18 years or older without a history of keloids (thick, raised scars).10


      Researchers have developed various devices for intradermal drug delivery, but in the absence of specialized devices, individuals can employ the Mantoux technique using a hypodermic needle.5 The Mantoux technique is named for French physician Charles Mantoux who used this method for tuberculosis testing in the early 1900s.11 The optimum needle size for this method is 26 to 27 gauge and ¼ to ½ inch long.4


      The Mantoux technique is new to pharmacists (we know because we could only find information about administration technique in nursing resources), so listen up, take notes, and remember that practice makes perfect4,10:

      • Inspect the injection site and select an area that is free from lesions, rashes, moles, or scars. Avoid vaccination in an area where there is a recent tattoo (less than one month old). If tattoos cover both arms, select an area without pigment (ink) if possible. If the tattoo is unavoidable, administer through it.
      • Clean the site with an alcohol or antiseptic swab using a firm, circular motion. Allow the site to dry completely to prevent alcohol from entering the tissue, which can cause stinging and irritation.
      • Using the nondominant hand, spread the skin taut at the injection site. Taut skin provides easy entrance for the needle. This is especially important in older individuals with less elastic skin.
      • Hold the syringe in the dominant hand between the thumb and forefinger at a 5- to 15-degree angle at the selected injection site with the bevel of the needle facing up.
      • Place the needle almost flat against the patient’s skin and insert the needle into the skin no more than 1/8-inch (about 3 mm) to cover the bevel. Keeping the bevel side up allows the needle to smoothly pierce the skin and deliver the medication to the dermis.
      • Once the needle is in place, use the thumb of the nondominant hand to slowly push the plunger to inject the medication.
      • Inspect the injection site for a bleb (small blister) which should appear under the skin. The presence of a bleb indicates that the medication is correctly placed in the dermis. The bleb is desired but not required, so if it doesn't appear, don't panic. Simply adjust your technique for next time.
      • Withdraw the needle at the same angle it was placed so as not to disturb the bleb and to minimize patient discomfort and tissue damage. Safely discard the syringe in a sharps container.


      More visual learners can find a video demonstrating how to administer a vaccine intradermally at https://www.youtube.com/watch?v=dRsQf_UHsjs. 


      CONCLUSION

      Vaccines work, that much we know. However, this is only true if they’re accessible, trusted, and used appropriately. Pharmacists can help promote access, education, and vaccine uptake if they have the knowledge and skills to do so. New vaccines and administration recommendations are challenging, but don’t let it get under your skin. We hope this quick-and-dirty overview of intradermal vaccines boosted your confidence and made it easier for you to give it a shot.


      Pharmacist Post Test (for viewing only)

      Only Skin Deep: The Pharmacist’s Guide to Intradermal Vaccine Administration
      25-073 Posttest

      Learning Objectives
      • DISCUSS the potential benefits of intradermal vaccine delivery
      • IDENTIFY how to administer intradermal injections

      *

      1. Which of the following is a benefit of intradermal vaccine delivery?
      A. It can deliver a larger vaccine dose
      B. It has the fastest rate of absorption
      C. It avoids the risk of nerve injury

      *

      2. Which of the following makes the dermis a good site for vaccine administration?
      A. High levels of Merkel cells
      B. High levels of antigen-presenting cells
      C. Low levels of Langerhans cells

      *

      3. About how far should you insert the needle to administer an intradermal injection via the Mantoux technique?
      A. 1/8-inch
      B. 1/4-inch
      C. 1/2-inch

      *

      4. Travis Barker comes into your pharmacy asking for an intradermal vaccine. You inspect his forearms full of tattoos and find a small space without ink. You complete intradermal administration and notice a small bubble form under his skin. What does this mean?
      A. You administered the vaccine subcutaneously
      B. You administered the vaccine too close to a tattoo
      C. You administered the vaccine correctly

      *

      5. Which of the following is appropriate technique for intradermal administration?
      A. Insert the needle at a 5- to 15-degree angle with the bevel facing up
      B. Pinch the skin between the thumb and forefinger of the nondominant hand
      C. Remove the needle slowly at a 45-degree angle to reduce discomfort

      Pharmacy Technician Post Test (for viewing only)

      Only Skin Deep: The Pharmacist’s Guide to Intradermal Vaccine Administration
      25-073 Posttest

      Learning Objectives
      • DISCUSS the potential benefits of intradermal vaccine delivery
      • IDENTIFY how to administer intradermal injections

      *

      1. Which of the following is a benefit of intradermal vaccine delivery?
      A. It can deliver a larger vaccine dose
      B. It has the fastest rate of absorption
      C. It avoids the risk of nerve injury

      *

      2. Which of the following makes the dermis a good site for vaccine administration?
      A. High levels of Merkel cells
      B. High levels of antigen-presenting cells
      C. Low levels of Langerhans cells

      *

      3. About how far should you insert the needle to administer an intradermal injection via the Mantoux technique?
      A. 1/8-inch
      B. 1/4-inch
      C. 1/2-inch

      *

      4. Travis Barker comes into your pharmacy asking for an intradermal vaccine. You inspect his forearms full of tattoos and find a small space without ink. You complete intradermal administration and notice a small bubble form under his skin. What does this mean?
      A. You administered the vaccine subcutaneously
      B. You administered the vaccine too close to a tattoo
      C. You administered the vaccine correctly

      *

      5. Which of the following is appropriate technique for intradermal administration?
      A. Insert the needle at a 5- to 15-degree angle with the bevel facing up
      B. Pinch the skin between the thumb and forefinger of the nondominant hand
      C. Remove the needle slowly at a 45-degree angle to reduce discomfort

      References

      Full List of References

      References

         
        REFERENCES
        1. U.S. Department of Health and Human Services. Biden-Harris Administration Bolsters Monkeypox Response; HHS Secretary Becerra Declares Public Health Emergency. August 4, 2022. Accessed October 26, 2022. https://www.hhs.gov/about/news/2022/08/04/biden-harris-administration-bolsters-monkeypox-response-hhs-secretary-becerra-declares-public-health-emergency.html
        2. U.S. Food and Drug Administration. Monkeypox Update: FDA Authorizes Emergency Use of JYNNEOS Vaccine to Increase Vaccine Supply. August 9, 2022. Accessed October 26, 2022. https://www.fda.gov/news-events/press-announcements/monkeypox-update-fda-authorizes-emergency-use-jynneos-vaccine-increase-vaccine-supply
        3. U.S. Department of Health and Human Services. Notice of Amendment to the January 1, 2016 Republished Declaration under the Public Readiness and Emergency Preparedness Act. October 3, 2022. Accessed October 26, 2022. https://public-inspection.federalregister.gov/2022-21412.pdf
        4. Administering intradermal medications. Open Resources for Nursing (Open RN). Accessed October 26, 2022. https://wtcs.pressbooks.pub/nursingskills/chapter/18-4-administering-intradermal-medication/
        5. Kim YC, Jarrahian C, Zehrung D, Mitragotri S, Prausnitz MR. Delivery systems for intradermal vaccination. Curr Top Microbiol Immunol. 2012;351:77-112.
        6. Hickling JK, Jones KR, Friede M, Zehrung D, Chen D, Kristensen D. Intradermal delivery of vaccines: potential benefits and current challenges. Bull World Health Organ. 2011;89(3):221-226.
        7. Brooks JT, Marks P, Goldstein RH, Walensky RP. Intradermal Vaccination for Monkeypox - Benefits for Individual and Public Health. N Engl J Med. 2022;387(13):1151-1153.
        8. Influenza vaccine. Aetna Clinical Policy Bulletins. Reviewed August 1, 2022. Accessed October 26, 2022. https://www.aetna.com/cpb/medical/data/1_99/0035.html
        9. Miller K. What Is an Intradermal Injection, the New Way the Monkeypox Vaccine Is Being Given? Prevention. August 12, 2022. Accessed October 26, 2022. https://www.prevention.com/health/health-conditions/a40869782/what-is-intradermal-injection/
        10. Centers for Disease Control and Prevention. JYNNEOS Smallpox and Monkeypox Vaccine:
        ALTERNATE REGIMEN Preparation and Administration Summary (Intradermal Administration). Updated September 27, 2022. Accessed October 26, 2022. https://www.cdc.gov/poxvirus/monkeypox/files/interim-considerations/guidance-jynneos-prep-admin-alt-dosing.pdf
        11. Kis EE, Winter G, Myschik J. Devices for intradermal vaccination. Vaccine. 2012;30(3):523-538.

        SPOTTED: MEASLES CASES RISING IN THE U.S.

        Learning Objectives


        After completing this application-based continuing education activity, pharmacists will be able to

        •        Identify the transmission of measles, its symptoms, and patients at higher risk for complications
        •        Describe the steps healthcare providers should take if measles is suspected or confirmed
        •        Determine appropriate patients for measles vaccination
        •        Apply patient counseling techniques regarding vaccine education

        After completing this application-based continuing education activity, pharmacy technicians will be able to

        •        Identify the symptoms of measles, its transmission, and patients at higher risk for complications
        •        Describe the steps healthcare providers should take if measles is suspected or confirmed
        •        Determine which patients might need vaccine education from the pharmacist

           Release Date

          Release Date: October 20, 2025

          Expiration Date: October 20, 2028

          Course Fee

          Pharmacists & Technicians:  FREE

          There is no funding for this CE.

          ACPE UANs

          Pharmacist: 0009-0000-25-060-H06-P

          Pharmacy Technician:  0009-0000-25-060-H06-T

          Session Codes

          Pharmacist: 25YC60-BFG57

          Pharmacy Technician: 25YC60-FBG75

          Accreditation Hours

          2.0 hours of CE

          Accreditation Statements

          The University of Connecticut School of Pharmacy is accredited by the Accreditation Council for Pharmacy Education as a provider of continuing pharmacy education.  Statements of credit for the online activity ACPE UAN 0009-0000-25-060-H06-P/T will be awarded when the post test and evaluation have been completed and passed with a 70% or better. Your CE credits will be uploaded to your CPE monitor profile within 2 weeks of completion of the program.


          Disclosure of Discussions of Off-label and Investigational Drug Use

          The material presented here does not necessarily reflect the views of The University of Connecticut School of Pharmacy or its co-sponsor affiliates. These materials may discuss uses and dosages for therapeutic products, processes, procedures and inferred diagnoses that have not been approved by the United States Food and Drug Administration. A qualified health care professional should be consulted before using any therapeutic product discussed. All readers and continuing education participants should verify all information and data before treating patients or employing any therapies described in this continuing education activity.

          Faculty

          Monica Holmberg, PharmD, BCPS
          Medical Writer
          Phoenix, AZ


          Faculty Disclosure

          In accordance with the Accreditation Council for Pharmacy Education (ACPE) Criteria for Quality and Interpretive Guidelines, The University of Connecticut School of Pharmacy requires that faculty disclose any relationship that the faculty may have with commercial entities whose products or services may be mentioned in the activity.

          Monica Holmberg has no relationships with ineligible companies.


          ABSTRACT

          Measles is a vaccine preventable disease, and yet its prevalence is rising. Shortly after the United States declared measles “eliminated” in 2000, measles vaccination rates began to drop. Reasons for decreased vaccination include misinformation regarding an association between measles vaccine and autism and interruption in routine care during the COVID-19 pandemic. As a result, measles cases continue to rise in unvaccinated patients. Post-exposure prophylaxis with a measles-containing vaccine or immunoglobulin may benefit some patients. Treatment for acute measles is mainly limited to supportive care and supplementation with vitamin A. Prevention with appropriate vaccination is the best method for minimizing the spread of measles. Vaccine hesitancy occurs worldwide and creates a challenge for obtaining adequate community vaccination rates for measles control. The pharmacy team can address vaccine hesitancy with education and empathy.

          CONTENT

          Content

          INTRODUCTION

          Measles is an extremely contagious viral illness caused by an enveloped RNA virus of the genus Morbillivirus and family Paramyxoviridae.1,2 Once a routine childhood disease, the development and consistent administration of a measles vaccine effectually eliminated measles in the United States (U.S.). Recent falling vaccination rates have led to the reemergence of measles.3


          Consider the following case: a man, Mike, and a toddler in a stroller, whose name is Bella, approach the pharmacy counter. He was shopping for nacho cheese flavored tortilla chips and saw the sign offering immunizations, which reminded him of his daughter’s recent well care visit. The pediatrician recommended routine vaccination with the measles, mumps and rubella vaccine, but Mike declined. He asks the pharmacist, someone he knows well and trusts, if the vaccine is necessary. Mike was under the impression there were no active measles cases in the U.S. Are there?


          PREVALENCE

          Prior to the availability of measles vaccine, almost everyone contracted measles during childhood. Approximately 90% of individuals obtained post-infection immunity by age 15.3,4


          The Vaccination Assistance Act provided federal funding to state and local agencies for childhood immunizations beginning in 1962.5 In 1963, two measles vaccines became available in the U.S.: a single dose of a live attenuated vaccine or three once-monthly doses of an inactivated vaccine.6 The inactivated vaccine was eventually discontinued in 1967 because it was less effective than the live vaccine.6,7 By mid-1967, the reported number of measles cases had decreased from 1000 to 200 weekly.5


          An increase in measles cases occurred from 1989 to 1991 due to decreased vaccination rates in young children and a rise in cases in individuals who had received only one dose of a measles vaccine. Increased vaccination awareness and rates in young children alongside the addition of a routine second dose of measles vaccine resulted in a major reduction in measles cases. The U.S. declared measles “eliminated” in 2000.1


          PAUSE AND PONDER: What factors influence vaccination rates?


          Since then, vaccine hesitancy due to misinformation regarding adverse effects and an incorrect association with autism has fueled decreasing vaccination rates. Other causes of declining measles vaccinations include missed routine vaccines during the COVID-19 pandemic and community complacency with measles’ severity and its complications. The resulting unvaccinated children are susceptible to the infection and its spread, thus propelling its resurgence.2,5


          As of August 2025 in the U.S., 41 states had reported 1,356 confirmed cases of measles since January of that year. Most cases occurred in unvaccinated patients8:

          • 92% were unvaccinated individuals or in people with unknown vaccination status
          • 4% had received only one dose of MMR
          • 4% had received two doses MMR.

          Among these cases, 13% were hospitalized, and three cases resulted in death.8


          A measles outbreak is defined as three or more related cases. From January to August 2025, the U.S. experienced 32 outbreaks, with 87% of confirmed cases related to these outbreaks. In 2024, 16 outbreaks were reported and 69% of measles cases were related to outbreaks.8


          Reflecting on our case, the pharmacist explains to Mike that domestic cases are rising due to declining vaccination rates worldwide, and that vaccination offers the best protection available.


          TRANSMISSION AND SYMPTOMS

          Transmission of measles occurs by direct contact or airborne spread through respiratory droplets and aerosols, which can stay airborne for up to two hours in enclosed areas.1,5,7 About 90% of non-immune people who are exposed to the measles virus will become infected.7


          The physical manifestation of measles infection begins 11 to 12 days after exposure with a prodrome of malaise, cough, coryza (runny nose and nasal congestion), and conjunctivitis.3 Approximately 50% to 70% of patients also develop Koplik spots, which are small white or grey papules in the mouth, during the prodrome phase.5


          After two to four days, a red, macropapular rash (a flat, red area on the skin that is covered with small bumps that may merge together) occurs, usually on the face or hairline.3,9 The rash progresses to the trunk, and then to the lower extremities.3 Patients with uncomplicated measles usually improve by the third day after the rash began, and most cases resolve within seven to 10 days. Patients are contagious from four days before until four days after the onset of the rash.9


          COMPLICATIONS

          Complications of measles include diarrhea, dehydration, pneumonia, encephalitis, and death.3 For every thousand cases of measles, one case may lead to encephalitis and two to three cases may lead to death. Measles-related deaths are typically due to respiratory and neurologic complications.1,3


          Rare complications of measles include measles inclusion body encephalitis (MIBE) and subacute sclerosing panencephalitis (SSPE). MIBE usually occurs in immunocompromised patients within one year of infection and is characterized by neurologic dysfunction, such as altered level of consciousness, seizures, loss of speech, one-sided paralysis, and lack of coordinated movements. MIBE has a mortality rate of 75%.1,10 SSPE is a degenerative central nervous system disease that results neurological decline and seizures. It usually develops seven to 11 years after infection, and it occurs most frequently in children infected with measles before age 2.1


          Patients at higher risk for measles infection are unvaccinated or incompletely vaccinated, have had exposure to measles, or have traveled to areas with active measles.8


          Severe cases of measles may require hospitalization.3 Patients who are younger than 5 or older than 20, pregnant, or immunocompromised are at the greatest risk for severe measles infections or complications.8


          Back to our case: Mike asks if there is medicine Bella can take to speed up her recovery if she catches measles, rather than prophylaxis with a vaccine.


          POST-EXPOSURE MANAGEMENT

          Confirmation of Diagnosis

          The diagnosis of measles is confirmed through laboratory findings. Positive serology for measles IgM antibodies, significant increase in IgG antibody levels, and cell culture of the measles virus can be assessed through blood assays. Evidence of measles RNA by reverse transcription polymerase chain reaction can be assessed through nasal, throat, or nasopharyngeal swab or a urine sample.5,11 Healthcare providers should obtain both a serum sample and a nasopharyngeal or throat swab or urine sample for all patients with clinical symptoms of measles.1,11 Just looking at the patient’s rash is not sufficient for diagnosis. Laboratory evidence is crucial because clinicians may incorrectly diagnose or report other febrile illnesses with rash as measles.5


          Reporting to Health Department

          Because measles has a significant impact on public health, it is a nationally notifiable disease. The purpose of national notification is to assess the incidence and spread of measles, with the goal of controlling outbreaks. Healthcare providers, laboratories, and hospitals should report confirmed cases of measles to local health departments. Each state has its own guidelines and requirements for reporting. The states report suspected and confirmed measles cases to the Centers for Disease Control and Prevention (CDC) using the National Notifiable Diseases Surveillance System.12,13


          Post-Exposure Prophylaxis

          Post-exposure prophylaxis (PEP) with measles, mumps and rubella vaccine (MMR) or immunoglobin in unvaccinated or partially vaccinated people may offer some protection against the disease, allowing for milder symptoms and a briefer course of illness.9 MMR should be administered within 72 hours of exposure.


          Patients who are ineligible for MMR (age less than 6 months, severely immunocompromised, or pregnant) and patients ages 6 to 11 months who did not receive MMR within the initial 72 hours can receive immunoglobulin within 6 days of exposure. Patients younger than 12 months of age can receive intramuscular immunoglobulin 0.5 mL/kg of body weight, with a maximum dose of 15 mL. Patients who are severely immunocompromised, pregnant, or weigh more than 30 kg can receive intravenous immunoglobulin 400 mg/kg.1


          Patients should not receive both immunoglobulin and MMR because the immunoglobulin will decrease the vaccine’s efficacy.14 Patients without immunity who receive immunoglobulin should be given MMR or MMRV (MMR with a varicella component) at least 6 months after intramuscular immunoglobulin and 8 months after intravenous immunoglobulin.


          Patients with documented immunity do not need PEP.1


          Treatment of Measles

          Treatment of measles is mainly limited to supportive care. Caregivers can give acetaminophen, ibuprofen, or intravenous fluids if needed for symptom control.15 Additionally, patients should isolate for four days after the rash appears to minimize the transmission of measles.16


          No antivirals are currently approved by the Food and Drug Administration for the treatment of measles. Although the measles virus displays in vitro susceptibility to riboviran, this has not been studied in clinical trials and is not indicated for the treatment of measles.1


          Treatment with vitamin A is an option for pediatric patients with measles. Vitamin A deficiency during measles infection has been linked with increased disease severity, additional complications, and prolonged recovery.15 Administration of vitamin A in children with measles in low- and middle-income countries has been connected to decreased morbidity and mortality.1 Although vitamin A deficiency is not as prevalent in higher income countries, infection with measles can reduce vitamin A stores.15 Given the benefit of vitamin A supplementation, the World Health Organization (WHO) recommends treatment with vitamin A for all children (not adults) with severe measles that requires hospitalization.1,15


          Vitamin A is given once daily for two days, as described in Table 1. Additionally, a third dose of vitamin A should be given two to six weeks after the initial dose for children with signs and symptoms of vitamin A deficiency.1


          Table 1. Vitamin A Dosing1,15,17
          Age of child Dose: International Units (IU) Dose: retinol activity equivalent (RAE)*
          12 months or older 200,000 60,000
          6 to 11 months 100,000 30,000
          Under 6 months 50,000 15,000
          *Research at the turn of the Century found that provitamin-A carotenoid absorption is only half as much as previously believed. Consequently, the U.S. Institute of Medicine recommended a new unit, the retinol activity equivalent (RAE) in 2001. Each mcg RAE corresponds to 1 mcg retinol, 2 mcg of β-carotene in oil, 12 mcg of "dietary" β-carotene, or 24 mcg of the three other dietary provitamin-A carotenoids.


          Revisiting our case: the pharmacist explains to Mike that although treatment with vitamin A is an option that may ease severity and promote recovery, it will not treat the infection. Mike now shares that Bella received a single dose of MMR five months ago (at age 10 months) before a trip to Europe for his sister’s wedding. He is wondering why she would need to be vaccinated again. Doesn’t that dose offer protection?


          VACCINE RECOMMENDATIONS

          To be considered immune to measles, patients must have documented administration of an age-appropriate live measles containing vaccine, laboratory confirmation of either immunity or disease, or birth prior to 1957.3 Individuals born before 1957 are assumed to be immune to measles due to childhood exposure, as most people developed immunity through infection with the virus before the availability of the vaccine.5


          Vaccination is key to measles prevention and control. Both the CDC and the American Academy of Pediatrics recommend routine vaccination with either MMR or MMRV.1,3 Table 2 provides additional information regarding current vaccines options.


          Table 2. Measles Vaccines Available in the United States1,18-20
          Brand name Manufacturer Active ingredients Age of administration Administration
          M-M-R II Merck measles, mumps, and rubella vaccine, live

          (MMR)

          12 months and older* 0.5 ml subcutaneously or intramuscularly
          Priorix GlaxoSmithKline measles, mumps, and rubella vaccine, live

          (MMR)

          12 months and older* 0.5 ml subcutaneously
          ProQuad Merck measles, mumps, rubella, and varicella vaccine, live

          (MMRV)

          12 months to 12 years 0.5 ml subcutaneously or intramuscularly
          *May be administered at ages 6 to 11 months for international travel, community outbreak, or post-exposure prophylaxis


          The first dose is usually given between 12 and 15 months of age, and the second dose is usually given between ages 4 and 6 years. The second dose may be given earlier, at least 28 days after the first dose for MMR and 90 days for MMRV, during a community outbreak of measles, before international travel, or to individuals who did not receive the vaccine during the recommended ages for administration. The MMRV vaccine should not be given to children younger than 1 year.1,21


          The CDC recommends that MMR and varicella vaccines are given separately when administered as the first dose for children aged 12 to 47 months, unless the parent or caregiver prefers MMRV. Clinicians usually prefer MMRV as the second dose in children age 15 months to 12 years and for both doses in unvaccinated children age 48 months and older. The SIDEBAR explains this further.


          At the time of this writing, the CDC Advisory Committee on Immunization Practices (ACIP) recommends that MMR and varicella vaccine be administrated separately until age 4. This is a change from the current recommendation to administer MMRV for the second dose in children 15 months and older. The ACIP recommendation is still pending approval from the CDC acting director and is not yet official.22


          SIDEBAR: How to choose MMR vs. MMRV23

          Piper, age 4, and her brother Oliver, age 12 months, are both due for measles and varicella vaccines. Piper received separate MMR and varicella vaccines when she was 1 year old. Their mom, Barbara, would like to minimize injections for each child. She asks if they can each receive MMRV to limit their shots today.


          Although MMRV is indicated for children ages 12 months to 12 years, it has been associated with an increased risk of fever and febrile seizure when given as the first dose to children ages 12 to 47 months of age. Experts encourage healthcare providers to counsel parents and caregivers of children in this age group regarding the risks and benefits of MMRV vaccination. MMRV may be administered if the parent or caregiver prefers; however, the CDC recommends that MMR and varicella vaccines are given separately for the first dose in this age range.


          Approximately 15% of children aged 12 to 47 months who receive MMR and varicella vaccines separately will experience post-vaccination fever (102°F or higher up to 42 days after vaccination), compared with 22% who receive MMRV. Administering the vaccines separately in this age group also decreases the febrile seizure risk by half: four of 10,000 children experience febrile seizure five to 12 days after vaccination with MMR and varicella separately, as compared to eight of 10,000 with MMRV.


          For children aged 48 months and older, the risk of fever or febrile seizure with the first dose of MMRV declines and is similar to the risk when MMR and varicella vaccine are administered separately. The risk also decreases in all age groups when MMRV is administered as the second dose. Clinicians usually prefer MMRV for both doses in children aged 48 months and older and for the second dose in children ages 15 months to 12 years.


          MMR and varicella vaccine should be administered separately for children with a personal or family history of seizures because they are at increased risk of febrile seizure after MMRV vaccination.


          The pharmacist discusses the risks and benefits with Barbara, explaining that Piper received MMR and varicella vaccines separately at age 1 to reduce the risk of fever and febrile seizure. Because Piper is 4, she is an excellent candidate for MMRV. Barbara confirms that neither Oliver nor anyone in his family has a history of seizures. The pharmacist discusses the risks of MMRV at Oliver’s age (increased risk of fever and febrile seizures) and benefits (one injection rather than two). Barbara weighs the information presented to her and decides to follow the CDC recommendation of vaccinating Oliver with separate vaccines today, but will plan for MMRV for his second dose at age 4.


          Before Barbara leaves, she pauses at the pharmacy counter. She asks about her niece, Lucy, who is 4 and unvaccinated. She wonders if Lucy is eligible for MMRV vaccination, and if consolidating shots might encourage Lucy’s mom to consider vaccination.


          The pharmacist confirms that MMRV is appropriate for Lucy based on her age and vaccination status. Children aged 4 and older have not demonstrated an increased incidence of fever and febrile seizure when MMRV is administered as either the first or second dose. A decreased risk of adverse events and administration of a single injection rather than two with each dose may be preferable to Lucy and her parent. The pharmacist offers to contact Lucy’s mom and discuss vaccination options with her, explaining that Lucy could receive the first dose of MMRV now and the second dose in 90 days.


          The MMR vaccine may be given to children ages 6 to 11 months if a community outbreak occurs or if the child is traveling internationally. For optimal efficacy, clinicians should give the vaccine at least two weeks before travel. It is important to note that a dose given before age 1 does not count towards completing the immunization series; a total of two doses are required to be administered after age 1, and doses given at ages 12 to 15 months and 4 to 6 years are still recommended.1


          Reflecting back on our case: the pharmacist explains to Mike that Bella needs two doses after age 1 to ensure immunity to measles. Although Bella received a dose prior to international travel, she was younger than 12 months old, and it does not count towards completing the series.


          PAUSE AND PONDER: Who else would benefit from measles vaccinations?


          Although the guidelines are age based for routine administration, some patients may fall outside these parameters. Adults and older children, such as those in high school or college, who received a single dose after 12 months of age should receive a second dose, regardless of their current age.1


          Other populations that should receive two doses of MMR, at least 28 days apart, include

          • Students without immunity at educational institutions after high school, such as college or university
          • International travelers without immunity
          • Healthcare workers without immunity
          • Healthcare workers born prior to 1957 without laboratory confirmation of immunity
          • Close contacts of immunocompromised individuals who do not have documented immunity
          • Individuals older than 12 months of age with human immunodeficiency virus (HIV) infection without immunosuppression and without immunity


          An additional one to two doses of MMR may be required for 21

          • Recipients of the inactivated measles vaccine between 1963 and 1967
          • Individuals at risk during an outbreak as determined by a health department


          People who should not receive MMR or MMRV are individuals with18-20

          • Hypersensitivity to any component of a measles-containing vaccine
          • Immunodeficiency or immunosuppression due to disease or medical therapy
          • Pregnancy or those who plan to become pregnant within a month
          • Active febrile illness with fever greater than 101.3°F (38.5°C) (M-M-R II and ProQuad)
          • Active tuberculosis in those who are not receiving treatment (M-M-R II and ProQuad)


            Patients who may be at greater risk for a experiencing a serious adverse reaction or having a less robust immune response after vaccination are those with21

            • Acute illness, with or without fever
            • Use of blood product containing antibodies within the past 11 months
            • Thrombocytopenia or thrombocytopenic purpura
            • Indication for tuberculin skin testing or interferon gamma release assay testing
            • Seizures, either personal or family history


            Back to the dad in our case: he’s still hesitant. He feels that his daughter has had so many vaccines already. And he’s read online that vaccines aren’t always safe. He wonders aloud if it is it really worth the risk?


            VACCINE HESITANCY

            Vaccine hesitancy (VH) is complicated and multifactorial. It is formed by social, cultural, political, and personal elements.24,25 The WHO defines VH as a “delay in acceptance or refusal of vaccines despite availability of vaccination services.”26 Examples include delaying vaccines, limiting the number of vaccines administered at the same time, avoiding specific vaccines, and omitting all vaccines completely.27 Some VH individuals believe that natural immunity (immunity resulting from infection) is more beneficial to the immune system than vaccine-induced immunity. While both routes provide immunity, the risks of vaccination are usually lower than the potential complications or consequences of acquiring the infection.25,28 VH is not clear cut; VH is a spectrum that encompasses a range of beliefs, attitudes, and actions.


            PAUSE AND PONDER: How can pharmacy teams effectively address VH?


            The 3 C model describes vaccine hesitancy as a result of decreased confidence, increased complacency, and decreased convenience. Table 3 describes the components of the 3 C Model of vaccine hesitancy.29


            Table 3. The 3 C Model of Vaccine Hesitancy29,30
            Confidence Patient trust regarding

            •   The safety and effectiveness of vaccines

            •   The healthcare system providing vaccines

            •   The motivation of policymakers who determine vaccine guidelines

            Complacency •   The risks of vaccine preventable diseases are believed to be low

            •   May occur when the disease being prevented is no longer prevalent

            Convenience Ease in obtaining vaccination, influenced by

            •   Availability

            •   Affordability

            •   Accessibility

            •   Literacy

            •   Immunization services

            •   Comfort


            Healthcare providers might assume VH is a fairly new development, resulting from and driven by the Internet and social media. While it is true that social media often propagates vaccine misinformation, VH was first recognized more than 200 years ago with the administration of smallpox inoculation. VH evolved further in the late 1800s when smallpox vaccination requirements led to the adoption of personal belief exemption. Personal belief exemption, which is the practice of omitting a vaccination based on individual convictions, continued to gain popularity as more vaccines became available.24


            Sources for vaccine information abound, including healthcare providers, the Internet, social media, word of mouth, and traditional media.27 Pharmacists are strong resources to answer vaccine questions and concerns because people view pharmacists as trusted and accessible. This position of responsibiliy allows pharmacists to help patients navigate the abundance of information—and misinformation—available.31


            Traditionally, healthcare providers tackled individual VH through fact-based education to correct misinformation. However, a well-rounded approach focusing on individual beliefs in addition to evidence-based facts may be more effective in encouraging vaccine adoption.31


            An option for addressing VH is the ASPIRE framework. This method helps pharmacists interact with patients regarding vaccination beyond basic education. It encourages pharmacists to actively engage with patients to establish trust and address their specific concerns.31


            The ASPIRE framework consists of the following actions31:

            • Assume that people want to be vaccinated and be prepared for questions
            • Share key facts and information sources to counter misinformation
            • Present strong recommendations to vaccinate and stories about vaccination experiences
            • Initiate discussion or address questions about adverse effects proactively and share credible information sources
            • Respond to questions and listen actively
            • Empathize and understand concerns


            In our case, the pharmacist recognizes Mike’s concern but assures him that misinformation is rampant. The pharmacist explains with empathy that measles vaccine is both safe and effective, and that exposure to the disease often carries severe complications. The pharmacist offers to vaccinate today. Mike decides to think it over while he shops for snacks. The pharmacist will continue to offer the vaccination every time Mike and Bella visit the pharmacy.


            CONCLUSION

            Measles is no longer a disease of the past. The recent uptick in cases is directly related to declining vaccination rates. Unvaccinated individuals are at risk for infection and complications, which may be severe. People without immunity may also transmit the disease to other unvaccinated individuals, perpetuating the cycle. Healthcare providers, laboratories, and hospitals should confirm suspected cases of measles with laboratory findings and report to the appropriate local health department. While supportive care may offer symptom control, prevention is key to measles control; both the MMR and MMRV vaccine are safe, effective, and available. Active and empathetic counseling techniques can help pharmacists build vaccine confidence and adoption.


            Pharmacist Post Test (for viewing only)

            SPOTTED: MEASLES CASES RISING IN THE U.S.
            25-060 P
            Pharmacist post-test

            Pharmacist Learning Objectives
            After completing this continuing education activity, pharmacists will be able to
            • Identify the transmission of measles, its symptoms, and patients at higher risk for complications
            • Describe the steps healthcare providers should take if measles is suspected or confirmed
            • Determine appropriate patients for measles vaccination
            • Apply patient counseling techniques regarding vaccine education

            1. How long is a patient with measles contagious?
            A. 2 days before until 2 days after rash appears
            B. 4 days before until 4 days after rash appears
            C. 6 days before until 6 days after rash appears

            *

            2. Which individual is at greatest risk for developing complications from measles?
            A. A 2-year-old child
            B. A 6-year-old child
            C. A 15-year-old adolescent

            *

            3. A 48-year-old woman with unknown vaccination status is exposed to measles. She is not pregnant or severely immunocompromised. Which of the following may be administered within 72 hours to minimize symptoms and hasten recovery?
            A. Immunoglobulin
            B. Vitamin A
            C. MMR

            *

            4. The patient from the previous question does not obtain the first line agent during the 72-hour window. What is her next option?
            A. Immunoglobulin
            B. Vitamin A
            C. MMR

            *

            5. An 18-year-old college student approaches the pharmacy counter to ask about MMR vaccination. He is preparing to begin his freshman year in a dorm, but he can’t find his childhood immunization records. He does not have the financial resources to obtain laboratory confirmation of immunity. What should the pharmacist tell him?
            A. Administration of MMR at age 18 is fine if his immunity status is unknown
            B. Administration of MMR at age 18 is not appropriate because he is too old
            C. The student should keep looking; his records must be somewhere

            *

            6. A man without measles immunity is preparing to travel outside the U.S. His flight departs in 12 weeks. The pharmacist administers MMR today. When should the second dose be administered?
            A. Only 1 dose should be administered prior to travel
            B. After 28 days
            C. After 90 days

            *

            7. An 11-month-old child presents with her parent at the pharmacy for measles vaccination due to a community outbreak. The parent is willing to vaccinate and prefers MMRV so that the child is also protected from varicella. What should the pharmacist tell the parent?
            A. No problem, MMRV can be administered today with no problem
            B. MMRV should not be administered because measles vaccination due to an outbreak is not appropriate for a child less than 12 months old
            C. MMRV should not be administered because the child is too young, however, MMR is appropriate for a community outbreak and may be administered today

            *

            8. A patient is overheard saying that exposure to infections is more beneficial than vaccinations. He says his grandchildren are unnecessarily exposed to “who knows what” in their vaccines and they would be better off just contracting the disease.
            How could the pharmacist address his vaccine hesitancy?

            A. Give him educational material regarding vaccine safety and effectiveness
            B. Actively listen to his concerns and engage with empathy and education
            C. Ignore him; he will never change his mind

            Pharmacy Technician Post Test (for viewing only)

            SPOTTED: MEASLES CASES RISING IN THE U.S.
            25-060 T
            Pharmacy technician post-test

            Pharmacy Technician Learning Objectives
            After completing this continuing education activity, pharmacy technicians will be able to
            • Identify the symptoms of measles, its transmission, and patients at higher risk for complications
            • Describe the steps healthcare providers should take if measles is suspected or confirmed
            • Determine which patients might need vaccine education from the pharmacist

            1. When was the first measles vaccine available in the U.S.?
            A. 1962
            B. 1963
            C. 1967

            *

            2. Which individual is at greatest risk for developing complications from measles?
            A. A 2-year-old child
            B. A 6-year-old child
            C. A 15-year-old adolescent

            *

            3. When does the rash from measles appear?
            A. Immediately after exposure
            B. 2 to 4 days after exposure
            C. 11 to 12 days after exposure

            *

            4. How long should a patient isolate after the rash appears?
            A. 2 days
            B. 4 days
            C. 6 days

            *

            5. Which organization collects and analyzes the measles data from local health departments?
            A. The American Academy of Pediatrics
            B. The World Health Organization
            C. National Notifiable Diseases Surveillance System

            *

            6. A patient asks where he can find vitamin A supplements. He heard that it is good for measles and wants to take some just in case he is exposed. How should the technician address this?
            A. Direct him towards the aisle of supplements; good news, vitamins are on sale this week
            B. Refer him to the pharmacist for education regarding measles treatment and supportive care
            C. Ask him if he’s had a fever or rash recently

            *

            7. Which individual would be most likely to benefit from MMR/MMRV education?
            A. 80-year-old woman purchasing acetaminophen
            B. 75-year-old man picking up his prescription for lisinopril
            C. Parent picking up amoxicillin for a 4-year old’s ear infection

            *

            8. A patient at the pharmacy counter is complaining about routine vaccinations. He tells another patient that vaccines are a conspiracy, and he will never vaccinate his children. How could this be addressed?
            A. Pharmacy staff should discretely attach educational vaccine information to his receipt
            B. It should be ignored; there is no point in arguing
            C. Engaging with empathy and education may be effective

            References

            Full List of References

            References

               
              1. Kimberlin DW, Banerjee R, Barnett E, Lynfield R, Sawyer M. Measles in Red Book: 2024–2027 Report of the Committee on Infectious Diseases. 33rd ed. American Academy of Pediatrics; 2024. Accessed August 29, 2025. https://doi.org/10.1542/9781610027373-S3_012_002

              2. Moss WJ, Griffin DE. What's going on with measles?. J Virol. 2024;98(8):e0075824. doi:10.1128/jvi.00758-24

              3. Manual for the Surveillance of Vaccine-Preventable Diseases. Chapter 7: Measles. Centers for Disease Control and Prevention. Accessed August 12, 2025. https://www.cdc.gov/surv-manual/php/table-of-contents/chapter-7-measles.html

              4. Measles Vaccine. American Academy of Pediatrics. Accessed August 17, 2025. https://www.aap.org/en/patient-care/measles/measles-vaccine/?_gl=1*uk5qr9*_ga*MzgyNDg1Njk2LjE3NTUwMjgxOTY.*_ga_FD9D3XZVQQ*czE3NTUwMjgxOTUkbzEkZzEkdDE3NTUwMjgyNjYkajU3JGwwJGgw

              5. Parums DV. A Review of the Resurgence of Measles, a Vaccine-Preventable Disease, as Current Concerns Contrast with Past Hopes for Measles Elimination. Med Sci Monit. 2024;30:e944436. Published 2024 Mar 13. doi:10.12659/MSM.944436

              6. Hendriks J, Blume S. Measles vaccination before the measles-mumps-rubella vaccine. Am J Public Health. 2013;103(8):1393-1401. doi:10.2105/AJPH.2012.301075

              7. Gastanaduy P, Haber P, Rota P, Patel M. Chapter 13: Measles. Centers for Disease Control Epidemiology and Prevention of Vaccine-Preventable Diseases. Accessed August 19, 2025. https://www.cdc.gov/pinkbook/hcp/table-of-contents/chapter-13-measles.html

              8. Red Book Online Outbreaks: Measles. American Academy of Pediatrics. Accessed August 12, 2025. https://publications.aap.org/redbook/resources/15187/Red-Book-Online-Outbreaks-Measles?autologincheck=redirected

              9. Measles vaccines: WHO position paper – April 2017. World Health Organization Weekly epidemiological record. 2017;(92):205–228. Accessed August 28, 2025. https://www.who.int/publications/i/item/who-wer9217-205-227

              10. Diwan MN, Samad S, Mushtaq R, et al. Measles Induced Encephalitis: Recent Interventions to Overcome the Obstacles Encountered in the Management Amidst the COVID-19 Pandemic. Diseases. 2022;10(4):104. Published 2022 Nov 17. doi:10.3390/diseases10040104

              11. Laboratory Testing for Measles. Centers for Disease Control: Measles. Accessed September 16, 2025. https://www.cdc.gov/measles/php/laboratories/index.html

              12. Measles: for public health professionals. Centers for Disease Control and Prevention. Accessed August 15, 2025. https://www.cdc.gov/measles/php/guidance/index.html

              13. National Notifiable Diseases Surveillance System. Centers for Disease Control. Accessed September 7, 2025. https://www.cdc.gov/nndss/docs/NNDSS-Overview-Fact-Sheet-508.pdf

              14. Measles Vaccine Recommendations: Information for Healthcare Professionals. Centers for Disease Control. Accessed September 11, 2025. https://www.cdc.gov/measles/hcp/vaccine-considerations/index.html#cdc_generic_section_5-post-exposure-prophylaxis-for-measles

              15. Call to Action: Vitamin A for the Management of Measles in the United States. National Foundation for Infectious Diseases. Accessed August 15, 2025. https://www.nfid.org/wp-content/uploads/2023/04/Call-to-Action-Vitamin-A-for-the-Management-of-Measles-in-the-US-FINAL.pdf

              16. Clinical Overview of Measles. Centers for Disease Control. Accessed August 27, 2025. https://www.cdc.gov/measles/hcp/clinical-overview/index.html

              17. Institute of Medicine (US) Panel on Micronutrients. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington (DC): National Academies Press (US); 2001. Accessed September 19, 2025. https://www.ncbi.nlm.nih.gov/books/NBK222310/ doi: 10.17226/10026

              18. M-M-R II. Prescribing information. Merck & Co., Inc.; 1978-2024. Accessed August 15, 2025.https://www.merck.com/product/usa/pi_circulars/m/mmr_ii/mmr_ii_pi.pdf

              19. Priorix. Prescribing information. GlaxoSmithKline; 2024. Accessed August 15, 2025. Available at https://gskpro.com/content/dam/global/hcpportal/en_US/Prescribing_Information/Priorix/pdf/PRIORIX.PDF

              20. ProQuad. Prescribing information. Merck & Co., Inc.; 2005-2024. Accessed August 15, 2025. https://www.merck.com/product/usa/pi_circulars/p/proquad/proquad_pi.pdf

              21. Routine Measles, Mumps, and Rubella Vaccination. Centers for Disease Control. Accessed August 12, 2025. https://www.cdc.gov/vaccines/vpd/mmr/hcp/recommendations.html

              22. ACIP Recommends Standalone Chickenpox Vaccination in Toddlers. U.S. Department of Health and Human Services. Accessed September 19, 2025. https://www.hhs.gov/press-room/acip-recommends-chickenpox-vaccine-for-toddlers.html
              23. MMR & Varicella Vaccines or MMRV Vaccine: Discussing Options with Parents. Centers for Disease Control: Vaccines and Immunizations. Accessed September 9, 2025. https://www.cdc.gov/vaccines/vpd/mmr/hcp/vacopt-factsheet-hcp.html

              24. Galagali PM, Kinikar AA, Kumar VS. Vaccine Hesitancy: Obstacles and Challenges. Curr Pediatr Rep. 2022;10(4):241-248. doi:10.1007/s40124-022-00278-9

              25. Dubé E, Laberge C, Guay M, Bramadat P, Roy R, Bettinger J. Vaccine hesitancy: an overview. Hum Vaccin Immunother. 2013;9(8):1763-1773. doi:10.4161/hv.24657

              26. World Health Organization. Summary WHO SAGE conclusions and recommendations on vaccine hesitancy. 2015. Accessed August 18, 2025. https://cdn.who.int/media/docs/default-source/immunization/demand/summary-of-sage-vaccinehesitancy-en.pdf

              27. Novilla MLB, Goates MC, Redelfs AH, et al. Why Parents Say No to Having Their Children Vaccinated against Measles: A Systematic Review of the Social Determinants of Parental Perceptions on MMR Vaccine Hesitancy. Vaccines (Basel). 2023;11(5):926. Published 2023 May 2. doi:10.3390/vaccines11050926

              28. Biggs AT, Littlejohn LF. Vaccination and natural immunity: Advantages and risks as a matter of public health policy. Lancet Reg Health Am. 2022;8:100242. doi:10.1016/j.lana.2022.100242

              29. Houle SKD, Andrew MK. RSV vaccination in older adults: Addressing vaccine hesitancy using the 3C model. Can Pharm J (Ott). 2023;157(1):39-44. Published 2023 Nov 24. doi:10.1177/17151635231210879

              30. MacDonald NE, SAGE Working Group on Vaccine Hesitancy Vaccine hesitancy: definition, scope and determinants. Vaccine. 2015;33(34):4161–4164. doi: 10.1016/j.vaccine.2015.04.036

              31. Shen AK, Tan ASL. Trust, influence, and community: Why pharmacists and pharmacies are central for addressing vaccine hesitancy. J Am Pharm Assoc (2003). 2022;62(1):305-308. doi:10.1016/j.japh.2021.10.

              Henry A. Palmer CE Finale, LIVE December 16, 2026

              The Henry A. Palmer CE Finale, named for beloved professor and mentor Dr. Henry A. Palmer, is held each December to help pharmacists fulfill their remaining continuing education (CE) requirements. This à la carte program offers presentations on contemporary issues in pharmacy practice and therapeutics. Pharmacists may enroll in one to eight hours of CE.

              Pharmacy’s Greatest Hits: Classics, Covers, Remixes, and New Releases. Eight Hours, No Fillers

              A LIVE (both virtual on Microsoft Teams and in-person) application-based continuing education activity for practicing pharmacists in all settings

              LIVE Event Date: December 16, 2026,  7:30 AM - 5:00 PM Eastern Time

              LIVE Encore Webinar Dates: December 21-30, 2026

              Microsoft Teams Webinars, links in confirmation emails


              NEW LOCATION THIS YEAR 2026!!!

              Leadership Center CT
              613 New Britain Ave, Farmington, CT 06032
              877-969-7383

              REGISTRATION LINK

              Accreditation Statements

              The University of Connecticut School of Pharmacy and Pharmaceutical Sciences is accredited by the Accreditation Council for Pharmacy Education as a provider of continuing pharmacy education.


              ACPE UAN 0009-0000-26-056-L03-P (Application-based)

              ACPE UAN 0009-0000-26-057-L01-P (Application-based)

              ACPE UAN 0009-0000-26-058-L01-P (Application-based)

              ACPE UAN 0009-0000-26-059-L01-P (Application-based)

              ACPE UAN 0009-0000-26-060-L06-P (Application-based)

              ACPE UAN 0009-0000-26-061-L05-P (Application-based)

              ACPE UAN 0009-0000-26-062-L06-P (Application-based)

              ACPE UAN 0009-0000-26-063-L01-P (Application-based)


              Credits will be awarded when the post test and evaluation have been completed and passed with a 70% or better. Your CE credits will be uploaded to your CPE monitor profile within 2 weeks of completion of the program.


              Disclosure of Discussions of Off-label and Investigational Drug Use

              The material presented here does not necessarily reflect the views of The University of Connecticut School of Pharmacy and Pharmaceutical Sciences or its co-sponsor affiliates. These materials may discuss uses and dosages for therapeutic products, processes, procedures and inferred diagnoses that have not been approved by the United States Food and Drug Administration. A qualified health care professional should be consulted before using any therapeutic product discussed. All readers and continuing education participants should verify all information and data before treating patients or employing any therapies described in this continuing education activity.

              Faculty

              Yvonne Riley-Poku, PharmD, RPh, Lecturer, Pharmacy Technician Certificate Program, CT State Community College, Bridgeport, CT
              Osama (Sam) Abdelghany, PharmD MHA, BCOP, Executive Director, Pharmacy Services, Yale-New Haven Hospital, New Haven, CT
              Youssef Bessada PharmD, BCPS, Assistant Clinical Professor of Pharmacy Practice, UConn School of Pharmacy and Pharmaceutical Sciences, Storrs, CT
              Kelsey Giara, PharmD, Adjunct Faculty, UConn School of Pharmacy and Pharmaceutical Sciences, Storrs, CT
              Brett Feret, PharmD, Clinical Professor, Director Office of Experiential Education, University of Rhode Island, Kingston, RI
              Katelyn Galli, PharmD, BCCP, UConn School of Pharmacy and Pharmaceutical Sciences, Storrs, CT
              C. Michael White, PharmD, FCP, FCCP, FASHP, Distinguished Professor and Chair, Pharmacy Practice, UConn School of Pharmacy and Pharmaceutical Sciences, Storrs, CT
              Devra Dang, PharmD, CDCES, FNAP, Clinical Professor, UConn School of Pharmacy and Pharmaceutical Sciences, Storrs, CT

              Faculty Disclosure

              In accordance with the Accreditation Council for Pharmacy Education (ACPE) Criteria for Quality and Interpretive Guidelines, The University of Connecticut School of Pharmacy and Pharmaceutical Sciences requires that faculty disclose any relationship that the faculty may have with commercial entities whose products or services may be mentioned in the activity.

              All the speakers have no relationships with ineligible companies.


              SCHEDULE/TOPICS/LEARNING OBJECTIVES

              7:30-8:00 a.m. - Registration and Check-In/Sign-In

              8:00-8:05 a.m. - Opening Remarks- Philip M. Hritcko, Dean and Clinical Professor, University of Connecticut School of Pharmacy and Pharmaceutical Sciences (UConn SoPPS), Storrs, CT

              8:05-8:10 a.m. – Operational Instructions- Jeannette Y. Wick, RPh, MBA, Director, Office of   Professional Pharmacy Development, UConn SoPPS, Storrs, CT


              8:10 - 9:10 a.m. – LAW: The Buzz About the Expanding Scope of Practice for Pharmacy Technicians

              Yvonne Riley-Poku, PharmD, RPh, Lecturer, Pharmacy Technician Certificate Program, CT State Community College, Bridgeport, CT

              0009-0000-26-056-L03-P (0.1 CEU or 1 contact hour) (Application-based)

              At the conclusion of this presentation, pharmacists will be able to
              • DESCRIBE the current scope of practice of pharmacy technicians nationally
              • IDENTIFY advanced and specialty certifications, and required credentials
              • DISCUSS new laws and proposed changes to scope of practice in CT and nationally, and their relevance in the workplace


              9:15 - 10:15 a.m. – On Target, On Tour: A Pharmacist’s Guide to Oral Therapy in Lung Cancer

              Osama (Sam) Abdelghany, PharmD MHA, BCOP, Executive Director, Pharmacy Services, Yale-New Haven Hospital, New Haven, CT

              0009-0000-26-057-L01-P  (0.1 CEU or 1 contact hour) (Application-based)

              At the conclusion of this presentation, pharmacists will be able to
              • DESCRIBE the role of molecularly targeted oral therapies in the management of Lung Cancer
              • IDENTIFY clinically significant drug-drug and drug-food interactions associated with commonly used oral targeted therapies for lung cancer
              • RECOGNIZE treatment-related toxicities that require pharmacist intervention or referral to the oncology team
              • DEVELOP patient counseling, medication-reconciliation, and monitoring strategies to support the safe use of oral targeted therapies across community and health-system settings


              10:20-11:20 a.m. – Factor XI Inhibitors – Coming Soon to an Antithrombotic Management Program Near You

              Youssef Bessada PharmD, BCPS, Assistant Clinical Professor of Pharmacy Practice, UConn SoPPS, Storrs, CT

              0009-0000-26-058-L01-P (0.1 CEU or 1 contact hour) (Application-based)

              At the conclusion of this presentation, pharmacists will be able to
              • DESCRIBE the role of Factor XI/XIa in coagulation and explain the mechanistic rationale for targeting Factor XI/XIa to reduce thrombosis while preserving hemostasis
              • DIFFERENTIATE emerging Factor XI/XIa inhibitors based on molecule, mechanism of action, formulation, route of administration, pharmacokinetic characteristics, duration of effect, and monitoring considerations
              • EVALUATE emerging clinical evidence for Factor XI/XIa inhibitors across major potential indications, including atrial fibrillation, venous thromboembolism, secondary stroke prevention, cancer-associated thrombosis, and special populations in thrombotic conditions
              • IDENTIFY potential opportunities and challenges for Factor XI/XIa inhibitors within contemporary pharmacy practice and antithrombotic stewardship


              11:25-12:25 p.m.  - Changing the Migraine Prevention Playlist: A New Guideline Hits the Charts

              Kelsey Giara, PharmD, Adjunct Faculty, UConn SoPPS, Storrs, CT

              0009-0000-26-059-L01-P (0.1 CEU or 1 contact hour) (Application-based)

              At the conclusion of this presentation, pharmacists will be able to
              • DESCRIBE key updates in the 2026 AAN/AHS guideline for migraine prevention
              • COMPARE established and newer preventive therapies with respect to efficacy, safety, tolerability, and practical considerations
              • IDENTIFY patient-specific factors that influence selection of migraine preventive therapy
              • APPLY current guideline recommendations to pharmacist-led patient education, monitoring, and care coordination


              12:25-12:45 p.m. – BREAK. Light snacks will be served.


              12:45-1:45 p.m. – IMMUNIZATION: The Updated Vaccine Playlist: Classics to New Releases

              Brett Feret, PharmD, Clinical Professor, Director Office of Experiential Education, University of Rhode Island, Kingston, RI

              0009-0000-26-060-L06-P (0.1 CEU or 1 contact hour) (Application-based)

              At the conclusion of this presentation, pharmacists will be able to
              • COMPARE and CONTRAST current CDC/ACIP immunization recommendations with guidance from other professional medical organizations to identify areas of alignment and differences in vaccine recommendations
              • DESCRIBE current recommendations for influenza, COVID-19, and RSV vaccinations, including notable clinical updates and areas of controversy
              • DISCUSS other updates to adult and pediatric immunization recommendations, including changes in vaccine schedules, safety considerations, and emerging vaccines relevant to pharmacy practice


              1:50-2:50 p.m.  – PATIENT SAFETY: Bad Medicine: Cardiovascular Drug Toxicities You Should Know by Heart

              Katelyn Galli, PharmD, BCCP, UConn SoPPS, Storrs, CT

              0009-0000-26-061-L05-P  (0.1 CEU or 1 contact hour (Application-based)

              At the conclusion of this presentation, pharmacists will be able to
              • IDENTIFY the most likely cardiovascular medication commonly implicated in toxicities and adverse effects based on a patient-specific presentation
              • ASSESS patient-specific and medication-related factors (e.g. organ dysfunction, electrolyte disturbances, drug interactions, comorbidities) that increase the risk of developing toxicity secondary to cardiac medications
              • RECOMMEND pharmacist interventions to manage or prevent toxicity secondary to cardiovascular medications


              2:55-3:55 p.m.  – PATIENT SAFETY: New risks: The Intoxicating Hemp Market: What Pharmacists Need to Know

              C. Michael White, PharmD, FCP, FCCP, FASHP, Distinguished Professor and Chair, Pharmacy Practice, UConn SoPPS, Storrs, CT

              0009-0000-26-062-L05-P  (0.1 CEU or 1 contact hour) (Application-based)

              At the conclusion of this presentation, pharmacists will be able to
              • DEFINE the definitional gap in the 2018 Farm Bill that lets intoxicating hemp cannabinoids bypass state cannabis regulation
              • IDENTIFY how CBD in hemp is turned into intoxicating hemp
              • LIST the major quality-control risks in hemp-derived products, including contamination, mislabeling, and inconsistent dosing
              • DESCRIBE the federal total-THC threshold and per-container cap that take effect mid-December 2026
              • APPLY knowledge to a case that will be discussed at the end of the presentation


              4:00-5:00 p.m. – The Ultimate Remixes of a Classic – Insulin Therapy in the Management of Type 2 Diabetes

              Devra Dang, PharmD, CDCES, FNAP, Clinical Professor, UConn SoPPS, Storrs, CT

              0009-0000-26-063-L01-P (0.1 CEU or 1 contact hour) (Application-based)

              At the conclusion of this presentation, pharmacists will be able to
              • LIST the major insulin formulations and their pharmacologic characteristics, including the newly once-weekly insulins
              • DIFFERENTIATE among insulin formulations and regimens based on clinical characteristics and practical considerations
              • EXPLAIN the current role of insulin therapy in the management of type 2 diabetes and how it has evolved in the setting of modern glucose-lowering therapies


              We use a continuous class schedule format.  This format does not include breaks but does include a 20-minute lunch period. Live activities on December 16th cost $60 for the first hour. Each additional activity costs $20. Early bird pricing ends December 8, 2026. Starting December 9, $25 is added to the total. We offer a 50% discount for UConn faculty/preceptors

              CE FINALE LIVE ENCORE WEBINARS AVAILABLE on Microsoft TEAMS  If you cannot make it to our LIVE EVENT on Wednesday, December 16, you can participate in our ENCORE LIVE WEBINARS that will stream on Microsoft Teams on the following dates in Eastern Standard Time:

              • Monday, December 21, Noon - 1 p.m. The Ultimate Remixes of a Classic – Insulin Therapy in the Management of Type 2 Diabetes
              • Monday, December 21, 7 - 8 p.m. Changing the Migraine Prevention Playlist: A New Guideline Hits the Charts
              • Tuesday, December 22, 7 - 8 p.m. PATIENT SAFETY: Bad Medicine: Cardiovascular Drug Toxicities You Should Know by Heart
              • Wednesday, December 23, Noon - 1 p.m. PATIENT SAFETY: New risks: The Intoxicating Hemp Market: What Pharmacists Need to Know
              • Monday, December 28, Noon - 1 p.m. Factor XI Inhibitors – Coming Soon to an Antithrombotic Management Program Near You
              • Tuesday, December 29, Noon - 1 p.m. On Target, On Tour: A Pharmacist’s Guide to Oral Therapy in Lung Cancer


              Refunds and Cancellations: The registration fee, less a $75 processing fee, is refundable for those who cancel their registration three (3) days prior to the program (by December 12) After that time, no refund is available.

              Location: The Henry A. Palmer C.E. Finale will be held both virtually and in-person at the Leadership Center CT, in Farmington, CT (a new location for 2026). You must sign in to the Microsoft Teams link at the designated time using the link in your confirmation email if you decide to participate virtually.

              Required Computer Hardware/Software: Virtual learners need an internet connection to see the slides, hear the speaker, participate in the chat, and have the opportunity to ask any questions via Microsoft Teams, and submit the evaluation afterward. We recommend using an updated Microsoft Edge or Google Chrome and your browser. The latest Firefox or Safari are also compatible with Teams. If you are using a desktop app you will need a dual-core processor and at least 4 GB of RAM, with 3 GB of available storage on Windows or 1.5 GB on Mac. 

              Continuing Education Units

              The University of Connecticut, School of Pharmacy and Pharmaceutical Sciences, is accredited by the Accreditation Council for Pharmacy Education as a provider of continuing pharmacy education. Statements of Credit will be awarded at CE Finale based on full sessions attended and completed online evaluations. Pharmacists can earn up to 8 contact hours (0.80 CEU) one of which is a Law credit, one is an Immunization Credit, and two are Patient Safety credits.

              Please Note: Pharmacists who wish to receive credit for the presentations must complete the registration and online evaluations accurately within 45 days of the live program (before January 26, 2027).  Participants are accountable for their own continuing education requirements for license renewal and are required to follow up with Heather.Kleven@uconn.edu to resolve a discrepancy in a timely manner. PLEASE CHECK YOUR CPE MONITOR PROFILE within 3 days of submission to ensure that your credits have been properly uploaded.  Requests for exceptions will be handled on a case-by-case basis and may result in denial of credit.

              Our paper check processing system is quite slow. Please contact Heather.Kleven@uconn.edu if you must pay by check.

              Download 2026 Event Brochure

              REGISTRATION LINK

              Immunization: The Right Tool for the Job: Precision and Preparation in Immunization Practice -RECORDED WEBINAR

              About this Course

              This course is a recorded (home study version) of the Arthur E. Schwarting Symposium on April 17, 2026 . The theme was "Measure Twice, Cut Once: A Carpentry Approach to Pharmacy."


              Learning Objectives

              Upon completion of this application based CE Activity, a pharmacist will be able to:

              • Analyze contraindications as the “measurement” step
              • Determine the correct vaccine, dose, route, and needle length
              • Document and report finishing work
              • Detect administration errors and adverse events
              • Illustrate reliable vaccine information

              Release and Expiration Dates

              Released:  April 17, 2026
              Expires:  April 17, 2029

              Course Fee

              $10 Pharmacist

              ACPE UAN

              0009-0000-26-011-H06-P

              Session Code

              26RS11-PAT74

              Accreditation Hours

              1 hour of CE (0.1 CEUs)

              Additional Information


              How to Complete Evaluation:  When you are ready to submit posttest answers, go to the BLUE take test/evaluation button. Use the session code from your confirmation email or from the box above, not from the end of the video!

              Accreditation Statement

              The University of Connecticut School of Pharmacy and Pharmaceutical Sciences is accredited by the Accreditation Council for Pharmacy Education as a provider of continuing pharmacy education.

              Pharmacists and Pharmacy Technicians are eligible to participate in this knowledge-based activity and will receive up to 1 CE Hours (or 0.1 CEUs)  for completing the activity ACPE UAN 0009-0000-26-011-H06-P, passing the quiz with a grade of 70% or better, and completing an online evaluation. Statements of credit are available via the CPE Monitor online system and your participation will be recorded with CPE Monitor within 72 hours of submission.

              Grant Funding

              There is no grant funding for this activity.

              Faculty

              Thomas E. Buckley, RPh, MPH, FNAP

              Associate Clinical Professor Professor of Pharmacy Practice Emeritus

              University of Connecticut School of Pharmacy and Pharmaceutical Sciences

              Storrs, CT

              Faculty Disclosure

              In accordance with the Accreditation Council for Pharmacy Education (ACPE) Criteria for Quality and Interpretive Guidelines, The University of Connecticut School of Pharmacy and Pharmaceutical Sciences requires that faculty disclose any relationship that the faculty may have with commercial entities whose products or services may be mentioned in the activity.

              • Thomas Buckley, RPh has no relationships with ineligible companies

              Disclaimer

              The material presented here does not necessarily reflect the views of The University of Connecticut School of Pharmacy and Pharmaceutical Sciences or its co-sponsor affiliates. These materials may discuss uses and dosages for therapeutic products, processes, procedures and inferred diagnoses that have not been approved by the United States Food and Drug Administration. A qualified health care professional should be consulted before using any therapeutic product discussed. All readers and continuing education participants should verify all information and data before treating patients or employing any therapies described in this continuing education activity.

              CONTENT

              Posttest

              The Right Tool for the Job: Precision and Preparation in Immunization Practice

              Post-test questions

              26-011

              1. Which statement is TRUE concerning contraindications & precautions?
                1. A person should not receive a vaccine if a contraindication or precaution exists.
                2. If a precaution is present, the decision to vaccinate can be based on a risk/benefit analysis.
                3. Recent exposure to an infectious disease and a current mild illness with a fever is a contraindication to receiving any vaccine.
              2. Which statement is TRUE concerning preventable errors giving vaccines?
                1. Giving a vaccine IM instead of the recommended SC always counts as a valid dose.
                2. Despite being more efficient & reducing pain, never give compatible vaccines in the same injection.
                3. Giving an expired vaccine dose by mistake can always be repeated the same day.
              3. What is the most important factor when administering an IM vaccine injection?
                1. To minimize SIRVA, avoid the upper 1/3 of the deltoid muscle.
                2. Any needle length and gauge size can be used for adults and children.
                3. Having the patient standing avoids a syncope reaction.
              4. Which statement is TRUE concerning documentation & error reporting of vaccines?
                1. Reporting an error to VAERS is done only for serious errors attributable to the vaccine.
                2. CT-WiZ is an online portal for the secure protection of pediatric vaccine inventories.
                3. CT-WiZ is an online portal of immunization records for all CT residents of all ages.
              5. What changes have occurred to ensure reliable vaccine access and information for providers and consumers?
                1. Some states, such as CT, are using medical organization recommendations rather than ACIP for their vaccine standards and reimbursement.
                2. All states are using CDC’s ACIP recommendations for their vaccine standards and reimbursement.
                3. Medical organizations have supported and concurred with ACIP recommendations to ensure consistent vaccine access.


              VIDEO

              Immunization: It is Now Time to Make it Unclear: Reconciling Differences between Public Health Vaccine Recommendations and FDA Product Labeling-RECORDED WEBINAR

              About this Course

              This course is a recorded (home study version) of the CE Finale Encore Webinars.


              Learning Objectives

              Upon completion of this application based CE Activity, a pharmacist will be able to:

              1. Compare and contrast the roles & activities of the Center for Biologics Evaluations and Research (CBER), US Food & Drug Administration (FDA), Centers for Disease Control & Prevention (CDC), and the Advisory Committee on Immunization Practices (ACIP) during the development and clinical use of vaccines in the United States.
              2. Describe one specific example where the routine clinical use of a vaccine may differ from FDA-approved product prescribing information due to the following:

              (a) costs, (b) disease epidemiology, (c) public acceptance, (d) vaccine supplies.

              Release and Expiration Dates

              Released:  December 15, 2023
              Expires:  December 15, 2026

              Course Fee

              $10 Pharmacist

              ACPE UAN

              0009-0000-23-042-H06-P

              Session Code

              23RW42-KXV39

              Accreditation Hours

              1.0 hours of CE

              Additional Information


              How to Complete Evaluation:  When you are ready to submit quiz answers, go to the BLUE take test/evaluation button.

              Accreditation Statement

              The University of Connecticut School of Pharmacy is accredited by the Accreditation Council for Pharmacy Education as a provider of continuing pharmacy education.

              Pharmacists and Pharmacy Technicians are eligible to participate in this application-based activity and will receive up to 1.0 CE Hours (or 0.1 CEUs)  for completing the activity ACPE UAN 0009-0000-23-042-H06-P, passing the quiz with a grade of 70% or better, and completing an online evaluation. Statements of credit are available via the CPE Monitor online system and your participation will be recorded with CPE Monitor within 72 hours of submission.

              Grant Funding

              There is no grant funding for this activity.

              Faculty

              Jeffery Aeschlimann, PharmD
              Associate Clinical Professor-Infectious Disease Specialty
              University of Connecticut School of Pharmacy
              Storrs, CT  

              Faculty Disclosure

              In accordance with the Accreditation Council for Pharmacy Education (ACPE) Criteria for Quality and Interpretive Guidelines, The University of Connecticut School of Pharmacy requires that faculty disclose any relationship that the faculty may have with commercial entities whose products or services may be mentioned in the activity.

              • Dr. Aeschlimann consults with F2G, Inc. but there is no crossover in the topics, so all issues have been mitigated.

              Disclaimer

              The material presented here does not necessarily reflect the views of The University of Connecticut School of Pharmacy or its co-sponsor affiliates. These materials may discuss uses and dosages for therapeutic products, processes, procedures and inferred diagnoses that have not been approved by the United States Food and Drug Administration. A qualified health care professional should be consulted before using any therapeutic product discussed. All readers and continuing education participants should verify all information and data before treating patients or employing any therapies described in this continuing education activity.

              Content

              Handouts

              Post Test


                Immunizations (Aeschlimann) – Post-Test Questions


                1. If asked, which of the following activities would the Food and Drug Administration decline to do and send to another agency?


                1. Verify appropriate vaccine manufacturing processes
                2. Approve advertising for vaccine products Reporting System (VAERS)
                3. Determine the strategy for public use of vaccines in the U.S.


                2.) Which of the following items would you expect to always/very-commonly see in the FDA-Approved product labeling for a vaccine product?


                1. Instructions for preparation of the product and route of administration
                2. Comparative effectiveness data for people taking chronic steroid therapy
                3. Recommendations for use of lower doses in case of product shortages


                3.) Which of the following is a correct example of a vaccination situation for which ACIP has issued “Shared Clinical Decision-making” (SCDM) guidance?


                1. Intranasal influenza vaccine administration in immunocompromised persons
                2. Respiratory syncytial virus vaccination for adults aged 60 years and older
                3. Human papillomavirus vaccination for persons aged 16-21 years


                4.) Which entity ultimately approves the content for FDA vaccine product labeling?


                1. The Vaccines and Related Biological Products Advisory Committee
                2. The Center for Biologic Evaluation & Research
                3. The Center for Drug Evaluation and Research


                5.) Which of the following people would be allowed to sit in the CDC’s Advisory Committee on Immunization Practices (ACIP)?


                1. A member of a vaccine manufacturer’s current Board of Directors
                2. A college professor whose expertise is mechanical engineering
                3. A practicing physician who is an expert in virology and vaccine safety


                6.) What does ACIP recommend after healthcare providers receive a full series of hepatitis B immunizations?


                1. Serologic testing for all healthcare providers at high risk for occupational percutaneous or mucosal exposure to blood or body fluids.
                2. Serologic testing for immunocomproised healthcare providers at high risk for occupational percutaneous of any type.
                3. Molecular testing for all healthcare providers at high risk for occupational percutaneous or mucosal exposure to blood or body fluids.

                VIDEO

                IIMMUNIZATION: Mountebanks, Grifters, and Frauds (Oh My!): An Update on the Management of Vaccine-Preventable Illnesses in 2025-RECORDED WEBINAR

                About this Course

                This course is a recorded (home study version) of the 2025 CE Finale Encore Webinars.


                Learning Objectives

                Upon completion of this application based CE Activity, a pharmacist will be able to:

                • Describe at least one important change (or proposed change) in childhood and adult vaccination recommendations put forth by the CDC and/or ACIP
                • Given a patient who inquires about receiving respiratory virus or bacteria vaccinations (e.g., Influenza, COVID-19, Respiratory Syncytial Virus (RSV), Pneumococcal), outline important differences between multiple products when they exist
                • Identify evidence-based pharmacotherapeutic treatments for common vaccine-preventable illnesses

                Release and Expiration Dates

                Released:  December 19, 2025
                Expires:  December 19, 2028

                Course Fee

                $10 Pharmacist

                ACPE UAN

                0009-0000-25-069-H06-P

                Session Code

                25RW69-MGF85

                Accreditation Hours

                1.0 hours of CE

                Additional Information


                How to Complete Evaluation:  When you are ready to submit quiz answers, go to the BLUE take test/evaluation button.

                Accreditation Statement

                The University of Connecticut School of Pharmacy is accredited by the Accreditation Council for Pharmacy Education as a provider of continuing pharmacy education.

                Pharmacists and Pharmacy Technicians are eligible to participate in this application-based activity and will receive up to 1.0 CE Hours (or 0.1 CEUs)  for completing the activity ACPE UAN 0009-0000-25-069-H06-P, passing the quiz with a grade of 70% or better, and completing an online evaluation. Statements of credit are available via the CPE Monitor online system and your participation will be recorded with CPE Monitor within 72 hours of submission.

                Grant Funding

                There is no grant funding for this activity.

                Faculty

                Jeffery Aeschlimann, PharmD
                Associate Clinical Professor-Infectious Disease Specialty
                University of Connecticut School of Pharmacy
                Storrs, CT  

                Faculty Disclosure

                In accordance with the Accreditation Council for Pharmacy Education (ACPE) Criteria for Quality and Interpretive Guidelines, The University of Connecticut School of Pharmacy requires that faculty disclose any relationship that the faculty may have with commercial entities whose products or services may be mentioned in the activity.

                • Dr. Aeschlimann consults with F2G, Inc. but there is no crossover in the topics, so all issues have been mitigated.

                Disclaimer

                The material presented here does not necessarily reflect the views of The University of Connecticut School of Pharmacy or its co-sponsor affiliates. These materials may discuss uses and dosages for therapeutic products, processes, procedures and inferred diagnoses that have not been approved by the United States Food and Drug Administration. A qualified health care professional should be consulted before using any therapeutic product discussed. All readers and continuing education participants should verify all information and data before treating patients or employing any therapies described in this continuing education activity.

                Content

                Post Test

                1. Which of the following recommendations did ACIP approve in 2025?
                  1. All adults receive single dose thimerosal-free seasonal influenza vaccine formulations free
                  2. State and local jurisdictions should require a prescription for the administration of a COVID-19 vaccination
                  3. COVID-19 vaccination should be administered to all adults 55 and older
                2. Baby Boy Blue develops measles today; the rash is widespread on his body and he cries incessantly. He has three unvaccinated siblings. His mom asks what the contagious period is and how contagious the infection is. What is the CORRECT answer?
                  1. Measles are contagious for roughly five days after the rash’s appearance, and they are not terribly contagious.
                  2. Measles are contagious for plus or minus five days of the rash’s appearance, and they are highly contagious.
                  3. Measles are contagious only in the week before the rash’s appearance, and they are highly contagious.
                3. Mom is surprised and braces herself for all of her children to contract measles; she heard that taking an antiviral will help. She asks if there is a pill that will help. What do you say?
                  1. The FDA has not approved any antiviral therapies to treat measles.
                  2. The most appropriate antiviral is daily vitamin A for at least 14 days.
                  3. She should ask her pediatrician for a prescription for acyclovir.
                4. Mom is very concerned. She asks if there is anything she can do to protect her other children. Is there?
                  1. No, she needs to ride out the storm and rethink her stance on vaccinations.
                  2. Yes, she should ask a family member to host her children until Baby Boy Blue is better.
                  3. Yes, her children can get post-exposure prophylaxis with MMR vaccine within 72 hours
                5. The ACIP panel voted to remove the option to use the MMRV vaccine in children younger than 47 months old. Why?
                  1. ACIP cited slightly higher risks of tonic-clonic seizures for MMRV vs. separately administered doses of MMR & VARIVAX
                  2. ACIP cited slightly higher risks of petit mal seizures for MMRV vs. separately administered doses of MMR & VARIVAX
                  3. ACIP cited a slightly higher risks of fevers/febrile seizures for MMRV vs. separately administered doses of MMR & VARIVAX
                6. Two children of 2700 in a premarketing study experienced seizures after receiving the MMRV vaccine. What other characteristic did they share?
                  1. They appeared to have a concurrent viral illness during vaccination.
                  2. They appeared to have a vitamin A deficit of longstanding duration.
                  3. They appeared to have contracted a cold shortly after vaccination.
                7. How many doses of hepatitis B vaccine are necessary to achieve protection at the 95% level?
                  1. One
                  2. Two
                  3. Three
                8. A 70-year-old male comes to the consultation window of your pharmacy. He would like to receive a vaccination for the flu. His only chronic health issues are hypertension and hypercholesterolemia (both effectively managed). You have three vaccines in stock. Which of the following products would be PREFERRED to administer to this patient?
                  1. Inactivated influenza vaccine (IIV3, Afluria)
                  2. High-dose inactivated influenza vaccine (HD-IIV3, Fluzone High-Dose)
                  3. Adjuvanted inactivated influenza vaccine (aIIV3, Fluad)

                VIDEO

                Immunization: A Quick Refresher: Perfect Intramuscular Injection Technique

                Learning Objectives


                After completing this application-based continuing education activity, pharmacists will be able to

                Review basic intramuscular technique for vaccine administration
                List changes in administration technique that increase safety and decrease patient pain
                Describe the "clean as you go" process that saves time and reduces error

                After completing this application-based continuing education activity, pharmacy technicians will be able to:

                Review basic intramuscular technique for vaccine administration
                List changes in administration technique that increase safety and decrease patient pain
                Describe the "clean as you go" process that saves time and reduces error


                  Release Date: January 9, 2024

                  Expiration Date: January 9, 2027

                  Course Fee

                  FREE

                  There is no funding for this CE.

                  ACPE UANs

                  Pharmacist: 0009-0000-24-005-H06-P

                  Pharmacy Technician:  0009-0000-24-005-H06-T

                  Session Codes

                  Pharmacist:  21YC03-ABC28

                  Pharmacy Technician: 21YC03-CBA24

                  Accreditation Hours

                  1.0 hours of CE

                  Accreditation Statements

                  The University of Connecticut School of Pharmacy is accredited by the Accreditation Council for Pharmacy Education as a provider of continuing pharmacy education.  Statements of credit for the online activity ACPE UAN 0009-0000-24-005-H06-P/T will be awarded when the post test and evaluation have been completed and passed with a 70% or better. Your CE credits will be uploaded to your CPE monitor profile within 2 weeks of completion of the program.


                  Disclosure of Discussions of Off-label and Investigational Drug Use

                  The material presented here does not necessarily reflect the views of The University of Connecticut School of Pharmacy or its co-sponsor affiliates. These materials may discuss uses and dosages for therapeutic products, processes, procedures and inferred diagnoses that have not been approved by the United States Food and Drug Administration. A qualified health care professional should be consulted before using any therapeutic product discussed. All readers and continuing education participants should verify all information and data before treating patients or employing any therapies described in this continuing education activity.

                  Faculty

                  Jill M. Fitzgerald, PharmD
                  Emeritus Associate Professor of Clinical Pharmacy
                  University of Connecticut School of Pharmacy
                  Storrs, CT

                  Jeannette Y. Wick, RPh, MBA
                  Director, Office of Pharmacy Professsional Development
                  University of Connecticut School of Pharmacy
                  Storrs, CT

                  Gabriella Scala
                  PharmD Candidate 2022
                  University of Connecticut School of Pharmacy
                  Storrs, CT

                  Samuel Breiner
                  PharmD Candidate 2021
                  University of Connecticut School of Pharmacy
                  Storrs, CT

                  Faculty Disclosure

                  In accordance with the Accreditation Council for Pharmacy Education (ACPE) Criteria for Quality and Interpretive Guidelines, The University of Connecticut School of Pharmacy requires that faculty disclose any relationship that the faculty may have with commercial entities whose products or services may be mentioned in the activity.

                  Jill Fitzgerald, Samuel Breiner,  Gabriela Scala and Jeannette Wick have no relationships with ineligible companies.


                  ABSTRACT

                  Over the next months, we expect that more people will receive intramuscular vaccines than ever before. Many pharmacists and in some cases, pharmacy technicians, will mobilize to help with the immunization efforts. Some will take training for the first time, and others will have been trained but rusty. This activity reviews the best practices associated with intramuscular injection. UConn School of Pharmacy is providing this continuing education activity free as a public service.

                  CONTENT

                  Content

                  INTRODUCTION

                  As the healthcare community mobilizes and begins vaccinating to prevent the spread of coronavirus-SARS-19, pharmacists and in many places pharmacy technicians will be called to assist. In an effort to engage Americans in the program and encourage vaccination, the media is full of stories and videos of people receiving vaccinations. We at the University of Connecticut School of Pharmacy have watched with great interest, reading national newspapers and watching television clips about vaccination. One comment posted in response to an article in the New York Times caught our attention. Someone who dubbed herself “Retired Nurse” wrote the following comments1:

                  “As for sore arms, I am not surprised. The wide variation in injection techniques displayed on television have been horrendous: Slow, tentative needle insertions, not stabilizing the site, too high up in the shoulder, exceptionally large needle lengths in tiny arms, etc. make me cringe. Hilariously, they showed doctors ceremoniously giving some of them on television but let's be honest, most physicians do not routinely administer shots. That task is delegated to a nurse or even a medical assistant in doctors' offices in many states. A vaccination can be a lot less painful, if not virtually painless, with good injection training.”

                  We could not agree more, and as we prepare to train people from a number of professions in our state, we decided to create this short continuing education homestudy to help you review injection technique and stay abreast of the most recent developments.

                  Intramuscular Injections

                  Vaccines administered in pharmacies are generally given by one of two routes: (1) intramuscularly, or (2) subcutaneously. Most (but not all) immunizations are given intramuscularly. Most inactivated vaccines are administered intramuscularly in the deltoid, whereas all live-attenuated injectable vaccines are administered subcutaneously in the anterior arm (midway between the elbow and armpit).2 An exception of a common inactivated vaccine given subcutaneously would be meningococcal vaccine. To date, the available COVID-19 vaccines are all given intramuscularly. Intramuscular (IM) injections are exactly what the name implies – they are injections given into a muscle using a syringe.

                  Let’s review the parts of the syringe very quickly. A syringe has three primary parts. The needle, the barrel, and the plunger (see Figure 1). The needle is also called the “sharp,” and for vaccines, it’s a very fine needle. This is the distal part of the syringe that penetrates the skin. The barrel is the tube that holds the vaccine, and it has markings similar to that on a ruler. In most cases, the barrel measures milliliters (mL). The plunger is the plastic device used to pull the vaccine into and push the vaccine out of the syringe.

                  Cartoon showing the sections of a syringe, including needle, hub, barrel, and plunger

                  An important area of the syringe is called the hub or the hilt. This is the place where the needle meets the barrel. When penetrating the skin, you will push the needle all the way to the hub or the hilt. Before you inject, the entire needle will be in the skin and the muscle – you won’t be able to see any of the metal needle. Many people worry that they will hit the patient’s bone. It’s a comfort to know that if you hit the bone, you will feel it. The patient will not. This is a word-for-word explanation that our peer reviewer and authors like3:

                  "Needle length should be chosen based on the body habitus and weight of the patient. A needle that is too long can penetrate the deltoid muscle, hitting the bone. Although patients will not feel their bones being hit, the vaccine might not fully absorb into the muscle, leading to a reduced immune response. Furthermore, if the needle is too short the vaccine might be administered subcutaneously, which might result in decreased immune response and the development of nodules or cellulitus."

                  Good Technique

                  Good technique starts with preparation. Before you start administering vaccines, it’s essential that you prepare and anticipate how many patients you’ll see and what their needs will be. A cornerstone of good technique is knowing exactly how you will document. Especially with the COVID-19 vaccine, knowing how to document will be essential. Our understanding is that a new Vaccine Administration Management System has been developed to capture that data. When you arrive at your site, and eventually when the vaccine is available in your pharmacy, someone should train you on how to use the Vaccine Administration Management System. As with all vaccines, you’ll need to document the patient’s name, the vaccine’s lot number and expiration date, and where you gave the vaccine (left deltoid, right deltoid, etc.).4 And here is a quick aside: Many pharmacies don’t do a good job of documenting vaccines they give in their medication systems. Be certain to know what documentation is necessary, either in addition to or instead of Vaccine Administration Management System. For instance, health systems will require documentation in their electronic medical records or pharmacy system.

                  Before you start, survey your area and ensure that the station at which you vaccinate has a sufficient amount of supplies. Table 1 lists items that you need at your station at all times and items you have to have ready for each patient. One thing we wish to emphasize is a technique that one of our students taught us. When you have gloves on, it’s very difficult to open a Band-Aid and apply it. In anticipation of needing it, if you peel back the outer wrapper before you start, it will be much easier to use the Band-Aid should you need it after vaccination.  Some people even place the small opened section of the bandage on the patient’s skin right next to where they will inject, so it’s easy access. And note that often, if you have good technique, the patient will not bleed. But use a Band-aid in case they “spring a leak” later.

                  Table 1. Necessary Supplies for Immunization4,5

                  Always at Your Station Have Ready for Each Patient
                  •        A sharps container

                  •        A handy trash can

                  •        Band-Aids

                  •        Cleaning solution

                  •        Your personal protective equipment (mask, face shield, gloves)

                  •        A box of tissues


                  •        One alcohol wipe

                  •        One sterile 2 x 2 gauze pad

                  •        A new needle and syringe that are the correct size

                  •        A clean pair of disposable gloves (for you to wear) for each patient

                  •        A Band-Aid, partially open


                  Next, commit to cleaning as you go. Have you ever noticed that when you go to any fast food restaurant, it is always clean and organized? That’s because they teach their staff to clean as they go. This lesson, when employed in our homes and in our workplaces, is extremely useful. It’s especially useful when you are immunizing many people. You don’t accumulate trash that has to be picked up later. This process has three key points when it comes to immunization4,5:

                  • Throw paper and miscellaneous trash away immediately. What this means is if you take the cap off the needle, throw it in the trash immediately. You won’t be using the cap because we don’t recap needles any longer. Throwing it in the trash ensures you won’t be tempted to recap the needle. Similarly, any paper trash generated from anything that you open should go into the trash can immediately.
                  • After you inject and withdraw the needle from the muscle, activate the safety device on the needle using a hands-free method immediately.
                  • Place used needles or sharps in the sharps container as soon as you finish with them. Do not place the used syringe on your work area even for a moment. Put it in the sharps container. (Yes, we are stressing this point!)

                  Have a Seat, Please

                  It’s critical for patients to be seated when you give injections. Ideally, you should be seated also and we will discuss why below. Ask patients to relax their arms. They can place their palms on their legs or dangle their arms at the sides. Completely expose the upper arm and find your upside-down triangle target area of the deltoid muscle. If administering more than one vaccine in the same arm, separate the injection sites by one inch so that any local reactions can be differentiated.6

                  As we implied above, for most adults, we administer the COVID-19 and most other IM vaccines in the upper arm. This is the location of the deltoid muscle. You will give the injection in the center of an upside-down triangle. To give the vaccine, completely expose the patient’s upper arm, and feel for the bone that goes across the top of the upper arm. This is the acromion process. The bottom of the acromion process is the flat edge of the inverted triangle (see Figures 2 and 3).5 The triangle points down. It ends at about the level of the armpit. You will inject into the lower two thirds of the deltoid. Note that giving injections in the upper third of the deltoid can damage the muscle and cause inordinate pain.7-9

                  Graphic showing the bones of the shoulder, including acromion


                  Drawing of person showing the deltoid injection area, which is an upside-down triangle in the mid-shoulder

                  Shoulder injury related to vaccine administration (SIRVA) is an emerging concern. 3,7-9 This occurs when immunizers inject vaccines into the subdeltoid bursa or within the joint space. SIRVA causes shoulder pain and limited range of motion within 48 hours after IM vaccine administration.10,11 Experts advise immunizers to avoid administering vaccines in the top one-third of the deltoid. Studies show that immunizers who sit and administer vaccines to seated patients, using needles of the appropriate length, reduce the risk of SIRVA.7,8,12

                  Let’s get more specific. The correct area to give an injection is in the center of the triangle. You would inject one to two inches or two to three finger widths below the lower edge of the acromion process.5,14 Gently stretch the skin around the injection site with your non-dominant hand. This displaces the subcutaneous tissue, aids needle entry and reduces pain. Insert the needle at a 90 degree angle, all the way to the hub. Depress the plunger at a rate of 1 second for every 0.1 ml of fluid.13 Again, avoid injecting too close to the top of the arm. Don’t use this site if a person is very thin or the muscle is very small. In these cases, it’s better to inject into the anterolateral thigh.4 The SIDEBAR describes considerations when selecting needles size and length.

                  A final word before we go to the actual injection process. Please don’t say, “This will not hurt a bit!” People have very different thresholds for pain and it’s impossible to predict whether it will hurt. Develop some language that you are comfortable with, and use it. A good response of people who ask if it will hurt is to say, “It may hurt or sting a little but just for a minute or two.”

                  Prepare yourself before you give an injection by using personal protective equipment, and using it correctly.4 During the pandemic, we advise covering your nose and your eyes, keeping your hands away from your face, and washing your hands often. Practice good hygiene before and after immunizing each patient. Do not wear the same set of gloves for more than one patient. Change gloves between patients and wash your hands and sanitize (and let dry) before putting on a new pair of gloves.4,5

                  SIDEBAR: Choosing the Right Needle4,5,14-17

                  Immunizers will administer current COVID-19 vaccine from Pfizer and Moderna using needles that fall in the ranges of 22-25 gauge and 1-1.5 inches in length. Remember, the higher the gauge, the finer the needle! The Pfizer COVID vaccine is currently approved for ages 16 and older while the Moderna vaccination has approval for ages 18 and older. CDC vaccination recommendations on needle gauge and length are consistent with current Pfizer and Moderna recommendations. The table below summarizes CDC recommendations on general needle gauges and lengths for IM injections based on age.

                  Chart showing CDC recommendations on needle gauge and length based on age and weight

                  Although we may be injecting 1 to 1.5-inch needles into patients' deltoids now, our near future will consist of younger and frail patients. This may require use of shorter needles (i.e., 5/8 inch) and a different injection site - that being the vastus lateralis (a muscle on the outer thigh).

                  Ready, Set, Go

                  Let’s go through the process twice and review first the general procedure, then some specifics.

                  Here are the steps4,14:

                  • First, open the alcohol wipe. Wipe the area where you plan to give the injection.
                  • Prepare the needle.
                  • Hold (stretch) the skin around where you will give the injection.
                  • Insert the needle into the muscle at a 90° angle, all the way to the hub.
                  • Inject the vaccine at a rate of 0.1 ml per second.
                  • Remove the needle at the same 90 degree angle.

                  Now let’s review some nuances.4,5,14

                  • First, open the alcohol wipe. Wipe the area where you plan to give the injection. Wiping in a circular motion from the center out sometimes increases circulation and desensitizes the area. However, there’s no need to scrub. Just wipe firmly and dispose of the used alcohol wipe and its wrapper. Let the area dry (approximately 30 seconds) and do not blow on or touch the area until you give the injection.
                  • Prepare the needle. Hold the syringe with your dominant hand and pull the cover off with your other hand. Throw the cover in the trashcan immediately so you are not tempted to recap. Place the syringe between your thumb and first finger (like a dart). Let the barrel of the syringe rest on your finger.
                  • Hold the skin around where you will give the injection. With your free hand, which is also your non-dominant hand, gently press on the skin and pull it so that it’s slightly tight. Experts recommend two different ways of doing this. One is to make a “C” with your nondominant hand and stretch the skin between your first finger in your thumb. The second is to use the outer edge of you hand below the pinkie finger and pull the patient’s skin taut by pushing toward the outer edge of the arm (toward your non-dominant hand).
                  • Insert the needle into the muscle. Hold the syringe barrel tightly and inject the needle through the skin and into the muscle at a 90° angle.
                  • Inject the vaccine. Push down on the plunger and inject the medicine using your index finger. Push firmly and steadily at a rate of about 0.1 mL per second. Note that the Pfizer COVID-19 vaccine is only 0.3 mL, so you can inject it in about three seconds. The Moderna COVID-19 vaccine is a 0.5 mL volume, so it will take five seconds to inject.
                  • Remove the needle. Once you have injected the vaccine, remove the needle at exactly the same angle as you used for it to go in – that is, 90°. Activate the safety device and dispose of the entire syringe in your sharps container. You can place gauze over the area where you give the injection or cover the injection site with a Band-Aid (do not massage the area).

                  SIDEBAR: Needle Safety4,18

                  Now let's quickly discuss how we can keep ourselves safe while immunizing. The CDC estimates that 590,194 needlestick injuries occur annually in all healthcare settings. Immunizing exposes pharmacists to an increased risk of needlestick injury and transmission of bloodborne disease, with the most dangerous being hepatitis B, hepatitis C, and HIV. Therefore, if we are to know the perfect technique to immunize we must also know the perfect technique to keep ourselves safe.

                  Prevention is key to avoiding needlestick injury. Prevention includes:

                  • NEVER recapping needles by hand (if you absolutely must recap a syringe by hand, use a one-handed method and scoop the cap onto the needle. That is, place cap on a flat surface, remove your hand from the cap, insert the syringe needle tip deep into the cap, and press the tip of the cap against an inanimate object to secure it in place)
                  • Disposing of used needles in sharps containers
                  • Use needles with safety features, called "engineered injury protection"
                  • NEVER handing a syringe with an uncapped needle to someone else

                  If a needlestick injury should occur, you must be equipped with the knowledge of what to do next.

                  • Needlestick/cut: wash with soap and water
                  • Splashed on skin or in nose or mouth: flush with water (soap if possible)
                  • Splashed in eyes: irrigate with clean water, saline, or sterile irrigants

                  Be sure to report the incident to your supervisor and seek medical treatment to discuss possible risk of exposure or need for post-exposure treatment. Keeping ourselves safe is just as important as keeping our patients safe.

                  Refining Technique

                  So now we’ve reviewed the step-by-step process for giving an IM vaccine. Let’s talk about a few points that will refine your technique and make you a real pro.

                  As we prepare to vaccinate an entire nation, pharmacists will be working side-by-side with people from many different healthcare disciplines. In fact, we may be working with people who are not healthcare providers but have simply been trained to administer immunizations. From our experience, we have learned that conflict sometimes arises because healthcare practitioners trained in different disciplines have different ways of doing things. Our intent is to follow the most recent expert advice and use best practices. For that reason, we want to point out a few things that are either so new that others may not be aware of them or different from what you may see or hear at immunization sites.

                  First, some helpful observers may tell you that you need to aspirate before you inject. For many years, many healthcare professionals were trained to aspirate – meaning after the needle is in the muscle, the immunizer will pull back on the plunger and see if they draw up any blood. This is an outdated practice.14 The Centers for Disease Control and Prevention indicates that aspiration is unnecessary and unwarranted when administering vaccines. They indicate, “Aspiration before injection of vaccines or toxoids (i.e., pulling back on the syringe plunger after needle insertion but before injection) is not necessary because no large blood vessels are present at the recommended injection sites, and a process that includes aspiration might be more painful for infants.”4,19  Should another provider approach you and criticize your technique, telling you that you need to aspirate, feel free to educate them about the proper way to give a vaccine!

                  Second, while you are going through the immunization steps, you can help patients relax and build some confidence if you talk to the patient. A little chitchat will help patients feel comfortable. We probably don’t need to say this but we will: Stick with safe topics. Some good questions are things like, “Do you have a pet?” or “It’s really cold today, isn’t it?” Remember that it’s best to use open-ended questions once you get the conversation started, with open-ended questions being those that cannot be answered with a yes or a no. For example, if the patient responds affirmatively to your question about pets, keep the ball rolling by saying “What kind of pet do you have?” If you’re talking about the weather, you can ask the patient what his or her favorite season is, or what they like about rainy days. Asking, “What’s for dinner tonight?” is also of great conversation starter. It will also give you some ideas for your own supper!

                  Next, let’s talk about skin that is not clear or is discolored. Ideally, we would want to inject into an area of the skin that is clear. You should never inject into broken skin, moles, or rashy areas. While you can inject into tattooed skin, we advise against it. The reason for this is the same as the reason that we inject into the clear areas of the skin: we want to be able to see a local reaction if it develops.4

                  Finishing Up

                  Finally, we are ready to finish the process. Once you’ve administer the vaccine, you’ll need to direct patients about their next steps and what they need to do. With the current COVID-19 vaccines at the current time, patients need to stay at the immunization site for 15 minutes for observation or as directed by your site’s specific policy.20 This may change as we administer significantly larger numbers of vaccinations. Older pharmacists were trained to provide a vaccine fact sheet to every patient they immunize. That practice seems to be site-specific at this point, so if your site requires a vaccine fact sheet be given to patients, do that.

                  Review your documentation, and make sure that you have completed it entirely. This is critical for the COVID-19 vaccines because at some point, patients may need to prove that they were vaccinated to engage in certain activities. Take a few minutes to ensure that you have completed the documentation and submitted it appropriately.20

                  A last PRO TIP is to take a minute to look at your station. Ensure that you have enough supplies to continue immunizing patients. Do not overfill your sharps containers. Know where the “FULL” line is. When they are close to full ask for or retrieve an empty container as a backup. Sanitize the area as directed by your site in preparation for the next patient.

                  CONCLUSION

                  Even the most proficient immunizer sometimes faces dilemmas in the immunization clinic. A final PRO TIP is indispensable: If at any time you encounter a problem and you are unsure or uncomfortable, find a more experienced immunizer and ask for help. We see all kinds of issues when we immunize—people who experience vasovagal syndrome (faint at the sight or thought of needles), people who are very thin or obese, people who have latex allergies and need to know if the vial’s stopper contains latex (neither the Pfizer or Moderna vaccine vials do). Finding someone with more expertise or simply collaborating with others to plan an approach is smart. It important to do your best to ensure the patient receives the vaccine; if you turn a patient away, he or she may not return.


                  Pharmacist and Pharmacy Technician Post Test (for viewing only)

                  Post Test

                  Immunization: A Quick Refresher: Perfect Intramuscular Injection Technique

                  1. When injecting a vaccine into the deltoid muscle, which area should you be certain to AVOID?
                  A. The lower 1/3 of the upside-down triangle in which the acromion process is the top edge
                  B. The middle 1/3 of the upside-down triangle in which the acromion process is the top edge
                  C. The upper 1/3 of the upside-down triangle in which the acromion process is the top edge
                  2. You have completed the steps necessary to prepare for injecting a vaccine. You are almost ready to insert the needle into the patient’s arm. What is the LAST STEP before inserting the needle?
                  A. Pinch the skin on both sides so it makes a “mountain” and inject into the scrunched skin
                  B. Use your non-dominant hand to pull the skin in one direction away from the injection site
                  C. Tell the patient that it will not hurt and inject in whatever way is most comfortable for you

                  3. After injecting the vaccine, removing the needle, activating the safety mechanism, and discarding the syringe in the sharps container, what should you do to ensure the medication is absorbed?
                  A. Nothing. If you have used good injection technique, your job is done!
                  B. Massage the area for approximately one or two minutes.
                  C. Apply a hot compress and have the patient hold it there for 15 minutes.

                  4. How quickly do most guidelines recommend to inject vaccines?
                  A. 1 mL/second
                  B. 0.1 mL/second
                  C. 0.01 mL/second

                  5. Why does the Advisory Committee for Immunization Practices recommend AGAINST aspiration when injecting vaccines?
                  A. It increases risk of bleeding that will be difficult to stop
                  B. It causes vaccine to leak from the muscle and decreases effectiveness
                  C. No large blood vessels are present at the recommended injection sites

                  6. Which of the following are the MOST COMMON bloodborne pathogens?
                  A. Hepatitis B, hepatitis C, and HIV
                  B. Influenza, coronavirus, and HIV
                  C. Pneumonia, pinkeye, and staphylococcus

                  7. Which of the following statements is TRUE?
                  A. Always recap needles by hand
                  B. Dispose of used needles in trash receptacles
                  C. Use needles with safety features

                  8. If you absolutely must recap a syringe by hand, how many hands should you use?
                  A. One
                  B. Two
                  C. Three (get someone else to help)

                  9. You are prepared to inject a vaccine and have uncapped the needle, and thrown away the cap. Your team leader enters the room and says she needs you immediately to answer some questions about your last patient. She has brought another immunizer to take over your station for 15 minutes. Which of the following is the BEST way to proceed?
                  A. Hand the syringe with the uncapped needle to your replacement so he can finish this patient’s vaccination and leave with the team leader.
                  B. Fish around in the trash can, find the cap, and recap the needle, and give the now-capped needle to your replacement to finish with this patient.
                  C. Tell the team leader that you have discarded the cap, and suggest you finish with your current patient since it will only be a few seconds.

                  10. You inadvertently squirt something from a used syringe into your eye. What do you do?
                  A. Irrigate with clean water, saline, or sterile irrigants
                  B. Wash with soap and water
                  C. Flush with detergent and water

                  11. Which of the following would be considered an “engineered injury protection”?
                  A. Syringes with sliding sheath that shields the attached needle after use
                  B. Using an open container in which to dispose used needles
                  C. Asking employees for input on what needles they prefer

                  12. Select the statement that is TRUE for the current Pfizer and Moderna vaccines:
                  A. Both vaccines do not come with administration devices
                  B. Both must be stored in the refrigerator until 15 minutes before use
                  C. Both require needles that are 22-25 gauge and 1-1.5 inches in length

                  13. You greet a patient and ask him to uncover his deltoid. As you assess him, you notice that he must weigh at least 350 pounds. Which factor needs to be adjusted before you administer the vaccine?
                  A. The dose
                  B. The needle gauge
                  C. The needle length

                  14. Your patient looks at the syringe, pales, and begins to shake. She tells you that she has a “vasovagal” reaction to needles. You do not know what this means. What is the BEST way to proceed?
                  A. Distract her with idle chit-chat
                  B. Find a more experienced immunizer
                  C. Tell her she will have reschedule

                  15. Patients can be quirky. Your current patient wants to stand to receive the vaccination. What is the BEST explanation for why both of you should sit?
                  A. Immunizers who sit and administer vaccines to seated patients reduce the risk of injury to the patient’s shoulder.
                  B. Immunizers who sit and administer vaccines to seated patients reduce the risk of needlestick injury to the immunizer.
                  C. Immunizers who stand and administer vaccines to seated patients reduce the risk of the patient fainting.

                  16. Your patient is heavily tattooed. In this training, we emphasized the importance of finding the area of clearest skin. Why?
                  A. We want to be able to see a local reaction if it develops.
                  B. Injecting into tattooed skin is more painful for the patient.
                  C. Current COVID vaccines cannot be given in a tattooed area.

                  17. What is the proper angle to give an IM injection?
                  A. 45o
                  B. 90o
                  C. Inject at 45o, withdraw at 90o.

                  18. Which of the following questions should you be prepared to answer in case a patient asks?
                  A. Does the vaccine’s vial have plastic in the stopper?
                  B. Does the vaccine’s vial have latex in the stopper?
                  C. Does the vaccine come in a multidose vial?

                  19. What is the BEST position for a patient’s arm while you are giving an IM injection?
                  A. Relaxed with palms on legs or arm dangling at sides
                  B. Taut with the patient squeezing a rubber ball
                  C. Flexed as if they were showing you the size of their deltoid

                  20. You’ve vaccinated a patient with a COVID vaccine, disposed of the sharp, and finished your task. What is the BEST thing to tell the patient?
                  A. Thanks for doing this, your nation appreciates you.
                  B. See you for the follow-up dose in six weeks!
                  C. Please remain in the clinic for 15 minutes.

                  References

                  Full List of References

                  References

                     
                    1. Harmon A. What the Vaccine Side Effects Feel Like, According to Those Who’ve Gotten It. Available at https://www.nytimes.com/2020/12/28/us/vaccine-first-patients-covid.html. Accessed December 30, 2020.
                    2. Wick JY. Immunization: Tips, tools, and total success. Available at https://www.pharmacytimes.com/publications/issue/2016/August2016/Immunization-Tips-Tools-and-Total-Succes. Accessed January 2, 2020.
                    3. Bancsi A, Houle SKD, Grindrod KA. Getting it in the right spot: Shoulder injury related to vaccine administration (SIRVA) and other injection site events. Can Pharm J (Ott). 2018;151(5):295-299.
                    4. Centers for Disease Control and Prevention. Vaccine administration. Available at https://www.cdc.gov/vaccines/hcp/acip-recs/general-recs/administration.html. Accessed December 30, 2020.
                    5. Centers for Disease Control and Prevention. Vaccine Administration: Intramuscular (IM) Injection Children 7 through 18 years of age. Available at https://www.cdc.gov/vaccines/hcp/admin/downloads/IM-Injection-children.pdf. Accessed December 30, 2020.
                    6. Centers for Disease Control and Prevention. Adminster the vaccines. Available at https://www.cdc.gov/vaccines/hcp/admin/administer-vaccines.html. Accessed January 3, 2021.
                    7. Bodor M, Montalvo E. Vaccination-related shoulder dysfunction. Vaccine. 2007;25(4):585-587.
                    8. Atanasoff S, Ryan T. Lightfoot R, Johann-Liang R. Shoulder injury related to vaccine administration (SIRVA). Vaccine. 2010;28(51):8049-8052. doi: 10.1016/j.vaccine.2010.10.005.
                    9. Cook IF. Subdeltoid/subacromial bursitis associated with influenza vaccination. Hum Vaccin Immunother. 2014;10(3):605-606. doi:10.4161/hv.27232.
                    10, National Vaccine Injury Compensation Program (VICP). Prevention of SIRVA. Health Resources and Services Administration website. Available at hrsa.gov/advisorycommittees/childhoodvaccines/meetings/20150604/sirva.pdf. Accessed December 30, 2020.
                    11. Cross GB, Moghaddas J, Buttery J, Ayoub S, Korman TM. Don’t aim too high: avoiding shoulder injury related to vaccine administration. Aust Fam Physician. 2016;45(5):303-306.
                    12. Kroger AT, Sumaya CV, Pickering LK, Atkinson WL. General recommendations on immunization: recommendations of the Advisory Committee on Immunization Practices (ACIP). MMWR Morb Mortal Wkly Rep. 2011;60(RR02):1-60.
                    13. : Dougherty L, Lister S (2015) The Royal Marsden Hospital Manual of Clinical Nursing Procedures. Oxford: Wiley-Blackwell.
                    14. Immunize.org. How to administer intramuscular and subcutaneous vaccine injections. Avaialble at https://www.immunize.org/catg.d/p2020.pdf. Accessed January 3, 2021.
                    15. Centers for Disease Control and Prevention. Moderna COVID-19 vaccine. Available at https://www.cdc.gov/vaccines/covid-19/info-by-product/moderna/downloads/standing-orders.pdf. Accessed January 3, 2021.
                    16. Centers for Disease Control and Prevention. Pfizer-BioNTech COVID-19 Vaccine. Available at https://www.cdc.gov/vaccines/covid-19/info-by-product/pfizer/downloads/prep-and-admin-summary.pdf. Accessed January 3, 2021.
                    17. Centers for Disease Control and Prevention. Vaccine administration: Needle gauge and length. Available at https://www.cdc.gov/vaccines/hcp/admin/downloads/vaccine-administration-needle-length.pdf. Accessed January 3, 2021.
                    18. U.S. Government Printing Office. Needlestick Safety and Prevention Act. Available at http://www.gpo.gov/fdsys/pkg/PLAW-106publ430/html/PLAW-106publ430.htm. Accessed January 3, 2021.
                    19. Ipp M, Taddio A, Sam J, Gladbach M, Parkin PC. Vaccine-related pain: randomised controlled trial of two injection techniques. Arch Dis Child. 2007;92(12):1105-1108. DOI: 10.1136/adc.2007.118695
                    20. Centers for Disease Control and Prevention. Resource library. Available at https://www.cdc.gov/vaccines/hcp/admin/resource-library.html. Accessed January 3, 2021.