Archives

A Team Effort: Helping Patients Manage Low Back Pain

Learning Objectives

After completing this continuing education activity, pharmacists will be able to

  • Classify common causes and types of low back pain
  • Recognize red-flag symptoms requiring referral or evaluation
  • Compare pharmacologic and nonpharmacologic low back pain treatments
  • Explain self-care and prevention strategies to patients who have low back pain

After completing this continuing education activity, pharmacy technicians will be able to

  • Identify common causes and risk factors for low back pain
  • Recognize symptoms that require pharmacist referral
  • Describe common medications and supportive therapies for low back pain
  • Explain safe self-care and prevention for low back pain

    a man is turned away in pain, holding this lower back with his hands. A red area glows through his shirt denoting pian.

     Release Date

    Release Date: September 15, 2026

    Expiration Date: September 15, 2029

    Course Fee

    $7 Pharmacist

    $4 Pharmacy Technician

    There is no funding for this CE.

    ACPE UANs

    Pharmacist: 0009-0000-26-043-H08-P

    Pharmacy Technician: 0009-0000-26-043-H08-T

    Session Codes

    Pharmacist: 26YC43-OHW18

    Pharmacy Technician: 26YC43-WOH81

    Accreditation Hours

    2.0 hours of CE

    Accreditation Statements

    The University of Connecticut School of Pharmacy and Pharmaceutical Sciences is accredited by the Accreditation Council for Pharmacy Education as a provider of continuing pharmacy education.  Statements of credit for the online activity ACPE UAN 0009-0000-26-043-H08-P/T will be awarded when the post test and evaluation have been completed and passed with a 70% or better. Your CE credits will be uploaded to your CPE monitor profile within 2 weeks of completion of the program.


    Disclosure of Discussions of Off-label and Investigational Drug Use

    The material presented here does not necessarily reflect the views of The University of Connecticut School of Pharmacy and Pharmaceutical Sciences or its co-sponsor affiliates. These materials may discuss uses and dosages for therapeutic products, processes, procedures and inferred diagnoses that have not been approved by the United States Food and Drug Administration. A qualified health care professional should be consulted before using any therapeutic product discussed. All readers and continuing education participants should verify all information and data before treating patients or employing any therapies described in this continuing education activity.

    Faculty

    Jennifer Kuivinen, BSPharm, RPh., CIP

    Recent graduate of UConn’s Medical Writing Certificate Program

    Alanson, MI

    Faculty Disclosure

    In accordance with the Accreditation Council for Pharmacy Education (ACPE) Criteria for Quality and Interpretive Guidelines, The University of Connecticut School of Pharmacy and Pharmaceutical Sciences requires that faculty disclose any relationship that the faculty may have with commercial entities whose products or services may be mentioned in the activity.

    Jennifer Kuivinen has no relationships with ineligible companies.


    ABSTRACT

    Low back pain is one of the most common causes of pain, disability, and reduced quality of life worldwide. Because the lumbar spine contains many muscles, bones, joints, discs, and nerves, determining the source of pain can be difficult. Most episodes improve with conservative care, but recurrent or poorly managed low back pain can progress to chronic pain, functional limitation, anxiety, depression, and work impairment. Pharmacists frequently encounter patients seeking relief with nonprescription medications, prescription therapies, topical products, supplements, or alternative treatments. This continuing education activity reviews common causes and types of low back pain, red-flag symptoms requiring referral, pharmacologic and nonpharmacologic treatment options, and self-care strategies. Pharmacy technicians can also support care by recognizing when patients with back pain should be referred to the pharmacist for counseling or medical triage.

    CONTENT

    Content

    INTRODUCTION

    Many pharmacy job sites require pharmacists and technicians to spend several hours standing. What’s the worst that could happen standing upright for hours or bent over a counter? It’s not like an athlete in a contact sport that significantly increases the risk of injury and pain. Or is it? Add a previous injury, a genetic predisposition, just time, or wear and tear and you, too, could be forced out of the job or game. Affecting close to 16 million adults in the United States (U.S.), back pain is the most common medical condition and the primary cause of disability globally.1


    Lasting for days, weeks, months, or years, back pain (also known as lumbago; see the SIDEBAR) can be challenging for patients and difficult for healthcare providers to diagnose and treat. Similarly, the game of baseball can be variable in duration, and the rules of the game can seem difficult to understand. The plethora of treatment options for back pain can seem overwhelming to patients. Using the game of baseball as an analogy, this continuing education activity will consider each base a different treatment modality. As the patient, or player, advances to the next plate, various supportive staff must provide direction.

    • First base covers the variety of medications used to treat low back pain (LBP)
    • Second base describes functional therapy
    • Third base explains interventions
    • The outfield represents alternative treatment options
    • Home plate signifies improvement in LBP factors that include life with decreased pain, patients acquiring the knowledge to prevent future flares, a return to daily functions, and improvement of anxiety and depression.

    This activity highlights the various causes and treatments available so pharmacists and technicians can help patients navigate treatment choices and cope with LBP. Advancing to home plate is the goal. Let’s play lumbago!


    SIDEBAR: Lumbago!2


    “Lumbago” is an old-fashioned medical and lay term for pain in the lower back (the lumbar region). It comes from the Latin lumbus (“loin” or lower back). Historically, physicians used it broadly for almost any LBP without specifying the cause. Today, most clinicians prefer more precise terms such as:

    • low back pain
    • lumbar strain
    • lumbar radiculopathy
    • herniated disc
    • sciatica (if nerve pain radiates down the leg)


    You’ll still encounter the term “lumbago” in older books or films, humorously (“my lumbago is acting up again”); among some older adults, and occasionally in insurance or historical medical records. The word also survives in pop culture. For example, the character Uncle in the video game Red Dead Redemption 2 repeatedly complains about having “lumbago” when asked to do work.


    Modern medicine generally considers it a vague, nonspecific term rather than a diagnosis.


    STARTING LINEUP

    Affecting one in 13 people globally, LBP was estimated to affect 619 million people in 2020.3 Since 1990, cases have increased by 60% due to the aging population and population growth with low and middle-income countries experiencing the largest increase, primarily in the continents of Africa and Asia. Statisticians consider LBP the main cause of disability globally including all ages and both sexes, however its frequency is higher in females and people 70 years and older. Cases of LBP are expected to increase by 36% to 843 million people by 2050.3 Table 1 lists factors that increase the risks of LBP.


    Table 1. Risk Factors for Low Back Pain4, 5,6

    Physical Psychological Lifestyle
    Age Anxiety or depression Alcohol consumption
    Sex, with women more likely to experience symptoms Fear of bodily activities that lead to bodily harm or pain Obesity
    History of back injury Long term mental stress Smoking
        Working a physically demanding job


    ALL-STAR PATHOLOGY, THE LBP LEAGUE

    A summer tradition since 1933, American professional baseball teams of the National League and American League select their most prestigious players to play in the All-Star Game each July.7 Currently, each league contains 15 teams. LBP is classified into four different “leagues”: specific or non-specific, spinal or non-spinal.


    Because LBP is classified as specific or non-specific, healthcare providers focus on determining the cause of the pain. Examples of specific LBP include

    • pain generated by a disease
    • structural issues in the spine
    • pain that flows from another area of the body

    The non-specific category of LBP is defined as unidentifiable and unexplainable and it unfortunately accounts for 90% of LBP.8


    LBP is also categorized into spinal and non-spinal origins.9 Table 2 lists examples of spinal and non-spinal conditions. Among specific spinal causes of LBP, disorders with nerve-root involvement occur more often than other specific spinal causes. The most frequent causes of LBP in the specific spinal category are herniated disk and spinal stenosis. compared to other spinal causes,  herniated disk and spinal stenosis have elevated prevalence rates of 5% to 10%.10


    Table 2. Low Back Pain Classification5,9,10

    Non-spinal Spinal
    Aortic aneurysm Arthritis
    Endometriosis Axial spondyloarthritis
    Fibromyalgia Disc degeneration
    Hip conditions Fracture
    Kidney stones Herniated disk
    Pregnancy Infection
    Prostatitis Osteoporosis
    Psychological disorders Skeletal irregularities
    Tumors with other origins than spine Spina bifida
      Spinal stenosis
      Spondylolisthesis
      Tumor
      Vertebrogenic endplate damage


    Considered highly prevalent, LBP lasting fewer than four weeks is defined as acute. Subacute pain lasts from four to 12 weeks, and LBP that extends beyond 12 weeks is described as chronic.11 Chronic LBP is associated with decreased participation in family, social, and work roles, with increased costs to families, communities, and health care systems.3 Since the burden of chronic LBP is staggering, researchers have tried to determine the risks and likelihood of transitioning from acute to chronic LBP.


    In a large prospective cohort, multicenter study conducted from May 2016 to March 2019 in the U.S., researchers classified 5,233 patients with acute LBP as low, medium or high risk for developing chronic LBP. Participants’ average age was 50.6 years with 3,029 (58%) women and 4,353 (83%) white.6 Characteristics most commonly associated with transition to chronic LBP were obesity, smoking, severe baseline disability, and diagnosed depression and anxiety. Researchers included an assessment of the clinician treatment, specifically pharmacotherapy guidelines, diagnostic imaging and referral to medical subspecialists. Here, it’s important to know that following current treatment guidelines is known as concordant care. When clinicians treated patients with nonconcordant pharmacotherapies (discussed below), 606 of 1544 (39%) of patients progressed to chronic LBP. The study also observed that within the three weeks of the initial visit to the clinician, half of patients (48%) received at least one discordant process of care regardless of the individual patient’s risk factor. The study determined that exposure to nonconcordant processes increases the risk of developing chronic LBP at six months. Current practice guidelines, however, do not recommend using the tools the researchers used to assess risk in this study due to the belief that acute back pain typically resolves favorably.6


    MVP: Most Valuable Pathologies

    Seasoned players on the LBP team include degenerative disc disease (DDD) and arthritis which historically have been considered LBP’s common culprits.5 Allowing one to move, bend and twist, the discs in the lumbar spine segment (L1 through L5) separate the vertebrae.12, 13 Acting like a rubbery cushion to absorb shocks and stresses from daily movements, the disks—pictured in Figure 1—are thickest in the lumbar region of the spine. Each disk is composed of the nucleus pulposus (NP) and is 66% to 86% water. The remainder of the NP is type II collagen and proteoglycans. The annulus fibrosus (AF) is the structure that surrounds the NP in the form of a fibrocartilage outer ring. Composed of mostly collagen, proteoglycans, glycoproteins, elastic fibers, and connective tissue cells, the AF provides strength and flexibility.13 See Figure 2. Pain from DDD can wax and wane, travel down the lower back and buttocks, and be aggravated with sitting, bending or lifting. Pain can also range from mild to severe, and may be sharp, aching, or stiff. Particularly after age 40, disc degeneration starts with 5% of adults experiencing LBP. As the body ages, the inner semifluid core may dry out, causing the disc to decrease in thickness. Tears and cracks within the disc can also develop due to minor injuries. Typically, the tears are close to nerves and when aggravated, can trigger the inflammation cascade that can lead to LBP. Cracking of the external wall potentially leads to a disc bulge, also known as a herniated disk. The bulging disc could then compress the spinal nerve and lead to LBP.12, 13


    Figure 1. Lumbar Region of the Spine
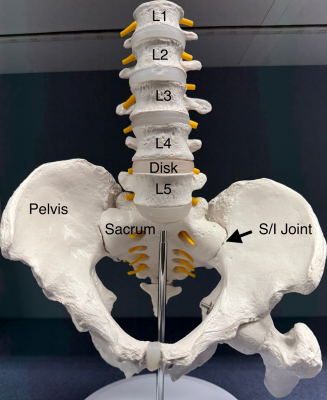
    Photo of the Lumbar Region of the Spine, labeled


    Figure 2. MRI of Lumbar Disk between L4-L5 with Bulge and Facet Joints
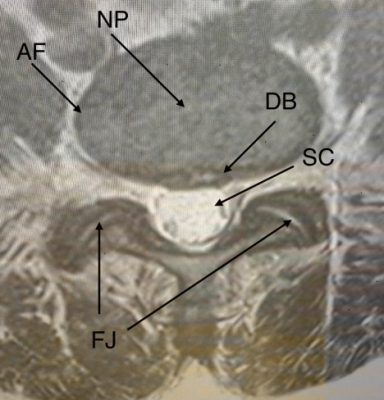
    MRI of Lumbar Disk between L4-L5 with Bulge and Facet Joints

    ABBREVIATIONS: NP: nucleus pulposus, AF: annulus fibrosus, SC: spinal cord, FJ: facet joint, DB: disk bulge


    A bit of a showboat on the team, spinal arthritis, is a frequent contributor to LBP and regularly leads to chronic back pain.14 Risk factors include 14

    • Age
    • Obesity
    • Comorbid diabetes, gout, psoriasis, tuberculosis, irritable bowel syndrome, or Lyme disease


    The origins of spinal arthritis are related to wear and tear, autoimmune disorders, and infection.14,15 Osteoarthritis or degenerative arthritis is a noninflammatory breakdown of cartilage between the joints and frequently encountered in the neck and lumbar areas of the spine. Areas most impacted by osteoarthritis in the low back can occur in the sacroiliac joint which is located between the sacrum and pelvis. Another notable area, known as the “three-joint complex,” is contained in each individual spine segment. The segment is composed of an intervertebral disk and two posterior lumbar facet joints.15 If one of the joints in the complex is affected by degeneration, the remaining joints’ biomechanics are impacted, leading to pain and limitation of movement in the low back DDD and spinal arthritis typically play on the same team as they both lead to breakdown of the disk. As the disk thins due to cartilage damage, the facet joints experience increased pressure and produce LBP.14,15


    Vertebrogenic back pain is another significant contributor to LBP but more closely associated with chronic LBP.16,17 A bilayer structure called the end plate is located between the disk and vertebrae. Made of cartilage and bone, end plates provide strength and help prevent vertebral fractures. End plates are also porous, allowing vertebral capillaries to connect to the disk nucleus. These porous pathways transport glucose, lactate, and oxygen to nourish the disk space and transport waste products out of the disk. Due to the conflicting demands of strength required for daily activity and porosity for nutrient passage, end plates are particularly vulnerable to damage. Once damaged, the end plate’s structure is altered and evidence suggests increased nerve proliferation, plus chemical sensitization and mechanical stimulation. The basivertebral nerve, which is located within the vertebrae, transports pain signals from the endplates to the brain. The pain that then results is termed vertebrogenic back pain.17,18


    Hallmark signs of vertebrogenic pain are deep, burning, or aching pain and intensified pain during periods of prolonged sitting, when physically active, and when bending forward.5 Due to the similarities of symptoms between vertebrogenic and DDD, misdiagnosis is possible and some patients could have DDD and vertebrogenic LBP concurrently.5


    Rheumatoid arthritis can also cause LBP.14 Considered inflammatory, rheumatoid arthritis attacks the immune system specifically at the lining of the joints or synovium. Another inflammatory arthritis that affects both the joints and the sites where ligaments and tendons attach to the bones and causes LBP is spondyloarthritis. Additional forms of spondyloarthritis that can cause LBP include ankylosing spondylitis, psoriatic arthritis, reactive arthritis, enteropathic arthritis, undifferentiated spondyloarthritis and juvenile spondyloarthritis.14


    Researchers have identified multiple genetic variants associated with chronic LBP, but there is no single “back pain gene.” Instead, studies suggest that LBP is influenced by many genes, each contributing a small amount to risk. One of the largest studies so far, published in 2025 in Nature Communications, analyzed genetic data from more than 550,000 people and identified 67 new genetic loci linked to chronic back pain.19\


    Some notable genes implicated include19,20,21

    • FOXP2 — one of the strongest newly identified associations in the 2025 study. This gene is involved in brain and nervous system function.
    • DRD2 — related to dopamine signaling and pain processing.
    • SCN9A — encodes the NaV1.7 sodium channel involved in pain signaling. Certain variants are associated with altered pain sensitivity, but evidence linking SCN9A directly to common low back pain is limited.
    • Genes involved in inflammation, disc degeneration, connective tissue maintenance, and nerve signaling have also been associated with chronic LBP.

    Researchers estimate that genetics may account for roughly 40% to 60% of susceptibility to chronic back pain, depending on the population studied.20


    TIMEOUT: PAIN REVIEW

    “I honestly try not to let myself get there, just because, when you’re going through it every single day, you just try to make it day to day. I think people out there with chronic pain, you don’t want to think about so far in the future, because you’re trying to get through the day.”

    -Kris Bryant, Major League Baseball player dealing with degenerative back pain.22


    The International Association for the Study of Pain (IASP) first defined pain in 1979.23 Adopted globally by the World Health Organization (WHO), various health care professionals, and researchers in the field of pain, the definition of pain remained unaltered through the years. Motivated by advances in pain research and seeking to improve evaluation of patients in pain, several professionals working in the field asked IASP for reassessment and revision of the definition of pain.


    After two years of deliberation, the IASP updated the definition of pain in 2020. Pain is currently defined as, “An unpleasant sensory and emotional experience associated with, or resembling that associated with, actual or potential tissue damage.” Knowing that a succinct definition of pain does not encompass the full complexity of the pain experience, a “Notes” section accompanies the definition to identify significant aspects of pain and are listed as follows 23:

    • Pain is consistently an individual experience impacted by fluctuating biological, psychological, and social factors.
    • Pain and nociception are different situations. Pain cannot be induced solely from activity in sensory neurons.
    • Through their life events, individuals recognize the concept of pain.
    • All clinicians must respect a person’s report of pain.
    • Although pain ordinarily functions as an adaptive role, negative effects on function, social and psychological well-being are possible.
    • Verbal description is only one of several behaviors to communicate pain; inability to convey does not negate the possibility that a human or a non-human animal experiences pain.


    Developed in the last 30 years, pain phenotypes describe various types of pain. Researchers and clinicians use three phenotypes regularly 24:

    • Nociceptive—pain that is diagnosable, localized and tissue damage
    • Neuropathic—pain that is diagnosable, caused by nerve damage
    • Nociplastic—pain that is poorly localized without clear tissue or nerve damage


    Although these terms are used to describe LBP, correlating the specific phenotype to a specific treatment is not recommended at this time due to lack of evidence-based research.25


    PAUSE AND PONDER: What symptoms would alert a technician to refer a patient to seek consultation with a pharmacist? What red flag warnings expressed by patients would prompt a pharmacist to recommend immediate medical evaluation?


    OVER THE COUNTER and FOUL BALL TERRITORY

    Going to bat, a ball hit outside the foul lines is out of play. Similarly, some symptoms fall outside the boundaries of self-care. Patients often ask pharmacy staff whether they can treat their symptoms with an OTC product or whether their symptoms have crossed into "foul ball territory" and require evaluation by a healthcare provider.


    It’s important to realize that while much back pain is minor and will resolve within a few days or weeks, it can be serious. Pharmacists should be aware of red flag symptoms that require further medical evaluation to prevent further disabling injury, complications, and pain. Self-treatment is excluded and immediate medical consultation is advised if the following are present26,27:

    • Severe pain (pain score of greater than 6)
    • Pain that lasts 10 days or more
    • Pain that continues more than seven days after treatment with topical analgesic
    • Increased intensity or change in character of pain
    • Accompanying nausea, vomiting, fever or other signs of systemic infection or disorder
    • Visually deformed joint, abnormal movement, or suspected fracture
    • Pregnancy
    • Back pain increases with rest
    • Back pain and loss of bowel and/or bladder control
    • Pain spreads down one or both legs
    • Pain causes weakness, tingling or numbness in one or both legs
    • The pain is associated with abdominal pain (other than dysmenorrhea)
    • LBP is the result of a fall or blow to the back (especially if older in age)


    Initially, self-care efforts such as gentle activity, ice packs, heating pads, analgesics, and limited rest are primary treatments for dealing with LBP.26 Over-the-counter (OTC) medications used for pain include acetaminophen, nonsteroidal anti-inflammatory drugs (NSAIDs), magnesium, topical lidocaine or capsaicin creams. Some patients may use transcutaneous electrical nerve stimulation (TENS) units.28 (Mayo Clinic recommends that patients seek additional medical care within 4 weeks if pain does not resolve with self-care initiatives or if pain escalates .26)


    FIRST BASE: MEDICATIONS

    Analogous to hitting a single in baseball, OTC and prescription medication are treatments patients seek to relieve LBP. While these medications do not get the patient “to home base,” meaning relief without medication, they do offer temporary relief. Table 3 describes medications used to minimize suffering, improve function, and minimize adverse effects.29 After assessing the pain’s cause, prescribers should explain the anticipated treatment duration and what to expect during treatment. Pharmacists can confirm and support these recommendations, specifically when it comes to pharmaceutical products.


    Table 3. Medication Treatments for Acute, Chronic, and Radicular LBP30

    Medication Class Pain Level Adverse Effects
    Acetaminophen Mild to moderate Thrombocytopenia, hypoglycemia, hypothermia, pancreatitis, nephrotoxicity, hepatotoxicity(with overdose), hepatic necrosis,  rash, hypersensitivity
    NSAIDs Mild to moderate Abdominal pain or cramps, dyspepsia, diarrhea, gastrointestinal bleeding, gastrointestinal perforation, dizziness, headache, edema, rash, heartburn, tinnitus, pruritus
    COX-2-Selective NSAIDs Mild to moderate Abdominal pain, dyspepsia, diarrhea, dizziness, headache, edema, rash, flatulence, nausea, upper respiratory tract infection, influenza-like illness, musculoskeletal and connective tissue signs and symptoms (back pain and muscle spasms and musculoskeletal pain)
    Opioids Persistent moderate to severe pain Short-term use: Nausea, dizziness, constipation, vomiting, somnolence, dry mouth

    Long-term use: Addiction, abuse, overdose, fractures, cardiovascular events, sexual dysfunction and motor vehicle accidents

    SMRs No data Sedation, drowsiness, dizziness
    Benzodiazepines No data Somnolence, fatigue, lightheadedness, addiction, abuse, overdose, fractures
    Antidepressants No data Drowsiness, dizziness, dry mouth, constipation, sexual dysfunction, nausea
    Systemic corticosteroids No data Facial flushing, infection, gastrointestinal bleeding, hyperglycemia requiring medical treatment
    ABBREVIATIONS: COX-2: Cyclooxygenase-2, NSAID: Nonsteroidal anti-inflammatory drug, SMR: Skeletal muscle relaxant


    In 2017, the American College of Physicians and the American Academy of Family Physicians

    adopted treatment guidelines for acute, subacute and chronic LBP.31 (The WHO and the U.S. Veterans Administration also publish guidelines and have similar recommendations; they are located at https://www.ncbi.nlm.nih.gov/books/NBK599212/ and https://www.healthquality.va.gov/guidelines/pain/lbp/, respectively.) Primary treatments revolve around superficial heat, massage, acupuncture or spinal manipulation for acute or subacute LBP. When the clinicians deems pharmacologic treatment necessary, the guidelines recommend NSAIDs or skeletal muscle relaxants (SMR). When treating chronic LBP, primary treatments include exercise, acupuncture, mindfulness-based stress reduction, yoga, tai chi, cognitive behavioral therapy, or spinal manipulation. Pharmacologic treatments for chronic LBP list NSAIDs monotherapy to start. If patients don’t experience relief of LBP with an NSAID, then tramadol or duloxetine are acceptable options. Opioids are recommended only if other treatments are ineffective and when the benefits exceed the risks for the individual patient.31


    When reviewing prescriptions, pharmacists should identify and counsel patients on the use of prescription medications used for LBP. Lack of adherence to guidelines when prescribing medications is known as nonconcordant prescribing. Nonconcordant prescribing is known to increase the risk of developing chronic LBP (as discussed above).6 Prescription use that might contribute to developing chronic LBP might include6

    • Opioid prescribing as first-line therapy
    • Benzodiazepines without an NSAID or SMR
    • Prolonged use of SMRs
    • Unnecessary oral corticosteroids, used alone or without an NSAID or SMR
    • Prescribing antibiotics when no infection is present
    • Continuing ineffective therapies long-term
    • Prescribing medications despite contraindication or poor risk-benefit balance


    SECOND BASE: FUNCTIONAL INTERVENTIONS

    Did you know that second base is the most common stolen base during the game?32 Prompt decision making and movement help the player advance to home plate quicker. Hitting a double, which is combining medication with movement, improves the chances of reducing LBP. Incorporating movement and aerobic exercise into daily routines when a patient experiences LBP seems counterintuitive, however, evidence-based research supports physical movement and physical therapy sessions within the first ninety days of acute LBP onset.33


    Physical Therapy

    A randomized controlled clinical trial assessed whether physical therapy introduced within 90 days of sciatica onset lowered disability outcomes.33 Secondary outcomes were pain intensity, patient reported treatment success, health care use and workdays absent. Prior to enrollment, all 220 patients, aged 18 to 60 years old, received imaging (computed tomography or magnetic resonance imaging) and medication from the healthcare provider. The researchers randomized the participants to one of two groups:


    • One educational session, standard care (SC)
    • One educational session, four weeks of physical therapy including exercise and manual therapy


    The researchers observed improved disability scores and back pain intensity at six months and one year after the trial. The physical therapy group had higher satisfaction with treatment after one year (45.2%) than the SC group (27.6%). Healthcare use and missed workdays were similar. Study limitations included unblinded patients and providers, and undetermined specific physical therapy interventions liable for the effects.33


    Physical therapy helps provide pain relief by stretching and strengthening the muscles that support the back. Which type of physical intervention has the best long-term benefits? Healthcare providers may advise patients to consider using a pool for therapy rather than relying on other types of physical activity. In a randomized clinical trial, researchers compared physical therapy to aquatic exercise for 113 adults with chronic LBP.34 The three-month, single-blind randomized clinical trial with a 12-month follow-up was completed in March of 2020. Participants in the physical therapy group received 60 minutes of therapeutic aquatic exercise or TENS and infrared ray thermal therapy twice a week for three months. Researchers used a disability questionnaire to measure disability outcomes and secondary outcomes were reported as pain intensity, quality of life, anxiety, depression, sleep quality, fear avoidance, and minimal clinically important difference in pain and function. Therapeutic water exercise programs led to significant reductions in symptoms compared to the physical therapy group with lasting benefits of up to 12 months.34


    Yoga

    A slow exhalation. A shift in weight. Complete concentration on a sequence of practiced movements. Then—the crack of the bat echoes across the stadium, and the crowd erupts. Although yoga predates baseball by thousands of years, the two share important characteristics. Both require balance, flexibility, body awareness, and the ability to execute controlled movements with precision. Whether on the pitcher's mound or a yoga mat, success depends on controlled movement, balance, and body awareness.


    Over the last 30 years, yoga has become increasingly popular among athletes, and many coaches and trainers incorporate it into conditioning programs to improve flexibility, balance, and core stability. Clinicians also recommend yoga for some patients with chronic LBP. Often considered comparable to a structured stretching program, yoga has been shown to reduce pain and improve mobility in many patients with chronic LBP.35


    Questioning yoga’s effect on pain intensity, back function, sleep quality, and pain medication usage, researchers conducted a single-blind, two arm (“yoga now” [n = 71] and “yoga later” [n = 69]), randomized clinical trial from May 2022 until May 23, 2023.L15 Inclusion criteria were as follows: beneficiaries of the Cleveland Clinic Employee Health Plan, adults aged 18 to 64, ability to comprehend the English language, and nonspecific LBP for at least 12 weeks. It also required a pain intensity score of at least four on an 11-point pain rating scale. Participants in both arms of the study took part in once weekly, 60-minute, virtual, live-streamed therapeutic (hatha) yoga classes for 12 consecutive weeks. The researchers offered the first group, called yoga now, classes in the initial 12-week session with assessment for a total of 24 weeks. They advised the control group, called yoga later, to continue their existing medical treatments and prohibited them from starting a new yoga routine until after completion of the final assessment.36


    All yoga instructors who taught the classes had at least 200 hours of training.36 Classes had two instructors, one to teach and the other to observe safety and advise correct alignment to reduce injury. Participants progressed through 12 to 15 different yoga poses with increasing level of difficulty at each session.36


    Results from the study yielded improvements in the yoga now group for pain intensity, back-related function, and sleep quality at six, 12 and 24 weeks.36 Use of any analgesic decreased at 12 and 24 weeks, specifically by 21.2 absolute percentage points as compared to the yoga later group. Notably, participants in the yoga now group substantially reduced use of NSAID pain medication by 17.9 absolute percentage points at week 24 compared to the control group. Study limitations included poor class attendance and insufficient feedback of data from participants. Investigators explained that since there were no financial incentives to complete the study, an unidentified number of participants failed to complete the weekly class and assessment. Incomplete reporting of assessment and self-report bias factored into unreliable methods of measurement in both arms of the study. Last, the study’s short duration was noted as a limitation.36 The investigators concluded that a virtual yoga class is efficacious and safe for those who suffer from LBP. They also encourage future studies that are longer in duration, include the cost savings benefit, and develop better recruitment designs to boost the variety of participants.36


    THIRD BASE: INTERVENTIONS

    The most difficult run a baseball player must make is the distance from third base to home plate.

    When LBP continues without improvement despite treatment, invasive procedures may be the only option. Several invasive treatment options are available; however, the outcomes have limited success and often include increased risk of additional surgeries. Lumbar spinal fusion is a common back surgery that removes a damaged disc(s) and fuses the adjacent vertebra in an effort to prevent motion-related pain.37 Disadvantages to lumbar spinal fusion are potential loss of motion and increasing wear and tear of the segments of the spine above and below the area of fusion. As a result, future surgical fusions in additional vertebral segments may become necessary.


    An alternative to lumbar fusion, artificial disc replacement has been around since the 1950s.37 In this procedure, a surgeon removes the damaged disc and replaces it with an artificial implant. Results have generally been lackluster due to the breakdown of the material used to produce the implant. Recent advances in implant composition and design have improved stability and spinal movement as compared to spinal fusion. Lumbar artificial disc replacement is generally reserved for carefully selected patients with symptomatic degeneration involving one or two intervertebral discs.38


    Surgical interventions should be considered the treatment of last resort. Newer minimally invasive treatments have emerged such as radiofrequency ablation (RFA).39 This minimally invasive procedure sends radio waves through a needle to heat an area on the nerve called the medial branch. Once the medial branch is ablated or burned, the pain signals sent from these joint area(s) to the brain decrease. RFA is used for patients who have axial LBP, pain that is confined to the back area, that does not radiate down the legs. Because identifying the pain generator can be challenging, patients typically undergo two diagnostic medial branch blocks using a local anesthetic before RFA is performed to confirm that the facet joints are the likely source of pain. Once RFA is completed, pain relief can last six to 10 months.39


    OUTFIELD: ALTERNATIVE TREATMENTS AND RESOURCES

    Outfielders adjust their positions to match each batter's tendencies, recognizing that no two hitters are exactly alike. Likewise, complementary therapies and other supportive resources can be tailored to an individual's symptoms, preferences, and response to treatment.


    Frustrated and desperate for relief of LBP, some patients will seek alternative treatments to treat their LBP. Pharmacists are uniquely positioned to inquire about and educate patients on use of unconventional treatments in LBP.


    PAUSE AND PONDER: Why is it important for healthcare providers to ask patients with LBP what treatments they have used or are currently using?


    Cannabidiol

    Legalized for use in some states and sold by dispensaries, pharmacies, or purchased online, cannabidiol (CBD) is available as capsules, gummies, oils, drinks, or tinctures.40 Recruited through social media, participants in an anonymous online survey in 2018 revealed that they used CBD to treat several medical conditions. Of the 2,409 participants, over 60% admitted to using CBD to treat pain, anxiety, depression, or sleep disorders.41


    CBD is derived from either the hemp plant or cannabis (marijuana) plant.42 Although both plants contain the psychoactive compound delta-9-tetrahydrocannabinol (THC), hemp contains low amounts of THC and high amounts of CBD. Cannabis on the other hand, contains high amounts of THC and low amounts of CBD.42 Cannabis containing 0.3% or less of THC is considered hemp, and cannabis containing more than 0.3% of THC is marijuana. This reflects a recent change pursuant to the passage of the Agriculture Improvement Act of 2018 and has led to the rise in usage and production of CBD products. This classification also removed hemp from the Schedule 1 drug substance list. Alternately, cannabis is a Schedule 1 substance per the Drug Enforcement Administration with no currently accepted medical use and a high potential for abuse.43


    Before 2018, federal law designated product that contained THC at any level as controlled substances.42 The government now requires more reliable testing techniques to determine actual levels of THC in products to identify the source as either hemp or marijuana. Therefore, the National Institute of Standards and Technology (NIST) developed extraction and analytical methods to confirm actual amounts of THC in plant materials. Researchers from the NIST screened 53 hemp samples in plant form from five separate commercial online vendors. Each vendor stated their product contained less than 0.3% THC or that products had been lab tested to validate the concentrations. Using peer-reviewed extraction methods with liquid chromatography, they analyzed the plant samples. Of the 53 samples, 49 were incorrectly labeled as hemp, having concentrations of THC above 0.3%. The researchers suggest that this data highlights the challenge for consumers who may be unaware of what they are actually ingesting.42 Some patients might work for a company or seek treatment from pain management providers that require periodic drug testing. Patients could potentially test positive for cannabis or marijuana due to the inaccuracy of reported THC on CBD products’ labels.44 Pharmacists are well positioned to remind patients that urinalysis drug screen testing could yield a positive result for cannabis or marijuana use when using CBD products.


    Acupuncture

    Acupuncture is another alternative treatment sought by patients to relieve LBP. The American College of Physicians lists acupuncture in their evidence-based clinical practice guideline as a treatment for acute or subacute LBP prior to pharmacologic treatment.30 Used alone or in combination with conventional therapy, acupuncture is thought to decrease pain by45:

    • Affecting pain processing centers of the brain, specifically the human limbic and basal forebrain areas by prolonged skin stimulation with the needle
    • Regulating the release of the neurotransmitter, adenosine, an inflammatory signaling molecule, that affects pain messaging to the spinal cord and periphery


    Looking to understand if acupuncture is an effective and safe treatment option, researchers conducted a randomized clinical trial from August 2021 to November 2023. Aged 65 years or older, 800 participants with chronic LBP compared three different treatment arms46:

    • Standard acupuncture (SA) treatment (8-15 sessions across 12 weeks plus usual medical care [UMC]).
    • Enhance acupuncture (EA) treatment (SA plus 4-6 added sessions across 12 weeks).
    • UMC alone.


    Follow up assessment at three, six, and 12 months was measured by the 24-item Roland-Morris Disability Questionnaire.46 Scientists concluded the acupuncture needling group at the six and 12-month assessments improved chronic LBP dysfunction as compared to UMC alone. Acupuncture needling was also considered an effective and safe treatment option for older adults with chronic LBP. Study limitations included lack of a sham control, limited access to participants’ medication changes and dispensing data at two sites, and incomplete outcome data from some participants who did not complete follow-up assessments.46


    THE SEVENTH INNING STRETCH: PREVENTION

    If you haven’t already, let’s incorporate some movement into this lengthy CE. It would be a good time to stretch, take a short walk or take a drink of water.


    Although there are reports of baseball’s inception prior to 1841 in America, the seventh-inning stretch didn’t evolve till around the late 1800’s.47 Brother Jasper FSC, an immigrant from Ireland, came to Manhattan University in New York in 1861. Tasked with helping students, he established extracurricular activities such as orchestra, glee club, and numerous literary societies. However, he was also the first athletic director and coach for the university’s first baseball team. At one particular game, noticing that the students watching the game were becoming agitated after sitting so long, he stopped the game and allowed people to stand, stretch and relax. This break helped ease the crowd and restored focus and order for the remainder of the game. This ritual spread to other professional baseball teams and now has become a cherished part of the game where people can take a break by singing, “take me out to the ball game” if one so prefers.47


    The following suggestions can also help avoid LBP and be integrated into daily life:48, 49

    • Lift correctly. When lifting an object or that heavy box of medications, patients should use their legs, bend at the knees, keep the back straight. They should hold the item close to the body while tightening their stomach muscles.
    • Preserve good posture. People with LBP should take frequent breaks, avoid slouching over the pharmacy counter when standing or sitting. They need to work on standing tall with the head up and shoulders back. If they work at a desk, they should take frequent breaks to move around.
    • Maintain a healthy weight. People with LBP should plan lunch and snacks that are nutritious, limit high fat, high caloric foods to special occasions. Less weight reduces stress and strain on the back.
    • Remain active. Regular movement keeps muscles strong. Aiming for 150 minutes of activity per week is a good goal. Setting a phone alarm is a good way to incorporate movement and stretch breaks throughout the day.
    • Consume enough calcium and vitamin D. Nutrients help maintain bone strength. Lack of these nutrients leads to osteoporosis which could lead to LBP if it affects the spine.
    • Quit smoking. Research shows that nonsmokers have fewer frequent episodes of back pain than people who smoke.
    • Meet a daily water intake goal based on a variety of factors (environment, physical activity, comorbidities, etc.; some references indicate 30 to 35 mL per kilogram of body weight per day, others say half the person’s body weight in ounces. Water helps lubricate and cushion joints. It also protects the spinal cord.


    CONCLUSION

    The diagnosis and treatment of LBP is astonishingly common. Frequent episodes of acute back pain can progress to chronic back pain and high rates of disability. LBP could be caused by a multitude of factors with a variety of treatment options. Informing patients of medication use and adverse effects is helpful for improving the patient’s quality of life. Although medications can provide pain relief for some, clinicians and patients can consider the addition of physical therapy, exercise, injections, and ablation interventions if pain persists. Surgical procedures should be considered a treatment of last resort due to risk of infection, possibility of failure and need for subsequent future back surgeries. Patients who experience LBP may also have depression and anxiety due to inability to work, socialize, and carry out daily tasks. Pharmacists can help patients by sharing the variety of treatment options available to those suffering with LBP.

    In the game of baseball, many different coaches assist the athletes to advance to home plate and win the game. Pharmacists and technicians can contribute to helping those experiencing LBP advance to home plate which is pain reduction and get back to living life.



    Pharmacist Post Test (for viewing only)

    A Team Effort: Helping Patients Manage Low Back Pain

    26-043 Pharmacist Post-test

    After completing this continuing education activity, pharmacists will be able to

    • Classify common causes and types of low back pain
    • Recognize red-flag symptoms requiring referral or evaluation
    • Compare pharmacologic and nonpharmacologic low back pain treatments
    • Explain self-care and prevention strategies to patients who have low back pain


    1. 52-year-old Jackie reports low back pain that began two weeks ago after lifting a heavy box. The pain remains confined to the lower back, and he has no neurologic symptoms or systemic complaints. How should the pharmacist classify this episode?

    a. Acute, nonspecific low back pain

    b. Chronic, neuropathic low back pain

    c. Subacute, specific low back pain


    *


    2. Babe describes burning low back pain that radiates down one leg and is accompanied by tingling. Which pain type best fits this presentation?

    a. Nociplastic pain

    b. Neuropathic pain

    c. Nociceptive pain


    *


    3. Dottie has deep, aching low back pain that worsens with prolonged sitting and bending forward. She says that her physician ordered imaging and it shows vertebral endplate damage. Which classification is most appropriate?

    a. Nonspinal low back pain

    b. Nonspecific low back pain

    c. Specific spinal low back pain


    *


    4. Which symptom is a red flag that requires prompt medical evaluation rather than self-treatment?

    a. Low back pain with new loss of bladder control

    b. Mild soreness after gardening for one day

    c. Pain that improves with gentle movement


    *


    5. Which patient characteristic excludes routine self-treatment of low back pain?

    a. Pain score of 3 after a long car ride

    b. Pregnancy in any trimester

    c. Pain present for 2 days


    *


    6. Which presentation is most consistent with a red flag for serious low back pathology?

    a. Pain that decreases with rest

    b. Pain relieved by a heating pad

    c. Pain with fever and vomiting


    *


    7. Hank has chronic low back pain and has completed an adequate NSAID trial without sufficient relief and has no contraindication to other recommended therapies. Which medication is a guideline-supported next option?

    a. Duloxetine

    b. An oral corticosteroid used indefinitely

    c. An antibiotic without evidence of infection


    *


    8. Satchel has acute low back pain., He asks whether medication is always the best first treatment. Which response most accurately compares recommended approaches?

    a. Opioids should be tried before superficial heat, massage, acupuncture, or spinal manipulation.

    b. Superficial heat, massage, acupuncture, or spinal manipulation may be tried before medication.

    c. Complete bed rest is preferred to movement or light exercise during the first several weeks.


    *


    9. Ruth, who is 71 years old and has chronic low back pain, wants a nonpharmacologic option that may improve function over time. Which comparison is most accurate based on the activity?

    a. Acupuncture is ineffective unless combined with opioids.

    b. Aquatic exercise provides immediate benefit but studies indicate that lasting improvement is rare.

    c. Structured options (e.g., acupuncture, yoga, aquatic exercise) may improve pain or function in some patients.


    *


    10. Roberto has recurrent low back pain. He works in a warehouse and asks how to lift boxes more safely. Which instruction is best?

    a. Bend the knees, keep the back straight, hold the load close, and lift with the legs.

    b. Keep the knees straight and lift quickly using the back.

    c. Twist at the waist while raising the load to reduce leg strain.


    *


    11. Yogi, recently diagnosed with uncomplicated low back pain, has avoided all activity for several days because movement seems counterintuitive. Which counseling point is most appropriate?

    a. Continue strict bed rest until all pain resolves.

    b. Resume gentle activity as tolerated and avoid prolonged inactivity.

    c. Go to the batting cages daily even if you experience pain.


    *


    12. A pharmacy employee stands for long shifts and wants to reduce future low back pain flares. Which plan is most appropriate?

    a. Take a short-acting nonsteroidal anti-inflammatory about one hour before every shift and then every 4 hours.

    b. Discuss the problem with the pharmacy supervisor and ask for “light duty,” meaning you need to have a sit-down job all day.

    c. Use good posture, take movement breaks, remain active, and address modifiable risks such as smoking and excess weight.


    Pharmacy Technician Post Test (for viewing only)

    A Team Effort: Helping Patients Manage Low Back Pain

    26-043 Pharmacy Technician Post-test

    After completing this continuing education activity, pharmacy technicians will be able to

    • Identify common causes and risk factors for low back pain
    • Recognize symptoms that require pharmacist referral
    • Describe common medications and supportive therapies for low back pain
    • Explain safe self-care and prevention for low back pain


    1. Mickey is 73 years old and asks whether age increases the likelihood of low back pain. Which response is most accurate?

    a. Aging is a recognized risk factor for low back pain.

    b. Age affects only recovery after surgery.

    c. Age has little relationship to low back pain.


    *


    2. Babe has obesity, depression, and smokes. He asks for an OTC product for recurrent low back pain. What should the technician notice about this patient?

    a. The patient has no known risk factors for chronic pain.

    b. The patient has risk factors for persistent or chronic low back pain.

    c. Only the patient's age is relevant to low back pain risk.


    *


    3. Dottie tells the technician that her low back pain began after several weeks of repeatedly lifting heavy boxes of files at work. Which risk factor is most likely contributing to her symptoms?

    a. Physically demanding work

    b. Adequate water intake

    c. Occasional stretching


    *


    4. Which symptom should a technician immediately refer to the pharmacist?

    a. Back pain with new leg weakness

    b. Mild stiffness after sitting

    c. Pain that improves with a heating pad


    *


    5. Which patient report requires pharmacist referral rather than routine product assistance?

    a. Soreness for one day after yard work

    b. Back pain after a fall down the stairs

    c. Mild discomfort relieved by rest


    *


    6. Which symptom combination is a red flag for low back pain?

    a. Pain and mild fatigue after exercise

    b. Pain that improves over several days

    c. Pain with fever and nausea


    *


    7. Which medication class is commonly used for mild to moderate low back pain but can cause gastrointestinal bleeding?

    a. NSAIDs

    b. Antibiotics

    c. Anticoagulants


    *


    8. Which supportive therapy uses electrical stimulation delivered through the skin?

    a. Acupuncture

    b. A TENS unit

    c. Spinal fusion


    *


    9. Which treatment uses heat to interrupt pain signals from selected nerves?

    a. Aquatic exercise

    b. Yoga

    c. Radiofrequency ablation


    *


    10. Patient Roberto asks the technician how to prevent another lifting-related episode of low back pain. Which response is appropriate?

    a. Lift with the legs, keep the load close, and avoid twisting.

    b. Keep the knees straight and bend from the waist.

    c. Hold objects away from the body to improve balance.


    *


    11. Yogi has uncomplicated low back pain and says, 'I plan to stay in bed until it is completely gone.' Which technician response best reinforces safe self-care?

    a. Complete bed rest is the safest approach and you should feel better within a week or so.

    b. Gentle activity is encouraged, but the pharmacist can help determine what is appropriate.

    c. Go to the batting cages daily even if you experience pain.


    *


    12. Lou has used a topical analgesic for more than seven days and says the pain is worsening. What should the technician do?

    a. Recommend using twice as much product.

    b. Suggest adding another topical product without consultation.

    c. Refer the patient to the pharmacist for possible medical referral.


    References

    Full List of References

    1. Blum, D., Schmall, E. The Debilitating Toll of Back Pain. The New York Times. December 10, 2024. Accessed June 20, 2026. www.nytimes.com/2024/12/10/well/back-pain-mangione.html
    2. Venes DD, ed. Taber's Medical Dictionary. 25th ed. F.A. Davis; 2025. Lumbago.
    3. WHO guideline for non-surgical management of chronic primary low back pain in adults in primary and community care settings. Accessed July 14, 2026. Geneva: World Health Organization; 2023.
    4. Yang QH, Zhang YH, Du SH, Wang YC, Wang XQ. Association Between Smoking and Pain, Functional Disability, Anxiety and Depression in Patients With Chronic Low Back Pain. Int J Public Health. 2023;68:1605583. Published 2023 Mar 7. doi:10.3389/ijph.2023.1605583
    5. Vertebrogenic Low Back Pain. Cleveland Clinic. Accessed June 2, 2026. https://my.clevelandclinic.org/health/diseases/vertebrogenic-low-back-pain
    6. Stevens JM, Delitto A, Khoja SS, et al. Risk Factors Associated with Transition From Acute to Chronic Low Back Pain in US Patients Seeking Primary Care. JAMA Network Open. 2021;4(2):e2037371. Published 2021 Feb 1. doi:10.1001/jamanetworkopen.2020.37371
    7. All-Star Game. Encyclopedia Britannica. Accessed January 5, 2026 https://www.britannica.com/sports/All-Star-Game
    8. Low Back Pain. World Health Organization. Accessed June 2, 2026. https://www.who.int/news-room/fact-sheets/detail/low-back-pain
    9. Shokri P, Zahmatyar M, Falah Tafti M, et al. Non-spinal low back pain: Global epidemiology, trends, and risk factors. Health Sci Rep. 2023;6(9):e1533. Published 2023 Sep 4. doi:10.1002/hsr2.1533
    10. Chiarotto A, Koes BW. Nonspecific Low Back Pain. N Engl J Med. 2022;386(18):1732-1740. doi:10.1056/NEJMcp2032396
    11. American College of Physicians issues guideline for treating nonradicular low back pain. American College of Physicians. Accessed May 20, 2026. https://www.acponline.org/acp-newsroom/american-college-of-physicians-issues-guideline-for-treating-nonradicular-low-back-pain
    12. Degenerative Disk Disease. Cleveland Clinic. Accessed June 8, 2026, 2026. https://my.clevelandclinic.org/health/diseases/16912-degenerative-disk-disease
    13. Waxenbaum JA, Reddy V, Futterman B. Anatomy, Back, Intervertebral Discs. [Updated 2023 Dec 9]. In: StatPearls [Internet]. StatPearls Publishing; 2025. https://www.ncbi.nlm.nih.gov/books/NBK470583/
    14. Spinal Arthritis (Arthritis in the Back or Neck). Johns Hopkins Medicine. Accessed June 11, 2026. https://www.hopkinsmedicine.org/health/conditions-and-diseases/spinal-arthritis
    15. Du R, Xu G, Bai X, Li Z. Facet Joint Syndrome: Pathophysiology, Diagnosis, and Treatment. J Pain Res. 2022;15:3689-3710. Published 2022 Nov 30. doi:10.2147/JPR.S389602
    16. van Dieën JH, Weinans H, Toussaint HM. Fractures of the lumbar vertebral endplate in the etiology of low back pain: a hypothesis on the causative role of spinal compression in aspecific low back pain. Med Hypotheses. 1999;53(3):246-252. doi:10.1054/mehy.1998.0754
    17. Lotz JC, Fields AJ, Liebenberg EC. The role of the vertebral end plate in low back pain. Global Spine J. 2013;3(3):153-164. doi:10.1055/s-0033-1347298
    18. Conger A, Smuck M, Truumees E, Lotz JC, DePalma MJ, McCormick ZL. Vertebrogenic Pain: A Paradigm Shift in Diagnosis and Treatment of Axial Low Back Pain. Pain Med. 2022;23(Suppl 2):S63-S71. doi:10.1093/pm/pnac081
    19. Stanaway IB, Suri P, Afari N, et al. Multi-ancestry meta-analysis of genome-wide association studies discovers 67 new loci associated with chronic back pain. Nat Commun. 2025;16(1):1525. Published 2025 Feb 11. doi:10.1038/s41467-024-55326-3
    20. Zorkoltseva IV, Elgaeva EE, Belonogova NM, et al. Multi-Trait Exome-Wide Association Study of Back Pain-Related Phenotypes. Genes (Basel). 2023;14(10):1962. Published 2023 Oct 19. doi:10.3390/genes14101962
    21. Dib-Hajj SD, Yang Y, Black JA, Waxman SG. Mutations in sodium-channel gene SCN9A cause a spectrum of human genetic pain disorders. Brain. 2007;130(Pt 7):1707-1718.
    22. Saunders P. Kris Bryant is ‘in pain every day’ and can’t play baseball for Colorado Rockies — but he’s not retiring. Chicago Tribune. February 17, 2026. https://www.chicagotribune.com/2026/02/17/kris-bryant-mlb-not-retiring/ Accessed February 18, 2026.
    23. Raja SN, Carr DB, Cohen M, et al. The revised International Association for the Study of Pain definition of pain: concepts, challenges, and compromises. Pain. 2020;161(9):1976-1982. doi:10.1097/j.pain.0000000000001939
    24. Antrim A. Reimagining Pain Management: Pharmacists Urged to “Deconstruct the Cupcake.” Pharmacy Times. June 8, 2025. Accessed June 20, 2026. https://www.pharmacytimes.com/view/reimagining-pain-management-pharmacists-urged-to-deconstruct-the-cupcake-
    25. Nijs J, Kosek E, Chiarotto A, et al. Nociceptive, neuropathic, or nociplastic low back pain? The low back pain phenotyping (BACPAP) consortium’s international and multidisciplinary consensus recommendations. Lancet Rheumatol. 2024;6(3):e178-e188. doi.org/10.1016/
    S2665-9913(23)00324-7
    26. When to See a Doctor for Back Pain. Mayo Clinic. Accessed June 17, 2026. https://www.mayoclinic.org/connected-care/when-to-see-a-doctor-for-back-pain/cpt-20470965
    27. Olenak, JL, Pezzino, NC. Musculoskeletal Injuries and Disorders. In: Handbook of nonprescription drugs : an interactive approach to self-care. 21st Edition. D. L. Krinsky, S. P. Ferreri, B. Hemstreet, A. Hume, C. J. Rollins, K. L. Scolaro, & K. J. Tietze. APhA, American Pharmacists Association. 2025.
    28. Peck J, Urits I, Peoples S, et al. A Comprehensive Review of Over the Counter Treatment for Chronic Low Back Pain. Pain Ther. 2021;10(1):69-80. doi:10.1007/s40122-020-00209-w
    29. Amaechi O, Huffman MM, Featherstone K. Pharmacologic Therapy for Acute Pain. Am Fam Physician. 2021;104(1):63-72.
    30. Qaseem A, Wilt TJ, McLean RM, et al. Noninvasive Treatments for Acute, Subacute, and Chronic Low Back Pain: A Clinical Practice Guideline From the American College of Physicians. Ann Intern Med. 2017;166(7):514-530. doi:10.7326/M16-2367
    31. Minor Injuries: Clinical Guidance and Practice Resources. American Academy of Family Physicians. Accessed June 13, 2026. https://www.aafp.org/clinical-insights/acute-care-office-procedures/minor-injuries
    32. Lehnardt K. 95 Fun Baseball Facts. Fact Retriever. Accessed June 20, 2026. https://www.factretriever.com/baseball-facts
    33. Fritz JM, Lane E, McFadden M, et al. Physical Therapy Referral From Primary Care for Acute Back Pain With Sciatica : A Randomized Controlled Trial. Ann Intern Med. 2021;174(1):8-17. doi:10.7326/M20-4187
    34. Peng MS, Wang R, Wang YZ, et al. Efficacy of Therapeutic Aquatic Exercise vs Physical Therapy Modalities for Patients With Chronic Low Back Pain: A Randomized Clinical Trial. JAMA Netw Open. 2022;5(1):e2142069. Published 2022 Jan 4. doi:10.1001/jamanetworkopen.2021.42069
    35. Tzelnic A. Has Anyone Noticed That Baseball Stretches Are A LOT Like Yoga Poses? Yoga Journal. June 25, 2025. https://www.yogajournal.com/practice/yoga-and-baseball/
    36. Tankha H, Gaskins D, Shallcross A, et al. Effectiveness of Virtual Yoga for Chronic Low Back Pain: A Randomized Clinical Trial. JAMA Netw Open. 2024;7(11):e2442339. Published 2024 Nov 4. doi:10.1001/jamanetworkopen.2024.42339
    37. Disc Replacement Rivals Spinal Fusion. Arthritis Foundation. Accessed June 20, 2026. https://www.arthritis.org/diseases/more-about/disc-replacement-rivals-spinal-fusion
    38. American Academy of Orthopaedic Surgeons. Lumbar artificial disk replacement. OrthoInfo. Accessed July 14, 2026. https://orthoinfo.aaos.org/en/treatment/artificial-disk-replacement-in-the-lumbar-spine/
    39. Expert Q&A: Radiofrequency Ablation for Back Pain. Arthritis Foundation. Accessed June 20, 2026. https://www.arthritis.org/health-wellness/healthy-living/managing-pain/pain-relief-solutions/expert-q-a-radiofrequency-ablation-for-back-pain
    40. Laurence, E. Your Guide to CBD Legalization by State. Forbes. September 7, 2023. Accessed June 20, 2026. https://www.forbes.com/health/cbd/cbd-legalization-by-state/
    41. Corroon J, Phillips JA. A Cross-Sectional Study of Cannabidiol Users. Cannabis Cannabinoid Res. 2018;3(1):152-161. Published 2018 Jul 1. doi:10.1089/can.2018.0006
    42. Wilson W, Urbas A, Scott F. Study Reveals Inaccurate Labeling of Marijuana as Hemp. National Institute of Justice. 2022. Accessed June 20, 2026. https://nij.ojp.gov/topics/articles/study-reveals-inaccurate-labeling-marijuana-hemp
    43. Drug Scheduling. DEA United States Drug Enforcement Administration. Accessed June 20, 2026. https://www.dea.gov/drug-information/drug-scheduling
    44. Wiginton, K. Will CBD Cause Me to Fail a Drug Test? WebMD. Accessed April 8, 2026. https://www.webmd.com/cannabinoids/features/cbd-drug-tests
    45. Giovanardi CM, Gonzalez-Lorenzo M, Poini A, et al. Acupuncture as an alternative or in addition to conventional treatment for chronic non-specific low back pain: A systematic review and meta-analysis. Integr Med Res. 2023;12(3):100972. doi:10.1016/j.imr.2023.100972
    46. DeBar LL, Wellman RD, Justice M, et al. Acupuncture for Chronic Low Back Pain in Older Adults: A Randomized Clinical Trial. JAMA Netw Open. 2025;8(9):e2531348. Published 2025 Sep 2. doi:10.1001/jamanetworkopen.2025.31348
    47. Who is Brother Jasper? Manhattan University. Accessed June 20, 2026. https://manhattan.edu/about/history/brother-jasper
    48. Stretching and Strengthening Exercises to Relieve and Prevent Lower Back Pain. Harvard Health Publishing. Accessed June 17, 2026. https://www.health.harvard.edu/pain/stretching-and-strengthening-exercises-to-relieve-and-prevent-lower-back-pain
    49. About Water and Healthier Drinks. CDC. Accessed June 17, 2026. https://www.cdc.gov/healthy-weight-growth/water-healthy-drinks/index.html

    Vaccine Hesitancy: Rebooting Management Strategies for Pharmacy Teams

    Learning Objectives

    After completing this continuing education activity, pharmacists will be able to

    1. DESCRIBE vaccine hesitancy and barriers to vaccination.
    2. RECOGNIZE how determinants of vaccine hesitancy contribute to behavioral outcomes.
    3. RECALL common anti-vaccine claims and evidence-based rebuttals.
    4. DISCUSS situation-appropriate intervention strategies.

    After completing this continuing education activity, pharmacy technicians will be able to

    1. RECALL the benefits of vaccination.
    2. RECOGNIZE determinants of vaccine hesitancy.
    3. LIST ways to promote vaccine acceptance.

       Release Date

      Release Date: September 14, 2026

      Expiration Date: September 14, 2029

      Course Fee

      $7 Pharmacist

      $4 Pharmacy Technician

      There is no funding for this CE.

      ACPE UANs

      Pharmacist: 0009-0000-26-049-H06-P

      Pharmacy Technician: 0009-0000-26-049-H06-T

      Session Codes

      Pharmacist: 26YC49-DIM37

      Pharmacy Technician: 26YC49-MDI73

      Accreditation Hours

      2.0 hours of CE

      Accreditation Statements

      The University of Connecticut School of Pharmacy and Pharmaceutical Sciences is accredited by the Accreditation Council for Pharmacy Education as a provider of continuing pharmacy education.  Statements of credit for the online activity ACPE UAN 0009-0000-26-049-H06-P/T will be awarded when the post test and evaluation have been completed and passed with a 70% or better. Your CE credits will be uploaded to your CPE monitor profile within 2 weeks of completion of the program.


      Disclosure of Discussions of Off-label and Investigational Drug Use

      The material presented here does not necessarily reflect the views of The University of Connecticut School of Pharmacy and Pharmaceutical Sciences or its co-sponsor affiliates. These materials may discuss uses and dosages for therapeutic products, processes, procedures and inferred diagnoses that have not been approved by the United States Food and Drug Administration. A qualified health care professional should be consulted before using any therapeutic product discussed. All readers and continuing education participants should verify all information and data before treating patients or employing any therapies described in this continuing education activity.

      Faculty

      Katherine E. MacDonald PharmD

      Walgreens Pharmacy

      Jewett City, CT


      Faculty Disclosure

      In accordance with the Accreditation Council for Pharmacy Education (ACPE) Criteria for Quality and Interpretive Guidelines, The University of Connecticut School of Pharmacy and Pharmaceutical Sciences requires that faculty disclose any relationship that the faculty may have with commercial entities whose products or services may be mentioned in the activity.

      Katherine MacDonald has no relationships with ineligible companies.


      ABSTRACT

      Vaccines are responsible for reducing the incidence of vaccine-preventable diseases. While most people receive routine recommended vaccinations, a small portion of the population does not. Vaccine hesitancy and refusal are complex behaviors, and the consequences of choosing not to vaccinate jeopardize both individual and societal health and safety.

      Pharmacists and pharmacy technicians must know the determinants and factors that contribute to vaccine hesitancy before they address and manage it appropriately. A comprehensive understanding of such influences can help pharmacists and pharmacy technicians identify and communicate with hesitant individuals better. Pharmacists and technicians are also able to screen patients for missing immunizations, provide patient education and support, and offer guidance.

      CONTENT

      Content

      Pause & Ponder: Which strategies have you used in the past to address patients’ vaccine concerns and questions?


      Introduction


      Vaccines benefit both the individual and the public by preventing the spread and reducing the incidence of vaccine-preventable diseases within a population.1 In developed countries, vaccines are responsible for diminishing the threat of vaccine-preventable diseases,2,3 particularly vaccine-preventable diseases that once plagued infants and children.4,5 A successful vaccination program is contingent on the majority of the population receiving recommended vaccinations as scheduled to ensure both individual and community protection.1,6 This creates ‘herd immunity.’ The vaccination coverage needed for community protection varies by disease; for measles, approximately 95% two-dose coverage is needed to prevent outbreaks. To ensure community protection and patient safety, healthcare providers should see all visits that do not risk patient and provider exposure as opportunities for patients to catch up on missing or late vaccinations.  Pharmacy teams should use every appropriate encounter to assess immunization status and provide needed catch-up vaccination.


      Nonadherence to vaccine recommendations, such as vaccination delay or refusal, undermines individual and public health initiatives.2,7,8 Pharmacists and technicians must also be aware that researchers may not have tested the efficacy of alternative vaccine schedules; such schedules may not produce an adequate immune response. Vaccine-preventable disease outbreaks are a consequence of undervaccination and are a prevalent threat even in the United States.7,8,9 As of August 13, 2026, CDC reported 2,566 confirmed U.S. cases during 2026, with 94% associated with outbreaks.10 Although vaccine-related concerns are common even among vaccine acceptors,1,5,11 several factors still motivate a minority of the population to delay or decline vaccination.1,8,11


      What is Vaccine Hesitancy?


      A panel of World Health Organization (WHO) immunization experts describes vaccine hesitancy as the ‘delay in acceptance or refusal of vaccines despite availability of vaccination services. Vaccine hesitancy is complex and context-specific; that means it varies across time, place, and vaccines. It is influenced by factors such as complacency, convenience, and confidence.’12


      It is important to understand that this definition recognizes only reluctant individuals’ possible decisions. In reality, hesitancy exists on a continuum.13 It ranges from complete refusal of all vaccines to complete acceptance without any concern; in between are intermediate decisions such as refusal of some vaccines and acceptance of others, and full acceptance although the individual is unsure.1 The spectrum of possible outcomes implies that the process of reaching a decision is complicated and guided by external and internal components.11 Identifying the factors that influence an individual’s behavior is essential to understanding the reasons for vaccine hesitancy. Knowing the specifics also helps determine the most appropriate intervention.8,11,13


      Understanding Vaccine Hesitancy


      The terms complacency, convenience, and confidence used in the WHO definition of vaccine hesitancy are the foundation of the ‘3 Cs’ model described in Table 1.14


      Table 1. Definitions of the ‘3 Cs’15


      Confidence: Trust in vaccine effectiveness and safety; the system that delivers them, including the reliability and competence of health services and health professionals; and the motivations of policy makers who decide on the needed vaccines.
      Complacency: The perceived risks of vaccine preventable diseases are low, and vaccination is not deemed a necessary preventive action.
      Convenience: A significant factor when physical availability, affordability and willingness to pay, geographical accessibility, ability to understand (language and health literacy), and appeal of immunization services affect uptake.


      These components are interlinked and influenced by vaccine hesitancy’s determinants (e.g., specific factors that influence an individual’s behavior; see Table 2) to ultimately affect vaccine-related decisions.13 Clinicians can use the determinants of vaccine hesitancy to determine an individual’s beliefs and opinions regarding vaccines and vaccination.5


      WHO’s Behavioral and Social Drivers (BeSD) framework identifies four domains that influence vaccine uptake: thinking and feeling, social processes, motivation, and practical issues. Beliefs, emotions, perceived risks, social norms, and recommendations influence a person’s motivation to receive a vaccine; however, practical barriers such as cost, convenience, and access may prevent vaccination even when motivation is strong. The framework encourages programs to measure these drivers and use the findings to design, implement, and evaluate interventions tailored to specific populations.16


      Table 2. Determinants of Vaccine Hesitancy13


      Influence Category Source of Influence Determinants (factors that affect outcome)
      Contextual influences Influences arising due to historic, socio-cultural, environmental, health system/institutional, economic or political factors §  Communication and media environment

      §  Influential leaders, immunization program gatekeepers and anti- or pro-vaccination lobbies

      §  Historic influences

      §  Religion/culture/gender/socio-economic

      §  Politics/policies

      §  Geographic barriers

      §  Perception of the pharmaceutical industry

      Individual and group influences Influences arising from personal perception of the vaccine or influences of the social/peer environment §  Personal, family, and/or community members' experience with vaccination, including pain

      §  Beliefs, attitudes about health and prevention

      §  Knowledge/awareness

      §  Health system and providers (trust and personal experience)

      §  Risk/benefit (perceived, heuristic [meaning learned from one’s own experiences])

      §  Immunization as a social norm vs. not needed/harmful

      Vaccine/vaccination-specific issues Directly related to vaccine or vaccinations §  Risk/benefit (epidemiological and scientific evidence)

      §  Introduction of a new vaccine , a new formulation, or a new recommendation for an existing vaccine

      §  Mode of administration

      §  Design of vaccination program/mode of delivery (e.g., routine program or mass vaccination campaign)

      §  Reliability and/or source of supply of vaccine and/or vaccination equipment

      §  Vaccination schedule

      §  Costs

      §  The strength of the recommendation and/or healthcare professionals’ knowledge base and/or attitudes


      Pause & Ponder: Which determinants have the most influence over an individual’s decisions? Which have the least?


      Contextual Influences


      Communication and Media Environment. The three most commonly referenced sources for vaccine-related information are healthcare providers, friends and family, and the media (primarily the Internet).5 Although healthcare providers encourage patients to seek knowledge about vaccines from reputable sources when making vaccine-related decisions, misinformation regarding vaccines is prevalent.17 Unfortunately, the widespread presence of incorrect information and universal use of the Internet and social media outlets can result in pervasive transmission of anti-vaccine messages.17 The pharmacy team also needs to repeat vaccine-promoting messages even if they perceive that the patient or parent is well educated; across the United States, areas of highly educated individuals include vaccine refusers.


      Exposure to anti-vaccine ideals can contribute to vaccine hesitancy through confirmation bias.17,18 Confirmation bias occurs when individuals accept only information that supports and validates what they already believe, perpetuating underlying bias.17 For example, if a person believes that all vaccines contain mercury, the person will preferentially read or listen to messages that confirm that incorrect information. (Routine childhood vaccines do not contain thimerosal as a preservative, except for certain multidose influenza vaccine formulations that always list thimerosal on the label.). The consequences of misinformation are twofold: misinformation contributes to how individuals and groups make vaccine-related decisions11,17 and provokes distrust of healthcare providers.2,9,17


      Religion. Faith and religion can have a profound impact on health-related behaviors, with pig (pork or porcine) consumption a particularly important consideration for people who are members of faiths that prohibit pork.19 (Some vegetarians and vegans also have concerns.) This belief does not impede many interventions, as pharmacists and other healthcare providers can recommend an alternative that does not contain porcine derivatives, and many individuals will accept it.19


      A few manufacturers use porcine gelatin as a stabilizer in some vaccine formulations (listed in Table 3).20 Its presence may be the sole reason that members of some religions refuse certain vaccines.19 If an appropriate substitute vaccine is available, pharmacy immunizers should offer this option.


      Table 3. US Vaccines Containing Porcine Gelatin20,21


      Porcine gelatin-containing vaccines Protects against Approximate gelatin per dose
      FluMist* Influenza 2 mg
      MMR-II** Measles, mumps, rubella 14.5 mg
      ProQuad***


      Measles, mumps, rubella, varicella 11mg
      Varivax**** Varicella 8.3–12 mg
      YF-VAX**** Yellow fever Not specified in current U.S. information
      Always check the current package insert/excipient information.

      * Injectable influenza vaccines provide alternatives to FluMist.

      ** PRIORIX is a gelatin-free alternative to M-M-R II.

      *** The United States currently has no gelatin-free varicella vaccine, so replacing ProQuad with PRIORIX plus Varivax does not entirely avoid gelatin.

      **** No alternative yellow fever vaccine is currently licensed in the United States.


      Individual and Group Influences


      Health system and providers: trust and personal experience. The patient-provider relationship is a central element of the vaccine decision-making process for many individuals.22,23 Patients hold healthcare providers—as educators and trusted health authorities—responsible for the outcomes of vaccine hesitancy and refusal-related conversations. The provider’s approach often influences the patient’s decision to vaccinate.


      If the relationship between patient and provider is built on cooperation, trust, and respect, patients are more likely to consider the provider a dependable resource and consider the provider’s behavior an example of best health practices.11 This dynamic permits healthcare professionals to engage in constructive discussion when approached with concerns, or to clarify misinformation that may obstruct the patient’s perspective on vaccines.24 From this vantage point, providers can advocate for vaccination acceptance while maintaining a patient-centered dialogue.5,11


      Conversely, an interaction’s outcome may instead be detrimental to the patient-provider relationship. Examples include when a provider assumes a patient’s reasons for hesitancy, or if a provider’s response does not meet the patient’s expectations.22 Misguided interventions often have the patient’s best interest in mind, yet neglecting a patient-centered approach will fall short of encouraging a reciprocal patient-provider relationship. Such an outcome can occur when a provider’s response to reluctance is providing information and education without first listening to the patient’s concerns (see the section on motivational interviewing below).22 For example, providers who do not ask patients why they refuse vaccines and simply present evidence-based information immediately come across as authoritarian and inflexible. Providers should not consider vaccine acceptance because the patient feels pressured or bullied to be a successful intervention. Other outcomes are also possible. The patient may misinterpret the provider’s efforts as patronizing and, in turn, dismiss the provider’s recommendations.25 Alternatively, patients may become distrustful. If they feel pressured by the provider to accept vaccination or believe the provider ignored or dismissed their concerns, they may consequently avoid future communication and possibly vaccination.22


      Perceived risk/benefit. Vaccine hesitancy is not only specific to vaccines—it also includes disease-specific concerns.8 If individuals believe that they are at risk for contracting a disease, they are more likely to seek and accept a vaccine to prevent that disease.1,8,11 However, this same risk/benefit analysis can produce the opposite outcome if the perceived risk of vaccination is greater than that of disease. It is critical to explain how dangerous vaccine-preventable diseases are.


      Vaccines are responsible for minimizing the incidence of many once-common vaccine-preventable diseases, which has altered many peoples’ perception of their disease susceptibility. That is, people think that now-rare diseases are unlikely to circulate.1,8 This unintended consequence has masked the risks and complications of many debilitating diseases, such as measles. In turn, some people have transferred the fears they previously held toward the disease to concerns regarding vaccine safety and the need for vaccines.1,2,8,9,22 A vaccine’s potential adverse health events may present a greater perceived risk than the disease, contributing to vaccine-hesitant beliefs and behaviors.1


      Knowledge/awareness. Although research confirms that vaccines are safe and effective,26 anti-vaccine sentiments take a variety of forms, as described in Table 4.


      Table 4. Common Anti-Vaccine Sentiments2,11,26,27

      Anti-vaccine claim Pro-vaccine rebuttal
      ‘Hot lots’ of vaccines are responsible for more serious adverse outcomes. Some people believe that some vaccine lots cause more side effects or vaccine injuries than other lots. People who perpetuate this myth apply data from the Vaccine Adverse Event Reporting System (VAERS) inappropriately.


      Members of the pharmacy team should explain that expected vaccine side effects—such as injection-site pain, fatigue, or a mild fever—differ from adverse events reported after vaccination. An adverse event is any health problem occurring after vaccination, whether mild or serious and whether or not the vaccine caused it. A VAERS report alone cannot establish causation; CDC and FDA use reports to identify signals that require further investigation.
      Antigenic overload occurs in children because their immune systems are unable to manage the number of antigens that vaccines introduce adequately, or antigenic overload causes a ‘cytokine storm’ that predisposes children to adverse events and vaccine-induced complications.


      No scientific evidence supports this claim. Additionally, children are exposed to significantly more antigens at birth than through vaccines. In a 2017 CDC comparison, vaccines used approximately 305 antigens to protect children against 14 diseases by age 2, compared with approximately 3,000 antigens used to protect against eight diseases 30 years earlier.
      Natural immunity from an infection is safer than immunity from a vaccine. Infection-induced immunity may elicit a superior immune response. However, the risks and complications associated with infection are significantly greater than those of vaccines. Vaccine-induced immunity is able to prevent infection successfully. Measles can cause immune amnesia, reducing previously acquired immune protection for months to years.
      Vaccines are responsible for the development of autoimmune diseases such as type 1 diabetes mellitus, multiple sclerosis, and Guillain-Barre syndrome.

      ·       This argument is based on the theory that the immune system is unable to discriminate between intrinsic antigens and the vaccine’s antigens, causing antibodies to bind the intrinsic antigens selectively, eliciting an autoimmune response.

      Multiple efforts have reviewed this claim. A panel of experts from the Institute of Medicine reviewed more than 12,000 published reports and several high-quality studies; none established a connection between vaccines and autoimmune diseases.


      Pause & Ponder: How do misinformation and anti-vaccine sentiments circulate widely when the correct recommendations and evidence supporting vaccination are just as accessible?


      Intervention Strategies: A Personalized Approach


      Patients and healthcare professionals need to work together—that is, collaborate and share decision-making—to adhere to vaccination programs and can do so after they take certain steps13:


      • Understand the risks and benefits of vaccination
      • Explain the vaccine-preventable disease and the consequences of contracting it. Make evidence-based decisions (such as adhering to recommended vaccine schedules) for patients. This means accessing CDC patient websites if patients need more information than the healthcare provider can provide.
      • Accept accountability for the health and safety of individuals who are unable to be vaccinated; patients who are healthy and robust need to understand that their failure to ‘join the herd’ of vaccinated people puts others at risk.
      • Advocate for health equity (the concept that everyone should have a fair opportunity to attain their full health potential and that no one should be disadvantaged from achieving this potential) regarding access to vaccine-related resources and the elimination of barriers.


      Efforts that involve patients and providers working collaboratively—sharing evidence, understanding each other’s points of view, and working toward good health for our entire society, not just the individual—depend on two things. First, providers must consider vaccine-hesitant patients’ needs and how they affect public health and safety needs. Second, providers need to consider their other patients; some practices will not see patients who refuse vaccines because they would potentially expose other patients to vaccine-preventable disease.22 Although the laws surrounding patient dismissal in this situation are not straightforward, ethical concerns such as negligence can manifest as legal troubles or disciplinary actions from the provider’s regulatory authority.28


      Beliefs and behaviors that relate to vaccine hesitancy vary at an individual level; clinicians must individualize strategies to address these concerns and ideally increase vaccine acceptance.1,9,11,19 Interventions should prioritize the patient’s autonomy,29 recognize the influence of specific determinants (particularly context and individual determinants),9,13 and ameliorate any barriers that may be present.11


      Identify Questions And Concerns: Motivational Interviewing

      Immunizers should begin the vaccine discussion with a strong recommendation presented in a presumptive format; that means speaking as though vaccination is the expected, routine next step—not presenting it initially as an open-ended decision. If the patient or parent expresses hesitancy, immunizers can then use motivational interviewing to explore and address the person’s concerns.30 Motivational interviewing is a communication technique that directs constructive conversations between patient and provider. This approach gives patients the opportunity to address their concerns consciously while actively informing the patient’s decision-making process, which promotes behavioral change through self-realized motivation.22,31 Motivational interviewing is not intuitive, and pharmacists and technicians sometimes need help identifying the questions to ask. The process itself has five steps:

      1. Listen to the patient’s concerns and any possibility that the patient may change
      2. Reflect back your understanding
      3. Identify missing or incorrect information
      4. Invite the patient to reconsider
      5. Summarize and reiterate the next steps


      Motivational interviewing (and open-ended questions) can help patients resolve their hesitancy.32,33 Immunizers need to listen to patients’ thoughts about change and what they think change will require. Reflect your understanding (‘I know that you have many vaccine-related concerns.’) Then, identify missing or incorrect information, but do not do it in a confrontational or scolding manner. Ask if you can address an issue directly and do so only if the patient agrees. (‘May I tell you something about vaccination that I learned in a continuing education class recently?’) Invite patients to reconsider, then summarize and reiterate next steps. (‘You said that needle-induced pain is a concern, and we talked about two things that might help—breathing exercises and topical spray that numbs the area. Which of those approaches might you be able to try before giving up?’)34,35 Some parents refuse the HPV vaccine for their teens, and after discussion, you might say, ‘You said that vaccination for HPV would encourage your son to engage in unprotected sexual activity. We agreed that it would be even MORE dangerous if he has unprotected sex without being vaccinated. And we agreed that kids often make risky decisions, and we identified two possible courses of action. You might talk to him about the risks of unprotected sex and ask him what he has heard about HPV vaccination in health class. Which of those approaches might you be able to try before giving up?’


      Providers must maintain a welcoming and patient-centered environment by remaining attentive and empathetic to the patient’s concerns and questions.31 To ensure this dynamic and encourage a cooperative and honest patient-provider relationship, providers should ask for the patient’s permission before dispensing advice or information if possible.25,31 This helps providers direct their input toward specific issues and prevents overwhelming the patient with unsolicited information.31


      Confront misinformation: Debiasing

      If a patient expresses concerns that refer to vaccine misinformation, debiasing may help correct the misconception.36 (These techniques come from social sciences journals and are not terms with which most pharmacists or technicians are familiar; they are included because they help address misinformation.) Providers must first gain an accurate understanding of the patient’s beliefs, as they can use debiasing techniques only if the patient is receptive to the proposed correction.36 Table 5 defines the potential impact of misinformation and associated intervention strategies. Debiasing requires everyone who counsels vaccine-hesitant patients to be on the same page.  Healthcare organizations should establish and consistently enforce evidence-based employee immunization policies that protect patients. Regardless of their personal beliefs, employees who counsel patients must provide accurate, evidence-based vaccine information and must not undermine recommended immunization practices.36


      Table 5. Misinformation Debiasing Strategies 36,37,38,39,40


      Effect of misinformation Debiasing techniques
      Misinformation, regardless of a correction, has continued influence over beliefs and behaviors. Clinicians create an information gap when they simply correct a misconception; provide an alternative evidence-based explanation to fill the gap.


      Familiarity backfire occurs when repetition strengthens a false belief. In some cases, patients later remember the myth rather than the evidence that disproves it—meaning the provider’s efforts backfired. Start with the facts and introduce the misinformation only afterward. Before mentioning misinformation, explicitly state that it is false. Explain why it is misleading and why people may believe it. Correct misinformation immediately after mentioning it and provide a reasonable explanation to replace the myth. Avoid repeating misinformation and then merely saying it is not true; focus on the correct explanation instead.


      Overkill backfire occurs when misinformation is easier to understand than a complicated correction, making the truth seem unrealistic. Corrections can occasionally strengthen a mistaken belief, but recent research suggests that these backfire effects are uncommon and should not discourage healthcare professionals from correcting misinformation. Keep corrections straightforward and short—less is more. For example, if a patient believes childhood vaccination causes type 1 diabetes, an elaborate explanation of disease pathology may overcomplicate the correction. A short, clear statement that evidence has not established such a connection is more useful.


      Worldview backfire occurs when a personal belief is threatened by the truth and misinformation is reinforced Affirm worldview with corrections that support the individual’s values and concentrate on positive facts, such as benefits and opportunities.


      Persistent refusal: Standby Strategies. Patients and parents may be unresponsive to vaccine-promoting interventions. If an individual continues to refuse vaccination, it is most important to acknowledge and honor the right to decline.17,25 Immunizers should not discount these interactions or label them as failures, but instead consider them an opportunity to try again later. Providers should encourage future contact if the patient has more questions or changes their mind regarding vaccination.25,41


      Healthcare providers must maintain respect and provide direct clinical recommendations for vaccinations.25 Finally, healthcare providers should inform patients of their responsibilities and vaccine refusal’s potential consequences (see Resources for Pharmacy Staff below for the CDC document, ‘If You Choose Not to Vaccinate Your Child, Understand the Risks and Responsibilities,’ and links to vaccine refusal documentation forms).41


      Conclusion


      Vaccine hesitancy is a complicated and often emotional issue. Pharmacists and pharmacy staff can identify obstacles and barriers to vaccination and acceptance through education and support while also offering reliable access to vaccines.4 Pharmacies eliminate barriers that prevent access to vaccine delivery services and increase vaccination rates through pharmacist-driven interventions.4,42,43 This presence and resultant impact on public health testifies to the importance of pharmacists as trained and certified immunizers.4 To maintain the success of pharmacy-based vaccination services, pharmacists and pharmacy staff should have a comprehensive and functional understanding of vaccine hesitancy and the skills to confront it appropriately.


      Be aware of common patient/parental concerns/misperceptions1,5,18,7:

      • Number of vaccines given to young children
      • Side effects and adverse health events (including misunderstandings including associations with autism)
      • Vaccine safety (harmful ingredients; insufficient safety testing)
      • Vaccine efficacy
      • Mandatory childhood vaccines1
      • Pain at vaccination

      Remember that questions and concerns offer the opportunity for discussion and should not be interpreted as defiance or the intent to delay or refuse a vaccine.5


      Identify barriers that prevent vaccination38,9:

      • Accessibility to vaccination services
      • Vaccination costs
      • Distrust of vaccine
      • Distrust of provider administering vaccination
      • Perceived need of vaccine
      • Gaps in knowledge – such as how vaccines work or about VPDs
      • Misinformation


      Implement an appropriate intervention: While various strategies may be employed to promote vaccine uptake, an intervention’s success is not contingent on its outcome – whether a patient chooses to vaccinate or not. Instead, immunizers should measure an intervention by its ability to meet the patient’s expectations and by the provider’s patience and empathy.


      Communicate risks: Effective risk communication is dependent on the patient and must be individualized to the patient’s or parents concerns.22,34,35 Risk discussion should disclose the potential risks of diseases and benefits of vaccines, in an honest, evidence-based, and intelligible manner.34,35


      Activation Strategies: Activation strategies encourage individuals that intend to get vaccinated to do so.41 Patient reminders are a useful method to increase vaccination across all ages.42 Phone calls, automated messages, and postcards are examples of successful activation opportunities.44 Immunizers and support staff can also activate patients during face-to-face interactions. Screening patients can help the pharmacy staff provide appropriate vaccine recommendations, education, and where vaccination services may be found.4


      Address pain: Needle-related pain is a common concern for people of all ages.5,7 Though recommendations to reducing pain vary between age groups, pain in adults can be minimized with the following recommendations7:

      • During vaccine administration have the patient sit upright, implement breathing techniques (such as asking the patient to hold their breath)
      • Avoid reassurances that convey that the experience will not be painful
      • Suggest a topical anesthetic - liposomal lidocaine, amethocaine, or lidocaine-prilocaine are agents that may be applied 20 to 60 minutes before injection, or a topical vapocoolant may be used right before vaccination

      Road_to_Vaccine_Acceptance_REVISED

      infographic on various roadblocks and suggestions for overcoming them

      Resources for the Pharmacy Staff

      Centers for Disease Control and Prevention—Vaccine Excipient Summary: Excipients Included in U.S. Vaccines, by Vaccine https://www.cdc.gov/vaccines/pubs/pinkbook/downloads/appendices/b/excipient-table-2.pdf


      CDC – “If You Choose Not to Vaccinate Your Child, Understand the Risks and Responsibilities” https://stacks.cdc.gov/view/cdc/49075


      CDC – Current immunization schedules www.cdc.gov/vaccines/schedules/index.html

      Pharmacist Post Test (for viewing only)

      Vaccine Hesitancy: Rebooting Management Strategies for Pharmacy Teams

      26-049-H06-Pharmacist Post-test


      Pharmacist Learning Objectives:

      1. Describe vaccine hesitancy and barriers to vaccination
      2. Recognize how determinants of vaccine hesitancy contribute to behavioral outcomes
      3. Recall anti-vaccine claims and rebuttals
      4. Discuss situation-appropriate intervention strategies


      1. Which of the following MOST CLOSELY corresponds to the WHO definition of vaccine hesitancy?

      a. Simple vaccine refusal in any context including lack of available vaccination services

      b. Acceptance of any vaccine if the ability to access vaccination is convenient

      c. Delay in acceptance or refusal of vaccines despite availability of vaccination services


      *


      2. Select the influence category, source of influence, and determinants that are paired correctly.

      a. Contextual influence—peer environment--costs

      b. Vaccine-specific issues—specific vaccine—mode of administration

      c. Group influences—political factors—reliability of vaccine supply


      *


      3. A mother indicates she does not and will not vaccinate her children. You use motivational interviewing and learn that she believes natural immunity is safer than vaccine-induced immunity. What is an appropriate rebuttal if she consents to listen?

      a. Infection-induced immunity may elicit a superior immune response. However, the risks and complications associated with infection are significantly greater than those of vaccines

      b. A panel of experts from the Institute of Medicine reviewed more than 12,000 published reports and several high-quality studies; none indicate natural immunity is stronger

      c. The CDC’s system to track natural immunity vs. vaccine-induced immunity is called VAERS; you can examine the data in VAERS and see that your assumptions are wrong


      *


      4. Susan comes to the pharmacy and your technician reminds her she is due for her second HPV vaccination. Susan glances to the pharmacist’s workstation and quickly says, “Ummm, not today.” The technician gently says, “You’re here, and we’re not busy. Why don’t we get it done?” Susan replies, “No, not today. That guy gave me the last one and left a huge bruise. Not today.” What type of barrier is keeping Susan from her second shot?

      a. Vaccine accessibility

      b. Distrust of provider

      c. Gaps in knowledge


      *


      5. Dave arrives at the pharmacy to pick up his “sugar meds” and you notice that he hasn’t received his flu shot yet. After providing him with a clinical recommendation for the vaccine, Dave replies, “Why do I need to? I work from home and have never gotten the flu before. What’s the point?!” Which barrier is preventing Dave from getting the flu shot?

      a. Distrust of vaccine

      b. Misinformation

      c. Perceived need for vaccine


      *


      6. Manny is a regular customer who appears to be up to date on all of his vaccines except for the shingles vaccination. When you ask him why, he states that it’s for religious reasons, but says “I’d give it a try if there’s a shot without any pork in it.” Which intervention strategy would be most appropriate for Manny’s situation?

      a. Motivational interviewing about worldview

      b. Debiasing techniques to address overkill

      c. Offering Shingrix as an alternative


      Pharmacy Technician Post Test (for viewing only)

      Vaccine Hesitancy: Rebooting Management Strategies for Pharmacy Teams

      26-049 Pharmacy Technician Post-test


      Pharmacy Technician Objectives:

      1.Recall the benefits of vaccination

      2. Recognize the various determinants of vaccine hesitancy

      3. List ways to promote vaccine acceptance


      1. Which of the following is a benefit of vaccination?

      a. Vaccines reduce the incidence of some diseases

      b. Vaccines completely eradicate vaccine-preventable diseases

      c. Vaccines only benefit vaccinated infants and children


      *


      2. Which of the following vaccination patterns helps ensure the success of a vaccination program?

      a. Only high-risk people receive recommended vaccines

      b. Most people receive recommended vaccines on schedule

      c. Most infants and children receive some vaccines


      *


      3. Mary tells you that she has not been vaccinated because the only place that is covered by her insurance requires a subway ride and then a taxi ride. Which of the following is the most likely factor preventing Mary from receiving a vaccine?

      a. Geographic restrictions imposed by insurance

      b. Poor communication with her healthcare provider

      c. A bad attitude about necessary health care


      *


      4. Joe lives in a rural area, and your pharmacist suggests he receive a flu shot. Joe says that his own doctor said that flu shots are fine, but not necessary for healthy folks. (The doctor said he hasn’t gotten one, and isn’t worried about it.) Which of the following is the most likely influence category to explain Joe’s vaccine hesitancy?

      a. Vaccine/ vaccination-specific issues

      b. Individual and group influences

      c. Contextual influences


      *


      5. Which of the following is a way to promote vaccination in hesitant individuals?

      a. Ask the pharmacist to increase motivation using pressure

      b. Debunk any misinformation an individual may reference

      c. Listen to the individual’s concerns before taking action


      References

      Full List of References

      1. Salmon DA, Dudley MZ, Glanz JM, Omer SB. Vaccine hesitancy: Causes, consequences, and a call to action. Vaccine. 2015;33 Suppl 4:D66-D71. doi:10.1016/j.vaccine.2015.09.035
      2. Poland GA, Jacobson RM. The clinician's guide to the anti-vaccinationists' galaxy. Hum Immunol. 2012;73(8):859-866. doi:10.1016/j.humimm.2012.03.014
      3. Andre FE, Booy R, Bock HL, et al. Vaccination greatly reduces disease, disability, death and inequity worldwide. Bull World Health Organ. 2008;86(2):140-146. doi:10.2471/blt.07.040089
      4. Aruru M, Truong HA, Clark S. Pharmacy Emergency Preparedness and Response (PEPR): a proposed framework for expanding pharmacy professionals' contributions to emergency preparedness and response during the COVID-19 pandemic and beyond. Res Social Adm Pharm. 2020;S1551-7411(20)30323-5. doi:10.1016/j.sapharm.2020.04.002
      5. Kennedy A, Lavail K, Nowak G, et al. Confidence about vaccines in the United States: understanding parents' perceptions. Health Aff (Millwood). 2011;30(6):1151-1159. doi:10.1377/hlthaff.2011.0396
      6. Mallory ML, Lindesmith LC, Baric RS. Vaccination-induced herd immunity: Successes and challenges. J Allergy Clin Immunol. 2018;142(1):64-66. doi:10.1016/j.jaci.2018.05.007
      7. Taddio A, McMurtry CM, Shah V, et al. Reducing pain during vaccine injections: clinical practice guideline. CMAJ. 2015;187(13):975-982. doi:10.1503/cmaj.150391
      8. Omer SB, Orenstein WA, Koplan JP. Go big and go fast—vaccine refusal and disease eradication. N Engl J Med. 2013;368(15):1374-1376. doi:10.1056/NEJMp1300765
      9. Habersaat KB, Jackson C. Understanding vaccine acceptance and demand—and ways to increase them. Bundesgesundheitsblatt Gesundheitsforschung Gesundheitsschutz. 2020;63(1):32-39. doi:10.1007/s00103-019-03063-0
      10. Centers for Disease Control and Prevention. Measles cases and outbreaks. Accessed August 21, 2026. https://www.cdc.gov/measles/data-research/index.html
      11. Nour R. A systematic review of methods to improve attitudes towards childhood vaccinations. Cureus. 2019;11(7):e5067. doi:10.7759/cureus.5067
      12. Report of the SAGE Working Group on Vaccine Hesitancy. 2014. Accessed August 21, 2026. https://www.medbox.org/document/report-of-the-sage-working-group-on-vaccine-hesitancy
      13. Butler R, MacDonald NE; SAGE Working Group on Vaccine Hesitancy. Diagnosing the determinants of vaccine hesitancy in specific subgroups: The guide to Tailoring Immunization Programmes (TIP). Vaccine. 2015;33(34):4176-4179. doi:10.1016/j.vaccine.2015.04.038
      14. WHO EURO Working Group on Vaccine Communications. Istanbul, Turkey. October 13-14, 2011.
      15. MacDonald NE; SAGE Working Group on Vaccine Hesitancy. Vaccine hesitancy: Definition, scope and determinants. Vaccine. 2015;33(34):4161-4164. doi:10.1016/j.vaccine.2015.04.036
      16. World Health Organization. Behavioural and Social Drivers of Vaccination: Tools and Practical Guidance for Achieving High Uptake. World Health Organization; 2022. Accessed August 21, 2026. https://www.who.int/publications/i/item/9789240049680
      17. MacDonald NE, Dubé E. Promoting immunization resiliency in the digital information age. Can Commun Dis Rep. 2020;46(1):20-24. doi:10.14745/ccdr.v46i01a04
      18. Meppelink CS, Smit EG, Fransen ML, Diviani N. ‘I was right about vaccination’: Confirmation bias and health literacy in online health information seeking. J Health Commun. 2019;24(2):129-140. doi:10.1080/10810730.2019.1583701
      19. Paterson P, Chantler T, Larson HJ. Reasons for non-vaccination: Parental vaccine hesitancy and the childhood influenza vaccination school pilot programme in England. Vaccine. 2018;36(36):5397-5401. doi:10.1016/j.vaccine.2017.08.016
      20. U.S. Food and Drug Administration. Vaccines licensed for use in the US. Accessed August 20, 2026. https://www.fda.gov/vaccines-blood-biologics/vaccines/vaccines-licensed-use-united-states
      21. Children’s Hospital of Philadelphia Vaccine Education Center. Vaccine ingredients: gelatin. Updated June 18, 2026. Accessed August 21, 2026. https://www.chop.edu/vaccine-education-center/vaccine-safety/vaccine-ingredients/gelatin
      22. Leask J, Kinnersley P, Jackson C, et al. Communicating with parents about vaccination: a framework for health professionals. BMC Pediatr. 2012;12:154. doi:10.1186/1471-2431-12-154
      23. Paterson P, Meurice F, Stanberry LR, et al. Vaccine hesitancy and healthcare providers. Vaccine. 2016;34(52):6700-6706. doi:10.1016/j.vaccine.2016.10.042
      24. Gust DA, Darling N, Kennedy A, Schwartz B. Parents with doubts about vaccines: which vaccines and reasons why. Pediatrics. 2008;122(4):718-725. doi:10.1542/peds.2007-0538
      25. Fogarty CT, Crues L. How to talk to reluctant patients about the flu shot. Fam Pract Manag. 2017;24(5):6-8.
      26. Six common misconceptions about vaccination—and how to respond to them. Int J Trauma Nurs. 1998;4(3):109-112. doi:10.1016/S1075-4210(98)90079-7
      27. Centers for Disease Control and Prevention. How Vaccines Strengthen Your Baby’s Immune System. Published July 10, 2017. Accessed August 21, 2026. https://stacks.cdc.gov/view/cdc/143124
      28. Halperin B, Melnychuk R, Downie J, Macdonald N. When is it permissible to dismiss a family who refuses vaccines? Legal, ethical and public health perspectives. Paediatr Child Health. 2007;12(10):843-845. doi:10.1093/pch/12.10.843
      29. Tafuri S, Gallone MS, Cappelli MG, et al. Addressing the anti-vaccination movement and the role of HCWs. Vaccine. 2014;32(38):4860-4865. doi:10.1016/j.vaccine.2013.11.006
      30. O’Leary ST, Opel DJ, Cataldi JR, Hackell JM; Committee on Infectious Diseases; Committee on Practice and Ambulatory Medicine; Committee on Bioethics. Strategies for improving vaccine communication and uptake. Pediatrics. 2024;153(3):e2023065483. doi:10.1542/peds.2023-065483
      31. Gagneur A, Gosselin V, Dubé È. Motivational interviewing: A promising tool to address vaccine hesitancy. Vaccine. 2018;36(44):6553-6555.
      32. Wibowo E, Wassersug RJ, Robinson JW, et al. An educational program to help patients manage androgen deprivation therapy side effects: feasibility, acceptability, and preliminary outcomes. Am J Mens Health. 2020;14(1):1557988319898991. doi:10.1177/1557988319898991
      33. Spencer JC, Wheeler SB. A systematic review of motivational interviewing interventions in cancer patients and survivors. Patient Educ Couns. 2016;99(7):1099-1105. doi:10.1016/j.pec.2016.02.003
      34. Gong Z, Veuthey J, Han Z. What makes people intend to take protective measures against influenza? Perceived risk, efficacy, or trust in authorities. Am J Infect Control. 2020;S0196-6553(20)30755-0. doi:10.1016/j.ajic.2020.07.029
      35. Krueger BS, Hutchison ML, Bodo EC, et al. Science-based communication to decrease disparities in adult pneumococcal vaccination rates. J Am Pharm Assoc (2003). 2020;S1544-3191(20)30263-6. doi:10.1016/j.japh.2020.05.020
      36. Lewandowsky S, Ecker UKH, Seifert CM, et al. Misinformation and its correction: continued influence and successful debiasing. Psychol Sci Public Interest. 2012;13:106-131.
      37. Dubé E, Gagnon D, Vivion M. Optimizing communication material to address vaccine hesitancy. Can Commun Dis Rep. 2020;46(2-3):48-52. doi:10.14745/ccdr.v46i23a05
      38. Ecker UK, Lewandowsky S, Tang DT. Explicit warnings reduce but do not eliminate the continued influence of misinformation. Mem Cognit. 2010;38(8):1087-1100. doi:10.3758/MC.38.8.1087
      39. van der Linden S. Misinformation: susceptibility, spread, and interventions to immunize the public. Nat Med. 2022;28:460-467. doi:10.1038/s41591-022-01713-6
      40. Swire-Thompson B, DeGutis J, Lazer D. Searching for the backfire effect: measurement and design considerations. J Appl Res Mem Cogn. 2020;9(3):286-299. doi:10.1016/j.jarmac.2020.06.006
      41. MacDonald NE, Butler R, Dubé E. Addressing barriers to vaccine acceptance: an overview. Hum Vaccin Immunother. 2018;14(1):218-224. doi:10.1080/21645515.2017.1394533
      42. Drozd EM, Miller L, Johnsrud M. Impact of pharmacist immunization authority on seasonal influenza immunization rates across states. Clin Ther. 2017;39(8):1563-1580.e17. doi:10.1016/j.clinthera.2017.07.004
      43. Alsabbagh MW, Church D, Wenger L, et al. Pharmacy patron perspectives of community pharmacist administered influenza vaccinations. Res Social Adm Pharm. 2019;15(2):202-206. doi:10.1016/j.sapharm.2018.04.015
      44. Jacobsen Vann JC, Jacobson RM, Coyne-Beasley T, et al. Patient reminder and recall interventions to improve immunization rates. Cochrane Database Syst Rev. 2018;1:CD003941.

      Rethinking Cholesterol: Putting the 2026 AHA/ACC Guidelines into Practice

      Learning Objectives

      At the completion of this activity, the pharmacist will be able to:
      1. RECALL lipid management goals and ASCVD risk based on comorbidities and cardiovascular disease history
      2. MATCH available lipid-lowering medications' mechanisms of action, efficacy, safety, and place in therapy
      3. IDENTIFY optimal lipid-management plans that combine evidence-based recommendations, patient-specific factors, and medication adherence
      4. MANAGE lipid-lowering medication regimens based on therapeutic lab monitoring and adverse effects when indicated

      At the completion of this activity, the pharmacy technician will be able to:
      1. REVIEW common lipid-lowering medications and their indications
      2. DETECT patient concerns or questions that warrant pharmacist intervention
      3. DESCRIBE proper storage, processing, dispensing, and counseling for lipid-lowering therapies
      4. OPTIMIZE coverage plans to decrease barriers to medication access

        A cross section of an artery with labeling on the artery wall, red blood cells, and cholesterol plaque partially blocking blood flow

         Release Date

        Release Date: September 10, 2026

        Expiration Date: September 10, 2029

        Course Fee

        $7 Pharmacist

        $4 Pharmacy Technician

        There is no funding for this CE.

        ACPE UANs

        Pharmacist: 0009-0000-26-046-H01-P

        Pharmacy Technician: 0009-0000-26-046-H01-T

        Session Codes

        Pharmacist: 26YC46-MLC51

        Pharmacy Technician: 26YC46-CLM15

        Accreditation Hours

        2.0 hours of CE

        Accreditation Statements

        The University of Connecticut School of Pharmacy and Pharmaceutical Sciences is accredited by the Accreditation Council for Pharmacy Education as a provider of continuing pharmacy education.  Statements of credit for the online activity ACPE UAN 0009-0000-26-046-H01-P/T will be awarded when the post test and evaluation have been completed and passed with a 70% or better. Your CE credits will be uploaded to your CPE monitor profile within 2 weeks of completion of the program.


        Disclosure of Discussions of Off-label and Investigational Drug Use

        The material presented here does not necessarily reflect the views of The University of Connecticut School of Pharmacy and Pharmaceutical Sciences or its co-sponsor affiliates. These materials may discuss uses and dosages for therapeutic products, processes, procedures and inferred diagnoses that have not been approved by the United States Food and Drug Administration. A qualified health care professional should be consulted before using any therapeutic product discussed. All readers and continuing education participants should verify all information and data before treating patients or employing any therapies described in this continuing education activity.

        Faculty

        Ethan Nolin-Halpern, B.S Pharmacy Studies, PharmD Candidate 2027

        University of Connecticut School of Pharmacy and Pharmaceutical Sciences

        Storrs, CT


        Jeannette Y. Wick RPh, MBA, FCCP

        Director Office Pharmacy Professional Development

        University of Connecticut School of Pharmacy and Pharmaceutical Sciences

        Storrs, CT

        Faculty Disclosure

        In accordance with the Accreditation Council for Pharmacy Education (ACPE) Criteria for Quality and Interpretive Guidelines, The University of Connecticut School of Pharmacy and Pharmaceutical Sciences requires that faculty disclose any relationship that the faculty may have with commercial entities whose products or services may be mentioned in the activity.

        Ethan Nolin-Halpern and Jeannette Wick have no relationships with ineligible companies.


        ABSTRACT

        Cardiovascular disease is one of the most common causes of death in the United States. Patients with cardiovascular disease are at a significantly heightened risk for serious cardiac events such as heart attack, stroke, and sudden cardiac death. Preventing the progression of cardiovascular disease through tailored cholesterol goals, lifestyle management, and guideline-directed lipid-lowering medications is vital.

        This continuing education activity highlights the 2026 update to the American Heart Association and American College of Cardiology Cholesterol Management Guidelines. The guidelines emphasize calculating 10-year cardiovascular disease risk, personalized risk calculation, reclassification with specific lipid biomarkers, and reassessment of lipid-lowering treatment—the CPR framework—to properly manage patients’ cholesterol. Pharmacists and pharmacy technicians should become familiar with the updated guidelines to improve patient outcomes in the evolving field of cholesterol management.

        CONTENT

        Content

        INTRODUCTION

        For decades, lipid management focused on treating lipoprotein numbers. The 2026 guidelines instead emphasize individualized cardiovascular risk, earlier intervention, and lower low-density lipoprotein (LDL) targets for patients at highest risk. Patient Nick Smith is a 68-year-old male recently seen by the cardiologist. He currently takes several medications: metformin, empagliflozin, metoprolol succinate, sacubitril/valsartan, rosuvastatin, and loratadine. He has a past medical history of type 2 diabetes mellitus, hyperlipidemia, hypertension, heart failure with reduced ejection fraction (38%), and seasonal allergies. He is also a current smoker with a 15-pack-year smoking history. He has no history of myocardial infarction, ischemic stroke, peripheral artery disease, or coronary revascularization. Reviewing the cardiologist’s notes, his LDL-C is 91 mg/dL and his PREVENT Score is 10.2%.

        Nick’s prescriber reviews the new guideline and pauses. Nick has several cardiovascular risk factors, but has never had an ASCVD event. Is this primary or secondary prevention? Does he need a coronary artery calcium (CAC) scan? Does his heart failure change the classification?  And is the statin dose sufficient? Rather than guess, the prescriber calls clinical pharmacist George Johnson and requests a complete lipid-management assessment.


        Atherosclerotic Cardiovascular Disease  

        Atherosclerosis, or the buildup of plaque within an artery, is a leading cause of death in the United States.1 In 2023, cardiovascular disease caused 1 in 3 deaths nationwide.2 As plaques grow, they progressively occlude arteries and can eventually rupture. Plaque rupture triggers local platelet-rich thrombus (clot) formation, leading to acute coronary syndromes (unstable angina or myocardial infarction [heart attack]), and sudden cardiac death. In cerebral circulation, atherosclerosis can reduce blood flow or promote thrombus formation, leading to ischemic stroke.3Two considerations guide lipoprotein management.3 The first consideration is determining if patients have established atherosclerotic cardiovascular disease (ASCVD), and the second is establishing individualized lipid goals based on the patient’s cardiovascular risk. This risk-based approach allows clinicians to tailor lifestyle interventions and initiate lipid-lowering therapy (LLT) to reduce the likelihood of future cardiovascular events. Strong evidence supports cholesterol management as the preferred method to reduce mortality and preventable cardiac deaths and improve quality of life.3

        High LDL can cause catastrophic cardiovascular events and stroke later in life. Unfortunately, patients do not experience bothersome symptoms until the damage is done. New evidence suggests that higher LDL-C values starting earlier in life are strong predictors of ASCVD events in adulthood.4 So, screening patients early and periodically, minimizing modifiable risk factors, and initiating aggressive early lipid-lowering interventions are important.5 After an ASCVD event, secondary prevention is imperative to reduce the risk of another event.


        Cholesterol Screening Blueprint

        When clinicians examine lipid panels for patients, they need to use standardized methods for measuring lipoprotein levels.3 Total cholesterol is the sum of high-density lipoprotein (HDL, also called the good cholesterol), LDL, and the very-low-density lipoprotein (VLDL) component of triglyceride (TG) levels.6 The 2026 American College of Cardiology/American Heart Association (ACC/AHA) guidelines define high total cholesterol as levels greater than 200 mg/dL. LDL is considered high above 100 mg/dL. HDL should remain above 40 mg/dL in men and 50 mg/dL in women. Non–HDL is calculated by subtracting HDL from total cholesterol or adding together the LDL and VLDL, with values above 130 mg/dL considered high. Non-HDL is important in determining other lipoproteins besides LDL that can contribute to atherosclerosis.

        The guidelines also recommend measuring lipoprotein(a), a cholesterol-carrying lipoprotein, at least once. Its normal levels are less than 75 nmol/L with intermediate levels between 75 and 125 nmol/L. Levels above 125 nmol/L independently increase the risk for ASCVD.7 Genetics heavily influences lipoprotein(a) levels, and levels remain relatively unchanged after age 5, meaning testing once is often sufficient.8

        LDL-C measurements may underestimate the number of circulating atherogenic particles. In patients who are taking lipid-lowering therapy (LLT) and have high TG levels, cardiometabolic disease, or diabetes despite LDL-C at goal, apolipoprotein B (ApoB) is useful to determine if therapeutic intensification is warranted.3,9,10 ApoB is the main structural protein found in LDL, VLDL, intermediate-density lipoprotein (IDL), and lipoprotein(a) particles. Elevated ApoB at therapeutic LDL levels suggests persistent atherogenic particle burden that may increase residual ASCVD risk. Many patients with diabetes who have normal cholesterol levels also have elevated ApoB concentrations.11 ApoB is a useful adjunct to traditional lipid measurements to determine if clinicians should intensify LLT.3

        TGs should be below 150 mg/dL.3 While high TG levels contribute to ASCVD risk, LDL is the primary lipid target for risk reduction. However, TG levels above 500 mg/dL increase the risk of pancreatitis. Lipoprotein and TG thresholds may change based on a patient’s cardiovascular risk factors and history, meaning interventions may be appropriate even when lipid values fall below these cutoffs.3

        Between 2017 and 2020, nearly 90 million adults aged 20 or older had elevated total cholesterol (200 mg/dL or greater).12 Increasing age, comorbidities, and established ASCVD are factors that call for increased screening frequency. Additionally, one in five adolescents had an LDL above 130 mg/dL.13 Pediatricians should screen children between the ages of 9 and 11 at least once, and again between the ages of 17 and 21.12 Children with obesity or diabetes may need more frequent screening. Diabetes, heart failure, hypertension, current or former smoking history, or consistently high LDL levels warrant more frequent testing. Clinicians should order lipid panels for patients with established ASCVD every 4 to 12 weeks after initiating or titrating LLT, and then every 6 to 12 months thereafter. 3

        PAUSE AND PONDER: Can LDL values be too low?


        Defining ASCVD, Calculating PREVENT Scoring, and Personalizing Primary Prevention Goals

        Determining if patients are at risk for ASCVD (and the level of risk) or have experienced an ASCVD event is critical. Whether or not a patient has established ASCVD greatly impacts their risk for future cardiovascular events, and their treatment goals. In short, the best predictor of a future event is a past event in this case.

        Because atherosclerosis affects the body systemically, clinical ASCVD can manifest in the heart and in other vascular areas.3 Locally, ASCVD can result in myocardial infarction (ST-segment elevation [STEMI] and non-ST-segment elevation [NSTEMI]), unstable angina, or the need for arterial revascularization, such as bypass or stents. Ischemic stroke or a transient ischemic attack (TIA) can result if clots embolize and travel to the brain. Finally, plaque buildup in lower extremity arteries leads to peripheral artery disease (PAD). Heart failure, hypertension, and atrial fibrillation do not, by themselves, constitute clinical ASCVD. Patients with these conditions who have no established ASCVD and should not receive lipid-lowering therapy for secondary prevention.

        Before clinicians can establish an individualized LDL-C target, they must first calculate the patient’s Predicting Risk of Cardiovascular Disease EVENTs (PREVENT) score.14 For patients aged 30 to 79 with an LDL-C of 70 to 189 mg/dL, the PREVENT score gauges patients’ 10- and 30-year ASCVD risk to determine optimal LDL-C targets and whether LLT is warranted. (The AHA provides an online calculator here: https://professional.heart.org/en/guidelines-and-statements/prevent-calculator.) The scoring system estimates an individual’s percentage risk of cardiovascular disease using age, systolic blood pressure, total cholesterol, HDL, estimated glomerular filtration rate, and body mass index (BMI).14 These factors guide LLT initiation. Clinicians can also input comorbidities such as diabetes, current smoking, or patients’ current use of lipid-lowering or antihypertensive medications. The scoring system breaks patients into four categories.3

        • Low-risk patients have a 10-year risk of less than 3%.
        • In borderline-risk patients who have a 3% to less than 5% risk, clinicians should discuss the risks versus benefits of initiating LLT with the patient.
        • For intermediate-risk patients (5% to less than 10%), LLT is indicated, with moderate-high intensity statins preferred.
        • High-risk patients with a 10% or greater PREVENT score should start a high-intensity statin or optimize LLT with other medications.

        In patients who have not experienced an ASCVD event, primary prevention strategies focus on reducing cardiovascular risk using less intensive interventions with higher LDL treatment thresholds. Primary prevention targets also depend on patient-specific risk factors. Risk factors include

        • Age 65 years or older
        • Chronic kidney disease
        • Current smoker
        • Diabetes
        • Heart failure
        • Heterozygous familial hypercholesterolemia
        • Hypertension
        • LDL value above 100 mg/dL despite optimized LLT

        For patients who do not have these risk factors, an LDL goal of below 100 mg/dL is adequate to reduce their risk of ASCVD. For patients at high risk for ASCVD (PREVENT score 10% or higher), clinicians should target an LDL goal of below 70 mg/dL.3 Prior guidelines favored less stringent goals for primary prevention, but lower LDL levels have been consistently linked to decreased ASCVD risk.


        Personalizing Secondary Prevention of ASCVD

        In patients with established ASCVD, the new ACC/AHA guidelines recommend aggressive lipid management—these patients are at the highest risk of additional ASCVD events. Secondary prevention targets also depend on defining patients as very high risk for another ASCVD event or not. Very high risk is defined as

        • 2 or more previous major ASCVD events, or
        • 1 major ASCVD event and 2 or more high-risk conditions (defined in primary prevention)

        The target for those at very high risk is an LDL of less than 55 mg/dL.3 The guidelines also indicate that an LDL goal of less than 70 mg/dL is acceptable for patients without high-risk factors for another ASCVD event. However, most patients require lower LDL targets. Evidence suggests that there is no clear lower LDL threshold at which LDL reduction harms patients. The Improved Reduction of Outcomes: Vytorin Efficacy International Trial (IMPROVE-IT) and Further Cardiovascular Outcomes Research with PCSK9 Inhibition in Subjects with Elevated Risk (FOURIER) trials demonstrated that patients with LDL-C values below 30 mg/dL experienced the lowest rates of cardiovascular events without an increase in adverse safety outcomes.15,16 So, clinicians can intensify LLT to achieve very low LDL levels without increasing safety concerns.

        For all patients, a TG level of below 150 mg/dL is optimal, but slight elevations contribute less to ASCVD risk than LDL-C elevations do. Figure 1 depicts primary and secondary prevention cholesterol goals.

        Figure 1. Cholesterol Targets for Primary and Secondary Prevention of ASCVD

        Lipoprotein goals for ASCD risk reduction table

        George begins by confirming that Nick has no established ASCVD. Although diabetes, hypertension, HFrEF, and smoking increase his cardiovascular risk, none converts his treatment to secondary prevention. So, Nick is receiving LLT for primary prevention. A PREVENT score of 10.2% puts him in the high-risk category, for which the LDL goal is below 70 mg/dL.


        SIDEBAR: When to Reclassify with Coronary Artery Calcium (CAC) Scoring?17,18

        Coronary Artery Calcium (CAC) refers to calcium deposits within the heart’s arterial walls. This noninvasive imaging test performed with a noncontrast cardiac scan is specific to atherosclerotic plaques, meaning it is a precise way to detect early cardiovascular disease. CAC at any level indicates subclinical coronary atherosclerosis, but it does not transform the patient into someone with clinical ASCVD or automatically place everyone into the same treatment category. CAC is principally a selective risk-reclassification tool when the treatment decision remains uncertain.

        Coronary artery calcium (CAC) is specific to atherosclerotic plaques and strongly predicts ASCVD risk. It can help refine risk estimates. In adults without established ASCVD who have a borderline or intermediate 10-year PREVENT-ASCVD risk (3% to less than 10%), CAC measurement may be considered when uncertainty remains about whether to initiate lipid-lowering therapy. CAC also guides treatment in asymptomatic men aged 40 years and older and women aged 45 years and older previously not receiving LLT. In patients with CAC scores greater than 0 Agatston Units (AU; a score that reflects both the area and density of calcified plaque in the coronary arteries) who are at borderline risk, clinicians should initiate LLT.

        Interestingly, elite endurance athletes can have increased CAC scores without significant risk for atherosclerosis.19,20 However, increased plaque calcification may serve a cardioprotective role, as calcified plaques are more stable and less likely to rupture and cause thrombosis than lipid-rich, vulnerable plaques. Further research is needed to clarify this association. Athletes with elevated CAC scores should not stop exercising, as exercise is cardioprotective.20

        The prescriber asks if a CAC scan would reclassify Nick’s ASCVD risk. George explains that a scan is unlikely to change how Nick is treated. Nick’s PREVENT score, age, and concurrent conditions are clear indications for LLT. A CAC scan is useful if providers are uncertain about initiating LLT, not if patients are already indicated.


        Special Population Lipid Targets

        Many patients’ concurrent conditions influence recommended lipid goals. For example, primary ASCVD prevention for adults with diabetes has an LDL goal of below 100, or below 70 in the presence of high-risk factors or a PREVENT score of 5% or higher.21 Diabetes significantly increases the risk of ASCVD, warranting early guideline-directed risk assessment and lipid-lowering interventions by clinicians.22 Chronic kidney disease, heart failure, and HIV also warrant early LDL lowering, targeting levels under 100 mg/dL if patients have no additional risk factors and under 70 mg/dL in higher-risk patients.3

        Patients older than 75 may require individualized lipid management rather than strict adherence to LDL targets. LLT still reduces the risk of major cardiovascular events, but data are limited on lower lipid levels for patients in this age group.23 While LLT is safe and effective in this population, evidence supporting very low LDL targets is more limited. Poor functional status, frailty, and polypharmacy put these patients at an increased risk for adverse effects and potential injury. Clinician-based decision-making is essential to weigh the cardiovascular benefits of stringent lipid targets against the potential negative impact on patients’ quality of life.24 In patients with limited life expectancy, the risk of a major cardiovascular event is low. So, if patients experience negative effects from aggressive lipid management, clinicians should consider less intensive management.

        In pregnant patients, cholesterol targets increase with each trimester of gestation. Maternal lipid levels progressively increase as the fetus grows, with triglycerides demonstrating the largest increase. Consequently, standard lipid goals are not applicable to this population, so the need for LLT is clinician-guided and only warranted in very high-risk individuals.25

        Current evidence has not established a lower LDL threshold at which treatment becomes harmful. Patients at very high ASCVD risk may benefit from LDL levels below 30 mg/dL, provided therapy is clinically indicated, tolerated, and monitored. All clinicians need to remember that “lower is better” does not mean “lower everyone’s cholesterol levels indiscriminately.”

        PAUSE AND PONDER: Which lipid-lowering medications bypass hepatic metabolism and may offer advantages in select patients with hepatic or renal dysfunction?


        Lifestyle Interventions

        Multimodal lifestyle modifications are the backbone of any lipid-lowering regimen, and prescribers should initiate them in all patients who meet the criteria for intervention.3 Dietary modifications emphasize consumption of fruits, vegetables, legumes, whole grains, fiber, and foods with low saturated fats and high mono- and poly-unsaturated fats. To examine the optimal diet to lower LDL, researchers compared the Mediterranean diet to a vegan diet.26 At 16 weeks, patients on a vegan diet decreased their LDL by an average of 15 mg/dL, while the Mediterranean diet failed to show a statistically significant decrease. These data are limited by small sample size—only 62 participants—so more data is needed.26 However, many patients prefer diets that include meat and meat products, rendering vegan diets unsustainable. Any nutritional intervention that lowers LDL and weight is beneficial, provided patients adhere to the diet indefinitely. When coupled with other lifestyle modifications, dietary modifications can lower LDL and reduce the risk of developing ASCVD. Triglyceride-lowering diets decrease added sugars, refined carbohydrates, saturated fats, and alcohol—these modifications can lower TG levels by over 70%.27

        Weight loss significantly decreases LDL and TG levels as well. A meta-analysis of 73 randomized controlled trials with more than 32,000 participants discovered that for every kilogram (2.2 pounds) of weight lost, LDL decreases by up to 1.3 mg/dL and TG levels decrease by 4 mg/dL.28 The AHA recommends 150 minutes or more of moderate- to high-intensity aerobic exercise with resistance training to reduce the likelihood of cardiovascular events.3 A meta-analysis conducted by the AHA demonstrated that weekly moderate-intensity exercise decreased the risk of cardiovascular mortality by 23%.29 The analysis followed 3.4 million patients over 12 years, and found that 150 minutes of moderate-intensity aerobic exercise per week yielded a mortality benefit and a 17% decrease in new cardiovascular disease. Combining interventions can drastically lower LDL levels and, rarely, eliminate the need to initiate LLT altogether.29


        Lipid-Lowering Medications—Statins

        Medications augment lifestyle modifications when lifestyle modifications fail to decrease cholesterol below accepted thresholds. Statins are the backbone of LLT due to their robust ability to decrease LDL.6 Low-, moderate-, and high-intensity statins decrease patients’ LDL values by 30%, 30-49%, and 50% or more, respectively. Figure 2 depicts statin intensity categories, available drugs, and equipotent statin doses.30


        Figure 2. Statin Intensity Classifications and Equipotent Daily Doses

        Available Statins in the US and their Intensity Categories table

        Statins reduce LDL by competitively inhibiting the 3-hydroxy-3-methylglutaryl coenzyme A (HMG-CoA) reductase enzyme, the rate-limiting enzyme in hepatic cholesterol synthesis.31 Statin-induced enzyme inhibition decreases hepatic cholesterol synthesis, meaning less LDL circulates throughout the body. After the initial LDL reduction achieved with the starting dose, each subsequent statin dose doubling lowers LDL by an additional 6% to 8%.32 Statins also decrease inflammation through antioxidant properties and stimulate the immune system. The liver primarily metabolizes statins. The liver cytochrome P450 (CYP) 3A4 enzyme metabolizes atorvastatin, simvastatin, and lovastatin, whereas CYP2C9 metabolizes fluvastatin and rosuvastatin to a lesser extent. Statins are eliminated through both hepatic and renal pathways, although the extent of renal excretion varies by agent. Therefore, statin dose adjustments may be necessary in patients with liver or kidney impairment. Statins are contraindicated in patients with active liver disease. Simvastatin is strictly contraindicated with CYP3A4 strong inhibitors, and has a maximum daily dose of 10 mg with diltiazem, verapamil, and dronedarone.33 The maximum simvastatin daily dose for patients taking amiodarone, amlodipine, and ranolazine is 20 mg. Technician recognition of new drug interactions is crucial to prevent adverse effects and decreased efficacy. Pharmacy technicians can identify new statin drug interactions by reviewing medication profiles, recognizing interaction alerts, and promptly notifying pharmacists of suspected interactions to prevent adverse effects. Clinicians should dose adjust statins in patients taking CYP enzyme inducers or inhibitors.

        Common Strong CYP3A4 inhibitors include:

        • Ritonavir
        • Itraconazole
        • Ketoconazole
        • Cobicistat
        • Grapefruit Juice

        Common Strong CYP3A4 and CYP2C9 inducers include:

        • Rifampin
        • Carbamazepine
        • Phenytoin
        • Phenobarbital

        Common Strong CYP2C9 inhibitors include:

        • Sulfamethoxazole/Trimethoprim
        • Amiodarone
        • Fluconazole


        Statin-associated muscle symptoms (SAMS) are the most commonly reported adverse effects associated with statin therapy.31 SAMS manifests as muscle aches, pain, and soreness primarily in the larger muscle groups of the body—the thighs, hips, and shoulders. High statin doses, advanced age, decreased thyroid function, diabetes, fibromyalgia, and CKD contribute to a patient’s risk of developing SAMS. The incidence of SAMS increases greatly with concurrent fibrates, which are medications that reduce high TGs. Gemfibrozil is contraindicated with some statins (e.g., simvastatin) and should generally be avoided because it increases the risk of SAMS. 34

        As noted above, strong evidence suggests that most muscle symptoms are not attributable to statins.35 Authors of a meta-analysis of 19 trials and 35,000 patients concluded that up to 90% of muscle symptoms attributed to statin therapy were not due to the medication.31 Instead, underlying conditions and advanced age played a large role in the misinterpretation. To classify a patient as statin intolerant, clinicians should rechallenge with at least two statins at the lowest approved dose.35 Additionally, switching from statins that are highly lipid-soluble like atorvastatin and simvastatin to a highly water-soluble statin like rosuvastatin could decrease muscle symptoms, but data are inconsistent.36 When initiating statins, clinicians should inform patients that the risk of statin-associated adverse effects is small and the cardiovascular benefits far outweigh the negative aspects of the medication. If patients experience severe muscle symptoms, creatine kinase measurements should be taken to rule out rare, life-threatening muscle breakdown like rhabdomyolysis.31

        Other rare adverse effects include mild nausea, diarrhea, or constipation, and small increases in blood sugar.31 Advising patients to take the medication with food and in the evening alleviates stomach discomfort. For statins with shorter half-lives (simvastatin and lovastatin), evening administration is traditionally recommended because hepatic cholesterol synthesis is greatest overnight. However, statins with longer half-lives, such as atorvastatin, and rosuvastatin maintain therapeutic activity throughout the day and may be taken at any time. Figure 3 summarizes statin administration instructions and counseling.

        The prescriber discusses doubling Nick’s rosuvastatin dose to 10 mg. George points out that rosuvastatin 5 mg and 10 mg are both moderate-intensity doses, and because Nick’s LDL remains above his goal, his dose should be increased to a high-intensity dose. George recommends increasing to rosuvastatin 20 mg, granted Nick agrees with the plan and has no contraindications. George also recommends obtaining a repeat lipid panel in 4 to 12 weeks to monitor adherence and response.


        Nonstatin Lipid-Lowering Medications

        A staple of oral nonstatin therapy, ezetimibe (Zetia) does not decrease cholesterol synthesis—instead, it inhibits intestinal absorption of dietary cholesterol by blocking the Niemann-Pick C1-Like-1 (NPC1L1) transporter. 37 Ezetimibe decreases LDL levels by 13% to 20%, making it a useful adjunct to statin therapy, or as monotherapy for less intensive lipid lowering.37 Prescribers should not use ezetimibe in people who have moderate and severe hepatic impairment, but the medication is generally well tolerated. Limited adverse effects include headache, congestion, and sore throat—a rarity for the majority of patients.

        For patients who require drastic reductions in LDL with or without statin therapy, subcutaneous proprotein convertase subtilisin/kexin type 9 (PCSK9) inhibitor injections decrease LDL-C by 45-65%.3 The medication blocks PCSK9 enzymatic activity, raising levels of LDL-receptors in the body, allowing the liver to remove more LDL from the bloodstream. When the ACC/AHA published cholesterol guidelines in 2018, clinicians lacked sufficient evidence to determine the long-term effects of the monoclonal antibody PCSK9 inhibitors evolocumab (Repatha) and alirocumab (Praluent).6 Today, more recent studies demonstrate that evolocumab and alirocumab significantly reduce heart attack, stroke, and cardiovascular death over a five-year period.38,39 Injected into the abdomen, thigh, or upper buttock once every few weeks, these medications offer less frequent dosing than any other lipid-lowering medication. Patients rarely experience significant adverse effects; injection-site reactions and hypersensitivity reactions occur most frequently.40

        Additionally, the 2018 AHA/ACC cholesterol guidelines did not include inclisiran (Leqvio), a novel small-interfering RNA PCSK9 inhibitor that blocks production of the PCSK9 protein in the liver.6 The Lancet Diabetes & Endocrinology published data demonstrating the twice-yearly injection provided sustained LDL reductions and medication tolerability in patients over a four-year period.41 The updated 2026 AHA/ACC guidelines recommend inclisiran as an alternative to monoclonal antibody PCSK9 inhibitors, but high cost and absence of completed cardiovascular outcome evidence are barriers for initiation. 3 Another difference between inclisiran and the monoclonal antibody PCSK9 inhibitors evolocumab and alirocumab is that a healthcare professional must administer inclisiran. For patients who want less frequent administration or prefer not to inject their medication themselves, inclisiran is a useful alternative.

        PCSK9 inhibitors excel in older adults. Researchers at the Erasmus MC Cardiovascular Institute concluded that patients older than 70 taking evolocumab and alirocumab had medication safety and efficacy profiles similar to those under 70.42

        In July 2026, the FDA approved the first oral PCSK9 inhibitor, enlicitide (Lipfendra), but the guidelines do not address the medication because it received approval after they were published.43 Decreasing LDL by 56% over 24 weeks, the medication has similar efficacy to injectable PCSK9 inhibitors, but is roughly half the out-of-pocket cost of injectables at $315 per month.44 PCSK9-targeting therapies have demonstrated efficacy in lowering LDL-C regardless of formulation, including injectable monoclonal antibodies, injectable small interfering RNA (siRNA), and oral agents.

        Clinicians can confidently prescribe PCSK9 inhibitors or ezetimibe as an adjunct or alternative to traditional statin therapy due to their robust reductions in LDL and low adverse effect profile.

        The 2026 AHA/ACC guidelines added bempedoic acid (Nexletol), an adenosine triphosphate citrate lyase (ACL) inhibitor, as an alternative for statin-intolerant patients, or an alternative medication.45 Bempedoic acid acts two enzymatic steps upstream from statins and reduces LDL by around 20%.46 However, bempedoic acid is metabolized via glucuronidation and not a CYP enzyme, but data regarding dose adjustments is limited. Adverse effects include cold or flu-like symptoms, muscle spasms, back and stomach pain. In CLEAR Outcomes, which enrolled 13,970 statin-intolerant patients, bempedoic acid reduced the relative risk of major adverse cardiovascular events by 13% over a median follow-up of 40.6 months. The trial included patients at high risk for ASCVD or with established ASCVD who reported being unable or unwilling to receive statins due to adverse effects. After treatment with bempedoic acid, LDL values dropped from an average of 139 mg/dL to 107 mg/dL, a 30 mg/dL decrease compared to placebo.45 Bempedoic acid is also available with ezetimibe as a once-daily fixed-dose combination tablet (Nexlizet; bempedoic acid 180 mg/ezetimibe 10 mg).47

        Finally, bile acid sequestrants—colesevelam, colestipol, and cholestyramine—are members of a lipid-lowering medication class that decreases LDL without being systemically absorbed, making them a viable option for pregnant patients.3 At full doses, they lower LDL by 15% to 30%.48 Gastrointestinal adverse effects like nausea, vomiting, constipation, and bloating prevent some patients from reaching higher doses. Bile acid sequestrants should generally be avoided with TG levels above 300 mg/dL, but contraindications vary by agent. Dosage formulations may also contribute to intolerance. All three available agents come as oral powders for suspension which some patients describe as having a chalky texture or bitter aftertaste. However, colesevelam and colestipol have tablet formulations. Patients with partial biliary obstruction and those who are pregnant or planning to become pregnant may benefit from this medication class. However, more effective therapies are preferred for most other patients.

        Administration instructions, storage, and patient counseling points can be found in Figure 3.


        Figure 3. Lipid-Lowering Therapy Quick Guide3

        Lipid-Lowering Therapies: Quick Storage and Administration Guide table


        Triglyceride Lowering Medications

        Statins remain the foundation for TG-lowering therapy.3 While fibrates, niacin, and prescription-strength omega-3 fatty acids have been shown to reduce TG levels, they fail to reduce the risk of cardiovascular events and ASCVD.49 The Reduction of Cardiovascular Events With Icosapent Ethyl–Intervention Trial (REDUCE-IT) trial demonstrates that icosapent ethyl (Vascepa) is beneficial in certain patient populations with high TG but normal LDL.50  In patients with TG levels surpassing 1,000 mg/dL, the apolipoprotein C-III (apoC-III) inhibitor reduces TG levels and the risk for pancreatitis by 63%.51

        Eight weeks later, Nick reports no adverse effects from rosuvastatin 20 mg daily. His repeat LDL has decreased to 78 mg/dL—closer to his goal but still above 70 mg/dL. The prescriber calls George again to ask what the next steps should be. George tells the prescriber that because Nick only needs modest additional LDL lowering, ezetimibe 10 mg is warranted. Ezetimibe is a once-daily pill that can be taken at the same time as Nick’s statin, is generally well-tolerated, and can lower LDL-C by an additional 13% to 20%.


        PAUSE and PONDER: If a patient who has an LDL of 53 mg/dL on a moderate-intensity statin has had a heart attack, is a high-intensity statin warranted?


        Lipid-Lowering Therapy Treatment Algorithm

        With defined lipid targets, initiating or optimizing LLT is crucial to reduce patients’ risk for ASCVD.

        For patients without established ASCVD and an LDL of 70 to 189, the 2026 AHA/ACC guidelines recommend using the PREVENT scoring system to estimate ASCVD risk.3 The guidelines recommend initiating a statin in patients with an intermediate risk (5%) or above, while those with borderline risk (3% to less than 5%) should engage in shared decision-making with their clinician regarding treatment initiation. The guidelines support moderate-intensity statin initiation in intermediate risk patients, with high-intensity statins indicated in higher risk patients. Unlike previous guidelines, which emphasized percent LDL reduction from baseline, the 2026 recommendations incorporate individualized LDL targets.6 If maximally tolerated statin therapy fails to reduce a patient’s LDL target, additional therapy—ezetimibe or a PCSK9 inhibitor—is necessary to reduce all-cause mortality and CV events.52,53,54 Bempedoic acid is a possible alternative, but ezetimibe and PCSK9 inhibitors alongside statins provide greater LDL reductions and are better tolerated.3

        The 2026 AHA/ACC cholesterol guidelines recommend initiation or titration to a high-intensity statin for all patients with established ASCVD, regardless of comorbidities, risk factors, or baseline LDL.3 As previously discussed, if patients remain above the LDL goal of 55 mg/dL, clinicians should add ezetimibe, a PCSK9 inhibitor, or bempedoic acid.3

        Age and PREVENT score guide statin therapy for patients with diabetes who do not have established ASCVD.3 The 2026 AHA/ACC guidelines recommend initiating at least a moderate-intensity statin, regardless of PREVENT score or LDL. For patients aged 30 to 39 years with PREVENT scores greater than 3%, clinicians should discuss cardiovascular risk reduction before considering moderate-intensity statin therapy. Beyond 75 years old, clinicians should engage in benefit-risk discussions with patients regarding statin therapy.3

        Several lipid-lowering medications should be avoided in pregnant patients or patients who wish to become pregnant. Technician and pharmacist recognition of potentially harmful medications to the fetus, known as teratogens, is vital to prevent birth defects, premature births, and fetal harm. Because lipid management goals change with each trimester, lifestyle management is the safest option and can effectively manage high LDL and TG levels throughout pregnancy.3 Women should stop statins one to two months before attempting to become pregnant or as soon as pregnancy is discovered. Some studies suggest statins decrease birth weights, and increase the risk of preterm birth, eclampsia, and preeclampsia.55,56 Newer data suggests that statin exposure during pregnancy is not associated with major fetal defects, and that spontaneous abortion rates could reflect other confounding factors like maternal comorbidities.56

        More data is needed to make definitive conclusions, but in 2021 the FDA revised statin warnings, indicating high-risk pregnant patients with established ASCVD could continue statin therapy when appropriate.57 Statins should still be avoided when breastfeeding. Clinicians should continue statin therapy only after conducting an individualized risk assessment and engaging in shared decision-making with the patient. Limited evidence for alternative lipid-lowering therapies leaves bile acid sequestrants (BAS) as the only evidence-based medication class for cholesterol reduction during pregnancy because they are not systemically absorbed.3 Unfortunately, BAS can impair fat-soluble vitamins (vitamin A, D, E, K) and folic acid, which can impact the fetus, maternal health, and milk production.58 To address TG levels above 500 mg/dL, fibrates and prescription-strength omega-three ethyl esters (DHA and EPA) can be initiated after the first trimester.59

        Dialysis status determines the optimal lipid-lowering therapy for patients with chronic kidney disease (CKD).3 Guidelines support primary prevention with a moderate-intensity statin with or without ezetimibe for patients 40 to 75 years old with an LDL of 70 to 189 mg/dL for patients not on dialysis. In contrast, statins have not demonstrated cardiovascular outcome benefits in patients receiving dialysis.60  

        Finally, patients with human immunodeficiency virus (HIV) are at heightened risk for ASCVD, particularly heart attack.61 Moderate-intensity statins reduce ASCVD risk in this population. However, many antiretroviral medications strongly inhibit CYP3A4, requiring clinicians to monitor for drug interactions and statin-related adverse effects.

        The 2026 AHA/ACC triglyceride recommendations remain mostly unchanged from the 2018 guidelines.3,6 LDL management through LLT decreases TG levels concurrently. In most cases, adequate LDL control and lifestyle management maintain healthy TG levels below 150 mg/dL. One major difference is the inclusion of icosapent ethyl (Vascepa) in the 2026 guidelines. The REDUCE-IT trial observed the effect icosapent ethyl had on patients with established ASCVD or diabetes with risk factors for ASCVD. Patients’ TG levels were between 135 and 499 mg/dL and LDL-C values between 41 and 100 mg/dL.50 When added to prior statin therapy, twice-daily icosapent ethyl reduced the relative risk of major cardiovascular events by over 20%. The medication also decreased TG levels by 40 mg/dL. So, clinicians can add icosapent ethyl in patients with diabetes and ASCVD risk factors or with established ASCVD already on statin therapy with high triglycerides. In patients with TG levels exceeding 500 mg/dL or familial chylomicronemia syndrome, olezarsen is indicated to reduce the risk of pancreatitis.62 Other TG-lowering therapies remain last line and are not recommended in the 2026 guidelines.3


        Whether preventing or managing ASCVD, clinicians must individualize lipid goals and consider special populations to reduce cardiovascular events and mortality.3


        SIDEBAR: Do patients with heart failure require lipid-lowering therapy? 3,63,64,65

        Heart failure alone is not an indication to initiate statin therapy. Irrespective of ejection fraction, the 2026 AHA/ACC guidelines quantify heart failure as a high-risk cardiovascular condition. Several conditions add to the progression of heart failure, with coronary artery disease being a major contributor. Coronary atherosclerosis restricts blood flow to the heart, increasing the risk of myocardial infarction. The resulting loss of viable cardiac cells triggers compensatory overactivation of the remaining healthy tissue, progressively impairing cardiac function and contributing to the development of heart failure. Lipid-lowering therapy may reduce heart failure-related hospitalizations in some patients with heart failure. However, without another indication for LLT, statins do not reduce sudden cardiac death and major cardiovascular events.


        Ten weeks after adding ezetimibe, Nick’s LDL is 65 mg/dL. He reports remaining adherent to his medications and has no new adverse effects. George recommends continuing the regimen and reinforces smoking cessation and lifestyle modifications. The prescriber thanks George for the assessment, as Nick has reached his LDL goals without unnecessary testing or premature initiation of costly injectable medications.


        Optimizing Access to New Lipid-Lowering Therapy

        The cost of new lipid-lowering medications can prevent patients from receiving guideline-directed treatment. Out-of-pocket costs for bempedoic acid and PCSK9 inhibitors can exceed $700 and $500 per month, respectively.66,67,68 Inclisiran presents additional coverage challenges because healthcare professionals must administer it in a clinical setting. Patients in low socioeconomic groups can struggle to achieve recommended lipid goals due to cost. Even insured patients frequently encounter stringent prior authorization requirements.69 Insurers frequently require medical records, specialist evaluation, and step-therapy requirements with statins before approving PCSK9 inhibitors or bempedoic acid.

        Pharmacists and pharmacy technicians can increase medication access by helping patients reduce financial barriers. Many manufacturers offer copay cards that reduce out-of-pocket costs for privately insured patients.70 Some manufacturers also provide patient assistance programs that offer free or reduced-price medications.71,72 These programs often require income documentation and provider approval. Evolocumab’s manufacturer, Amgen, even offers patients a one-time, one-month free trial of evolocumab.73 Coverage for these medications can reduce monthly costs to as little as $50 per month.

        Additionally, Medicare Part D has an annual out-of-pocket spending cap of $2,100, meaning covered lipid-lowering therapies cost patients little or nothing after the cap is reached.74 Pharmacists and technicians should familiarize themselves with available assistance programs and insurance requirements to identify eligibility and serve patients better. These resources improve medication access, boost adherence, and help patients achieve guideline-directed cholesterol goals to reduce ASCVD risk.


        CONCLUSION

        The update to the 2026 AHA/ACC Cholesterol Management Guidelines offers new guidance to clinicians on how to optimize lipid-lowering interventions to achieve individualized cholesterol targets. The guidelines equip pharmacists to calculate 10-year ASCVD risk, personalize patients’ estimated risk using the PREVENT-ASCVD equation, reclassify risk with CAC, and reassess treatment success. As newer lipid-lowering therapies are incorporated into standard practice, pharmacists should understand the updated treatment algorithm to improve medication selection and reduce ASCVD events. Pharmacy technicians can enhance patient care through recognition of potential drug interactions, identification of adverse effects, and improvement of medication access.


        Pharmacist Post Test (for viewing only)

         Rethinking Cholesterol: Putting the 2026 AHA/ACC Guidelines into Practice 

        26-046-H01-P

        Pharmacist Post-test


        After completing this continuing education activity, pharmacists will be able to

        1. Recall lipid management goals and ASCVD risk based on comorbidities and cardiovascular disease history.
        2. Match available lipid-lowering medications’ mechanisms of action, efficacy, safety, and place in therapy
        3. Identify optimal lipid-management plans that combine evidence-based recommendations, patient-specific factors, and medication adherence.
        4. Manage lipid-lowering medication regimens based on therapeutic lab monitoring and adverse effects when indicated


        1. Annie Wilson is a 66-year-old female with a past medical history of heart failure, chronic obstructive pulmonary disease (COPD), hypertension, and an ischemic stroke in 2023. Her medications include lisinopril 10 mg, amlodipine 5 mg, fluticasone/umeclidinium/vilanterol (Trelegy Ellipta), metoprolol succinate, and empagliflozin 10 mg. Based on her past medical history, does Annie have established ASCVD? If so, what condition?

        a. Yes, heart failure

        b. Yes, ischemic stroke

        c. This patient does not have established ASCVD


        *


        2. Based on Annie Wilson’s medical history, which type of cholesterol prevention does this patient require?

        a. Primary Prevention

        b. Secondary Prevention

        c. Tertiary Prevention


        *


        3. Annie Wilson’s lipid panel comes back, and her LDL-C is 115 mg/dL. What is her LDL-C goal given her past medical history?

        a. LDL-C <100 mg/dL

        b. LDL-C <70 mg/dL

        c. LDL-C <55 mg/dL


        *


        4. What lipid-lowering class is the cornerstone of lipid-lowering therapy?

        a. HMG-CoA reductase inhibitors

        b. Cholesterol absorption inhibitor

        c. ATP citrate lyase (ACL) inhibitor


        *


        5. What medication(s) inhibits intestinal absorption of dietary cholesterol?

        a. PCSK9 inhibitors

        b. Statins

        c. Ezetimibe


        *


        6. Patient Ethan Davis is a 47-year-old who has a past medical history of hypertension and smoking with a 10-year pack history. He takes lisinopril 10 mg daily. At his yearly physical, his lipid panel reveals his LDL-C is 103 mg/dL. The clinician calculates his PREVENT ASCVD risk score, and it is 4.3%. What risk category does this PREVENT score fall into?

        a. High Risk

        b. Intermediate Risk

        c. Borderline Risk


        *


        7. The clinician is unsure if Ethan Davis should initiate LLT given his borderline risk PREVENT score. What additional test can be conducted to determine if Ethan Davis is indicated for LLT?

        a. Lipoprotein(a)

        b. Coronary artery calcium

        c. ApoB

        *


        8. Ethan Davis’ clinician calls you into the pharmacy to inform you that Ethan’s coronary artery calcium score is 46 Agatston Units (AU). After discussing this with Ethan first, the clinician decides to initiate a statin. What intensity statin is indicated in this patient?

        a. Low-intensity statin

        b. Moderate-intensity statin

        c. High-intensity statin


        *


        9. Judy Thompson is a 55-year-old female with a past medical history of hypertension, hyperlipidemia, a heart attack in 2020, and seasonal allergies. She currently takes lisinopril 20 mg, loratadine 20 mg, and rosuvastatin 40 mg daily. Her lipid panel comes back, and you notice that her LDL-C is 101 mg/dL. The patient states she has been adherent and on rosuvastatin 40 mg for 5 years. Her prescriber asks you to recommend an additional lipid-lowering therapy that could lower the patient’s LDL-C to the goal of below 55 mg/dL. What is your recommendation?

        a. Bempedoic acid

        b. Ezetimibe

        c. A PCSK9 inhibitor


        *


        10. Nick Brown is a 39-year-old male with a past medical history of hypertension, hyperlipidemia, and major depressive disorder. He currently takes atorvastatin 10 mg, losartan 25 mg, and sertraline 100 mg. His newest lipid panel reveals his LDL-C is 98 mg/dL, and his triglyceride level is 335 mg/dL. His clinician calls you to ask how Nick’s triglycerides should be managed? How do you respond?

        a. Increasing his atorvastatin to 20mg

        b. Adding gemfibrozil 600 mg once daily

        c. The patient does not need additional triglyceride lowering therapy

        Pharmacy Technician Post Test (for viewing only)

        Rethinking Cholesterol: Putting the 2026 AHA/ACC Guidelines into Practice 

        26-046-H01-T

        Pharmacy Technician Post-test


        After completing this continuing education activity, pharmacists will be able to

        1. Review common lipid-lowering medications and their indications
        2. Detect patient concerns or questions that warrant pharmacist intervention
        3. Describe proper storage, processing, dispensing, and counseling for lipid lowering therapies
        4. Optimize coverage plans to decrease barriers to medication access


        1. Which lipid-lowering medication is a common initial medication for patients with newly diagnosed high cholesterol?

        a. Ezetimibe

        b. A statins

        c. Bempedoic Acid


        *


        2. A patient approaches the pharmacy counter and asks why his doctor prescribed ezetimibe if he already takes rosuvastatin. What do you tell the patient?

        a. The medication is not for cholesterol lowering, it is for triglyceride management

        b. The statin is not working and he should ask the prescriber to take him off it

        c. Adding ezetimibe to statin therapy minimizes the risk of cardiovascular disease


        *


        3. What class of drug includes alirocumab?

        a. PCSK9 inhibitor

        b. Statin

        c. Bile acid sequestrant


        *


        4. Annie Edwards is a 29-year-old female who approaches the drop-off window to pick up a medication and get a flu vaccine. During the vaccine administration, the patient tells you how she recently found out she is pregnant and wants to make sure no live vaccines are given to her. When you meet her back at the register, you notice the medication she is picking up is atorvastatin. What should your next steps be?

        a. Dispense the medication so you don’t make a line of patients

        b. Dispense it and direct her to her provider if she has any concerns

        c. Hold the medication and talk with the pharmacist


        *


        5. Michael Hanes is a 54-year-old male who arrives to the pharmacy to pick up a new prescription for a ritonavir-containing antiretroviral regimen. While processing the prescription, you see he has been taking simvastatin for the last three years. What is the most appropriate next step?

        a. Advise the patient to take the medications at least four hours apart

        b. Hold the prescription and notify the pharmacist

        c. Dispense the antiviral regimen and tell him to call with any questions


        *


        6. You are asked how to store evolocumab, a PCSK9 inhibitor. How do you respond?

        a. Store evolocumab in the refrigerator

        b. Store evolocumab in the freezer

        c. Store evolocumab at room temperature


        *


        7. Jack Johnson is picking up a new prescription for alirocumab. He does not remember where he can inject the medication. What locations are acceptable to administer this medication?

        a. Any muscles in his arms, legs, or buttocks

        b. The largest vein in his forearm or back of the hands

        c. The fatty tissue of his abdomen, thigh or upper arm


        *


        8. Jack Johnson returns several months later and reports that, despite having commercial insurance, he is having difficulty affording his alirocumab prescription. Which resource can you recommend to help reduce his out-of-pocket costs?

        a. Using an alirocumab copay card

        b. Administering it every other day

        c. Paying cash for his medication


        *


        9. Sean O’Connor is picking up a prescription for rosuvastatin. As you give him his refill, he hands you a pillbox to ring up so he “can store it next to the shower” so he does not forget. What should your response be?

        a. That is a perfect spot!

        b. Buy a pill organizer with bigger letters so you can see it more easily

        c. This medication should not be stored near excess moisture


        *


        10. A Medicare Part D patient is concerned about the cost of her lipid-lowering medication. She has already spent $1,950 out-of-pocket for covered medications this year. Which statement is most accurate?

        a. Medicare Part D does not cover lipid-lowering medications

        b. Medicare Part D limits annual out-of-pocket costs, and you are about $150 from that spending cap

        c. Medicare Part D requires another insurance plan to pay for medications after the spending cap is reached


        References

        Full List of References

        1. National Heart, Lung, and Blood Institute. Atherosclerosis - What Is Atherosclerosis?; 2024. https://www.nhlbi.nih.gov/health/atherosclerosis (accessed 2026-07-23).
        2. CDC. Multiple Cause of Death Data on CDC WONDER; 2024. https://wonder.cdc.gov/mcd.html (accessed 2026-07-23).
        3. Blumenthal RS, Morris PB, Gaudino M, et al. 2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Dyslipidemia: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Circulation 2026. doi:10.1161/CIR.0000000000001423
        4. Wu F, Juonala M, Jacobs DR Jr, et al. Childhood Non-HDL Cholesterol and LDL Cholesterol and Adult Atherosclerotic Cardiovascular Events. Circulation. 2024;149(3):217-226. doi:10.1161/CIRCULATIONAHA.123.064296
        5. Navar-Boggan AM, Peterson ED, D'Agostino RB Sr, Neely B, Sniderman AD, Pencina MJ. Hyperlipidemia in early adulthood increases long-term risk of coronary heart disease. Circulation. 2015;131(5):451-458. doi:10.1161/CIRCULATIONAHA.114.012477
        6. Grundy SM, Stone NJ, Bailey AL, et al. 2018 AHA/ACC/AACVPR/AAPA/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Blood Cholesterol: A Report of the American College of Cardiology/American Heart Association Task Force on Clinical Practice Guidelines. Circulation. 2019;139(25):e1082-e1143. doi:10.1161/CIR.0000000000000625
        7. American Heart Association. Lipoprotein(a). Accessed July 24, 2026. https://www.heart.org/en/health-topics/cholesterol/genetic-conditions/lipoprotein-a
        8. Alebna PL, Mehta A. An Update on Lipoprotein(a): The Latest on Testing, Treatment, and Guideline Recommendations. J Am Coll Cardiol. Published September 19, 2023. Accessed July 24, 2026. https://www.acc.org/latest-in-cardiology/articles/2023/09/19/10/54/an-update-on-lipoprotein-a
        9. Johannesen CDL, Mortensen MB, Langsted A, Nordestgaard BG. Apolipoprotein B and Non-HDL Cholesterol Better Reflect Residual Risk Than LDL Cholesterol in Statin-Treated Patients. J Am Coll Cardiol. 2021;77(11):1439-1450. doi:10.1016/j.jacc.2021.01.027
        10. Sayed A, Peterson ED, Virani SS, Sniderman AD, Navar AM. Individual Variation in the Distribution of Apolipoprotein B Levels Across the Spectrum of LDL-C or Non-HDL-C Levels. JAMA Cardiol. 2024;9(8):741-747. doi:10.1001/jamacardio.2024.1310
        11. Wägner AM, Pérez A, Calvo F, Bonet R, Castellví A, Ordóñez J. Apolipoprotein(B) identifies dyslipidemic phenotypes associated with cardiovascular risk in normocholesterolemic type 2 diabetic patients. Diabetes Care. 1999;22(5):812-817. doi:10.2337/diacare.22.5.812.
        12. Centers for Disease Control and Prevention. Testing for Cholesterol; 2024. https://www.cdc.gov/cholesterol/testing/index.html (accessed 2026-07-23).
        13. Zhang, Y.; An, J.; Reynolds, K.; Safford, M. M.; Muntner, P.; Moran, A. E. Trends of Elevated Low-Density Lipoprotein Cholesterol, Awareness, and Screening Among Young Adults in the US, 2003-2020. JAMA Cardiology 2022, 7 (10), 1079. https://doi.org/10.1001/jamacardio.2022.2641.
        14. Khan SS, Matsushita K, Sang Y, et al. Development and Validation of the American Heart Association's PREVENT Equations. Circulation. 2024;149(6):430-449. doi:10.1161/CIRCULATIONAHA.123.067626
        15. Cannon CP, Blazing MA, Giugliano RP, et al. Ezetimibe added to statin therapy after acute coronary syndromes. N Engl J Med. 2015;372(25):2387-2397. doi:10.1056/NEJMoa1410489
        16. Sabatine MS, Giugliano RP, Keech AC, et al; FOURIER Steering Committee and Investigators. Evolocumab and clinical outcomes in patients with cardiovascular disease. N Engl J Med. 2017;376(18):1713-1722. doi:10.1056/NEJMoa1615664.
        17. Budoff MJ, Young R, Burke G, et al. Ten-year association of coronary artery calcium with atherosclerotic cardiovascular disease (ASCVD) events: the multi-ethnic study of atherosclerosis (MESA). Eur Heart J. 2018;39(25):2401-2408. doi:10.1093/eurheartj/ehy217
        18. American Heart Association. PREVENT Equations Quickstart Guide. Published 2024. Accessed July 23, 2026. https://professional.heart.org/en/-/media/PHD-Files/Guidelines-and-Statements/PREVENT/PREVENT-Equations-Quickstart-Guide.pdf.
        19. Boutsikos I, Gkraikou T, Saad R, et al. Coronary Atherosclerosis in Master Athletes: Current Knowledge and Future Challenges. J Pers Med. 2026;16(3):172. Published 2026 Mar 23. doi:10.3390/jpm16030172
        20. Krishnan S, La Gerche A. CV Sports Chat: Coronary Artery Calcium in the Masters' Athlete – Part 2. American College of Cardiology. Published December 18, 2023. Accessed July 27, 2026. https://www.acc.org/latest-in-cardiology/articles/2023/12/05/04/29/cv-sports-chat-cac-in-the-masters-athlete-part-2
        21. de Vries FM, Denig P, Pouwels KB, Postma MJ, Hak E. Primary prevention of major cardiovascular and cerebrovascular events with statins in diabetic patients: a meta-analysis. Drugs. 2012;72(18):2365-2373. doi:10.2165/11638240-000000000-00000
        22. American Heart Association. Cardiovascular Disease and Diabetes; 2024. https://www.heart.org/en/health-topics/diabetes/diabetes-complications-and-risks/cardiovascular-disease--diabetes (accessed 2026-07-23).
        23. Armitage J, Baigent C, Barnes E, et al. Efficacy and safety of statin therapy in older people: a meta-analysis of individual participant data from 28 randomized controlled trials. Lancet. 2019;393(10170):407-415. doi:10.1016/S0140-6736(18)31942-1
        24. Kutner JS, Blatchford PJ, Taylor DH Jr, et al. Safety and benefit of discontinuing statin therapy in the setting of advanced, life-limiting illness. JAMA Intern Med. 2015;175(5):691-700. doi:10.1001/jamainternmed.2015.0289
        25. National Lipid Association. Specialty Corner: Lipid Management in Pregnancy and Lactation | National Lipid Association Online; 2024. https://www.lipid.org/lipid-spin/spring-2024/specialty-corner-lipid-management-pregnancy-and-lactation (accessed 2026-07-23).
        26. Barnard ND, Alwarith J, Rembert E, et al. A Mediterranean Diet and Low-Fat Vegan Diet to Improve Body Weight and Cardiometabolic Risk Factors: A Randomized, Cross-over Trial. J Am Nutr Assoc. 2022;41(2):127-139. doi:10.1080/07315724.2020.1869625
        27. Virani SS, Morris PB, Agarwala A, et al. 2021 ACC expert consensus decision pathway on the management of ASCVD risk reduction in patients with persistent hypertriglyceridemia. J Am Coll Cardiol. 2021;78(9):960-993. doi:10.1016/j.jacc.2021.06.011
        28. Hasan B, Nayfeh T, Alzuabi M, et al. Weight Loss and Serum Lipids in Overweight and Obese Adults: A Systematic Review and Meta-Analysis. J Clin Endocrinol Metab. 2020;105(12):dgaa673. doi:10.1210/clinem/dgaa673
        29. Wahid A, Manek N, Nichols M, et al. Quantifying the Association Between Physical Activity and Cardiovascular Disease and Diabetes: A Systematic Review and Meta-Analysis. J Am Heart Assoc. 2016;5(9):e002495. Published 2016 Sep 14. doi:10.1161/JAHA.115.002495
        30. Sizar, O.; Khare, S.; Jamil, R. T.; Talati, R. Statin Medications; StatPearls Publishing: Treasure Island (FL), 2024. https://www.ncbi.nlm.nih.gov/books/NBK430940/ (accessed 2026-07-23).
        31. Collins R, Reith C, Emberson J, et al. Interpretation of the evidence for the efficacy and safety of statin therapy. Lancet. 2016;388(10059):2532-2561. doi:10.1016/S0140-6736(16)31357-5
        32. Zheng H. Lowest effective doses and intermittent dosing of statins. Am J Med. Published online February 9, 2026. doi:10.1016/j.amjmed.2026.02.004
        33. US Food and Drug Administration. Zocor (simvastatin) tablets: prescribing information. Revised December 2020. Accessed July 27, 2026. https://www.accessdata.fda.gov/drugsatfda_docs/label/2020/019766s101lbl.pdf
        34. Wiggins BS, Saseen JJ, Page RL 2nd, et al. Recommendations for Management of Clinically Significant Drug-Drug Interactions With Statins and Select Agents Used in Patients With Cardiovascular Disease: A Scientific Statement From the American Heart Association. Circulation. 2016;134(21):e468-e495. doi:10.1161/CIR.0000000000000456
        35. Cheeley MK, Saseen JJ, Agarwala A, et al. NLA scientific statement on statin intolerance: a new definition and key considerations for ASCVD risk reduction in the statin intolerant patient. J Clin Lipidol. 2022;16(4):361-375. doi:10.1016/j.jacl.2022.05.068
        36. Mueller AM, Liakoni E, Schneider C, et al. The Risk of Muscular Events Among New Users of Hydrophilic and Lipophilic Statins: an Observational Cohort Study. J Gen Intern Med. 2021;36(9):2639-2647. doi:10.1007/s11606-021-06651-6
        37. Sizar, O.; Talati, R. Ezetimibe; StatPearls Publishing: Treasure Island (FL), 2020. https://www.ncbi.nlm.nih.gov/books/NBK532879/ (accessed 2026-07-24).
        38. O'Donoghue ML, Giugliano RP, Wiviott SD, et al. Long-Term Evolocumab in Patients With Established Atherosclerotic Cardiovascular Disease. Circulation. 2022;146(15):1109-1119. doi:10.1161/CIRCULATIONAHA.122.061620
        39. Schwartz GG, Steg PG, Szarek M, et al. Alirocumab and cardiovascular outcomes after acute coronary syndrome. N Engl J Med. 2018;379(22):2097-2107. doi:10.1056/NEJMoa1801174
        40. Binod Pokhrel; Pellegrini, M. V.; Levine, S. N. PCSK9 Inhibitors; StatPearls Publishing, 2024. https://www.ncbi.nlm.nih.gov/books/NBK448100/#article-37376.s3 (accessed 2026-07-24).
        41. Ray KK, Troquay RPT, Visseren FLJ, et al. Long-term efficacy and safety of inclisiran in patients with high cardiovascular risk and elevated LDL cholesterol (ORION-3): results from the 4-year open-label extension of the ORION-1 trial. Lancet Diabetes Endocrinol. 2023;11(2):109-119. doi:10.1016/S2213-8587(22)00353-9
        42. Visseren FLJ, Mach F, Koskinas KC, et al. Lipid-lowering therapy in patients with atherosclerotic cardiovascular disease: an international expert consensus statement. Atherosclerosis. Published online 2025. doi:10.1016/j.atherosclerosis.2025.119206
        43. Office of the Commissioner. FDA Approves First Oral PCSK9 Inhibitor to Lower LDL Cholesterol in Adults with High Cholesterol. U.S. Food and Drug Administration. https://www.fda.gov/news-events/press-announcements/fda-approves-first-oral-pcsk9-inhibitor-lower-ldl-cholesterol-adults-high-cholesterol (accessed 2026-07-24).
        44. Empirical Health. How Much Does Lipfendra Cost? Published July 24, 2026. Accessed July 27, 2026. https://www.empirical.health/blog/lipfendra-cost/
        45. Chandramahanti, S.; Farzam, K. Bempedoic Acid; StatPearls Publishing: Treasure Island (FL), 2023. https://www.ncbi.nlm.nih.gov/books/NBK594232/ (accessed 2026-07-24).
        46. Laufs U, Banach M, Mancini GBJ, et al. Efficacy and Safety of Bempedoic Acid in Patients With Hypercholesterolemia and Statin Intolerance. J Am Heart Assoc. 2019;8(7):e011662. doi:10.1161/JAHA.118.011662
        47. Nissen SE, Lincoff AM, Brennan D, et al. Bempedoic Acid and Cardiovascular Outcomes in Statin-Intolerant Patients. N Engl J Med. 2023;388(15):1353-1364. doi:10.1056/NEJMoa2215024
        48. Lent-Schochet, D.; Jialal, I. Antilipemic Agent Bile Acid Sequestrants; StatPearls Publishing: Treasure Island (FL), 2021. https://www.ncbi.nlm.nih.gov/books/NBK549906/ (accessed 2026-07-24).
        49. Katzmann JL, Laufs U. Choosing the right non-statin therapy for the right patient—how to sequence advanced lipid-lowering therapies. Curr Atheroscler Rep. 2026;28(1):28. doi:10.1007/s11883-026-01390-7
        50. American College of Cardiology. Reduction of Cardiovascular Events With Icosapent Ethyl–Intervention Trial (REDUCE-IT). Published November 10, 2018. Updated August 26, 2022. Accessed July 24, 2026. https://www.acc.org/latest-in-cardiology/clinical-trials/2018/11/08/22/48/reduce-it
        51. Marston NA, Bergmark BA, Alexander VJ, et al. Olezarsen for managing severe hypertriglyceridemia and pancreatitis risk. N Engl J Med. Published online 2025. doi:10.1056/NEJMoa2512761
        52. Banach M, Jaiswal V, Ang SP, et al. Impact of Lipid-Lowering Combination Therapy With Statins and Ezetimibe vs Statin Monotherapy on the Reduction of Cardiovascular Outcomes: A Meta-analysis. Mayo Clin Proc. 2025;100(12):2152-2171. doi:10.1016/j.mayocp.2025.01.018
        53. Khan SU, Yedlapati SH, Lone AN, et al. PCSK9 inhibitors and ezetimibe with or without statin therapy for cardiovascular risk reduction: a systematic review and network meta-analysis. BMJ. 2022;377:e069116. Published 2022 May 4. doi:10.1136/bmj-2021-069116
        54. Bohula EA, Marston NA, Bhatia AK, et al. Evolocumab in patients without a previous myocardial infarction or stroke. N Engl J Med. Published online 2025. doi:10.1056/NEJMoa2514428
        55. Edison RJ, Muenke M. Central nervous system and limb anomalies in case reports of first-trimester statin exposure. N Engl J Med. 2004;350(15):1579-1582. doi:10.1056/NEJM200404083501524
        56. Karadas B, Uysal N, Erol H, et al. Pregnancy outcomes following maternal exposure to statins: A systematic review and meta-analysis. Br J Clin Pharmacol. 2022;88(9):3962-3976. doi:10.1111/bcp.15423
        57. US Food and Drug Administration. FDA requests removal of strongest warning against using cholesterol-lowering statins during pregnancy; still advises most pregnant patients should stop taking statins. Published July 20, 2021. Accessed July 24, 2026. https://www.fda.gov/drugs/drug-safety-and-availability/fda-requests-removal-strongest-warning-against-using-cholesterol-lowering-statins-during-pregnancy
        58. Agarwala A, Dixon DL, Gianos E, et al. Dyslipidemia management in women of reproductive potential: An Expert Clinical Consensus from the National Lipid Association. J Clin Lipidol. 2024;18(5):e664-e684. doi:10.1016/j.jacl.2024.05.005
        59. Ghio A, Bertolotto A, Resi V, Volpe L, Di Cianni G. Triglyceride metabolism in pregnancy. Adv Clin Chem. 2011;55:133-153. doi:10.1016/b978-0-12-387042-1.00007-1
        60. Fellström BC, Jardine AG, Schmieder RE, et al. Rosuvastatin and cardiovascular events in patients undergoing hemodialysis. N Engl J Med. 2009;360(14):1395-1407. doi:10.1056/NEJMoa0810177
        61. Grinspoon SK, Fitch KV, Zanni MV, et al; REPRIEVE Investigators. Pitavastatin to prevent cardiovascular disease in HIV infection. N Engl J Med. 2023;389(8):687-699. doi:10.1056/NEJMoa2304146
        62. US Food and Drug Administration. FDA approves first treatment shown to reduce risk of acute pancreatitis in adults with severe hypertriglyceridemia. Published June 24, 2026. Accessed July 24, 2026. https://www.fda.gov/drugs/news-events-human-drugs/fda-approves-first-treatment-shown-reduce-risk-acute-pancreatitis-adults-severe-hypertriglyceridemia
        63. Al-Gobari M, Le HH, Fall M, Gueyffier F, Burnand B. No benefits of statins for sudden cardiac death prevention in patients with heart failure and reduced ejection fraction: A meta-analysis of randomized controlled trials. PLoS One. 2017;12(2):e0171168. Published 2017 Feb 6. doi:10.1371/journal.pone.0171168
        64. Lala A, Desai AS. The role of coronary artery disease in heart failure. Heart Fail Clin. 2014;10(2):353-365. doi:10.1016/j.hfc.2013.10.002
        65. Kjekshus J, Apetrei E, Barrios V, et al. Rosuvastatin in older patients with systolic heart failure. N Engl J Med. 2007;357(22):2248-2261. doi:10.1056/NEJMoa0706201
        66. GoodRx. How Much Is Repatha Without Insurance? Accessed July 24, 2026. https://www.goodrx.com/repatha/how-much-is-repatha-without-insurance
        67. GoodRx. Praluent Cost Without Insurance. Accessed July 24, 2026. https://www.goodrx.com/praluent/praluent-cost-without-insurance
        68. GoodRx. Nexletol Cost Without Insurance. Accessed July 24, 2026. https://www.goodrx.com/nexletol/nexletol-cost-without-insurance
        69. Doshi JA, Puckett JT, Parmacek MS, Rader DJ. Prior Authorization Requirements for Proprotein Convertase Subtilisin/Kexin Type 9 Inhibitors Across US Private and Public Payers. Circ Cardiovasc Qual Outcomes. 2018;11(1):e003939. doi:10.1161/CIRCOUTCOMES.117.003939
        70. Regeneron Pharmaceuticals, Inc. PRALUENT® (alirocumab) injection: access and affordability. Accessed July 24, 2026. https://www.praluenthcp.com/s/access-and-affordability
        71. Amgen Inc. Repatha (evolocumab) cost and co-pay card information. Accessed July 24, 2026. https://www.repatha.com/repatha-cost
        72. Novartis Pharmaceuticals Corporation. LEQVIO (inclisiran) Care Program: Savings and Support. Accessed July 24, 2026. https://www.leqvio.com/savings-and-support/leqvio-care-program
        73. Amgen Inc. Repatha (evolocumab) Free Trial Program. Accessed July 24, 2026. https://www.repatha.com/freetrial
        74. Centers for Medicare & Medicaid Services. How Much Does Medicare Drug Coverage Cost? Medicare.gov. Accessed July 24, 2026. https://www.medicare.gov/health-drug-plans/part-d/basics/costs

        LAW: The Legal Blueprint: Designing Error-Proof Pharmacy Policies

        Learning Objectives

        After completing this continuing education activity, pharmacists and pharmacy technicians will be able to

        1. RECALL the key governing bodies and their role
        2. RECOGNIZE important details, dates, and timelines for a pharmacy manager
        3. DESCRIBE the duties of pharmacy technicians and interns
        4. DETERMINE the roles and responsibilities of a pharmacy manager
        5. IDENTIFY key pharmacy laws that pharmacy managers should implement in practice


          A man is adding notes to a blue paper set on a table, using a pencil

           Release Date

          Release Date: August 15, 2026

          Expiration Date: August 15, 2029

          Course Fee

          $7 Pharmacist

          $4 Pharmacy Technician

          There is no funding for this CE.

          ACPE UANs

          Pharmacist: 0009-0000-26-042-H03-P

          Pharmacy Technician: 0009-0000-26-042-H03-T

          Session Codes

          Pharmacist: 26YC42-DEP75

          Pharmacy Technician: 26YC42-PDE57

          Accreditation Hours

          2.0 hours of CE

          Accreditation Statements

          The University of Connecticut School of Pharmacy and Pharmaceutical Sciences is accredited by the Accreditation Council for Pharmacy Education as a provider of continuing pharmacy education.  Statements of credit for the online activity ACPE UAN 0009-0000-26-042-H03-P/T will be awarded when the post test and evaluation have been completed and passed with a 70% or better. Your CE credits will be uploaded to your CPE monitor profile within 2 weeks of completion of the program.


          Disclosure of Discussions of Off-label and Investigational Drug Use

          The material presented here does not necessarily reflect the views of The University of Connecticut School of Pharmacy and Pharmaceutical Sciences or its co-sponsor affiliates. These materials may discuss uses and dosages for therapeutic products, processes, procedures and inferred diagnoses that have not been approved by the United States Food and Drug Administration. A qualified health care professional should be consulted before using any therapeutic product discussed. All readers and continuing education participants should verify all information and data before treating patients or employing any therapies described in this continuing education activity.

          Faculty

          Dylan DeCandia, PharmD, RPh.

          Manager, Franklin’s Pharmacy

          Ho-Ho-Kus, NJ

          Faculty Disclosure

          In accordance with the Accreditation Council for Pharmacy Education (ACPE) Criteria for Quality and Interpretive Guidelines, The University of Connecticut School of Pharmacy and Pharmaceutical Sciences requires that faculty disclose any relationship that the faculty may have with commercial entities whose products or services may be mentioned in the activity.

          Dylan DeCandia, PharmD has no relationships with ineligible companies.


          ABSTRACT

          As the retail pharmacist’s scope of practice evolves and pharmacies become busier, pharmacy managers' responsibilities grow more and more complex. To understand these complexities, pharmacy managers require a deep understanding of state and federal laws. The most successful pharmacy managers operate in a constant state of readiness, treating compliance as an everyday process rather than a response to an inspection. This continuing education activity will develop pharmacy managers and provide resources for upcoming or unannounced inspections.

          CONTENT

          INTRODUCTION

          Along with pharmacy practice becoming more complex, well-being reports reveal pharmacy staff members experience high rates of burnout and distress. Often, these factors lead to staff turnover, medication errors, inadequate patient education, and increased risk of patient harm. To mitigate these issues and manage staff, pharmacies require highly educated and trained pharmacy managers. For pharmacy managers, companies have high expectations that the candidates they select will know and adhere to company policy, but also state and federal laws.1,2 The most successful pharmacy managers operate in a constant state of readiness, treating compliance as an everyday process rather than a response to an inspection.


          Pharmacy manager responsibilities fall into three main categories: the pharmacy, the personnel, and the prescription. The pharmacy manager's responsibilities are broad because the manager is accountable for anything that occurs in the pharmacy. Let's start with a PRO TIP: The best pharmacy managers don't prepare for inspections—they practice in a constant state of readiness every day.


          REGULATORY BODIES IN PHARMACY

          When they have knowledge of pharmacy governing bodies, pharmacy managers improve efficiency when filing reports, researching pharmacy law updates, and reviewing statutes. The Food and Drug Administration (FDA) and the Drug Enforcement Agency (DEA) are the major players at the federal level. The FDA creates and enforces regulations for all consumer products, including pharmaceuticals. FDA inspectors review each step of the pharmacy supply chain; any issue during this process must be reported to them.


          The DEA enforces the U.S. controlled substance laws. Pharmacy managers must report any issue with controlled substance distribution and manufacturing, or general related concerns to the DEA. We discuss some specific DEA Forms during the Legend Drug Inventory section later in this activity.3


          The Joint Commission (TJC) creates pharmacy practice standards and, similar to the FDA, they enforce these standards. TJC is an independent, non-profit entity that accredits and manages healthcare facilities and services, such as hospitals, home care pharmacies, and point-of-care testing.4,5


          On the state level, the Board of Pharmacy (BOP) regulates pharmacy practices. Every state has different pharmacy laws. Pharmacy managers must be familiar with their state's BOP to understand changes in laws or pharmacy practice to maintain a CONSTANT STATE OF READINESS. In many states like Connecticut, the BOP acts as a judicial group, approving licenses or registrations and ruling on penalties if anything transpires during inspections.6 Pharmacists under investigation or at risk of having their license suspended or revoked may need to visit BOP meetings to hear the judgements.6

          A woman is very excited to be promoted to pharmacy manager

          PAUSE AND PONDER: Congrats! Your management promoted you to pharmacy manager. Take a moment and consider your new responsibilities. What have you seen pharmacy managers oversee in the past? Who or what do you supervise?


          PHARMACY MANAGER RESPONSIBILITIES


          New Pharmacy Managers

          Many states have specific regulations for newly promoted pharmacy managers. Regulations for reporting controlled substance inventories, reporting changes in management, and potential interviews with the BOP after promotion often differ between states.


          Many states like Alabama, Nevada, New Jersey, and Texas require pharmacy managers to record controlled substance inventories upon promotion.7 The timeline to report the inventory also differs between states. Alabama requires a full controlled substance inventory within 15 days promotion, whereas Texas and Nevada have stricter reporting laws after the manager changes.8 Texas requires inventory on the day of management change and Nevada requires inventory within 48 hours.8,9,10 A PRO TIP is that new pharmacy managers should record a full controlled substance inventory, even if state laws do not mandate one. While taking inventory, the pharmacy manager can reconcile old problems that occurred prior to their supervision, preventing future liability issues.


          Reporting updates in management also differs between states. A new pharmacy manager should always report a management change to the board. Many states require the out-going pharmacy manager to report their departure as well.7,11 During state inspections, clarity about the current pharmacy manager can improve the efficiency of the visit.


          Upon promotion to pharmacy manager in Connecticut, the state's Department of Consumer Protection requires an in-person interview with the Commission of Pharmacy (COP). The COP, known as the BOP in most states, will discuss new manager responsibilities and assess the pharmacist's character during the interview. The COP meets on the last Wednesday of every month, except for December, January, and February, so each pharmacy manager should plan accordingly and submit requests to appear at the monthly meeting early.6,12


          Personnel

          A pharmacy manager's main responsibility is managing the pharmacy's personnel. Outside of pharmacy law, managers handle staff scheduling and complaints. At first, scheduling may not seem so terrible, but having to schedule an entire staff with no prior experience can quickly become overwhelming. Managers need to plan and inform the team about deadlines for requesting days off. A PRO TIP is to prepare for any eventuality by having staff contact information handy at work and at home. Last minute emergencies or changes will happen sooner than later!


          Licenses and registration requirements are ubiquitous in pharmacies. It's the manager's job to ensure that personnel, the premises, and the controlled substance licenses remain active and valid. Inspectors often check license expiration dates, and they may ask the pharmacist in charge to pull all the pharmacy's licenses for staff and the premises. This is where maintaining a CONSTANT STATE OF READINESS is key. The manager needs to guarantee each staff member's license or registration is current and readily available.13


          In a world plagued with staff burnout, understanding each pharmacy team member and creating a positive environment will prevent errors. According to a 2024 National Pharmacist

          Workforce Study, 73% of pharmacists rated their workload as high or excessively high.14 Across different pharmaceutical fields, retail/community pharmacists ranked highest with 91% of employees reporting excessive workloads.14 Researchers concluded that the pharmacy work environment requires drastic changes. PRO TIP: Pharmacy managers should learn each individual staff member's preferences. Some staff members require scheduled one-on-one time to voice their concerns and questions, others prefer more autonomy to make their own decisions. Pharmacy managers should avoid micromanaging their staff.

          A stick figure leans on the 3 dimensional words PRO TIP

          Let's discuss the details of each pharmacy personnel to understand how to manage them better.


          Personnel: Pharmacist

          Pharmacists must renew their licenses in keeping with state requirements; The National Association of Boards of Pharmacy (NABP) maintains the CPE Monitor system. Upon upgrading to the Plus Plan, users can receive a state-by-state breakdown of renewal requirements for all 50 states and the District of Columbia (DC).15 Other Plus Plan features include a dashboard that outlines the states' required hours and develops alerts for upcoming deadlines.15 Managers need to remind pharmacists as renewal dates approach because, from time to time, states may change the renewal process or period.16


          Pharmacy managers can purchase pharmacy compliance software to track staff licenses and non-CE training requirements. If managers find themselves inundated with tasks, they can designate a pharmacy technician to monitor overall staff progress. For staff members, federal laws mandate training courses on HIPAA, pseudoephedrine, and Fraud, Waste, and Abuse initially upon hire and/or annually.17,18,19,20 Pseudoephedrine training is required for any individual who is directly involved in the sale of Scheduled Listed Chemical Products containing ephedrine, pseudoephedrine, or phenylpropanolamine.20,21 Fraud, Waste, and Abuse training is required for any facility participating in Medicare Part C or Part D or other federal programs.18,19


          Compliance software provides courses and tracks each staff member's progress to help the pharmacy meet federal training requirements annually.22 Some software offers extra management training for pharmacy managers to improve.22 Larger retail chains have proprietary software for management to use like LearnRX for CVS pharmacy technician training.23 Many options for compliance tracking are available for independent pharmacies such as COMPLIANCETrack, PRS Pharmacy Services, and AlignRX.22,24 Independent store pharmacy managers should discuss options with their pharmacy software representatives as they may recommend specific compliance trackers that integrate better with the software.


          For license renewal, pharmacy boards generally notify individuals whose licenses are expiring 30 to 45 days before license expiration. Many states, like Connecticut, use fast-track renewal personal identification numbers (PINs) that identify the license or registration, making renewal simple.25 Renewing the pharmacy license follows the same procedure, which we will discuss later.


          During each renewal period, pharmacists need continuing education (CE) credits. Motivating and encouraging pharmacists to keep up with their CE helps prevent license renewal delays.26 Monitoring each staff member's CEs is difficult, so the pharmacy manager can intermittently remind pharmacists about acquiring CE credits. Many states have different specifications for each CE; Connecticut only requires one annual pharmacy law credit (congrats!).26 As the pharmacy manager also needs CE credits, finding and sharing CEs with staff from accepted accreditors may ease the process.26 The most common place to find specific CE is through the Accreditation Council for Pharmacy Education or the state BOP website. Some states allow pharmacists to take Continuing Nursing Education, Continuing Medication Education classes, or other accredited institutions for credits.26 Although pharmacists do not need to submit CEs when renewing their license, CE audits can occur up to three years after renewal, so pharmacists should track and record each one in CPE Monitor.15


          PAUSE AND PONDER: You've completed hundreds of prescriptions, but the list keeps growing! Meanwhile, your pharmacy technicians, Ethan and Matthew, are bickering about renewing their pharmacy technician license. They seem unsure about their requirements after hearing other pharmacists talk about CE credits. Do pharmacy technicians complete CE credits for license registration renewal? What resources can you show them? Why is it necessary to keep staff educated?


          Personnel: Pharmacy Technicians and Interns

          The Pharmacy Technician Certification Board (PTCB) certifies some pharmacy technicians nationally, designating them Certified Pharmacy Technicians (CPhT). Certain states, such as Texas, North Dakota, and Virginia, require pharmacy technicians to become nationally certified  with the PTCB in addition to registering with the state for licensure; all 50 states, DC, and the U.S. territories recognize technician certification.27 States that do not require this certification often allow higher technician ratios if one technician is a CPhT. If the state authorizes more technicians per pharmacist when the pharmacy employs a CPhT, pharmacy managers can encourage pharmacy technicians to become certified and consider offering a better salary as an incentive.28 Managers should remember that pharmacists may refuse to supervise extra pharmacy technicians if they are not comfortable directly supervising more staff. How pharmacists handle the refusal depends on state law, employer policy, and professional duty standards.


          National certification requires CE credits for technicians.29 Uncertified pharmacy technicians who register with their states (not nationally) often do not need CE. An advantage to certification is that the PTCB helps pharmacy technicians develop and train continuously. Notifying uncertified technicians and encouraging them to take CE is smart. Complacency causes workplace errors and mistakes, so consistent engagement with CE courses will galvanize development and reaffirm skills to prevent medication errors.30


          Each pharmacy technician and intern requires direct supervision. In other words, the pharmacist on duty must be physically present to make in-progress and final checks during the prescription filling process. The supervising pharmacist is responsible for any and all actions of the pharmacy technicians and interns. Federal law does not limit the number of pharmacy technicians, but many states dictate a maximum technician to pharmacist ratio.28,31 Table 1 shows some state limits to technician ratios.7,28,32,33,34,35


          Table 1. Pharmacy Personnel in Various States7,28,32,33,34,35
          Connecticut Massachusetts New Jersey New York
          Pharmacy Manager PIC (resident pharmacy) or Manager of Record (non-resident pharmacy) PIC Supervising Pharmacist or PIC
          Pharmacy Technician

          (2:1 or 3:1 ratio)

          Pharmacy Technician

          (3:1 or 4:1 ratio)

          Pharmacy Technician

          (2:1 ratio)

          Pharmacy Technician

          (2:1 ratio)

          Pharmacy Intern Pharmacy Intern Pharmacy Extern (student) Pharmacy Intern
          Pharmacy Intern

          (post-graduation)

          ABBREVIATIONS: PIC = Pharmacist-in-Charge


          In many states, pharmacy interns must accrue at least 1500 hours across the course of their internships, but cannot work more than 40 hours in a week.31,36 One of few exceptions is Illinois, only requiring students to accumulate 400 hours of training.37 During this time, interns can perform pharmacist tasks including compounding, dispensing medications, and other services, as long as they have direct supervision from a pharmacist.38 To oversee interns, pharmacists must become pharmacy intern preceptors.


          Compared to pharmacy interns, pharmacy technicians have a limited scope of responsibility. Technicians cannot perform tasks that call for extended clinical knowledge or decision making, such as counseling patients, receiving new verbal prescriptions, or determining therapeutic alternatives. Besides general prescription filling, technicians can receive refill authorizations from practitioners, given the prescription is identical to the previous refill and not a controlled substance.39 The pharmacist should establish that the prescription remains unchanged from the previous refill by checking the technician's prescription. Pharmacy managers must confirm that staff members practice within their scope.


          Sometimes, busy pharmacies use pharmacy interns as extra labor during their rotations. Pharmacy managers should NOT encourage using pharmacy interns this way; all pharmacy managers should remember their time as interns and use that to help promote a safe environment that nurtures learning without overworking them. Because pharmacy managers are knowledgeable in pharmacy practice, they should offer themselves as a resource to pharmacy interns.


          The same applies to pharmacy technicians. Pharmacy technicians are the pharmacists' most important assets. Without them, the pharmacy would not run smoothly. Pharmacy managers should not delegate menial tasks to them, but rather work alongside them to form a proper team.


          To avoid patient confusion (patients sometimes think anyone in a white coat or scrubs is “the pharmacist,” when in reality, the person may be a technician or a clerk), pharmacy managers should encourage the use of clearly visible name tags. Name tag laws change among states. New York requires anyone working in a registered pharmacy to wear a name tag that also indicates their position.40,41 New Jersey instructs all pharmacy personnel to wear name tags, except when actively compounding sterile prescriptions.42 In Connecticut, state law requires only pharmacy technicians to wear name tags.39 Every state is different!


          Originally, Iowa required pharmacy personnel to wear identification name tags but have since repealed those laws.43 In April 2024, Iowa legislators developed a new pharmacy practice act to update a 40-year-old law and nurture a modern standard of care. Behind Alaska and Idaho, Iowa became the 3rd state to overhaul their pharmacy laws to push pharmacists toward higher practitioner status.44 Although not specifically mentioned, some may attribute the name tag repeal to the cut and slash for removing outdated, overly meticulous pharmacy laws.


          Maintaining current licenses, required training, and clearly defined staff responsibilities keeps both the team and the pharmacy in a constant state of readiness.


          The Pharmacy

          Every pharmacy location differs, so each pharmacy manager should identify the exact parts of the premise they control. If the prescription department resides within a regular store, the pharmacy manager will have less to oversee than if the whole store is devoted to pharmacy as its primary operation. The location of the prescription department will also change requirements for personnel, security, signage, and licensing change.


          If the pharmacy is entirely devoted to the practice of pharmacy (i.e., not a pharmacy located within a business), the pharmacy manager must supervise all products in the store. Pharmacy managers can delegate clerks or other pharmacy employees to check over-the-counter stock to prevent any safety issues due to misbranded drugs or devices.45 Staff should remove any improperly labelled, expired, or other damaged products from stock.45 Independent of normal stock, staff must maintain the pharmacy in clean, sanitary order.46


          PAUSE AND PONDER: The prescriptions keep piling up, patients are upset, there is simply not enough room or staff to manage the workload. Thankfully, you have notified your pharmacy owner, Frank, and he (finally) determined that the pharmacy needs a new, larger location. As pharmacy manager, what tasks do you perform during the move? Does Frank need your help or can he manage the BOP by himself?


          The Pharmacy: Licensure

          When applying for pharmacy licensure, state regulations may require the presence of the pharmacy manager. In Connecticut, regardless of whether the application for the pharmacy licensure is for a new pharmacy or a relocating pharmacy, the pharmacy manager must present in person with the licensee to the board.47 In other states, pharmacy managers are, more often, not required to appear before the board, unless they are the owners. For example, New Jersey and Massachusetts require new owners to disclose their pharmacy manager on the application, but the manager does not always have to interview. Massachusetts indicates any member of the application process, such as the pharmacy manager, applicant, or interest holder, may be required to appear before the board.48,49 New pharmacy managers should understand their responsibilities in new pharmacy applications.


          North Dakota remains the only state that requires the pharmacy owner to be a registered pharmacist in good standing. This law, enacted in 1963, prevents chain pharmacies from opening stores throughout the state. Chains, such as Walgreens and Walmart, attempted to repeal the law in 2009, 2011, and 2014, but were unsuccessful. In 2014, Walmart spent nearly $3 million to campaign pushing to overturn the ownership law, stating that their presence could lower prescription prices. At the time, North Dakota ranked as the 13th lowest state for prescription pricing.50,51


          Renewing pharmacy licenses follows the same procedure as pharmacists and pharmacy technicians. PRO TIP: Pharmacy managers can create charts to help visualize and track deadlines. Table 2 illustrates how a Connecticut pharmacy manager can display license renewal dates and cost for staff reference.


          Table 2. CT License Renewal Information 16,25,52
          License Date Required (Annually) New License Cost ($) Renewal License Cost ($)
          Pharmacist January 31st 200 100
          Pharmacy Technician March 31st 50 50
          Pharmacy August 31st 750 190


          The Pharmacy: Hours of Operation & Signage

          After the board approves the pharmacy's license, the pharmacy manager must supervise the proper placement of signage and hours of operation. Each state has specific requirements for minimum hours of operation and sign placement. For Connecticut, the pharmacy must remain open at least 35 hours per week.53 Unscheduled closings of the prescription department may occur due to emergencies that leave prescription departments without a pharmacist. Unscheduled closings for Connecticut pharmacies must not exceed one day and 18 times in a 365-day period or more than twice in any 39-day period.54 Within 72 hours of any unscheduled closing, the pharmacy manager must report the closure to the COP.


          The pharmacy manager must post helpful details, such as closure duration or any pharmacies in a two-mile radius, so patients can continue to receive therapy.54 If pharmacy managers find it difficult to keep the business open for lack of staff or other reasons, they can request a change in hours to the prescription department. The pharmacy manager must notify the COP 30 days before making any permanent changes.55


          Hours of operation in rural states continue to challenge lawmakers. Currently, Maine requires pharmacies to remain open for 40 hours per week.56 When 10% of Maine pharmacies closed between 2013 and 2024, lawmakers began to push new changes to pharmacy law to prevent more closures and pharmacy deserts.57,58 A new bill allowing retail pharmacies to operate remote dispensing sites in rural areas is fighting through the Maine legislative system to challenge the current laws.59


          Without directly changing the hours of operation laws, remote dispensing sites allow pharmacies to employ less staff onsite while increasing access to healthcare. While needing to reach minimum staffing and hours requirements, independent pharmacy gross profit margins plummeted to 21%, the lowest since the National Community Pharmacist Association began recording the data.60 Rural pharmacy managers must identify ways to reach minimum hours of operation to maximize expenses while providing optimal care to patients. Some rural states, like Montana, do not specify a minimum hours of operation for retail pharmacies.61


          If the business is devoted to the practice of pharmacy, the pharmacy manager should post its hours at all pharmacy entrances.62 In addition, pharmacy managers must display their own name within or near the prescription department so patients can identify them.63 Although signage seems menial, inspectors consistently check during routine visits. For all other signage, pharmacy managers can employ Table 3 to guarantee signage compliance in future inspections.


          Table 3. Key Signage Checklist46
          Sign Specifications
          Pharmacy License Conspicuously posted
          Pharmacy manager name Clearly and readily identifiable to patients and customers
          Generic Drug Substitution “THIS PHARMACY MAY BE ABLE TO SUBSTITUTE A LESS EXPENSIVE DRUG PRODUCT OR INTERCHANGEABLE BIOLOGICAL PRODUCT WHICH IS THERAPEUTICALLY EQUIVALENT TO THE ONE PRESCRIBED BY YOUR DOCTOR UNLESS YOU DO NOT APPROVE””


          Block letters not less than one inch in height

          Reporting of prescription errors Lettering in a size and style that allows for consumers to read without difficulty at the prescription department distribution counter


          “If you have a concern that an error may have occurred in the dispensing of your prescription you may contact the Department of Consumer Protection, Drug Control Division, by calling 1-800-842-2649"


          The Pharmacy: Equipment & Security

          For pharmacy managers in new pharmacies or relocating pharmacies, the BOP must first approve storage conditions for controlled substance and other legend drugs. Facility security requirements will change depending on previous security incidents or vulnerability to theft, number of controlled substances on hand, and other conditions that warrant increased security. Federal law mandates a steel cabinet or approved safe weighing at least 750 pounds or bolted/cemented into the building.64,65,66


          Other pharmacy equipment subject to inspection include refrigerators, balances, and pharmacy pill counters. The pharmacy manager should maintain equipment in clean, working order.46 Some states require pharmacies to keep specific equipment on hand, especially if non-sterile compounding occurs on site. Although tedious, New Jersey law instructs pharmacies to keep certain spatulas, volumetric devices, pharmaceutical references, and other materials on hand.67 Originally, New York instructed every pharmacy to carry the United States Pharmacopoeia Dispensing Information, but recent changes dictate only physical copies of pharmacy law are kept on hand. For other current references, New York law permits online access.68

          Pharmacy managers should delegate refrigerator and freezer temperature tracking twice daily. When logging temperatures, staff should confirm each metric falls within appropriate ranges. Connecticut state law indicates specific safe temperature ranges:

          • Refrigerator
            • 2 to 8o C OR
            • 36 to 46o F
          • Freezer
            • Minus 25 to minus 10o C OR
            • Minus 13 to 14o F

          Staff must notify the pharmacy manager if temperatures stray from the recommended range (called temperature excursions) as inspectors frequently check refrigeration logs.46 Small details add up during inspections! Routine attention to equipment, security, and environmental requirements prevents last-minute scrambling and reinforces a constant state of readiness.


          The Prescription

          Document, document, document. If you didn't document it, it did not happen. These phrases should ring in every pharmacist's ears. Whether changing a prescription with practitioner approval, making a generic substitution, or other prescription adjustments, the pharmacy personnel should document everything. Documentation could protect the pharmacy manager and pharmacists from potential liabilities. Always document when dispensing!

          PAUSE AND PONDER: What are your state's electronic prescribing laws? How does your staff handle/check written controlled substance prescriptions? Do you accept verbal prescriptions for controlled substances?


          The Prescription: Controlled Substances

          Recent pharmaceutical trends show changes between opioid and stimulant prescribing in the United States. The opioid epidemic forced healthcare professionals to adjust prescribing patterns for optimal treatment to ensure minimal opioid use. Meanwhile, stimulant prescribing rates steadily increased between 2012-2022. With the DEA monitoring both situations, pharmacy managers must prepare their pharmacists.69,70,71

          Electronic prescribing laws can improve the safety, quality, and efficacy of dispensing and prescribing.72 Most states in the northeast United States have mandatory electronic prescribing laws for controlled substances, except for Vermont and New Jersey. As of 2015, Vermont became the 50th (last) state to allow electronic prescribing of controlled substances, without any hopes of electronic prescribing mandates on the horizon.73 Some New Jersey legislators drafted bills for mandating electronic prescribing for all prescriptions, but none of them passed. The most recent New Jersey mandate bill died January 12, 2026 after two years in the committee.74

          New York became the first state to mandate electronic prescribing for both controlled and non-controlled substance prescriptions.75,76 The Center for Medicare and Medicaid Services (CMS) has specific policies for electronic prescribing; currently, CMS requires Part D prescribers to send at least 70% of their prescriptions electronically. States like New York have few worries because their laws align with the CMS mandate.77,78

          Each state restricts controlled substance prescribing differently. States like North Carolina and New Jersey limit prescribing on initial opioid prescriptions for acute pain to five days. Across the U.S., states often limit initial opioid prescribing to seven days. Filling initial opioid prescriptions outside of these recommendations leave pharmacies open to liabilities.79 PRO TIP: Pharmacy managers can post these recommendations near workstations as a constant reminder.

          Prescription drug monitoring programs (PDMP) are state level databases that help track controlled substance habits for each patient. State laws mandate pharmacists use the PDMP to inform clinical decision making. The PDMP verifies that other pharmacies did not dispense the controlled substance in recent history or check to see if the patient has tolerance to opioids to receive more than an initial day supply. Electronic software should transmit all prescription and patient information, including pay code for cash or insurance, to the PDMP. Pharmacists must check the PDMP before filling controlled substance prescriptions and report controlled substance fills to the PDMP.80,81

          Because controlled substance scheduling changes, each state may require different reporting to the PDMP. For example, gabapentin scheduling varies drastically between states. Kentucky became the first state to reclassify gabapentin to a schedule V controlled substance, so pharmacists must report gabapentin prescriptions to the state's PDMP.82 Similarly, in 2019, Michigan reclassified gabapentin as a schedule V controlled substance. However, only six years later, Michigan descheduled gabapentin back to non-scheduled; pharmacy laws are always changing!83 Meanwhile, New Jersey does not classify gabapentin as a controlled substance, but still requires pharmacists to report fills to the PDMP.84 Pharmacy managers should stay up-to-date with their state's reporting regulations to properly submit PDMP information.


          The Prescription: Legend Drug Inventory

          Pharmacy managers monitor controlled substance inventories. Many states enforce perpetual inventory records for Schedule II controlled substances. Perpetual inventory records allow pharmacies to identify mistakes or stock loss effortlessly during reconciliation periods. Because federal law requires pharmacies to report significant controlled substance loss within one day, perpetual inventory organization bolsters the pharmacy's CONSTANT STATE OF READINESS.

          If a significant loss or theft of a controlled substance occurs, the pharmacy manager must report to the DEA in writing within one business day, then file DEA Form 106 within 45 days.85 The DEA does not specify what constitutes a significant loss, but their Diversion Control Division gives criteria to help pharmacists estimate if a loss is significant86:

          • Quantity lost in relation to the business
          • Type of controlled substance lost
          • If a pattern of loss is identified
          • The controlled substance lost is a candidate for diversion

          The DEA no longer accepts paper DEA form 106, so pharmacy managers should submit electronic forms only. Pharmacy managers will have to report to both federal and state agencies. Although all pharmacies must adhere to federal reporting guidelines, some states allow longer intervals when reporting to state agencies. For example, Connecticut permits 72 hours when reporting loss or theft to the Commissioner of Consumer Protection.87

          For confirming controlled substance stock, many large retail or inpatient pharmacies use automated dispensing cabinets (ADCs) or pharmacy software equipped with back counting features. Examples of popular ADCs found in hospitals include BD's Pyxis Medflex or Omnicells XT.88,89 Pharmacies lacking funds for expensive hardware can track similarly with logbooks. In this case, each staff member should write the prescription number, amount dispensed, date, and their name for each fill. If pharmacy managers implement techniques like these, the risk of medication loss will diminish.

          A pharmacist fills out a logbook after accessing the substance controlled safe

          After placing an order for new controlled substances, staff should attach DEA Form 222 (electronic or print) to schedule II invoices. On the invoice, it's necessary to record who received the inventory, when it was received, and how much was received. If the manager discovers a major issue with the inventory, organized records will help pinpoint a date, time, and the person last responsible for that stock.90

          The DEA enforces a biennial inventory for staff to report and reconcile inventory for all controlled substances. Each inventory record must report if the inventory occurred before opening of business or after close of business, the date, and the staff member responsible.91

          If a patient does not pick up prescribed medication, staff must return those medications to stock. Before relocating the bottle to the shelf, staff must credit the insurance by reversing the claim.92 To prevent misbranded drugs in the pharmacy stock, staff must take precautions to properly label returned medications. Return to stock medications should display the drugs name, strength, lot number, manufacturer, and expiration date.93 Managers should encourage staff to use this advice for other legend drugs as well. Pharmacies should not shelve medication with damaged labels; tears that obstruct small information could lead to fines during inspection.

          Well-organized records do more than satisfy inspectors—they allow pharmacy managers to demonstrate a constant state of readiness every day of the year.


          The Prescription: Record Keeping

          In many pharmacy basements, anyone can find boxes and boxes of prescription records as old as time. Maybe they do not have to stay there forever! Connecticut state law deems three years as satisfactory for documentation87,94,95,96,97,98:

          • Prescription records (regular and controlled)
          • Medication error documentation
          • Controlled substance inventories (annual and perpetual)
          • Pharmacist prescribing screening

          Every pharmacy manager should understand that record keeping regulations change between states. Other states, such as Colorado and Virginia, require pharmacies to keep prescription records on file and retrievable for only two years.99,100

          State pharmacy inspections often allow 48 hours to retrieve these documents, except for controlled substance inventory records. Pharmacy managers must produce controlled substance inventory data immediately upon inspection. The DCP permits electronic records, but if staff print the electronic copy, then they must add them to regular prescription records in chronological order.96 Outside of pharmacy records, pharmacists should keep their continuing education certificates for three years for potential CE audits.26 Connecticut's three-year record keeping requirement generally satisfies federal regulations. For electronic controlled substance ordering system (CSOS) records and prescriptions, federal law mandates pharmacies keep records for two years.101,102

          Note that, despite state law, many pharmacies keep prescription records longer. CMS dictates retaining prescription records for at least 10 years, a requirement for all Part D sponsors and their downstream entities, like pharmacies, to receive Medicare reimbursement.103 A PRO TIP is to mark boxes headed to storage with the content by date and prescription number range, and also include the date on which the contents can be destroyed.

          PAUSE AND PONDER: A patient calls you over for consultation. She received someone else's prescription! As a newly promoted pharmacy manager, what steps do you need to take? Who is responsible?


          The Prescription: Quality Assurance and Reporting

          Quality improvement, a major task delegated to the pharmacy manager, ensures that the pharmacy and its staff members monitor prescription errors. The strongest programs identify potential oversight and correct them before a medication error occurs. Every staff member in the pharmacy should receive a copy of the quality improvement policies and procedures from the pharmacy manager. When pharmacy managers create strong quality assurance programs, they reduce liabilities. PRO TIP: Pharmacy managers with interest in learning new quality improvement techniques can visit the National Coordinating Council for Medication Error Reporting and Prevention (https://www.nccmerp.org/).104

          When an error occurs, the pharmacy manager or staff should notify all involved parties: the prescriber, the patient, and the person who made the error (if applicable). Any error ideally initiates a policy review. The person closest to the error must document the date of the review, the name and title of the reviewer, and any information related to the prescription error. Every medication error should be documented on a separate incident report. Organization is key for prescription error reports. Clear and concise notes allow future inspectors or pharmacy managers to determine potential areas of vulnerability.105 Supplement 1 is an example of a prescription error reporting form that pharmacy managers can use in practice.

          Pharmacy managers should update procedures after identifying problem areas to prevent future errors. If a change in the procedure occurs, the pharmacy manager should properly educate all staff. Some staff members take longer to learn, so pharmacy managers should allow time to learn and adjust.

          Discovering medication errors will test pharmacy managers' ability to lead their teams. Many times, managers discipline staff after finding medication errors, but, instead of scolding staff, pharmacy managers should learn more progressive alternatives. The more a manager scolds staff, the less the staff will bring issues to the manager. Healthier work environments create stronger error prevention systems.106

          Four pharmacists happily attend the monthly meeting with the pharmacy manager

          Some managers use monthly staff meetings to identify potential problems. Pharmacy managers cannot observe at all times. When pharmacists speak at monthly meetings, they create conversations about topics that went unnoticed. Multiple staff recognizing the same issue means discovering a trend. At meetings, pharmacists can brainstorm alternatives, refurbish policies, and improve communication between staff!

          Apart from onsite medication error reporting, the Food and Drug Administration (FDA) hosts a post-marketing surveillance system called MedWatch (https://www.fda.gov/safety/medwatch-fda-safety-information-and-adverse-event-reporting-program). If patients experience adverse events, quality issues, medication errors, or other therapeutic failures, they can visit the FDA website to submit the event. After receiving the information, the FDA will monitor other patient reports. If additional patients note the same dilemma, a team of experts may trigger a recall or further investigation to amend the issue.107

          The FDA MedWatch helps advance public health initiatives. Pharmacy managers should encourage staff to use and recommend patients report to MedWatch to prevent future harm.


          The Prescription: Child Resistant Caps

          A major federal law change in pharmacy history was the Poison Prevention Act of 1970. This law mandates manufacturers and pharmacies to have child resistant packaging on any over-the-counter or prescription medication. Pharmacy managers must instruct all staff to default child resistant caps for prescription bottles.108

          If patients cannot open the child resistant cap due to disability, preference, or other limitations, they can ask the pharmacy to provide them only non-child resistant caps. The pharmacy manager should teach staff to document the patient's request and date on their file for future fills.

          Pharmacists must inform patients on proper storage of prescription medications in homes where children frequent. Children are resilient and always find ways into places they should not access. Using all precautions, such as keeping medication out of reach or locking medication away, avoids accidental poisoning.

          A child is kneeling on the bathroom sink while reaching into the medicine cabinet and taking out a prescription bottle

          The Prescription: Hypodermic Needles

          Pharmacy managers should teach staff about over-the-counter needle sales. Pharmacy managers should teach staff about over-the-counter needle sales. States like New Jersey and Connecticut permit over-the-counter needle sales, but an individual may only receive 10 needles or fewer per over-the-counter purchase. New Jersey limits over-the-counter needle sales to patients 18 years and older. Any quantity that exceeds that amount needs a prescription. The NJ Harm Reduction and CT Syringe Services programs do not specify any weekly or monthly limit on over-the-counter purchases of hypodermic needles. Meanwhile, the California Department of Public Health NO limit on the number of syringes sold at a single time. New York's Expanded Syringe Access Program permits daily purchases.109,110,111,112,113,114

          Expanding access to hypodermic needles prevents the spread of bloodborne diseases. Pharmacy managers should work with staff to create a stigma free environment for patients seeking cleaner methods.110,111


          The Prescription: Omnibus Budget Reconciliation Act of 1990 (OBRA)

          The Omnibus Budget Reconciliation Act of 1990 (OBRA) was designed to improve dispensing laws for Medicaid beneficiaries; any pharmacy wanting to receive funding from Medicaid programs must comply. The federal government made pharmacies responsible for obtaining, recording, and maintaining patient information. Furthermore, OBRA requires pharmacies to review previously received medications to assess the risk for starting or continuing therapy. This practice, called drug utilization review (DUR), became a staple in current pharmacy practice. OBRA also requires pharmacies to offer counseling to every patient.115,116

          Originally intended for only Medicaid beneficiaries, many states adopted OBRA policies to improve pharmacy practice. For example, the Connecticut Medical Assistance DUR Board retroactively reviews HUSKY Health medication claims.117 Each state has similar programs to identify fraud or take corrective action on improperly filled prescriptions.


          Pharmacist Prescribing

          Pharmacist prescribing is a fresh topic for pharmacy managers. Because of the risk associated with prescribing, pharmacy managers must create proper policies and procedures for staff to adhere. All pharmacy staff must document, document, document! Every pharmacy manager should review state record keeping regulations for prescribing; the time for retaining records changes across states.

          As of January 2026, pharmacists can prescribe contraceptives to patients in 30 states and DC. Each state has specific prescribing laws, but all require pharmacists to take extra training for prescribing.118 Notably, these courses review the United States Medical Eligibility Criteria for Contraceptive Use published by the Centers for Disease Control and Prevention (CDC). The training provides a certificate for the pharmacy's records. The eligibility criteria from the CDC discusses the leading guidelines for prescribing contraceptives, so any pharmacist who prescribes outside of its recommendation should document their thought process.119

          After completing the training program, all states require pharmacists to screen any patient who requests a contraceptive prescription.118 Generally, the screening process consists of documenting medical history, recording blood pressure, and completing intake forms.120 Patients are only eligible if they meet the criteria set by the U.S. Medical Eligibility Criteria for Contraceptive Use.120 Most states limit each prescription for 12-months, like normal, non-controlled prescriptions, however, Indiana limits each pharmacist prescribed contraceptive to a maximum of 6-month supply.


          CONCLUSION

          Consistently changing pharmacy laws create a complex environment for pharmacy managers. Controlling the pharmacy, the personnel, and the prescription handling means pharmacy managers must develop a strong understanding of these changing laws. A strong foundation in pharmacy law and organization improve the pharmacy's likelihood of success and help prevent future liabilities and fines during inspections. Ultimately, a constant state of readiness is not simply preparation for an inspection. It is a leadership philosophy that integrates legal compliance, staff development, patient safety, and continuous quality improvement into daily pharmacy practice.

          PAUSE AND PONDER: The stack of prescriptions is falling over. Matt and Ethan have not stopped arguing about nonsense in three hours. The line of patients stretches out the door, and they are tired of waiting. But wait… What is that? Through the glass doors a figure appears with sunlight glimmering around her. The light is bright, but you recognize her. Is it your savior? A floater pharmacist? A technician returning from vacation?

          Nope. The state inspector. She expects you to move fast despite the 30 barking patients. Have you developed your CONSTANT STATE OF READINESS?

          Pharmacist Post Test (for viewing only)

          LAW: The Legal Blueprint: Designing Error-Proof Pharmacy Policies

          26-042 Pharmacist Post-test


          After completing this continuing education activity, pharmacists will be able to

          • RECALL the key governing bodies and their roles
          • RECOGNIZE important details, dates, and timelines for a pharmacy manager
          • DESCRIBE the duties of pharmacy technicians and interns
          • DETERMINE the roles and responsibilities of a pharmacy manager
          • IDENTIFY key pharmacy laws that pharmacy managers should implement in practice


          1. Which government agency creates and enforces regulations for all consumer products, including pharmaceuticals?

          a. The Food and Drug Administration (FDA)

          b. The Drug Enforcement Agency (DEA)

          c. The Joint Commission (TJC)


          *


          2. According to federal law, pharmacies looking to receive Medicare reimbursement must retain prescription records for how many years?

          a. Two

          b. Three

          c. Ten


          *            


          3. What state requirements led to local controversy and pharmacy closures in Maine and other rural states?

          a. Pharmacy technician ratios

          b. Hours of operation

          c. Electronic prescribing laws


          *


          4. How do interns and technicians differ in their responsibilities?

          a. Interns can perform pharmacist tasks including compounding, dispensing medications, and other services with pharmacist supervision

          b. Interns can receive refill authorizations from practitioners, given the prescription is identical to the previous refill and not a controlled substance

          c. Interns can verify prescriptions filled by other interns or technicians for all medications except controlled substances


          *


          5. What technician certification is required in some states, but allows pharmacies in other states to have higher technician:pharmacist ratios?

          a. Certified Pharmacy Technician (CPhT)

          b. Bachelor of Science

          c. Pharmacy Intern License


          *


          6. Which of the following BEST describes the pharmacy manager's responsibilities?

          a. Licensing statuses of other pharmacy personnel

          b. Maintaining the pharmacy in clean, sanitary order

          c. Managing everything that occurs in their pharmacy


          *


          7. Which of the following are federal compliance training requirements for staff members to complete annually and/or upon hire?

          a. Pseudoephedrine, Fraud, Waste, & Abuse, and HIPAA

          b. Phenylephrine, Fraud, Waste, & Abuse, and HIPAA

          c. Pseudoephedrine, Fraud, Waste, & Abuse, and pharmaceutical calculations.


          *


          8. Before prescribing contraceptives to a patient, which of the following must pharmacists complete?

          a. Review OBRA 1990 policies and procedures to ensure they are following the United States Medical Eligibility Criteria for Contraceptive Use.

          b. Complete extra courses for training and screening patients upon request for contraceptives as required by the state.

          c. Nothing. After recent law changes pharmacists are eligible to prescribe any contraceptive upon request of the patient.


          *


          9. A shopper, not a registered patient, comes to your pharmacy counter and asks your technician to purchase hypodermic needles. How is your technician taught to proceed?

          a. Any patient can receive hypodermic needles with a prescription. Because the patient is presenting without one, they cannot receive any needles.

          b. Many states limit the sale of over-the-counter needle sales; the technician may sell needles over-the-counter up to that limit.

          c. Your technician can sell hypodermic needles over-the-counter, but it can only be to regular patients that you recognize with special diagnoses. Notify the patient they can receive needles if they have their prescriptions transferred from their regular pharmacy.


          *


          10. In terms of pharmacy, what was the original goal of OBRA 1990?

          a. Retrospective DURs could help the federal government make more money and cut financial deficits

          b. Improving the quality of dispensing for Medicaid beneficiaries

          c. Develop a series of record keeping requirements for pharmacy licensing


          Pharmacy Technician Post Test (for viewing only)

          LAW: The Legal Blueprint: Designing Error-Proof Pharmacy Policies

          26-042 Technician Post-test


          After completing this continuing education activity, pharmacists will be able to

          • RECALL the key governing bodies and their roles
          • RECOGNIZE important details, dates, and timelines for a pharmacy manager
          • DESCRIBE the duties of pharmacy technicians and interns
          • DETERMINE the roles and responsibilities of a pharmacy manager
          • IDENTIFY key pharmacy laws that pharmacy managers should implement in practice


          1. Which government agency creates and enforces regulations for all consumer products, including pharmaceuticals?

          a. The Food and Drug Administration (FDA)

          b. The Drug Enforcement Agency (DEA)

          c. The Joint Commission (TJC)


          *


          2. According to federal law, pharmacies looking to receive Medicare reimbursement must retain prescription records for how many years?

          a. Two

          b. Three

          c. Ten


          *


          3. What state requirements led to local controversy and pharmacy closures in Maine and other rural states?

          a. Pharmacy technician ratios

          b. Hours of operation

          c. Electronic prescribing laws


          *


          4. How do interns and technicians differ in their responsibilities?

          a. Only interns can perform pharmacist tasks including compounding, dispensing medications, and other services with pharmacist supervision

          b. Only interns can receive refill authorizations from practitioners, given the prescription is identical to the previous refill and not a controlled substance

          c. Only interns can verify prescriptions filled by other interns or technicians for all medications except controlled substances


          *


          5. What technician certification is required in some states, but allows pharmacies in other states to have higher technician:pharmacist ratios?

          a. Certified Pharmacy Technician (CPhT)

          b. Bachelor of Science

          c. Pharmacy Intern License


          *


          6. What resource can pharmacy technicians use for national licensure, technician training courses, and technician continuing education courses?

          a. State Board of Pharmacy

          b. The Pharmacy Technician Certification Board

          c. The FDA Website


          *


          7. Which of the following BEST describes the pharmacy manager's responsibilities?

          a. Licensing statuses of other pharmacy personnel

          b. Maintaining the pharmacy in clean, sanitary order

          c. Managing everything that occurs in their pharmacy


          *


          8. Which of the following are federal compliance training requirements for staff members to complete annually and/or upon hire?

          a. Pseudoephedrine, Fraud, Waste, & Abuse, and HIPAA

          b. Phenylephrine, Fraud, Waste, & Abuse, and HIPAA

          c. Pseudoephedrine, Fraud, Waste, & Abuse, and pharmaceutical calculations.


          *                              


          9. A shopper, not a registered patient, comes to your pharmacy counter and asks your technician to purchase hypodermic needles. How is your technician taught to proceed?

          a. Any patient can receive hypodermic needles with a prescription. Because the patient is presenting without one, they cannot receive any needles.

          b. Many states limit the sale of over-the-counter needle sales; the technician may sell needles over-the-counter up to that limit.

          c. Your technician can sell hypodermic needles over-the-counter, but it can only be to regular patients that you recognize with special diagnoses. Notify the patient they can receive needles if they have their prescriptions transferred from their regular pharmacy.


          *


          10. In terms of pharmacy, what was the original goal of OBRA 1990?

          a. Retrospective DURs could help the federal government make more money and cut financial deficits

          b. Improving the quality of dispensing for Medicaid beneficiaries

          c. Develop a series of record keeping requirements for pharmacy licensing


          References

          Full List of References

          1. Pharmacy 2024. Well-Being Index. Accessed February 3, 2026. https://www.mywellbeingindex.org/state-of-well-being-2024/pharmacy-sowb-2024/
          2. The pharmacist’s guide to recognizing and preventing burnout. American Pharmacist Association. Updated July 30, 2021. Accessed February 5, 2026. https://www.pharmacist.com/Publications/Transitions/the-pharmacists-guide-to-recognizing-and-preventing-burnout
          3. Who we are. U.S. Drug Enforcement Administration. Accessed March 10, 2026. https://www.dea.gov/who-we-are/about
          4. About Us. Joint Commission. Accessed March 10, 2026. https://www.jointcommission.org/en-us/about-us
          5. Joint Commission Accreditation. Joint Commission. Accessed March 10, 2026. https://www.jointcommission.org/en-us/accreditation/
          6. The Commission of Pharmacy. Connecticut Department of Consumer Protection. Accessed February 3, 2026. https://portal.ct.gov/dcp/drug-control-division/commission-of-pharmacy/the-commission-of-pharmacy
          7. N.J. Admin. Code 13:39-6.2 - Pharmacist-in-charge. Cornell Legal Information Institute. Updated December 4, 2017. Accessed February 5, 2026. https://www.law.cornell.edu/regulations/new-jersey/N-J-A-C-13-39-6-2
          8. Alabama Administrative Code Rule 680-X-2-.12 - Supervising Pharmacist. Alabama Legislative Services Agency. Accessed March 13, 2026. https://admincode.legislature.state.al.us/administrative-code/680-X-2-.12
          9. Nev. Admin. Code § 453.475 - Initial and biennial inventory of controlled substances by new managing pharmacist. Cornell Legal Information Institute. Accessed March 13, 2026. https://www.law.cornell.edu/regulations/nevada/NAC-453-475
          10. 22 Tex. Admin. Code § 291.17 - Inventory Requirements. Cornell Legal Information Institute. Accessed March 13, 2026. https://www.law.cornell.edu/regulations/texas/22-Tex-Admin-Code-SS-291-17
          11. 247 CMR § 20.05 - Change of Manager of Record and Pharmacist in Charge
          Cornell Legal Information Institute. Accessed June 10, 2026. https://www.law.cornell.edu/regulations/massachusetts/247-CMR-20-05
          12. Connecticut Comprehensive Drug Laws. Sec. 20-576-23. Newly designated pharmacist managers. Connecticut Department of Consumer Protection; May 2025. Accessed February 3, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          13. Connecticut Comprehensive Drug Laws. Sec. 20-607. Certificate of license, temporary permit or registration to be available for inspection. Connecticut Department of Consumer Protection; May 2025. Accessed February 3, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          14. 2024 Executive Summary: National Pharmacist Workforce Study. Pharmacy Workforce Center. Updated June 2025. Accessed March 10, 2026. https://www.aacp.org/sites/default/files/2025-06/2024-npws-executive-summary-5.27.25.pdf
          15. CPE Monitor. National Association of Boards of Pharmacy. Accessed March 10, 2026. https://nabp.pharmacy/programs/cpe-monitor/
          16. Pharmacist License. Connecticut Department of Consumer Protection. Accessed February 3, 2026. https://portal.ct.gov/dcp/knowledge-base/articles/drug-control/licenses/pharmacist
          17. How Often is HIPAA Training Required? The HIPAA Journal. Updated January 20, 2026. Accessed March 10, 2026. https://www.hipaajournal.com/how-often-is-hipaa-training-required/
          18. 42 C.F.R. 422.503(b)(4)(vi)(C) Medicare Advantage General Provisions. Code of Federal Regulations. Accessed March 10, 2026. https://www.ecfr.gov/current/title-42/chapter-IV/subchapter-B/part-422/subpart-K/section-422.503
          19. 42 C.F.R. 423.504(b)(4)(vi)(C) Voluntary Medicare Prescription Drug Benefit General Provisions. Cornell Legal Information Institute. Accessed March 10, 2026. https://www.law.cornell.edu/cfr/text/42/part-423
          20. Training Required to Sell Drug Products Containing Ephedrine, Pseudoephedrine, and Phenylpropanolamine. U.S. Department of Justice Drug Enforcement Administration. Accessed March 10, 2026. https://deadiversion.usdoj.gov/meth/trg_retail_081106.pdf
          21. CMEA Self Certification. U.S. Department of Justice Drug Enforcement Administration. Accessed March 10, 2026. Updated February 1, 2009. Accessed June 10, 2026. https://www.deadiversion.usdoj.gov/meth/self_cert.html
          22. Compliance Overview. PRS Compliance Services. Accessed March 10, 2026. https://prsrx.com/compliance-overview/
          23. Healthy Business. CVSHealth. Accessed March 11, 2026. https://www.cvshealth.com/impact/healthy-business.html
          24. Professional Compliance Track Platform Features. Compliance Track. Accessed March 11, 2026. https://compliancetrack.co/#features
          25. Pharmacy License Within The State of Connecticut. Connecticut Department of Consumer Protection. Accessed February 3, 2026. https://portal.ct.gov/dcp/drug-control-division/commission-of-pharmacy-licenses/pharmacy-license-within-the-state-of-connecticut
          26. Pharmacist Continuing Education Requirement. Connecticut Department of Consumer Protection. Accessed February 3, 2026. https://portal.ct.gov/dcp/-/media/dcp/drug_control/commission/rph-ce-requirement.pdf
          27. State Regulations and Map. Pharmacy Technician Certification Board. Updated December 31, 2024. Accessed March 10, 2026. https://ptcb.org/resources/state-regulations-and-map/
          28. Connecticut Comprehensive Drug Laws. Sec. 20-576-36. Ratio. Connecticut Department of Consumer Protection; May 2025. Accessed February 3, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          29. Renewal Requirements. Pharmacy Technician Certification Board. Accessed March 10, 2026. https://ptcb.org/renewal-requirements/
          30. Complacency Kills: The Dangers of Complacency in the Workplace. OSHA. Updated February 8, 2023. Accessed February 3, 2026. https://www.osha.com/blog/complacency-safety
          31. Connecticut Comprehensive Drug Laws. Section 20-576-8(c)(1). Sec. 20-576-8. Registration of pharmacy. Connecticut Department of Consumer Protection; May 2025. Accessed February 3, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          32. N.J. Admin. Code § 13:39-6.15 - Pharmacy technician duties and pharmacist-technician ratios. Cornell Legal Information Institute. Updated June 21, 2010. Accessed February 5, 2026. https://www.law.cornell.edu/regulations/new-jersey/N-J-A-C-13-39-6-15
          33. In State and Nonresident Outsourcing Facilities Supervising Pharmacist Responsibilities (Pharmacist in Charge). New York State Education Department. Accessed February 5, 2026.
          https://www.op.nysed.gov/professions/pharmacy-establishments/information/pharmacist-in-charge
          34. Section 39J: Non-resident pharmacies; licensure; designation of pharmacist in charge; distribution of drug preparations produced or compounded by a pharmacy not granted a non-resident license prohibited. The Commonwealth of Massachusetts. Accessed February 5, 2026.
          https://malegislature.gov/Laws/GeneralLaws/PartI/TitleXVI/Chapter112/Section39j
          35. Policy 2024-03: Ratios, Intern Supervision, and Dedicated Training Personnel. The Commonwealth of Massachusetts. Updated September 5, 2024. Accessed February 5, 2026. https://www.mass.gov/doc/2024-03-ratios-intern-supervision-and-dedicated-training-personnel-pdf/download
          36. How do I verify my internship hours for the eLTP application? National Association of Boards of Pharmacy. Accessed March 13, 2026.
          https://nabp.pharmacy/help/how-do-i-verify-my-internship-hours-for-the-eltp-application/
          37. TITLE 68: Professions and Occupations, Section 1330.300 Approval of Pharmacy Programs. Illinois General Assembly. Accessed March 10, 2026. https://ilga.gov/agencies/JCAR/EntirePart?titlepart=06801330
          38. Connecticut Comprehensive Drug Laws. Sec. 20-576-9. Authority of registered pharmacy intern. Connecticut Department of Consumer Protection; May 2025. Accessed February 3, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          39. Connecticut Comprehensive Drug Laws. Sec. 20-576-39. Limitations. Name tags. Connecticut Department of Consumer Protection; May 2025. Accessed February 3, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          40. Frequently Asked Questions for Registered Pharmacy Technicians. New York State Education Department. Accessed June 10, 2026. https://www.op.nysed.gov/professions/registered-pharmacy-technicians/faqs
          41. Education (EDN) Chapter 16, Title 8, Article 137, Section 6808-A Identification of Pharmacists. New York State Senate. Updated September 22, 2014. Accessed February 5, 2026. https://www.nysenate.gov/legislation/laws/EDN/6808-A
          42. N.J. Admin. Code § 13:39-6.3 - Identification tag. Cornell Legal Information Institute. Accessed June 10, 2026. https://www.law.cornell.edu/regulations/new-jersey/N-J-A-C-13-39-6-3
          43. Iowa Admin. Code r.657-5.15: Identification of pharmacy support person. Cornell Legal Information Institute. Updated July 16, 2025. Accessed March 11, 2026. https://www.law.cornell.edu/regulations/iowa/Iowa-Admin-Code-r-657-5-15
          44. Iowa bill updates pharmacy practice act to standard of care framework. American Pharmacists Association. Updated July 3, 2024. Accessed March 11, 2026. https://www.pharmacist.com/APhA-Press-Releases/iowa-bill-updates-pharmacy-practice-act-to-standard-of-care-framework
          45. First-Time Pharmacy Managers Q&A. Connecticut Department of Consumer Protection. Accessed February 3, 2026. https://portal.ct.gov/dcp/-/media/dcp/migrated-docs/commissionfirsttimemanagerquestionsandanswerspdf.pdf
          46. Pharmacy Compliance and Opening Inspection Form. Connecticut Department of Consumer Protection. Accessed February 3, 2026. https://portal.ct.gov/dcp/-/media/dcp/drug_control/pharmacy/inspection-forms/pcy-inspection-questions-compliance-not-official.pdf
          47. Connecticut Comprehensive Drug Laws. Sec. 20-576-20. New pharmacy or relocation of existing pharmacy Connecticut Department of Consumer Protection; May 2025. Accessed February 3, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          48. N.J. Admin. Code 13:39-4.1 - New pharmacies; pharmacy departments; eligibility and application. Cornell Legal Information Institute. Accessed March 13, 2026. https://www.law.cornell.edu/regulations/new-jersey/N-J-A-C-13-39-4-1
          49. 247 CMR: Board of Registration in Pharmacy; 6.04: General Application Requirements. The Commonwealth of Massachusetts. Accessed March 13, 2026. https://www.mass.gov/doc/247-cmr-6-licensure-of-pharmacies/download
          50. North Dakota Century Code t43c15. North Dakota Legislation. Accessed April 15, 2026. https://ndlegis.gov/cencode/t43c15.pdf
          51. North Dakota's Pharmacy Ownership Law. Institute for Local Self Reliance. Updated October 2014. Accessed April 15, 2026. https://ilsr.org/wp-content/uploads/2014/10/ND_Pharmacy_Ownership_Report.pdf
          52. Pharmacy Technician Registration. Connecticut Department of Consumer Protection. Accessed February 3, 2026. https://portal.ct.gov/dcp/drug-control-division/commission-of-pharmacy-licenses/pharmacy-technician-registration
          53. Connecticut Comprehensive Drug Laws. Sec. 20-576-13. Hours of operation of a pharmacy. Connecticut Department of Consumer Protection; May 2025. Accessed February 3, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          54. Connecticut Comprehensive Drug Laws. Sec. 20-576-18a. Unscheduled closing of the prescription department or the pharmacy. Connecticut Department of Consumer Protection; May 2025. Accessed February 3, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          55. Connecticut Comprehensive Drug Laws. Sec. 20-576-17. Closing of prescription department. Connecticut Department of Consumer Protection; May 2025. Accessed February 3, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          56. Maine Board of Pharmacy 02-392 C.M.R. Chapter 3: 13-2 - Hours of Operation; Posting of Hours. Cornell Legal Information Institute. Accessed March 14, 2026. https://www.law.cornell.edu/regulations/maine/02-392-C-M-R-ch-3-SS-13-2
          57. A tenth of Maine’s pharmacies have closed in the past decade. The Maine Monitor. Updated March 3, 2024. Accessed March 14, 2026. https://themainemonitor.org/maine-pharmacy-closure-trend/
          58. Bridging the Gap: Maine’s New Law Empowers Pharmacies and Pharmacists to Improve Rural Access to Medications. The Buchanon. Updated November 25, 2025. Accsessed June 10, 2026. https://www.bipc.com/bridging-the-gap-maine%E2%80%99s-new-law-empowers-pharmacies-and-pharmacists-to-improve-rural-access-to-medications
          59. SP 105, LD 239: An Act to Allow Retail Pharmacies to Operate Remote Dispensing Sites in Rural Areas. Maine Legislature Bill Tracking. Accessed March 14, 2026. https://legislature.maine.gov/billtracker/#Paper/239?legislature=132
          60 NCPA Releases 2023 Digest Report. National Community Pharmacist Association. Updated October 15, 2023. Accessed March 15, 2026. https://ncpa.org/newsroom/news-releases/2023/10/15/ncpa-releases-2023-digest-report
          61. Board of Pharmacy: Subchapter 24.174.8 Pharmacies. Montana Secretary of State. Accessed March 14, 2026. https://rules.mt.gov/browse/collections/aec52c46-128e-4279-9068-8af5d5432d74/sections/536ba0ba-db35-4ecf-9de9-bc609928faba
          62. Connecticut Comprehensive Drug Laws. Sec. 20-576-19. Disclosure of times of operation of prescription department. Connecticut Department of Consumer Protection; May 2025. Accessed February 3, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          63. The Practice of Pharmacy Regulations, Title 20 - Professional and Occupational Licensing, Certification – Subtitle 20-576. The Office of Secretary of the State. Accessed February 3, 2026. https://eregulations.ct.gov/eRegsPortal/Browse/RCSA/Title_20Subtitle_20-576/
          64. Connecticut Comprehensive Drug Laws. Sec. 21a-262-1. Definitions. Connecticut Department of Consumer Protection; May 2025. Accessed February 3, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          65. Code of Federal Regulations. 21 CFR Part 1301 Security Requirements. National Archives and Records Administration. Updated February 3, 2026. Accessed February 3, 2026. https://www.ecfr.gov/current/title-21/chapter-II/part-1301/subject-group-ECFRa7ff8142033a7a2
          66. Connecticut Comprehensive Drug Laws. Sec. 21a-262-5. Licensed pharmacies. Connecticut Department of Consumer Protection; May 2025. Accessed February 3, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          67. N.J. Admin. Code § 13:39-5.8 - Minimum equipment and supplies; cleanliness. Cornell Legal Information Institute. Updated December 4, 2017. Accessed March 13, 2026. https://www.law.cornell.edu/regulations/new-jersey/N-J-A-C-13-39-5-8
          68. Pharmacy Personnel and Required References in the Pharmacy. New York State Education Department. Accessed March 13, 2026.
          https://www.op.nysed.gov/professions/pharmacist/frequently-asked-questions/pharmacy-personnel-and-required-references-in-the-pharmacy
          69. Stimulant Prescription Trends in the United States From 2012-2022. IQVIA. Updated August 31, 2023. Accessed March 13, 2026. https://www.deadiversion.usdoj.gov/drug_chem_info/stimulants/IQVIA_Report_on_Stimulant_Trends_from_2012-2022.pdf
          70. Understanding the Opioid Overdose Epidemic. Centers for Disease Control and Prevention. Updated June 9, 2025. Accessed March 13, 2026. https://www.cdc.gov/overdose-prevention/about/understanding-the-opioid-overdose-epidemic.html
          71. Opioid Dispensing Rate Maps. Centers for Disease Control and Prevention. Updated February 11, 2026. Accessed March 13, 2026. https://www.cdc.gov/overdose-prevention/data-research/facts-stats/opioid-dispensing-rate-maps.html
          72. Hareem A, Lee J, Stupans I, Park JS, Wang K. Benefits and barriers associated with e-prescribing in community pharmacy - A systematic review. Explor Res Clin Soc Pharm. Updated November 25, 2023. Accessed March 12, 2026. doi:10.1016/j.rcsop.2023.100375
          73. Vermont Approves E-Prescribing for Schedule II Drugs. Bloomberg Law. Updated September 14, 2015. Accessed February 5, 2026. https://news.bloomberglaw.com/health-law-and-business/vermont-approves-e-prescribing-for-schedule-ii-drugs
          74. NJ A1853. BillTrack 50. Updated January 12, 2026. Accessed February 5, 2026. https://www.billtrack50.com/billdetail/1668952#:~:text=A%20prescription%20issued%20by%20a,transmitted%20by%20electronic%20means%20under
          75. Letter to Practitioners Regarding Electronic Prescribing Mandate. New York State Department of Health. Updated November, 2015. Accessed February 5, 2026.
          https://www.health.ny.gov/professionals/narcotic/electronic_prescribing/docs/2015-11_epcs_practitioner_letter.pdf
          76. Electronic Prescribing Exceptions - Dispensing Clarification for Pharmacists. New York State Department of Health. Updated November, 2022. Accessed February 5, 2026. https://www.health.ny.gov/professionals/narcotic/electronic_prescribing/elec_pres_except_disp_clar_4_pharm.htm
          77. CMS EPCS Frequently Asked Questions. Center for Medicare and Medicaid Services. Updated March 25, 2025. Accessed February 5, 2026. https://www.cms.gov/files/document/epcs-frequently-asked-questions.pdf-3
          78. Electronic Prescribing (eRx) for Small Practices: 2025 Complete Guide. Proactive Chart. Updated November 16, 2025. Accessed March 10 , 2026. https://www.proactivechart.com/resources/electronic-prescribing-small-practice/
          79. Opioid Regulations: State by State Guide. American College of Emergency Physicians. Updated January 2021. Accessed March 13, 2026. https://www.acep.org/siteassets/sites/acep/media/by-medical-focus/opioids/opioid-guide-state-by-state.pdf
          80. Connecticut Comprehensive Drug Laws. Sec. 21a-254-4. Reporting. Connecticut Department of Consumer Protection; May 2025. Accessed February 3, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          81. Prescription Drug Monitoring Programs (PDMPs). Centers for Disease Control and Prevention. Updated May 7, 2024. Accessed March 13, 2026. https://www.cdc.gov/overdose-prevention/php/interventions/prescription-drug-monitoring-programs.html
          82. Title 902, Chapter 055, Regulation 015: Schedules of Controlled Substances. Kentucky General Assembly. Updated January 1, 2026. Accessed March 13, 2026. https://apps.legislature.ky.gov/law/kar/titles/902/055/015/
          83. Data Submission Guide for Dispensers: Michigan Automated Prescription System. Bamboo Health PMP AWARxE. Updated July 2024. Accessed April 9, 2026. https://www.michigan.gov/-/media/Project/Websites/lara/bpl/MAPS/Michigan-Data-Submission-Dispenser-Guide.pdf?rev=99cbbca54a464ff98ad67ad92a1b464b
          84. NJ Prescription Monitoring Program: Pharmacy Reporting Requirements. New Jersey Division of Consumer Affairs. Updated April 30, 2025. Accessed March 13, 2026. https://www.njconsumeraffairs.gov/pmp/Pages/reporting.aspx
          85. Theft/Loss Reporting. U.S. Drug Enforcement Administration. Accessed March 12, 2026. https://www.deadiversion.usdoj.gov/21cfr_reports/theft/theft-loss.html
          86. Theft or Loss Q&A. U.S. Drug Enforcement Administration. Accessed March 12, 2026. https://deadiversion.usdoj.gov/faq/theft-loss-faq.html
          87. Connecticut Comprehensive Drug Laws. Sec. 20-633e. Pharmacy and institutional pharmacy perpetual inventory of Schedule II controlled substances. Regulations. Connecticut Department of Consumer Protection; May 2025. Accessed February 3, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          88. BD Pyxis™ MedFlex Automated Dispensing Cabinets. Becton Dickinson. Accessed March 12, 2026. https://www.bd.com/en-us/products-and-solutions/products/product-families/pyxis-medflex
          89. XT Automated Dispensing Cabinet. Omnicell. Accessed March 12, 2026. https://www.omnicell.com/points-of-care/xt-automated-dispensing-cabinet/
          90. Connecticut Comprehensive Drug Laws. Sec. 21a-254(f). Designation of restricted drugs or substances by regulations. Records required by chapter. Electronic prescription drug monitoring program. Connecticut Department of Consumer Protection; May 2025. Accessed February 4, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          91. Code of Federal Regulations. 21 CFR Part 1304.11 Inventory requirements. National Archives and Records Administration. Accessed June 10, 2026. https://www.ecfr.gov/current/title-21/chapter-II/part-1304/subject-group-ECFR9944e94ba5f1eb0/section-1304.11
          92. Delate T, Kastendieck D. Assessment of the rates and characteristics of unclaimed prescriptions. J Am Pharm Assoc . Updated February 17, 2024. Accessed March 12, 2026. doi:10.1016/j.japh.2017.01.003
          93. Connecticut Comprehensive Drug Laws. Sec. 20-618. Repackaged drugs not considered misbranded. Connecticut Department of Consumer Protection; May 2025. Accessed February 4, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          94. Public Act No. 17-131: E-Prescribing for Controlled Substances. Connecticut General Assembly. Updated June 30, 2017. Accessed February 3, 2026. https://www.cga.ct.gov/2017/act/Pa/pdf/2017PA-00131-R00HB-07052-PA.PDF
          95. Connecticut Comprehensive Drug Laws. Sec. 21a-254. Designation of restricted drugs or substances by regulations. Records required by chapter. Electronic prescription drug monitoring program(h). Connecticut Department of Consumer Protection; May 2025. Accessed February 3, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          96. What are the record keeping requirements for pharmacists/pharmacies for Electronic Prescribing of Controlled Substances? Connecticut Department of Consumer Protection. Updated April 17, 2025. Accessed February 4, 2026.
          https://portal.ct.gov/dcp/knowledge-base/articles/drug-control/providers/electronic-prescribing-faqs/pharmacist-record-keeping-requirements-for-ecps?language=en_US
          97. Connecticut Comprehensive Drug Laws. Sec. 20-635-5. Records. Connecticut Department of Consumer Protection; May 2025. Accessed February 4, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          98. Connecticut Comprehensive Drug Laws. Sec. 20-633k-6. Record Keeping. Connecticut Department of Consumer Protection; May 2025. Accessed February 4, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          99. Virginia Law 18VAC110-20-240 Manner of maintaining records, prescriptions, inventory records. Legislative Information System. Accessed April 25, 2026. https://law.lis.virginia.gov/admincode/title18/agency110/chapter20/section240/
          100. 11.04.10 Colorado Administrative Code 3 CCR 719-1-11.00.00 - Records and Recordkeeping. Cornell Legal Information Institute. Accessed April 25, 2026. https://www.law.cornell.edu/regulations/colorado/3-CCR-719-1-11.00.00
          101. 21 eCFR 1311.305 Recordkeeping. National Archives Code of Federal Regulations. Accessed March 13, 2026. https://www.ecfr.gov/current/title-21/chapter-II/part-1311/subpart-C/section-1311.305
          102. 21 eCFR 1311.60 Recordkeeping. National Archives Code of Federal Regulations. Accessed March 13, 2026. https://www.ecfr.gov/current/title-21/chapter-II/part-1311/subpart-B/section-1311.60
          103. Code of Federal Regulations. 42 CFR 423.505 Contract Provisions. National Archives and Records Administration. Updated February 3, 2026. Accessed February 4, 2026. https://www.ecfr.gov/current/title-42/chapter-IV/subchapter-B/part-423/subpart-K/section-423.505
          104. Recommendations / Statements. National Coordinating Council for Medication Error Reporting and Prevention. Updated July 10, 2025. Accessed March 11, 2026. https://www.nccmerp.org/recommendations-statements
          105. Connecticut Comprehensive Drug Laws. Sec. 20-635. Prescription error reporting. Connecticut Department of Consumer Protection; May 2025. Accessed February 4, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          106. Statement Opposing the Criminalization of Errors in Healthcare. National Coordinating Council for Medication Error Reporting and Prevention. Updated April 4, 2022. Accessed March 12, 2026. https://www.nccmerp.org/statement-opposing-criminalization-errors-healthcare
          107. MedWatch: The FDA Safety Information and Adverse Event Reporting Program. U.S. Food & Drug Administration. Accessed February 4, 2026. https://www.fda.gov/safety/medwatch-fda-safety-information-and-adverse-event-reporting-program
          108. Poison Prevention Packaging Act Business Guidance. United States
          Consumer Product Safety Commission. Accessed February 4, 2026.
          https://www.cpsc.gov/Business--Manufacturing/Business-Education/Business-Guidance/PPPA
          109. Connecticut Comprehensive Drug Laws. Sec. 21a-65(b). Sale of hypodermic needles and syringes restricted. Connecticut Department of Consumer Protection; May 2025. Accessed February 4, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          110. Syringe Access. New Jersey Harm Reduction Coalition. Accessed February 4, 2026. https://njharmreduction.org/syringe-access/
          111. Expanded Syringe Access Program (ESAP): Overview of the Law and Regulations. New York State Department of Health. Updated, April 2024. Accessed February 4, 2026. https://www.health.ny.gov/diseases/aids/consumers/prevention/needles_syringes/esap/overview.htm
          112. Nonprescription Sale of Syringes in Pharmacies. California Department of Public Health. Accessed March 11, 2026. https://www.cdph.ca.gov/Programs/CID/DOA/pages/OA_prev_npss.aspx
          113. CT Syringe Services Program (SSP). Connecticut Public Health. Updated August 2024. Accessed March 11, 2026. https://portal.ct.gov/-/media/departments-and-agencies/dph/aids--chronic-diseases/prevention/ct-syringe-services-program_8_6_2024.pdf
          114. Get Syringes: Frequently Asked Questions. New Jersey Harm Reduction Coalition. June 10, 2026. https://njharmreduction.org/get-syringes/
          115. H.R.5835 - Omnibus Budget Reconciliation Act of 1990. Congress.gov. Updated November 5, 1990. Accessed February 5, 2026. https://www.congress.gov/bill/101st-congress/house-bill/5835/text
          116. OBRA ’90 at Sweet Sixteen: A Retrospective Review. U.S. Pharmacist. Updated March 20, 2008. Accessed February 5, 2026. https://www.uspharmacist.com/article/obra-90-at-sweet-sixteen-a-retrospective-review
          117. Pharmacy Information. Connecticut Department of Social Services. Accessed February 5, 2026. https://www.ctdssmap.com/ctportal/Pharmacy-Information
          118. Pharmacist-Prescribed Contraceptives. Guttmacher. Updated January 30, 2026. Accessed March 11, 2026. https://www.guttmacher.org/state-policy/explore/pharmacist-prescribed-contraceptives
          119. Connecticut Comprehensive Drug Laws. Sec. 20-633k. Prescribing of emergency and hormonal contraceptives by licensed pharmacists. Training. Patient screening. Disclosures and notices. Assistance by pharmacy technicians. Recordkeeping. Connecticut Department of Consumer Protection; May 2025. Accessed February 4, 2026. portal.ct.gov/dcp/-/media/dcp/pdf/drug_control_pdf/lawbook.pdf
          120. U.S. Medical Eligibility Criteria for Contraceptive Use, 2024. Centers for Disease Control and Prevention. Accessed March 11, 2026. https://www.cdc.gov/contraception/hcp/usmec/index.html

          PATIENT SAFETY: Prescription for Precision: Improving Pharmacy Typing Accuracy

          Learning Objectives

          After completing this continuing education activity, pharmacists and pharmacy technicians will be able to

          1. EXPLAIN the relationship between typing accuracy, workflow efficiency, and medication safety in pharmacy practice
          2. DEMONSTRATE techniques that improve the accurate entry of prescription information, including drug names, SIG codes, patient demographics, and numeric data
          3. IDENTIFY cognitive, environmental, and ergonomic factors that contribute to pharmacy data-entry errors
          4. APPLY deliberate practice and error-prevention strategies to enhance typing performance and reduce transcription-related medication errors

            cartoon of a person standing at a computer and typing at the keyboard

             Release Date

            Release Date: July 20, 2026

            Expiration Date: July 20, 2029

            Course Fee

            $7 Pharmacist

            $4 Pharmacy Technician

            There is no funding for this CE.

            ACPE UANs

            Pharmacist: 0009-0000-26-040-H05-P

            Pharmacy Technician: 0009-0000-26-040-H05-T

            Session Codes

            Pharmacist: 26YC40-KTF31

            Pharmacy Technician: 26YC40-FKT13

            Accreditation Hours

            2.0 hours of CE

            Accreditation Statements

            The University of Connecticut School of Pharmacy and Pharmaceutical Sciences is accredited by the Accreditation Council for Pharmacy Education as a provider of continuing pharmacy education.  Statements of credit for the online activity ACPE UAN 0009-0000-26-040-H05-P/T will be awarded when the post test and evaluation have been completed and passed with a 70% or better. Your CE credits will be uploaded to your CPE monitor profile within 2 weeks of completion of the program.


            Disclosure of Discussions of Off-label and Investigational Drug Use

            The material presented here does not necessarily reflect the views of The University of Connecticut School of Pharmacy and Pharmaceutical Sciences or its co-sponsor affiliates. These materials may discuss uses and dosages for therapeutic products, processes, procedures and inferred diagnoses that have not been approved by the United States Food and Drug Administration. A qualified health care professional should be consulted before using any therapeutic product discussed. All readers and continuing education participants should verify all information and data before treating patients or employing any therapies described in this continuing education activity.

            Faculty

            Sandra Casinghino, MS

            Graduate of the UConn Medical Writing Certificate Program

            Storrs, CT


            Dylan DeCandia, PharmD, RPh.

            Manager, Franklin’s Pharmacy

            Ho-Hokus, NJ


            Gabrielle Ruggiero, PharmD

            Pharmacist, Mercy Medical Center

            Springfield, MA


            Kayla Gibson, PharmD, PhC, BCPS

            Ambulatory Care Pharmacy Specialist II

            Hartford Hospital

            Middletown, CT


            Maria S. Charbonneau, PharmD.

            Clinical Assistant Professor of Pharmacy Practice

            College of Pharmacy and Health Sciences

            Western New England University

            Springfield, MA

            Faculty Disclosure

            In accordance with the Accreditation Council for Pharmacy Education (ACPE) Criteria for Quality and Interpretive Guidelines, The University of Connecticut School of Pharmacy and Pharmaceutical Sciences requires that faculty disclose any relationship that the faculty may have with commercial entities whose products or services may be mentioned in the activity.

            Sandra Casinghino, Dylan DeCandia, Gabrielle Ruggiero, Kayla Gibson, and Maria S. Charbonneau have no relationships with ineligible companies.


            ABSTRACT

            Accurate data entry is a critical pharmacy technician skill that directly affects workflow efficiency, prescription processing, and patient safety. Typing and transcription errors involving medication names, numeric values, patient information, and prescription directions can contribute to dispensing delays, workflow inefficiencies, and medication errors. This continuing education activity. reviews practical strategies pharmacy technicians can use to improve typing proficiency and data-entry accuracy in pharmacy practice. Topics include prioritizing accuracy over speed, developing touch-typing skills, improving numeric keypad proficiency, mastering common drug names and SIG codes, and using deliberate practice techniques to strengthen performance. Additional discussion focuses on cognitive control, task switching, simulation-based training, deliberate error review, ergonomic principles, and methods for improving pharmacy-specific reading speed. The activity also examines how interruptions, distractions, and environmental factors can affect typing performance and provides evidence-based recommendations for reducing error risk. By combining structured practice, targeted feedback, pharmacy-specific skill development, and ergonomic optimization, pharmacy technicians can enhance both efficiency and accuracy during prescription processing. Strengthening these competencies supports safer medication use, reduces the need for rework and error correction, and contributes to improved patient care in community and health-system pharmacy settings.

            CONTENT

            Content

            INTRODUCTION

            Jake works as a pharmacy technician. He prides himself on being the fastest typist on his team and is confident that he will catch his mistakes upon proofreading. He doesn’t understand why the pharmacist always tells Laurie to take over for him when it gets busy.


            Brenda is a new pharmacy technician who incorrectly transcribed a prescription as prednisolone. The prescription is for a patient who has severe liver disease, and the doctor prescribed prednisolone to treat an infection. Patients with liver disease usually cannot metabolize prednisone, and the medication would not be effective.1 Luckily, Brenda’s coworker caught the error before the patient received the drug. Retyping labels and correcting the insurance submission delayed delivery of the prescription to the patient. Many drugs have similar names, which are easy to confuse, and pharmacy technicians must stay focused on accuracy.


            Both Jake and Brenda can improve their job performance by honing their skills to type, transcribe, and enter information accurately. Pharmacy technicians should focus on drug name accuracy, and correct doses, units, and quantities. They should also focus on providing high quality patient instructions and entering the correct patient data including medical history and drug allergies, health conditions, and other medications that the patient takes.2,3


            PAUSE AND PONDER: When it’s your turn to occupy the data entry hotseat, how do you feel? What is your “net words per minute”?


            PRIORITIZE ACCURACY OVER SPEED

            Focusing only on speed as a measure of success is flawed thinking. Gross words per minute (WPM) is not a true indication of mastery. Experts use net WPM to account for typing errors to give an overall picture of speed plus accuracy.4 In the example above, Jake’s gross WPM is 55 but he makes 10 mistakes per minute. This results in a net of 45 correct WPM. Laurie types at only 50 WPM (gross) but makes only one error every two minutes. Her net WPM of correct words is 49.5. Even though Jake is a good proofreader and catches most of his errors, it takes time to locate the errors and retype them, further increasing the time to complete the job. Laurie’s efficiency is greater than Jake’s and justifies the pharmacist’s decision to call on Laurie when the pharmacy is busy.

            cartoon of a computer keyboard with two hands poised over, pointer fingers extended

            Fast, error prone typing takes longer than slower-paced error-free typing. Every error requires extra time to complete the task. Technicians must locate each error, delete the wrong letters, and then retype. Pharmacy personnel may then need to repeat multiple tasks: printing labels, writing SIGs, dispensing medications, and resubmitting claims to insurance companies. If personnel do not discover errors until further down the line, the consequences may be more damaging, including patient harm and required reporting to regulatory authorities.


            Here are some suggestions for improving typing accuracy 5,6:

            • Practice, practice, practice.
            • Mix it up. Open any book and type a page, then proofread. Move on to a pharmacy-related textbook.
            • Track your progress.
            • Use online tools
              • Typing.com, which is a general typing improvement website but has advanced lessons including common medical terms
              • The Practice Test (https://thepracticetest.com/typing/), which contains pharmacy-specific typing and data entry lessons, drills, and tests. It also prompts you to slow down if you type like Jake does!
              • You can find additional online typing tools in the Learn True Touch Typing section below.


            Once technicians consistently achieve high accuracy (greater than 95% accurate), they can work to gradually increase WPM. They can periodically retest and participate in additional practice exercises, when needed, to help maintain a high level of competency.


            Learn True Touch Typing

            Imagine: It’s January 2nd. Phones are ringing off the hook because the pharmacy was closed the day before. The pickup line is already five patients deep and each patient’s deductible has reset for the year. There’s a knock at the door. The wholesaler delivery is already here, and the pharmacist needs to verify the narcotics in the shipment. Oh, and the regional manager only authorized enough hours for one pharmacist and one technician for the full day. Wouldn’t it be nice if there were eight more people behind the counter with you to help?


            Now, imagine another situation: 10 employees are scheduled, but only six are doing their job efficiently. The other four just stand in each corner and put away a bottle of medication every few minutes. This analogy can also apply to your typing. Whether you peck the buttons like a chicken with just two fingers or only use six of your 10 fingers to type, you’re not operating at maximum efficiency. True touch typing, also referred to as just “touch typing,” involves using all 10 fingers to type, thus increasing efficiency and speed.7 Think about how much time you spend tilting your head down to the keyboard to look for the letter you need to type, back up to the computer monitor to make sure the correct letter was selected, back down to the keyboard for the next letter, and so on.


            Alternatively, even if you’re using more than two fingers to type, how often do you make mistakes that take time for correction? Learning true touch typing will be a boon for all levels of typists.

            No special equipment is needed: just your standard work-issued QWERTY keyboard (see the SIDEBAR) and all ten of your fingers. An ergonomic keyboard may offer some comfort. If you currently suffer from carpal tunnel or general wrist/hand strain, the act of keeping your wrists in a neutral position and using each finger equally with true typing may provide even better relief.7 Resources on learning or even improving your typing technique are available online at no charge. Everyone has a different learning level and current level of accuracy. Consider visiting any of the following websites to start:


            SIDEBAR: Practice Makes Permanent: QWERTY Can Teach Us About Typing Accuracy8,9


            Christopher Latham Sholes, who helped create one of the first commercially successful typewriters, developed the QWERTY layout in the 1870s. It’s named for the first six letters in the upper-left row of the keyboard. A common myth is that Sholes designed QWERTY to make people type slowly. The reality is more nuanced. Early typewriters used mechanical arms (called typebars) that could jam if the typist struck neighboring keys in rapid succession. Sholes rearranged letters to reduce the likelihood of mechanical interference among commonly used letter combinations. The goal was to improve the machine's reliability.


            When the Remington company marketed Sholes's typewriter, users widely adopted the QWERTY arrangement. By the time alternative layouts were introduced in the 1930s, millions of people had already learned QWERTY. The cost and inconvenience of retraining typists outweighed any potential advantages of switching.


            Today, QWERTY remains the dominant keyboard layout worldwide, despite repeated claims that other layouts may be faster or more ergonomic. Research generally shows that while alternative layouts may have benefits, experienced QWERTY typists can achieve very high speeds and accuracy because of years of practice and muscle memory.


            The QWERTY keyboard’s enduring success illustrates an important principle of learning: repeated actions become automatic. Just as experienced typists no longer think consciously about the location of individual keys, pharmacy technicians can develop automatic accuracy through deliberate, correct practice. As typing instructors often say, "Practice makes permanent."


            Once you find a website or two that meshes well with your learning style, the next step is to simply practice! Touch typing involves building muscle memory. Did you learn how to ride a bike proficiently in one day? If you did, you may also already be a good typist. For most of us, removing the training wheels and learning to balance on a bike took multiple evenings and weekends of practice. Noticeable improvement in typing proficiency can develop in as few as two weeks of practice.10


            Once you learned how to balance on the bike, did you start speeding down big hills or did you stick to the flat neighborhood streets? True typing values accuracy over speed. Trying to type 90 words per minute without proper finger placement is like attempting to bike down big, steep hills as you keep falling off your bike. You may land at your destination at the same time as your friend who took it slow on the flat neighborhood rows and didn’t fall. Then again, you may not.


            Finger placement is key for accuracy, and it all starts with the home row. Unless you’re working on a very old and well-used keyboard, you might have noticed the F and J buttons have raised notches on the bottom of the buttons. These are called “tactile home position indicators” and they serve as physical guides to keep your hands oriented correctly.11 When you’re getting ready to type, start with your left index finger on the F button and your right index finger on the J. From there, you might find your fingers naturally rest on the surrounding letters with your thumbs oriented towards the spacebar. Left middle finger goes to D, left ring finger to S, and left pinky to A.12 Mirror the placement for your right hand. Now the whole row of letters, save for G and H, have a finger resting on them. This finger placement is ideal for stretching your reach as little as possible to access each possible letter. Save your pinkies for the Caps Lock, Shift, and Enter buttons. With proper hand placement, you are now prepared to run some typing drills! Remember, practice makes perfect. Don’t be discouraged if your starting word count per minute is 25. Keep at it and soon enough you can be three times as proficient. Next, let’s discuss the specific typing needed in the pharmacy.


            Practice Pharmacy-Specific Typing

            Let there be a signature! Or, “let it be labeled.” This is what the Latin word signetur means.7 Often shortened to just “SIG,” this is the information that the pharmacy’s typist transcribes from the original prescription to the prescription label for the directions for use. Pharmacy SIGs are a language of their own, often shortened to various acronyms. There is plenty to learn, but never fear: with enough practice, you’ll catch onto the lingo. Before you buy a dictionary, let’s first decode a SIG. Every valid SIG will contain three “hows”: how to take the medication; how much to take of the medication; and how often to take the medication. A fourth how is included sometimes but isn’t always necessary: how long to take the medication.


            Let’s focus on how to take the medication first. “Take” is often followed by “by mouth” after the quantity is listed. Medications can also be inhaled, injected, applied topically, inserted vaginally, or dropped into the eyes. The amount of medication to be taken follows the first verb of the SIG, which tells the patient how the medication is to be consumed. After the amount of medication is known, the action is completed with the route of administration. Table 1 lists common routes of administration and their SIG codes. For routes of administration that don’t translate directly in English, the abbreviation is often in Latin.


            Table 1. Common Routes of Administration and Their SIGs7,10

            SIG Definition Latin (if applicable)
            AAA Apply to affected area
            AD* Right ear auris dextra
            AS* Left ear auris sinistra
            AU* Each ear, both ears auris utraque
            BUCC Buccal, inside the cheek bucca
            IM Intramuscular, into the muscle
            INH Inhalation, inhale
            INJ Injection, to be injected
            IV Intravenous, into the vein
            OD* Right eye oculus dexter
            OS* Left eye oculus sinister
            OU Each eye, both eyes oculus uterque
            PO By mouth per os
            PR Per rectum, by rectum
            SC, SQ, SUB Q* Subcutaneous, under the skin
            *For many years, the Institute of Safe Medication Practices (ISMP) has published a list of DO NOT USE SIGs because they are associated with errors. Regardless, clinicians continue to use them and they are in red text for that reason. Find the complete list here: https://www.ismp.org/sites/default/files/attachments/2017-11/Error%20Prone%20Abbreviations%202015.pdf


            The next part of the SIG is how much of the medication to take. This is a numeric value accompanied by the type of medication being prescribed. When an ointment or lotion is to be applied topically, sometimes both the amount to be applied and the type of medication itself is omitted from the SIG. “Apply topically to affected area” followed by the frequency of application is often sufficient. Table 2 lists some additional abbreviations that pharmacy personnel need to know.


            Table 2. Additional Abbreviations 7,10

            SIG Definition Latin (if applicable)
            AMP Ampule
            CAP Capsule
            CR Cream
            GTT Drop gutta
            LOT Lotion
            MDI Metered dose inhaler
            NEB Nebulizer
            PKT Packet
            SUSP Suspension
            TAB Tablet
            TROCH Troche, lozenge trochiscus
            UNG Ointment unguentum


            The final part of the SIG is how often to take the medication (see Table 3). The abbreviation “Q” is popular, but never alone. It’s always followed by further instruction. “QHS” would be every night. “Q4h” would be every four hours. How long to take the medication may be included if it’s not a maintenance medication. “TAT” or “Until all gone” is common for antibiotics, as this encourages the patient to finish their prescription even if they’re feeling better mid-course.


            Table 3. Common Frequencies and Their SIGs7,10

            SIG Definition Latin (if applicable)
            AM Morning, in the morning ante meridiem
            BID Twice daily, two times daily bis in die
            H or hr Hour hora
            HS* At bedtime hora somni
            PM Evening, in the evening post meridiem
            PRN As needed pro re nata
            Q Each, every quaque
            QID Four times daily quater in die
            QAD or QOD* Every other day quaque alternis die
            TAT Until all taken
            TID Three times a day ter in die
            *For many years, the Institute of Safe Medication Practices (ISMP) has published a list of DO NOT USE SIGs because they are associated with errors. Regardless, clinciians continue to use them and they are in red text for that reason. Find the complete list here: https://www.ismp.org/sites/default/files/attachments/2017-11/Error%20Prone%20Abbreviations%202015.pdf


            Sometimes the prescriber includes further instruction concerning the time of day the medication should be taken or other conditions that need to be met when the medication is taken. Table 4 describes these.


            Table 4. Abbreviations for Consumption Conditions10

            SIG Definition Latin (if applicable)
            ac Before meals ante cibum
            c With cum
            Pc or pp Postprandial, After meals post cibum
            s Without sine


            Beyond the label you’ll come across some other common abbreviations in the pharmacy. “Dispense as written” is abbreviated as “DAW.” This means that the medication needs to be dispensed exactly as prescribed without any substitution for brand or generic when applicable. In the Notes to Pharmacy section, a provider may write, “d/c amlodipine.” This means amlodipine is to be discontinued. Sometimes the prescriber omits the forward slash.


            The long 11 or 12-digit code on the medication bottles is the “National Drug Code” or “NDC.”7 This is a unique set of numbers assigned to each medication manufacturer, the medication itself, the strength, and formulation of the medication.


            Transcribing SIGs is serious business. If the wrong information is entered from the get-go, the whole prescription could be misfilled.11 Study these acronyms and SIG formulas often. Soon enough, you’ll have mastered another language.


            Build Numeric Keypad Skills 

            Numeric data entry is a significant source of medication errors.13-15 It is easy to leave a number out, enter a wrong number, swap the number order, or add an extra number. 16 Any of these mistakes could have catastrophic consequences for the patient.


            Using the numeric keypad instead of the main keyboard number row can help lower error rates, especially when under time constraints. 16 When you have the choice, use a numeric keypad with a calculator layout (1-2-3 on the bottom), which is faster and more accurate than a keypad with a telephone layout (1-2-3 on the top).17 Building your skill and confidence with the numeric keypad will help you enter medication quantities, NDC numbers, day supplies, dates of birth (DOBs), and insurance IDs with accuracy and speed.


            It’s (mostly) all in the fingers! Single-finger typing is faster and more accurate than multi-finger typing for numeric data entry.18 A PRO TIP is to use your dominant hand’s index finger on the numeric keypad – it’s the speediest and most accurate way to enter numbers!19,20 And here’s a suggestion for left-handers. Numeric keypads are always located on the right, making typing with your left index finger very awkward. Some lefties learn to be ambidextrous. Others use a detachable keypad on the left side of the keyboard.


            Practice typing quickly when you are not under time constraints to increase speed and accuracy over time.21 Enter mock prescriptions, dates of birth, patient phone numbers, and day supply calculations as quickly as you can for practice. Repetition is key! Drill specific number sequences that you often use, like certain NDC numbers.22 When you do this, your brain recognizes the number sequence, and your finger follows the movement pattern easily and quickly. With repetition, your brain and finger muscle memory may retain this number sequence for months!


            “Memory loading” can help increase speed while maintaining accuracy on the numeric keypad, too. This is when you type the previous number from memory while viewing the next number in the sequence.23 Let’s see memory loading in practice! You need to type 48372619 into the system. Instead of looking back and forth at each individual number, you might briefly memorize 48-37 and type it while looking ahead to the next part – 26-19. This reduces interruptions in visual focus and allows for faster, smoother data entry.


            “Chunking” (which sounds like a silly word but is the exact term that psychologists use for this practice) is another way to increase speed on the numeric keypad.23 Separating long strings of numbers into two- or three-digit groups can facilitate faster data entry. For example, if you needed to enter the sequence 4958928495 into the system, you could break it into groups such as 49-58-92-84-95.

            Here’s another PRO TIP: Practice typing quickly, drill commonly used number sequences, use the memory loading technique, and chunk long strings into two- or three-digit groups!


            Be aware that digits 3, 8, and 9 tend to be the highest-risk keys on the numeric keypad (probably because they tend to be used less frequently in prescriptions).16,17 Knowing this can help you avoid mistakes when you encounter them! Additionally, be aware that “out by 10” errors – miskeying a zero or decimal point - are common and potentially very dangerous.24. In fact, this is the most clinically dangerous numeric entry error there is. Stay vigilant.


            Producing medication labels may be one of the most error-prone pharmacy tasks due to numeric keypad errors and rushing under time pressure.25. Consider implementing the following strategies in your pharmacy to reduce the risk of errors 23,26-28:

            • Require a second verification for all numeric fields
            • Discourage rushing during numeric data entry
            • Use barcode scanning as the primary entry method if it’s available
              • Use manual keypad entry only as a backup
            • Include a confirmation step after numeric fields are entered
            • Standardize field formatting
              • Present NDCs, insurance IDs, and other long numeric strings in chunks when possible to align with natural cognitive processing


            LEARN COMMON DRUG NAMES IN CHUNKS

            With thousands upon thousands of medications in the world, learning and accurately typing their names are daunting tasks for even the most fearless pharmacy technicians! Many drug names are similar, and drug classes often share suffixes (a final segment added at the end of a word to modify the word's meaning). Biologics come with their own naming conventions. In addition, medicines have both generic and brand names. The limitless number of names to learn can contribute to inaccuracies when typing and transcribing prescriptions. Mixing up drug names is a serious problem that may harm patients, require repeating parts of the pharmacy workflow (decreasing efficiency), and necessitate reporting to regulatory authorities.3 Breaking the task down into manageable steps may be useful. This section offers potentially helpful approaches.


            Understand the classes of medicines

            Classes of drugs often share word components and often have a common suffix. Examples of drugs with common suffixes include: -pril (ACE inhibitors) such as lisinopril, enalapril; -olol (beta blockers) such as metoprolol, propranolol; -cillin (antibiotics) such as amoxicillin, penicillin; -statin (statins) such as atorvastatin, simvastatin. The Top 200 Drugs Study Guide contains an extensive list of examples.29


            Many biologics follow naming conventions and can also share common suffixes. Examples include: -ase (enzymes), -cel (cell therapies), and -rsen (antisense oligonucleotides).30


            Monoclonal antibody and gene therapy names are even more complex but convey a lot of valuable information. Historically, monoclonal antibody names consist of a prefix (a segment added at the beginning of the word to help with pronounceability), then components to identify the antibody target and the species from which the antibody was derived, followed by the suffix “mab” (monoclonal antibody).30 In 2021 the World Health Organization International Nonproprietary Names Programme retired the universal -mab suffix for new monoclonal antibodies and replaced it with four new stems.31 The change was made because the number of antibodies had become so large that the old system was running out of distinguishable names.31 Table 5 lists the new names and their meanings.


            Table 5. New INN Monoclonal Antibody Nomenclature Scheme31

            Stem Meaning
            -tug Unmodified monospecific immunoglobulins
            -bart Engineered ("artificial") monospecific immunoglobulins
            -mig Bi- or multispecific immunoglobulins
            -ment Antibody fragments lacking an Fc region


            Gene therapy names consist of two words. The first word corresponds to the gene (being replaced or corrected) and the second word corresponds to the vector (the backbone of the gene therapy product). Components also include prefixes for uniqueness, elements to denote the pharmacology class, and the type of viral vector.32


            Breaking it Down – the Process

            From the few examples given, one can appreciate the enormity of the task of mastering the spelling and error-free typing of even a fraction of the drugs and biologics that exist. Here are some suggestions for breaking the task down29,30,33-35:

            • Work from the list of the Top 200 Drugs and study materials available to pharmacy technicians.
            • Focus on one drug class at a time
            • Set reasonable goals; for example, practice typing 10 names per day for 20 days
            • Proofread carefully for correct spelling; remember that accuracy is key
            • Focus on the whole name, instead of the order of the individual letters, to increase the chance of recognizing misspelled names
            • Once accuracy is high, purposefully increase typing speed
            • For more advanced practice, use lists of sound-alike drug names


            Practice, Practice, Practice

            After initial success in mastering the Top 200 drug list, and lists of sound-alike drug names, technicians can—and must—continue to practice to keep their typing and spelling skills sharp. Technicians can apply many of the same principles they used for increasing the accuracy of typing drug names to increasing the accuracy of other pharmacy tasks, such as typing common SIG codes and common insurance terms.


            PAUSE AND PONDER: After practicing your typing, you finally believe you are comfortable at the computer in your pharmacy. You log in and begin your first new patient data entry. First name? C-H-R-I-S-T-O.... *the pharmacist calls your name* ... P-H-E.... *pharmacy call on line one* ...R *another patient appears at the counter yelling for help*. Too many things are happening at once! Who do you help first? Do you continue your entry? What can you do to prepare in advance for the future?


            Simulate Real Pharmacy Conditions

            Learning typing skills from the comfort of home is a great place to begin, but it may not prepare a pharmacy technician for the hustle-and-bustle of everyday pharmacy life. Pharmacy is a dynamic environment; technicians constantly answer phone calls, triage patients, count prescriptions, and complete many other exhausting responsibilities.


            To prepare for typing during busy pharmacy hours, technicians can use simulated pharmacy environments to learn cognitive control techniques (mental processes that allow individuals to plan, focus, remember, and juggle multiple tasks effectively). Cognitive control consists of two perspectives, called cognitive stability and cognitive flexibility, that can help anyone improve their adaptive behavior and handle overwhelming environments.36 Technicians must understand each cognitive perspective and learn which predominates for them to create the optimal pharmacy simulation..


            Generally, cognitive stability helps block unimportant background noise to prevent distraction, whereas cognitive flexibility helps switch between tasks swiftly and accurately. However, true cognitive control requires a balance between both. For example, pharmacy technician Annie’s cognitive stability is strong but she may accidentally ignore a patient during data entry; conversely, Paul’s cognitive flexibility dominates but he is consistently distracted by other triggers, potentially leading to medication errors.36


            For overly stable technicians like Annie, task switching techniques can improve flexibility. Task switching refers to the ability of an individual to transition between tasks in changing environments.37 Although most often seen in people with attention deficit disorder, task or decision paralysis can inhibit individuals from completing tasks if they become fixated on one task or find themselves overwhelmed with responsibilities.38 People with these characteristics will benefit the most from simulations that refine task switching behaviors.


            For technicians trying to improve task switching competency, a PRO TIP is timing how long it takes to enter a fake prescription correctly, then gradually decreasing the time intervals during practice. Over time, this practice can improve task pacing to prepare for moving swiftly in a busy pharmacy. After the timer ends, technicians should halt their task and switch focus entirely on a new task or typing exercise. Task switching proficiency also helps prevent multitasking while typing, which is associated with increased prescription errors and results in more time spent per task.39


            After achieving success with beginner timer simulations, technicians can increase the task’s difficulty. Technicians can shorten the timer, make it louder and more annoying, or work with fake patient situations. To further simulate the pharmacy experience, technicians can address the fake patient while finishing up typing tasks:

            • “Hold on Mrs. Smith; I’ll be at the register in one minute.”
            • “Mr. Brown, how are you today?”
            • “Crazy weather we had recently, hopefully the rain isn’t ruining your week!”

            In addition to improving cognitive stability, adding these quips to the simulation will help improve patient experiences if applied to the real world. Researchers believe that these non-medical discussions can improve patient perceptions of medical interaction. By adding them to the simulation, pharmacy technicians learn to cultivate an elevated pharmacy experience for patients, while improving typing task switching.40


            On the other end of the spectrum, overly flexible technicians like Paul must learn to avoid distractions. Researchers reviewed 51 studies that indicated pharmacists and technicians experience up to 20 interruptions per hour.41 With frequent interruptions, pharmacy technicians must maintain focus to prevent medication errors. It may be difficult to create a natural, noisy environment at home, so technicians can practice in busy locations such as coffee shops, diners, or other locations to simulate typing with distractions. (Just be sure to use information that’s been de-identified or fake, if you’re outside the pharmacy!) Technicians can integrate skills needed to master typing in a pharmacy setting, such as reading pharmacy specific documentation that includes drug names, SIG codes, and other medical terminology.


            Outside of creating a mock pharmacy environment, some online computer software mimics prescriptions and patient interactions. Major companies including Redbull, Johnson & Johnson, and Walmart use popular online simulator called The Forage (find it here: https://careerhub.umt.edu/resources/forage/) for jobs across all fields.42 For pharmacy technicians, The Forage created a simulator that delivers a free, fast-paced retail pharmacy re-creation that even provides a certificate after completion.43 Other companies designed services such as MyDispense or Pharmacy Simulator for pharmacists, but offer customizable options to decrease complexity if needed.44 Any of these software programs can teach technicians to type in pharmacy specific scenarios.


            USE DELIBERATE ERROR REVIEW

            For some people, certain typing errors occur repeatedly. These errors may involve medication names, SIG codes, quantities, days' supply calculations, or patient information. Rather than simply correcting mistakes as they occur, technicians can improve accuracy by using a deliberate error review process.


            Deliberate error review involves identifying recurring mistakes, tracking them, and practicing the skills needed to prevent them. This approach is based on the principle that targeted practice is often more effective than general repetition. By focusing on specific weaknesses, technicians can develop greater accuracy and confidence when entering prescription information.


            A simple method is to maintain a personal list of common errors. The list might include frequently misspelled drug names, SIG instructions that are often entered incorrectly, confusing abbreviations, or days' supply calculations that have required correction in the past. For example, a technician who repeatedly misspells “hydroxyzine” or confuses it with “hydralazine” can devote extra attention to distinguishing these medications; she might remind herself to “look beyond the H-Y-D.” Similarly, a technician who frequently enters incorrect days' supply values can review calculation procedures and practice with sample prescriptions.


            Periodic review of this error list helps reinforce correct habits. Some technicians find it useful to create flashcards, practice typing challenging medication names, or review examples during downtime.


            Learning to type medication names accurately is similar to learning a difficult passage on the piano. Many beginning pianists make the mistake of practicing a piece at full speed and simply repeating it whenever they make an error. Unfortunately, repetition can strengthen the memory of the mistake and the memory of the incorrect notes. Piano teachers often recommend slowing down, playing the passage correctly several times in a row, and gradually increasing speed only after accuracy becomes automatic. Technicians can approach challenging medication names the same way. If a technician repeatedly misspells a medication name, slowly typing it correctly multiple times can help establish the correct spelling pattern. Speed should increase only after accuracy is consistent. This deliberate practice helps replace incorrect habits with correct spellings and reduces future typing errors. A good way to remember this is that practice does not necessarily make perfect — practice makes permanent.


            Others may benefit from discussing recurring errors with a supervisor or experienced colleague who can suggest strategies for improvement. The goal of deliberate error review is not to dwell on mistakes but to learn from them. Consistently examining and addressing recurring errors can improve data-entry accuracy, reduce the need for corrections, and contribute to medication safety. Over time, technicians who actively monitor their own performance often become faster and more accurate because they have eliminated many of the errors that previously interrupted their workflow.


            Improve Ergonomics

            An ergonomically designed workspace (an environment designed to be comfortable, efficient, and safe for humans to use) maximizes typing efficiency, reduces fatigue, and helps to prevent long-term overuse injuries. Chairs, desks, keyboards, monitors, and more can be optimized to promote a neutral body position, where joints are held in their natural alignment. According to the Occupational Safety and Health Administration (OSHA), this looks like45

            • Hands, wrists, and forearms aligned and nearly parallel to the floor
            • Head and torso aligned and facing forward
            • Shoulders relaxed, without needing to scrunch up or hunch forward
            • Elbows bent at a 90-to-120-degree angle and kept close to the body
            • Back vertical or slightly reclined, with the spine’s natural S-shape maintained
            • Thighs, knees, and hips in alignment
            • Feet flat on the floor or on a footrest


            Adjust chairs (if you’re lucky enough to have one in your pharmacy) and keyboard trays so that elbows are at or slightly above keyboard height when arms hang naturally. Let’s go back to the piano example. Piano teachers help their youngest students sit in the proper position by having them sit on a book! Periodically check your shoulder position to avoid scrunching. Keep keyboards close enough to avoid reaching or leaning forward, but far enough away to position forearms parallel to the floor. Experiment with adjusting the keyboard feet or raising the front of the keyboard to avoid any upward, downward, or sideways bending of the wrists. Let your hands move freely above the keyboard when typing, so you won’t need to stretch or bend your wrists to reach keys. Wrist rests should only be used to support the palm or heel of the hand when resting between spurts of typing.45


            Position computer monitors 20 to 40 inches away from your eyes, with the top of the monitor at or just below eye level.45 The goal is to read comfortably with your neck in a neutral position. Monitors should ideally sit directly in front of you, but no more than 35 degrees to either the left or the right. A document holder beneath or to the side of the monitor minimizes head and neck movement when transcribing from a paper prescription. The American Optometric Association recommends taking a 20-second break to focus on something 20 feet away every 20 minutes when using a computer.46 To further reduce eye fatigue, keep the workspace well lit (while taking care to avoid glare on screens).


            Pharmacies can also increase efficiency by protecting workers from phones. A 2025 review of 51 studies found that distractions and interruptions47

            • Happen to pharmacy personnel 5 to 20 times per hour
            • Occupy nearly 25% of US pharmacy personnel’s work time
            • Account for 12% of reported medication errors in community pharmacies
            • Are most commonly phone calls


            Phone calls create both distractions (shifts in workers’ attention as they decide whether to take the call) and interruptions (switching tasks if the call is answered).48 Place phones away from medication preparation and dispensing areas, and consider using a call center or an answering machine to more safely integrate phone calls into the workflow. Mobile phone use is also a frequent cause of distractions,47 so for the sake of patient safety, be sure yours does not interfere with your work.


            Develop “Pharmacy Reading Speed”

            Typing speed is often limited by reading speed, and reading speed is severely limited by unfamiliar words. A 2011 study suggests that people read familiar words whole, regardless of word length, while they decode unfamiliar words slowly syllable-by-syllable.49 Since skilled typists often scan multiple words ahead while transcribing,50 unfamiliar words can bottleneck this process. Drilling brand and generic pairs of frequently prescribed medications transforms unfamiliar words into well-known vocabulary, while enabling efficient selection of products to dispense. Flashcards are available from the Pharmacy Technician Certification Board (PCTB)51 for individuals or employers to purchase, or from a variety of different study aid sites for free.


            While an unfamiliar word presents a bottleneck in the prescription entry process, an illegible handwritten prescription can be a cork. Fortunately, with the rise of electronic prescribing (even back in 2021, 94% of all prescriptions in the United States were e-prescribed52), pharmacy staff encounter this issue less frequently. When they do, familiarity with top medications, including names, routes, and typical doses, can help provide clues for interpretation.53 PCTB has practice tools that drill these key facts for commonly prescribed medications.51


            Practicing reading handwritten prescriptions can also be helpful (and entertaining). Articles in Pharmacy Times,54 pharmacy forums, and media accounts provide plenty of examples and techniques for practicing. Of course, pharmacy personnel should be familiar with the Institute for Safe Medication Practices List of Error-Prone Abbreviations (https://www.ismp.org/sites/default/files/attachments/2017-11/Error%20Prone%20Abbreviations%202015.pdf),55 and never hesitate to have a prescriber clarify when needed. If a prescription reads like a guessing game, the prescriber should be ready to provide an answer key.


            E-prescriptions may be legible, but they often still require translation by pharmacy staff before they are ready to go on a patient label. Prescribers can free-text patient SIGs, using abbreviations and medical jargon. A 2021 study of data from a U.S. mail-order pharmacy found that pharmacy staff edited 83.8% of all e-prescription directions.56 These edits improved readability from an 11th or 12th grade level to a 4th grade level, while resolving 79.5% of quality issues identified by the study’s authors.56


            To perform this vital task with ease and quickly generate accurate, straightforward medication labels, become an expert in translating SIG codes. Several websites, including Pharmacy Times, have free resources for learning SIG codes and practicing their rapid translation.57 This improves processing speed before fingers even move, optimizing both efficiency and patient safety.


            Use Repetition in Short Sessions 

            Sometimes pharmacy technician job postings include written proficiency and typing speed expectations, usually measured in WPM.58 For most data entry roles, 25 to 35 WPM is a minimum, but 40 to 50 WPM is preferred.59 Pharmacy data entry requires accuracy and speed, especially considering most pharmacies process roughly 20 prescriptions per hour.60 As such, a practical typing goal for pharmacy personnel involved in data entry is 40-50 WMP with high accuracy.59


            How can you achieve an average of 40-50 WMP with high accuracy?

            The answer to that question starts with short, frequent practice sessions!61,62,63 Practicing 15 to 20 minutes per day, most days of the week, allows long-lasting habit building. Your practice time doesn’t need to be all day, every day. Resting 12 to 24 hours between practice sessions allows time for your brain to translate the skill into muscle memory.18,19 But your practice time needs to be consistent – that’s the key here!

            cartoon of a pharmacist standing at a counter, looking at a computer screen with his hands typing on a keyboard

            Consistency matters more than session duration.61,59,63 Practicing for 15-20 minutes each day has greater impact on skill retention than a single, long practice session once per week does. However, practice sessions should still be long enough to be meaningful – just a few minutes of practice here and there is unlikely to have the same impact as sustained 15-20 minute practice.64 With consistent practice most days of the week, it still takes about one to three months to reach a 40 to 50 WPM goal.64, 65,66


            In addition to consistency, the quality of practice matters, too. High-quality practice uses structured feedback, which focuses on targeted improvement.67,68 Structured feedback includes three components:

            • Clearly define the skill you want to practice. Be as specific as you can. “Accurately enter prescription directions” is a better, more specific goal than “practice typing.”
            • Identify the gap between your current skill level and your desired skill level. Perhaps your accuracy drops when entering drug names with similar spellings. Or maybe your speed falls when entering numeric doses. Whatever the issue is, identify it so that you can work on it.
            • Make a specific, measurable action plan for improvement! This will help you close the gap between your current skill level and your desired skill level. Perhaps your plan is “slow down during drug name entry and double check before continuing” or “practice the numeric keypad for five minutes daily.” Whatever your plan is, follow through with it!

            A PRO TIP is to choose one specific skill you want to work on, identify what is holding you back, and follow through with an action plan to improve.


            Practice with pharmacy-related content (NDC numbers, prescription directions, patient demographics, etc.) rather than generic typing exercises.69 Greater familiarity with pharmacy terminology leads to improved speed and accuracy over time. Get comfortable using your numeric keypad. Efficiency with the numeric keypad will support your overall typing accuracy and speed.70 (Refer to the section on the numeric keypad for tips and tricks to do this!)


            CONCLUSION

            Accurate typing and data entry are essential pharmacy skills. The good news is that typing accuracy can be improved through deliberate practice. Techniques such as touch typing, chunking, numeric keypad training, error review, and repeated exposure to common pharmacy terminology help build speed, confidence, and accuracy over time. As correct habits become automatic, efficiency naturally improves.

            Remember: accuracy comes before speed. By practicing consistently and learning from mistakes, pharmacy technicians can strengthen their skills, support patient safety, and become more effective members of the pharmacy team. As typing instructors often say, practice makes permanent.

            Pharmacist Post Test (for viewing only)

            PATIENT SAFETY: Prescription for Precision: Improving Pharmacy Typing Accuracy

            26-040 P/T

            Learning Objectives

            Upon completion of this activity, participants should be able to

            1. Explain the relationship between typing accuracy, workflow efficiency, and medication safety in pharmacy practice
            2. Demonstrate techniques that improve the accurate entry of prescription information, including drug names, SIG codes, patient demographics, and numeric data
            3. Identify cognitive, environmental, and ergonomic factors that contribute to pharmacy data-entry errors
            4. Apply deliberate practice and error-prevention strategies to enhance typing performance and reduce transcription-related medication errors


            1. A pharmacy employee types 55 words per minute but frequently makes typing errors that require correction. Why is typing accuracy important to overall workflow efficiency?

            a. Correcting errors often requires additional time and repeated work

            b. Increasing typing speed eliminates the need for proofreading

            c. Faster typing automatically improves prescription processing quality


            *

            1. Which outcome is most directly associated with inaccurate prescription data entry?

            a. Reduced medication inventory costs

            b. Increased risk of medication errors

            c. Decreased patient counseling needs


            *


            1. Which statement best describes the relationship between typing speed and accuracy in pharmacy practice?

            a. Accuracy should be established before speed is increased

            b. Speed should be prioritized before accuracy is measured

            c. Accuracy and speed should be developed independently


            *


            1. Which technique can help improve the accuracy of entering long numeric strings such as NDC numbers?

            a. Dividing the numbers into smaller groups or chunks

            b. Alternating between both hands during entry

            c. Memorizing each digit separately before typing


            *


            1. A pharmacy employee is learning to transcribe prescription directions more accurately. Which skill is most likely to improve performance?

            a. Using abbreviations whenever possible

            b. Increasing typing speed during every entry

            c. Practicing translation of common SIG codes


            *


            1. Which approach do experts recommend when pharmacy employees are learning medication names?

            a. Focus primarily on increasing typing speed

            b. Memorize only brand names before generic names

            c. Study drug classes and common name patterns

            *


            1. Which workplace factor is most commonly associated with interruptions in pharmacy practice?

            a. Barcode verification systems

            b. Incoming telephone calls

            c. Automated dispensing cabinets


            *


            1. Which workstation adjustment best supports ergonomic typing practices?

            a. Positioning the monitor at or slightly below eye level

            b. Positioning the monitor above head height

            c. Positioning the monitor at desk surface level


            *


            1. A pharmacy employee notices repeated spelling errors when entering bevacizumab prescriptions. Which strategy best supports deliberate error review?

            a. Increasing typing speed to improve familiarity

            b. Tracking recurring mistakes and practicing correct entries

            c. Avoiding prescriptions that contain difficult names


            *


            10. You want to improve performance in a busy pharmacy environment. Which practice activity best develops task-switching skills?

            a. Completing timed simulations that require changing tasks

            b. Repeating the same typing exercise without interruption

            c. Practicing typing only in a quiet environment


            Pharmacy Technician Post Test (for viewing only)

            PATIENT SAFETY: Prescription for Precision: Improving Pharmacy Typing Accuracy

            26-040 P/T

            Learning Objectives

            Upon completion of this activity, participants should be able to

            1. Explain the relationship between typing accuracy, workflow efficiency, and medication safety in pharmacy practice
            2. Demonstrate techniques that improve the accurate entry of prescription information, including drug names, SIG codes, patient demographics, and numeric data
            3. Identify cognitive, environmental, and ergonomic factors that contribute to pharmacy data-entry errors
            4. Apply deliberate practice and error-prevention strategies to enhance typing performance and reduce transcription-related medication errors


            1. A pharmacy employee types 55 words per minute but frequently makes typing errors that require correction. Why is typing accuracy important to overall workflow efficiency?

            a. Correcting errors often requires additional time and repeated work

            b. Increasing typing speed eliminates the need for proofreading

            c. Faster typing automatically improves prescription processing quality

            *

            1. Which outcome is most directly associated with inaccurate prescription data entry?

            a. Reduced medication inventory costs

            b. Increased risk of medication errors

            c. Decreased patient counseling needs

            *

            1. Which statement best describes the relationship between typing speed and accuracy in pharmacy practice?

            a. Accuracy should be established before speed is increased

            b. Speed should be prioritized before accuracy is measured

            c. Accuracy and speed should be developed independently

            *

            1. Which technique can help improve the accuracy of entering long numeric strings such as NDC numbers?

            a. Dividing the numbers into smaller groups or chunks

            b. Alternating between both hands during entry

            c. Memorizing each digit separately before typing

            *

            1. A pharmacy employee is learning to transcribe prescription directions more accurately. Which skill is most likely to improve performance?

            a. Using abbreviations whenever possible

            b. Increasing typing speed during every entry

            c. Practicing translation of common SIG codes

            *

            1. Which approach do experts recommend when pharmacy employees are learning medication names?

            a. Focus primarily on increasing typing speed

            b. Memorize only brand names before generic names

            c. Study drug classes and common name patterns

            *

            1. Which workplace factor is most commonly associated with interruptions in pharmacy practice?

            a. Barcode verification systems

            b. Incoming telephone calls

            c. Automated dispensing cabinets

            *

            1. Which workstation adjustment best supports ergonomic typing practices?

            a. Positioning the monitor at or slightly below eye level

            b. Positioning the monitor above head height

            c. Positioning the monitor at desk surface level

            *

            1. A pharmacy employee notices repeated spelling errors when entering bevacizumab prescriptions. Which strategy best supports deliberate error review?

            a. Increasing typing speed to improve familiarity

            b. Tracking recurring mistakes and practicing correct entries

            c. Avoiding prescriptions that contain difficult names

            *

            10. You want to improve performance in a busy pharmacy environment. Which practice activity best develops task-switching skills?

            a. Completing timed simulations that require changing tasks

            b. Repeating the same typing exercise without interruption

            c. Practicing typing only in a quiet environment

            References

            Full List of References

            1. Tsao CW, Aday AW, Almarzooq ZI, et al. Heart Disease and Stroke Statistics-2023 Update: A Report From the American Heart Association. Circulation. 2023;147(8):e93-e621. doi:10.1161/CIR.0000000000001123
            2. Muntner P, Hardy ST, Fine LJ, et al. Trends in Blood Pressure Control Among US Adults With Hypertension, 1999-2000 to 2017-2018. JAMA. 2020;324(12):1190-1200. doi:10.1001/jama.2020.14545
            3. Whelton PK, Carey RM, Aronow WS, et al. 2017 ACC/AHA/AAPA/ABC/ACPM/AGS/APhA/ASH/ASPC/NMA/PCNA Guideline for the Prevention, Detection, Evaluation, and Management of High Blood Pressure in Adults: Executive Summary: A Report of the American College of Cardiology/American Heart Association Task Force on Clinical Practice Guidelines. Hypertension. 2018;71(6):1269-1324. doi:10.1161/HYP.0000000000000066
            4. Writing Committee Members*, Jones DW, Ferdinand KC, et al. 2025 AHA/ACC/AANP/AAPA/ABC/ACCP/ACPM/AGS/AMA/ASPC/NMA/PCNA/SGIM Guideline for the Prevention, Detection, Evaluation and Management of High Blood Pressure in Adults: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Hypertension. 2025;82(10):e212-e316. doi:10.1161/HYP.0000000000000249
            5. World Health Organization. Hypertension fact sheet. World Health Organization. Accessed November 25, 2025. https://www.who.int/news-room/fact-sheets/detail/hypertension
            6. Siddiqui TW, Siddiqui RW, Nishat SMH, et al. Bridging the Gap: Tackling Racial and Ethnic Disparities in Hypertension Management. Cureus. 2024;16(10):e70758. Published 2024 Oct 3. doi:10.7759/cureus.70758
            7. Kirkland EB, Heincelman M, Bishu KG, et al. Trends in Healthcare Expenditures Among US Adults With Hypertension: National Estimates, 2003-2014. J Am Heart Assoc. 2018;7(11):e008731. Published 2018 May 30. doi:10.1161/JAHA.118.008731
            8. Muntner P, Miles MA, Jaeger BC, et al. Blood Pressure Control Among US Adults, 2009 to 2012 Through 2017 to 2020. Hypertension. 2022;79(9):1971-1980. doi:10.1161/HYPERTENSIONAHA.122.19222
            9. Clinical Practice Guidelines We Can Trust National Academies of Sciences, Engineering, and Medicine. 2011. Washington, DC: The National Academies Press. https://doi.org/10.17226/9546. The National Academies Press. Accessed March 30, 2026. https://www.nationalacademies.org/read/13058/chapter/7

            10. Gastens V, Tancredi S, Kiszio B, et al. Pharmacists delivering hypertension care services: a systematic review and meta-analysis of randomized controlled trials. Front Cardiovasc Med. 2025;12:1477729. Published 2025 Mar 14. doi:10.3389/fcvm.2025.1477729
            11. Gastens V, Tancredi S, Bonnan D, et al. Pharmacist interventions to improve hypertension management among patients with diabetes: a systematic review and meta-analysis of randomized controlled trials. BMC Health Serv Res. 2025;25(1):1268. Published 2025 Oct 1. Doi:10.1186/s12913-025-13461-7

            12. Machado M, Bajcar J, Guzzo GC, Einarson TR. Sensitivity of patient outcomes to pharmacist interventions. Part II: Systematic review and meta-analysis in hypertension management. Ann Pharmacother. 2007;41(11):1770-1781. doi:10.1345/aph.1K311
            13. NPTA Staff. Pharmacy Technicians and Patient Safety: Your Role in Preventing Medication Errors. National Pharmacy Technician Association. Published July 23, 2025. Accessed March 30, 2026.
            14. Taylor B, Mehta B. The Community Pharmacy Technician's Role in the Changing Pharmacy Practice Space. Innov Pharm. 2020;11(2):10.24926/iip.v11i2.3325. Published 2020 Apr 30. doi:10.24926/iip.v11i2.3325
            15. Chobanian AV, Bakris GL, Black HR, et al. Seventh report of the Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure. Hypertension. 2003;42(6):1206-1252. doi:10.1161/01.HYP.0000107251.49515.c2
            16. Williams B, Mancia G, Spiering W, et al. 2018 ESC/ESH Guidelines for the management of arterial hypertension. Eur Heart J. 2018;39(33):3021-3104. doi:10.1093/eurheartj/ehy339
            17. Unger T, Borghi C, Charchar F, et al. 2020 International Society of Hypertension Global Hypertension Practice Guidelines. Hypertension. 2020;75(6):1334-1357. doi:10.1161/HYPERTENSIONAHA.120.15026
            18. SPRINT Research Group; Wright JT Jr, Williamson JD, Whelton PK, Snyder JK, Sink KM, Rocco MV, Reboussin DM, Rahman M, Oparil S, Lewis CE, Kimmel PL, Johnson KC, Goff DC Jr, Fine LJ, Cutler JA, Cushman WC, Cheung AK, Ambrosius WT. A Randomized Trial of Intensive versus Standard Blood-Pressure Control. N Engl J Med. 2015 Nov 26;373(22):2103-16. doi: 10.1056/NEJMoa1511939. Epub 2015 Nov 9. Erratum in: N Engl J Med. 2017 Dec 21;377(25):2506. doi: 10.1056/NEJMx170008.
            19. ACCORD Study Group. Intensive BP control in diabetes. N Engl J Med. 2010;362:1575–1585.
            20. Appel LJ, Moore TJ, Obarzanek E, et al. A clinical trial of the effects of dietary patterns on blood pressure. DASH Collaborative Research Group. N Engl J Med. 1997;336(16):1117-1124. doi:10.1056/NEJM199704173361601
            21. KDIGO 2021 Clinical Practice Guideline for BP in CKD. Kidney Int. 2021;99:S1–S87.
            22. Machado M, Bajcar J, Guzzo GC, Einarson TR. Sensitivity of patient outcomes to pharmacist interventions. Part II: Systematic review and meta-analysis in hypertension management. Ann Pharmacother. 2007;41(11):1770-1781. doi:10.1345/aph.1K311
            23. Rohatgi KW, Humble S, McQueen A, et al. Medication Adherence and Characteristics of Patients Who Spend Less on Basic Needs to Afford Medications. J Am Board Fam Med. 2021;34(3):561-570. doi:10.3122/jabfm.2021.03.200361
            24. Chaturvedi A, Zhu A, Gadela NV, Prabhakaran D, Jafar TH. Social Determinants of Health and Disparities in Hypertension and Cardiovascular Diseases. Hypertension. 2024;81(3):387-399. doi:10.1161/HYPERTENSIONAHA.123.21354
            25. Morales-Garzón S, Parker LA, Hernández-Aguado I, González-Moro Tolosana M, Pastor-Valero M, Chilet-Rosell E. Addressing Health Disparities through Community Participation: A Scoping Review of Co-Creation in Public Health. Healthcare (Basel). 2023;11(7):1034. Published 2023 Apr 4. doi:10.3390/healthcare11071034
            26. Athavale A, Roberts DM. Management of proteinuria: blockade of the renin-angiotensin-aldosterone system. Aust Prescr. 2020;43(4):121-125. doi:10.18773/austprescr.2020.021
            27. Liebson PR, Amsterdam EA. Ongoing Telmisartan Alone and in Combination With Ramipril Global Endpoint Trial (ONTARGET): implications for reduced cardiovascular risk. Prev Cardiol. 2009;12(1):43-50. doi:10.1111/j.1751-7141.2008.00010.x
            28. Carey RM, Calhoun DA, Bakris GL, et al. Resistant Hypertension: Detection, Evaluation, and Management: A Scientific Statement From the American Heart Association. Hypertension. 2018;72(5):e53-e90. doi:10.1161/HYP.0000000000000084
            29. Benetos A, Petrovic M, Strandberg T. Hypertension Management in Older and Frail Older Patients. Circ Res. 2019;124(7):1045-1060. doi:10.1161/CIRCRESAHA.118.313236
            30. Williams B, MacDonald TM, Morant S, et al. Spironolactone versus placebo, bisoprolol, and doxazosin to determine the optimal treatment for drug-resistant hypertension (PATHWAY-2): a randomised, double-blind, crossover trial. Lancet. 2015;386(10008):2059-2068. doi:10.1016/S0140-6736(15)00257-3
            31. Ho PM, Bryson CL, Rumsfeld JS. Medication adherence: its importance in cardiovascular outcomes. Circulation. 2009;119(23):3028-3035. doi:10.1161/CIRCULATIONAHA.108.768986
            32. Renfro CP, Turner K, Seeto J, Ferreri SP. Medication synchronization adoption and pharmacy performance. Res Social Adm Pharm. 2021;17(8):1496-1500. doi:10.1016/j.sapharm.2020.11.009
            33. Waghmare PH, Lindsey R, Reed JB, Gao S, Zillich AJ Systematic review of the impact of medication synchronization on healthcare utilization, economic, clinical, and humanistic outcomes. J Am Coll Clin Pharm. 2023; 6(6): 597-614. doi:10.1002/jac5.1815

            LAW: Human Trafficking: Recognize, Respond, Refer

            Learning Objectives

            At the end of this continuing education activity, pharmacists will be able to

            • Review the history and current laws of human trafficking in the United States
            • Recognize common terms, warning signs, and/or vulnerabilities for human trafficking in pharmacy patients/customers
            • Describe pharmacists’ impact on identifying and supporting victims and survivors of human trafficking
            • Ensure proper referral, treatment, and counseling for common health risks associated with human trafficking

            At the end of this continuing education activity, pharmacy technicians will be able to

            • Review the history and current laws of human trafficking in the United States
            • Recognize common terms, warning signs, and/or vulnerabilities for human trafficking in pharmacy patients/customers
            • Identify signs/signals of human trafficking red flags that may be helpful to bring to the attention of pharmacists or law enforcement

              A barcode with silhouettes of men, women, and children built into the lines

               Release Date

              Release Date: July 15, 2026

              Expiration Date: July 15, 2029

              Course Fee

              $7 Pharmacist

              $4 Pharmacy Technician

              There is no funding for this CE.

              ACPE UANs

              Pharmacist: 0009-0000-26-039-H03-P

              Pharmacy Technician: 0009-0000-26-039-H03-T

              Session Codes

              Pharmacist: 26YC39-AGS84

              Pharmacy Technician: 26YC39-GSA48

              Accreditation Hours

              2.0 hours of CE

              Accreditation Statements

              The University of Connecticut School of Pharmacy and Pharmaceutical Sciences is accredited by the Accreditation Council for Pharmacy Education as a provider of continuing pharmacy education.  Statements of credit for the online activity ACPE UAN 0009-0000-26-039-H03-P/T will be awarded when the post test and evaluation have been completed and passed with a 70% or better. Your CE credits will be uploaded to your CPE monitor profile within 2 weeks of completion of the program.


              Disclosure of Discussions of Off-label and Investigational Drug Use

              The material presented here does not necessarily reflect the views of The University of Connecticut School of Pharmacy and Pharmaceutical Sciences or its co-sponsor affiliates. These materials may discuss uses and dosages for therapeutic products, processes, procedures and inferred diagnoses that have not been approved by the United States Food and Drug Administration. A qualified health care professional should be consulted before using any therapeutic product discussed. All readers and continuing education participants should verify all information and data before treating patients or employing any therapies described in this continuing education activity.

              Faculty

              Sarah Meade, PharmD, BCPPS

              Pediatric Oncology Infusion Pharmacist

              Department of Pharmacy, Dana Farber Cancer Institute

              Boston, MA

              Faculty Disclosure

              In accordance with the Accreditation Council for Pharmacy Education (ACPE) Criteria for Quality and Interpretive Guidelines, The University of Connecticut School of Pharmacy and Pharmaceutical Sciences requires that faculty disclose any relationship that the faculty may have with commercial entities whose products or services may be mentioned in the activity.

              Sarah Meade, PharmD has no relationships with ineligible companies.


              ABSTRACT

              Americans may widely underestimate human trafficking’s current extent in the United States because of stereotypes about traffickers, victims, and sex workers, and also because many Americans lack knowledge about this topic. Despite the general public’s lack of knowledge, trafficking reports are rapidly increasing in the United States today. Healthcare for trafficking victims and survivors is often complicated due to clinicians’ lack of sensitivity about a patient’s trafficking experiences. Because victims of human trafficking are highly likely to seek medical care while under a trafficker’s control, training healthcare providers to identify, handle, and report suspected human trafficking is critical. Without trafficking education, providers’ biases and misunderstanding of victim trauma may hinder the ability to develop a trusting patient-provider relationship. Pharmacy teams should know how to identify human trafficking while protecting victims’ safely, providing appropriate resources for victims to seek help, and assisting with individualized treatment selection.

              CONTENT

              Content

              Introduction

              Human trafficking is a growing concern globally. Americans may widely underestimate human trafficking’s current extent in the United States (U.S.) because of stereotypes about traffickers, victims, and sex workers, and also because many Americans lack knowledge about this topic. Despite the general public’s lack of knowledge, trafficking reports are rapidly increasing in the United States today. The SIDEBAR defines terms associated with human trafficking.


              SIDEBAR: Human Trafficking Definitions1,2

              • Human Trafficking: Recruiting, transporting, harboring, soliciting, maintaining, patronizing, advertising, providing, and obtaining people through force, manipulation, fraud, or threats to achieve control over a person for exploitation
              • Victims: people currently in an exploitative situation
              • Sex worker: A person who voluntarily provides sex work regularly or occasionally in commercial exchange for money or goods. Sex work differs from sexual exploitation, or the forcing of a person to commit sexual acts.
              • Survivors: people who have escaped their trafficking situations
              • Survivor-informed practice: Including meaningful input from a diverse community of survivors at all stages of a program or project, including development, implementation, and evaluation
              • Traffickers: people using force, manipulation, threats, or fraud to force victims into exploitative situations
              • Trauma-informed care: collaborating with community resources to empower individuals to determine their own futures
              • Venue: The place in which trafficking occurs; human trafficking does not necessarily involve crossing state or international borders


              In 2010, Faith Robles, a 14-year-old teenager from Mexico, moved in with her boyfriend’s family in Queens, New York.3 The family promised her a job that would “change her life,” but she did not learn this involved sleeping with men against her will—sometimes up to 30 men daily—until after her boyfriend smuggled her into the U.S. At the time, Robles was unaware that her boyfriend and four of his relatives were involved in a human trafficking ring. After she arrived, the family threatened to kill her family and traffic her sister if she sought help from authorities or did not comply with their demands. Robles was a victim of sex trafficking for three and a half years, suffering multiple beatings, sexual assaults, and a broken jaw following an escape attempt. She was finally able to escape at age 17 when she sought help from police officers.3 Hearing from survivors like Faith Robles has helped healthcare providers develop interventions that are survivor-informed. This continuing education activity will cover several aspects of human trafficking as it relates to pharmacy using evidence collected by reliable organizations and researchers.


              Unfortunately, many victims in the U.S. today share stories like Robles’. In August 2022, the Federal Bureau of Investigation (FBI) announced that they located and identified 84 minors who were victims of sex trafficking during a nationwide sex trafficking operation. (Most trafficked victims are between 16 and 24 years of age. Even when adult victims are identified, they could have just turned 18 or are still young adults. People in the human trafficking community have a saying: “Trafficked children become trafficked adults when not found.”) FBI agents found an additional 141 adult victims. Human trafficking rates continue to increase in the U.S. Reports of human trafficking to the National Center for Missing and Exploited Children Tipline increased from 21.7 million to 29.3 million reports from 2020 to 2021.4 Readers should note that collecting and reporting data on human trafficking has some limitations; many cases of human trafficking are never reported.5 Sometimes it’s because the victims are afraid or under a trafficker’s strict control and cannot seek help. Sometimes, it's because people who might be able to help a victim do not recognize the problem or have no idea how to help. Sometimes, it’s because systems have not looked at the issue, determined what (if anything) the system’s responsibilities are, and established policies and procedures to prevent trafficking and provide help.


              Readers should also note that to be considered human trafficking, the trafficker need not move a victim across state or international borders; thinking that movement is a necessary component of human trafficking is a common misperception. Current federal laws only require that the trafficker has met the criteria for the 3 elements of “act,” “means,” and “purpose.”6

              • ACT means that the trafficker has recruited, transported, transferred, harbored, harbored, provided, advertised, maintained, obtained, or received a victim
              • MEANS is only required if the victim is over 18 and indicates the trafficker has used threat or use of force, coercion, fraud, deception, abuse of a position of vulnerability, payments or benefits, or abduction. A minor cannot consent to sex with an adult and automatically is considered a victim of trafficking if ACT and PURPOSE are identified.
              • PURPOSE is very simple; the trafficker’s sole purpose is to exploit the victim

              In short, these requirements indicate that someone who coerces an individual to provide sex or labor against their will in exchange for housing or drugs would be considered a human trafficker, as doing so is exploitation. Someone who moves victims from place to place is also a trafficker, and in some states, people or organizations that knowingly harbor traffickers and their victims would also be complicit in human trafficking.7,8


              In 2024, the National Human Trafficking Hotline reported California, Texas, and Florida as the top states for human trafficking with 1733, 1360, and 832 cases identified, respectively.9 Between 2019 and 2023, the picture changes somewhat, with Nevada, Georgia, and Mississippi documenting rates of 58.5, 46.6, and 43.1 cases per 100,000 residents, respectively.10 Human trafficking often occurs along highways that provide access to easy getaways, quick transportation, or access to large numbers of men; many traffickers move their victims often to avoid detection, but also move their victims to follow the money. In the latter case, they may move their victims closer to a place where men will congregate in large numbers—sorting events, conferences, etc. The busiest interstates in the U.S. include I-5 in the West, I-95 in the East, and I-80 stretching from California to New Jersey. The Polaris Project (see SIDEBAR) asserts that common trafficking venues include illicit massage parlors, informal underground businesses, and hotels and motels along major highways. For this reason, the National Association of Truck Stop Operators and large hotel chains, such as Marriott, offer training to help employees identify and report human trafficking victims.11


              SIDEBAR: The Polaris Project12

              The Polaris Project is a nonprofit social justice organization that fights sex and labor trafficking through the U.S. National Human Trafficking Hotline. Polaris uses survivor-driven trafficking data to improve trafficking identification, provides assistance for victims and survivors, and educates the community. More information on the Polaris Project can be found on its website (https://polarisproject.org/).


              Polaris hosts the National Human Trafficking Hotline around the clock. Readers should make note of this resource, as it will often be the first and safest place to seek help when patients indicate or pharmacy staff suspects that an individual is being trafficked.


              Human trafficking is a crime under federal and international law. The International Labor Organization estimates that the human trafficking “industry” generated $32 billion in 2005, making it the third largest source of income for organized crime.13,14 Current estimates are unavailable but would clearly be much larger. Human trafficking victims can come from any background and may live for years under their trafficker’s control. Trafficking is rarely stranger abduction. Victims may be trafficked by their own family, friends, or acquaintances with or without the victim’s knowledge.15,16


              Human traffickers prey on others in reprehensible ways.17 Policy makers, public health groups, and researchers have tried to understand the motives behind human trafficking to identify factors that would help develop anti-trafficking interventions. Many publications indicate traffickers become involved primarily for financial gain because the profits associated with human trafficking can be enormous. Many of the interventions currently employed identify traffickers by tracking large quantities of cash and banking patterns. Recent research has found that in some cases, traffickers make considerably less money than expected. These traffickers may be motivated by cultural norms, ideology, or religions that devalue human life. Traffickers may be former victims who go on to recruit and control others. And some traffickers simply have sociopathic tendencies.17


              Traffickers use various tactics to manipulate victims, including15

              • Debt-bondage
              • Emotional manipulation
              • Lies or deceit
              • Subjecting victims to unstable or unpredictable conditions
              • Physical, sexual, or psychological violence
              • Threats against family members
              • Transporting victims to unfamiliar places to create a language barrier
              • Withholding documents


              Pre-trafficking vulnerabilities for victims include poverty, trauma, domestic violence, learning difficulties, lack of educational or work opportunities, loss of family, community- or gender-based violence, and natural disasters.2 Human trafficking survivors with vulnerabilities are at higher risk of re-victimization. The SIDEBAR describes types of human trafficking.


              SIDEBAR. Types of Human Trafficking16,18,19

              All forms of human trafficking include exploitation, abuse of vulnerable situations, psychological violence, and deprivation of freedom. Added physical and/or sexual violence is also common. Specific types of trafficking may include one or more of the following:

              • Sex trafficking: forcing someone to sell sex; more commonly affects women but often happens to children of both sexes
              • Forced labor: involuntary servitude, often in industries with large numbers of workers and little regulation; most common element of modern-day slavery. (Readers should be aware that the use of the word “slavery” is controversial. Many U.S. groups do not use it due to historical context. It’s more often used globally.)
              • Domestic servitude: jobs related to domestic help; often hidden in plain sight
              • Debt bondage: begins with debt that the victim is unable to pay immediately; employer exploits the victim by adding additional expenses to increase debt
              • Other forms: forced marriage, organ removal for sale, and enforced crime


              Readers should note that human trafficking differs from human smuggling. In human smuggling, the purported purpose is to transport or hide individuals who lack proper documentation (e.g., passports, driver’s licenses, or other identification) and circumvent officials without regard to immigration laws (a transportation-based crime). The people smuggled across borders often have chosen to be smuggled as a means to reach an otherwise inaccessible destination. Victims of human trafficking are generally held in circumstances against their will. Nevertheless, traffickers may also use victims’ immigration status and threaten to deport victims to coerce victims to do as they are told. In some cases, smuggling may lead to trafficking.


              With 30% to 88% of U.S. trafficking victims seeking healthcare at least once while being trafficked, life-saving identification of trafficking victims in healthcare settings is crucial.20 Several researchers have attempted to estimate how many victims seek healthcare, but because of the nature of the topic and the risk associated with disclosure, it’s been difficult. Two studies shed some light on victims’ contact with healthcare providers. In a meta-analysis of 420 victims, 50% to 98% of victims reported seeking healthcare services in diverse medical settings while they were trafficked.21A second study found that roughly 63% of victims had visited emergency departments (ED) and identified hospitals and ED as their most frequent source of care.22 Trafficking victims tend to use complaint-based episodic acute care services (e.g., minute clinics, urgent care centers, and EDs) more often than long-term comprehensive primary care services.23 Each visit represents an opportunity to identify potential behaviors, injuries, or actions that may signal victimization. Several studies have documented that healthcare professionals tend to have limited recognition and knowledge of human trafficking.24,25


              No data is available about victims’ use of pharmacies, but pharmacy employees in community settings are likely to encounter human trafficking victims. Pharmacists and technicians should be prepared to recognize human trafficking signs for quick, appropriate, and life-saving action.


              History of Human Trafficking in the United States

              Let’s return to Faith Robles. Fortunately, Ms. Robles pressed charges against her boyfriend and his family for the damage and trauma she endured. In 2020, a judge sentenced Robles’ boyfriend and his family to prison terms of between 25 and 40 years under charges of “sex trafficking, sex trafficking conspiracy, sex trafficking of minors, interstate prostitution, alien smuggling, and money laundering conspiracy.”3 However, if Robles had reported her case in the early 1970s, she would not have been able to press charges; the federal government did not incorporate human trafficking crimes into U.S. law until recently.


              The first U.S. law for human trafficking was the 1974 Child Abuse Prevention and Treatment Act (CAPTA). CAPTA required states to establish child abuse reporting laws as a condition of receiving federal funds.26 Mandated reporters and agencies to which people who observe or suspect abuse are to report vary by state law but generally states require reporting in some capacity. Healthcare providers should always check their states’ applicable laws periodically so they know exactly what the state requires.


              Mandated reporters are personnel who must report suspected or confirmed exploitation, abuse, or neglect of vulnerable populations. As of July 2023, Alabama, Colorado, Connecticut, Hawaii, Oregon, Vermont, and Washington state laws specifically list pharmacists as mandated reporters for child victims. Other states list mandated reporters as “healthcare personnel” or people responsible for the care and/or treatment of child victims. The reporting timeframe for suspected child abuse is highly state-specific. Many states still require a written follow-up within 48 hours, while others have changed to 48 hours (New York, Massachusetts), 24 hours (Virginia, Texas), 12 hours (Connecticut), or require reporting "immediately."27-31 Pharmacy staff should check their states’ requirements. Most states do not require mandatory reporting by healthcare personnel for victims 18 years old or older unless the adult is elderly or in some way vulnerable. States that do not require healthcare providers to report adult victims may do so because of the victims’ heightened safety risk, vulnerability, mistrust in authorities, and fear of their traffickers.32 Federal law does not currently require states to mandate reporting for adults or provide funding to meet reporting requirements.


              The Trafficking Victims Protection Act (TVPA) of 2000 created the first comprehensive federal law to address human trafficking. The TVPA offered immigration relief for human trafficking victims, creation of public educational programs for prevention of future trafficking, and increased prosecution of trafficking.26,33 Since January 2000, Congress has reauthorized this Act multiple times, with the last reauthorization in 2023. Recent efforts to reauthorize the bill have stalled in Congress.34 The 2023 TVPA reauthorization added some additional coverage35:

              • It increased protections for child survivors of human trafficking
              • It provided funding for state welfare agencies to identify and assist child victims of human trafficking and work more closely and efficiently with the juvenile justice system
              • It eliminated barriers to services for child victims of human trafficking: consent from a parent or guardian is no longer necessary to apply for ID and other forms of identification, making it easier for children to apply for benefits and services
              • It expanded support for research concerning social media’s impact on human trafficking


              As an aside, proponents of better laws regarding human trafficking point to the Epstein case as affirmation that human trafficking survivors deserve justice.36 The core components are still in effect, but some authorizations for funding, grant and pilot programs, and reporting and coordination mandates need reauthorization.36


              In 2013, the U.S. Department of Health and Human Services (HHS) created the Stop, Observe, Act, and Respond (SOAR) program to provide human trafficking training to healthcare and related professionals. The program includes victim identification and implementation of best practices for necessary reporting, referrals, communication, and treatment. In 2018, the HHS required public posting of best practices on the HHS website for entities receiving federal grants.37 SOAR’s program for individuals and groups are available at https://acf.gov/otip/training-technical-assistance/soar-health-and-wellness.


              In 2015, the Justice for Victims of Trafficking Act (JVTA) improved U.S. trafficking response. The law strengthened victim resources, including increasing individuals’ criminal liability if they buy commercial sex from victims, creation of the survivor-led U.S. Advisory Council on Human Trafficking, and a national strategy for combating human trafficking.38


              Current human trafficking reporting laws are inconsistent due to variations among states; federal law does not clearly define a “mandated reporter” and does not require healthcare providers to report trafficking victims 18 years old or older.26 The American Hospital Association; the law firm of Jones Day; and the Health, Education, Advocacy, Linkage (HEAL) Trafficking network have collated state-specific reporting requirements for healthcare providers on the HEAL Trafficking website (https://healtrafficking.org/wp-content/uploads/2021/01/Human-Trafficking-and-Health-Care-Providers_Legal-Requirements-for-Reporting-and-Education-02_25_21.pdf).26


              PAUSE AND PONDER: What policies, if any, does your workplace currently have to identify trafficking victims?


              Healthcare Providers & Human Trafficking

              Human trafficking victims are often in situations that compromise their health and safety. Most trafficked people seek healthcare from licensed providers at some point during their exploitation. Pharmacists and pharmacy technicians in outpatient settings may interact with victims without realizing their situation. Healthcare providers should be able to recognize possible victims and survivors confidently and take appropriate action to intervene if needed; however, most health professionals report that they are unfamiliar with how to identify or respond to a trafficked person effectively.2,39


              The Pharmacy Team in Action

              Pharmacists’ involvement on the healthcare team is increasing and expanding from dispensing drugs to include medication and disease management and more expansive responsibilities. Pharmacy is unique because the available healthcare counseling is highly accessible by the public.

              For safety and reporting, pharmacy team members should generally trust their instincts in a suspicious situation, especially when patients2,39,40

              • Act as if under control of another person, i.e., another person accompanies the patient, speaks for them, or there is a lack of rapport between the patient and accompanying individual
              • Report a history of frequent address changes, vagueness about where they live and/or medical history
              • Have poor or concerning physical appearance suggesting neglect, and/or physical harm, i.e., poor hygiene or inappropriate clothing for current weather conditions or for their age (i.e., clothing is more promiscuous or revealing than normal for a teen)
              • Present with illnesses or injuries not easily explained, especially repeated or partially treated concerns
              • Exhibit signs and symptoms of self-harm, suicidal ideation, depression, or drug or alcohol misuse


              Many state laws require pharmacists to counsel patients on new prescriptions. Prescription filling patterns that may signal trafficking include frequent sexually transmitted infection (STI) treatment, no insurance coverage, cash-only payments, prescriptions routinely lost or stolen, or a medical history of prescriptions from acute care clinics rather than a primary care physician.33 Victims may be hesitant to access healthcare because of safety concerns and are more likely to self-treat using over the counter (OTC) medications. Table 1 lists frequently used or misused OTC products for self-treatment, and this information may assist pharmacists and pharmacy technicians with screening for potential victims. Upon suspicion of trafficking, pharmacists should try to screen the patient privately.


              Table 1. OTC Products Frequently Used or Misused for Self-Treatment of Trafficking-Associated Medical Concerns41,42

              Health Concern OTC Products
              Mental health and substance abuse St. John’s Wort

              Dextromethorphan

              Diphenhydramine

              Pseudoephedrine

              Phenylephrine

              Sexual intercourse or urinary tract infection Condoms or spermicides

              Levonorgestrel (Plan B)

              Norgestrel (Opill)

              Miconazole, clotrimazole, or tioconazole

              Pregnancy tests

              Phenazopyridine

              Genital anti-itch creams

              Physical abuse Painkillers (i.e., acetaminophen, ibuprofen, aspirin)

              First aid items (i.e., bandages, gauzes, antiseptics, Neosporin)


              Privacy is essential to obtaining accurate and sensitive information that a victim might otherwise not be comfortable with sharing, especially for victims who fear for their safety and accompanied by an abuser. When pharmacy team members try to speak to the patient alone, they should remain calm and ask for privacy cautiously. The pharmacy team may emphasize the importance of privacy to the accompanying individual, perhaps by saying, “I’m going to step in here and speak to [patient’s name] alone because these are deeply personal health issues.” Note that this approach doesn’t ask a question—which might give the trafficker wiggle room to argue—but instead states a fact in a neutral manner. However, pharmacy staff should not push if they experience push-back from the suspected trafficker. Most pharmacies have a separate space for consultation or vaccinations that they may use when patients need privacy or to review sensitive information.


              PAUSE AND PONDER: What are some ways your pharmacy team can work to improve health outcomes for victims and survivors of human trafficking?


              Avoiding Bias + Using the Correct Language

              Pharmacy team members should be aware of their language when speaking to victims; personal biases may perpetuate stereotypes and influence clinical decision making for therapy or diagnoses.


              Well-intentioned but poorly informed organizations or people can perpetuate stereotypes that are not evidence-based or all-encompassing. Understanding bias and perpetuated stereotypes reduces barriers to optimal healthcare. Stereotypes associated with trafficking including victim appearance, location, traffickers, or current situations prevent victims from escaping and/or receiving treatment.1 Table 2 addresses common stereotypes or myths associated with human trafficking in the U.S.. Pharmacy team members should question, acknowledge, and resolve their personal biases towards trafficking to reduce stigmatizing language and shame.


              Table 2. Common Human Trafficking Myths vs Reality1,43

              Myth Reality
              Human trafficking victims are always undocumented foreign women or children. Victims can be any age, sex, ethnicity, or legal status. Sensationalized imagery of victims in the media, such as on TV or in the news, creates bias and provides an inconsistent narrative. Researchers estimate as many as half of all victims and survivors are male, but healthcare professionals are less likely to identify males as victims.
              All commercial sex is human trafficking. Commercial sex is not human trafficking if the patient is an adult and gives informed consent for all activities involved.
              Traffickers always hold victims against their will. Victims may stay involved in trafficking due to lack of resources to leave, fear for their safety, or manipulation by the trafficker. Victims may face shame from their trauma, including cultural attitudes about prostitution, debt, poor health conditions, or working conditions.
              Labor trafficking is only an issue in developing countries. Labor trafficking occurs in the U.S. but is reported less often than sex trafficking.
              Human trafficking is always a violent crime. Human trafficking rarely includes physical force such as kidnapping in its initial stages. Most traffickers manipulate victims through psychological means such as defrauding, manipulating, or threatening vulnerable populations. As the trafficking continues, however, traffickers almost always become physically violent.
              If individuals consented to be in their initial situation, they are not victims of trafficking. Initial consent to commercial sex or labor prior to force, manipulation, or fraud is irrelevant if the situation becomes one of coercion and exploitation later.


              Healthcare providers should always use strength-based language to avoid victim blaming. For example, providers should refrain from using the term “child pornography,” and instead refer to it as “child sexual abuse materials.”1 For sex trafficking victims, they should refer to sexual acts as “exploitation” rather than “prostitution.” Table 2 explains the difference between sex trafficking and commercial sex or prostitution.


              Victims may experience intense shame or secrecy surrounding their experiences that limits their ability to seek medical attention. Healthcare equity for trafficking victims starts with establishing trust. To gain trust, providers should identify and eliminate unconscious biases to improve service accessibility and health outcomes.


              HEALTH CONSEQUENCES FOR VICTIMS

              Traffickers often expose victims to numerous health risks before, during, and after exploitation and may restrict victims’ access to care. A key indicator of human trafficking is delayed care. Many patients have reasons to delay care (e.g., lack of insurance, no transportation, or difficult access to care), but delayed care in combination with other flags may indicate a patient is in trouble.44,35 Victims’ lack of access to proper care and poor environmental conditions may lead to deterioration or exacerbation of conditions.45


              Mental Health and Addiction

              Due to mental exhaustion from trauma, most victims face debilitating mental health issues. Victims may present with signs and symptoms of posttraumatic stress disorder (PTSD), depression, anxiety, dissociation, and substance use disorders. Serious symptoms warranting need for behavioral health therapy may include

              • Difficulty sleeping
              • Feeling detached or withdrawn
              • Guardedness
              • Hopelessness
              • Recurrent thoughts of trauma
              • Sudden emotional reaction when reminded of trauma
              • Suicidal ideation
              • Tendency to startle easily


              Drug or alcohol addiction may exacerbate victim vulnerability, be used as a coping mechanism, or be a part of the trafficker’s tactic to control victims. An anti-trafficking service provider reported that 66% of victims claimed their substance use led to being trafficked, while 4.5% claimed their substance use began after being trafficked.46 Substance use throughout victimization occurred in 84.3% of victims, with the most common substances used being alcohol, marijuana, cocaine, and opioids.46 Due to high mortality rates from opioid overdoses, patients who are or have been trafficked warrant screening for opioid addictions.


              Healthcare providers need to engage in trauma-informed care when helping victims of human trafficking.47 The experience of trauma overwhelms the victim’s ability to cope and healthcare providers need to recognize trauma’s impact on victims. They need to employ a trauma-informed approach. A trauma-informed approach has four components47:

              • Realizing trauma’s pervasive impact and the potential paths victims can follow for recovery
              • Recognizing trauma’s signs and symptoms in individuals, families, staff, and others involved in the system
              • Responding in a manner that fully integrates knowledge about trauma into policies, procedures, and practices
              • Taking care to communicate in ways that actively avoid retraumatization


              A trauma-informed approach means collaborating with community resources to empower individuals to determine their own futures.47 Using the National Human Trafficking Resource Center (NHTRC) hotline is a good way to initiate contact with community resources, as its staff is trained to help healthcare providers determine and identify the next best steps when trafficking is suspected or reported.


              The Substance Abuse and Mental Health Services Administration (SAMHSA) supplies additional information on child trauma-informed care for patient and provider use (https://www.samhsa.gov/childrens-awareness-day/child-traumatic-stress-resources).47


              Unprotected Sexual Intercourse

              Victims of sex trafficking are at elevated risk for STIs and unwanted pregnancies. Pharmacists should attempt to counsel victims of sex trafficking on proper testing or screening, including the common signs and symptoms of various STIs, types of tests, and when and how to test. The CDC lists specific STI treatment guidelines on its website (https://www.cdc.gov/std/treatment-guidelines/default.htm).48


              Monkeypox (now called Mpox) has been an emerging concern particularly for men who have sex with men. Monkeypox presents as a painful rash accompanied by fever, lethargy, muscle aches, and headaches.49


              In female patients of childbearing age who have had recent unprotected sexual intercourse, pharmacists may recommend OTC emergency contraceptive pills (ECPs), or an intrauterine device (IUD) or “morning after” pill if allowed by state law.


              Copper IUDs are a highly effective emergency contraceptive when inserted up to five days after sexual intercourse. This extended period for use and high efficacy rate may be beneficial for victims of human trafficking who may not have immediate access to emergency contraceptives, but IUD insertion can be expensive, and the trafficker may not allow the victim to see a qualified provider. The most common side effects for IUDs are heavy menstrual bleeding, spotty menstruation, or abdominal discomfort. Because victims of sex trafficking may have increased risk for STIs, victims should generally be tested and/or treated for STIs prior to IUD insertion and monitored after insertion.50


              ECPs contain either levonorgestrel or ulipristal acetate (UPA) with 1.2% and 1.2-2.1% efficacy, respectively. UPA-containing ECPs are more effective between 72 and 120 hours post-intercourse than levonorgestrel-containing ECPs. Side effects may include nausea, vomiting, fatigue, and irregular vaginal bleeding.50


              More information on emergency contraception eligibility criteria and safety is located on the World Health Organization’s (WHOs) website.50 In any emergency contraceptive, efficacy decreases as the time between intercourse and treatment increases. Pharmacists should inform patients that contraceptives do not induce abortions.


              Physical Abuse

              Victims may be vulnerable to physical abuse while being trafficked. Common signs of physical abuse are bruises, wounds, fractures, internal injuries, chronic pain, or head, neck and back injuries. Physical abuse may also present as substantial weight loss, dehydration, malnutrition, increased vulnerability to illness, and insomnia. Physical abuse is a medical emergency; if a patient’s safety is in danger, the pharmacy must report the situation to authorities immediately if the patient is a minor. States may require pharmacists to report abuse of an adult under state-specific mandatory reporting laws.


              Acting on Human Trafficking

              Upon suspicion or confirmation of trafficking, pharmacy technicians should alert the pharmacist and pharmacists should try to see the patient alone when possible. All involved staff must remain vigilant about everyone’s safety and avoid directly challenging the victim and/or accompanying individual. Direct confrontation, or raising the suspicion of an accompanying individual, can put a victim at risk of additional harm. It’s critical to note repeatedly that intervention can be dangerous. Most authorities indicate that the best action is to call the National Human Trafficking Hotline at 1(888) 3737-888 or call 911.51


              In instances that involve language barriers, pharmacists should advise the accompanying individual that professional interpreters may be needed instead of relying on ad hoc interpreters (untrained children [who should only be used in emergencies], friends, family, or untrained staff).52-58 The reasons for working alongside interpreters (and interpreters prefer healthcare providers use the term “working alongside” rather than “using” to reflect that this is a collaborative endeavor) are evidence-based. Ad hoc interpreters are more likely to make mistakes, violate confidentiality rules, and increase risk of adverse outcomes. Professional interpreters are also fluid speakers and need not stop and think or reformulate language before translating. Untrained interpreters often leave out the niceties of language—niceties that increase trust and cultural understanding between patient and provider. When using an interpreter, the clinician should address the patient directly and seat the interpreter next to or slightly behind the patient.52-58 Readers who want to learn more about the nuances of professional interpretation may be interested in What’s in a Word? A Guide to Understanding Interpreting and Translation, available online for free at https://www.ncihc.org/assets/documents/publications/Whats_in_a_Word_Guide.pdf.


              Pharmacists and technicians should be patient, compassionate, and sensitive to build trust and gather sufficient information. Since 2011, the Institute of Medicine and the U.S. HHS have recommended screening for intimate partner violence and abuse by asking patients, “Do you feel safe at home?” at each visit.59 In 2013, the U.S. Preventive Services Task Force also made this recommendation. Although the question was meant to identify intimate partner violence, it has identified other types of abuse. This question surprises many patients, and many healthcare practitioners find it uncomfortable to ask. Pharmacy staff might ask this question, but it probably should not be the first question to the suspected victim. Saving this and similar questions should come after establishing some rapport with the patient and the patient seems comfortable. Regardless, patients may not answer truthfully or at all, but just asking the question let’s victims know that someone cares, and help is available.52 When interviewing patients, pharmacists should ask “trauma-informed” questions but consider the harmful effect of reliving traumatic experiences.2 Table 3 provides additional appropriate example questions when screening patients for human trafficking.


              Table 3. Example Screening Tool for Suspicion of Human Trafficking2,15,18

              • Are you limited as to who you can talk to and when?
              • Do you have the freedom to leave your current job?
              • Do you have to ask permission for necessities, such as eating or using the bathroom?
              • Do you owe your employer money or other debts?
              • Has anyone ever physically hit, threatened, or raped you or anyone you work with for any reason?
              • Has anyone ever forced you into sexual intercourse for work?
              • Has anyone threatened your family?
              • Has anyone threatened you with deportation?
              • Is someone else controlling your money or finances?
              • Is someone else in control of where you are allowed to go?
              • Is someone else in control of your identification documents, including your birth certificate or passports?
              • Was someone else in control of your travel arrangements to the U.S.?
              • What is your working or living condition like?


              Healthcare providers may be unable to help patients involved in human trafficking—affected individuals may be too afraid to engage. Individuals need to be able and willing to help themselves. Providers should also offer patients choices; if the patient does not verbalize immediate danger, pharmacists can gently discuss reporting to police, non-government organizations, or helplines. When patients do not want to act, healthcare providers should prioritize care for the patient’s health conditions, gain the victim’s trust, and document clearly. Pharmacy teams should write down any information that may be helpful in an investigation, including time of day, address, and vehicle information, if available.


              Providers must always consider security risks. Pharmacy staff should never attempt to confront a potential human trafficker or victim directly. They should try to arrange follow-up with patients and document their contact information. Pharmacists may also ask for consent to call the patient’s primary care provider.


              That said, pharmacy teams need to always follow statutory and healthcare organization procedures. Again, the National Human Trafficking Resource Center (NHTRC) hotline is available for pharmacy teams to use and pharmacy personnel can call the hotline for guidance. The NHTRC helps providers identify local resources and coordinate with social service organizations. Its hotline is available 24/7 at 1 (888) 3737-888 or text HELP or INFO to “BeFree” (233733). Pharmacists may choose to submit an anonymous tip online on the NHTRC website (https://humantraffickinghotline.org/report-trafficking).60 If the patient is a minor or in imminent danger, a staff member should stay with the patient, remain calm, and contact 911 or the local police department when it is safe to do so.


              Providers should do their best to ensure proper self-care after a stressful or intense situation.


              Conclusion

              Faith Robles is now a spokeswoman, advocate, and aftercare provider for victims of human trafficking which demonstrates that victims, when they can access help, can survive and flourish.61 Pharmacy teams should remain vigilant when encountering suspicious circumstances. Trafficking victims may have multiple health issues because of their trauma and abuse. Pharmacy team members can easily recognize signs of human trafficking through prescription, disease, or behavioral patterns. Individualized screening and determination of the type of trafficking involved is necessary for treatment recommendations and referrals. Pharmacy teams should address victims’ concerns while considering the patient’s health, safety, and personal hardships. Pharmacies may advocate for federal and/or local legislation focused on trafficking prevention and education to drive large-scale change.

              Pharmacist Post Test (for viewing only)

              LAW: Human Trafficking: Recognize, Respond, Refer

              26-039 Pharmacist Posttest


              Learning Objectives

              At the end of this continuing education activity, pharmacists will be able to

              • Review the history and current laws of human trafficking in the United States
              • Recognize common terms, warning signs, and/or vulnerabilities for human trafficking in pharmacy patients/customers
              • Describe pharmacists’ impact on identifying and supporting victims and survivors of human trafficking
              • Ensure proper referral, treatment, and counseling for common health risks associated with human trafficking


              1. Which of the following statements describes the Trafficking Victims Protection Act (TVPA) of 2000?
                1. TVPA was the first law to address child trafficking reporting laws
                2. TVPA offers immigration relief for victims and survivors of human trafficking
                3. TVPA created the US Advisory Council on Human Trafficking


              *


              1. Which of the following is a component of both federal- and state-specific laws that addresses healthcare providers’ responsibilities regarding human trafficking?
                1. Reporting of human trafficking victims 17 years old or younger
                2. Differing definitions concerning who is a “child” or a “minor”
                3. Mandated human trafficking training for healthcare workers


              *


              1. Which act included increased individuals’ criminal liability if they buy sex from victims?
                1. The Child Abuse Prevention and Treatment Act (CAPTA)
                2. The Stop, Observe, Act, and Respond (SOAR) to Health and Wellness Act
                3. The Justice for Victims of Trafficking Act (JVTA)


              *


              1. Which action may result in increased harm for human trafficking victims when accompanied by an individual?
                1. Asking to see the patient alone during private exams because of the sensitive nature of required counseling.
                2. Allowing the accompanied individual to act as an interpreter when there is a language barrier
                3. Staying aware of your own safety when encountering a victim who is accompanied by another person


              *


              1. Which of the following situations during counseling may suggest a patient may be a victim of human trafficking?
                1. A 37-year-old female patient approaches the consulting window alone asking to pick up her birth control prescription 2 days earlier than allowed by insurance
                2. A patient calls the pharmacy asking about selection of vaginal itch creams and pregnancy tests three separate times within one month
                3. A smiling 9-year-old patient accompanied by his legal guardian picking up a new prescription for an albuterol inhaler for the child


              *


              1. When heightening awareness of human trafficking, what do healthcare providers need to know?
                1. Human trafficking victims are likely to seek healthcare at least once during captivity
                2. Human trafficking victims are predominately female adults aged 25 to 34
                3. Traffickers often force victims into trafficking through physical force such as kidnapping


              *


              1. A young woman visits the pharmacy accompanied by a man who seems to hover and intervene in your conversations with the woman. You are able to gently pry her away and interview her in the counseling room. She tearfully says that 4 days ago, she had unprotected sexual intercourse with a man who told her he may have an STI after they had sex. Which emergency contraceptive would you choose for her?
                1. Ulipristal acetate (UPA) emergency contraceptive pills
                2. Levonorgestrel emergency contraceptive pills
                3. Refer her for a copper intrauterine device


              *


              1. A young male who is unkempt and has a prescription for an antibiotic used to treat syphilis. He listens intently as you counsel him on how to take the medication. You ask him how he has been feeling in general in an attempt to build trust. He says that his clothes have gotten tight, but he sleeps heavily all night. He says has been having headaches, fatigue, dizziness and thirst. Which symptom set may indicate he may be a victim of physical abuse?
                1. His clothes have gotten tight
                2. Oversleeping
                3. Headache, fatigue, dizziness and thirst


              *


              9. Alex, Ben, and Carrie each describe symptoms that seem to suggest opioid addiction in individual counseling sessions. Alex, 17, says that he has used heroin since he was 12. Ben, 42, says that he currently has little access to opioids and needs treatment to reduce craving. Carrie, 15, says that she uses alcohol when her “friend” cannot find opioids for her. Which patients are most in need of screening for possible human trafficking?

                1. Alex and Ben
                2. Ben and Carrie
                3. Carrie and Alex


              *


              10. The lead technician comes to you and says that she tried to complete medication reconciliation for a female youth. The youth is 16 years old and has just been admitted to the emergency department for abdominal pain that started with a diagnosis of chlamydia two weeks ago. Now, she may have pelvic inflammatory disease. The patient does not speak English. The woman’s companion said that he would translate for her because she has antisocial personality disorder. Choose the BEST way to approach this dilemma.

                1. Say, “Are you aware that your actions seem suspicious? Either let us talk to her in private or we are going to call the police”
                2. Say, “We have called a translator, and we’ll speak to [patient’s name] alone because these are deeply personal health issues.”
                3. Say, “You have a choice here. We can use the hospital translator with or without you present, or you can take your friend and leave AMA.”


              Pharmacy Technician Post Test (for viewing only)

              LAW: Human Trafficking: Recognize, Respond, Refer

              26-039 Posttest for Pharmacy Technicians

              At the end of this continuing education activity, the pharmacy technician will be able to

              • Review the history and current laws of human trafficking in the United States
              • Recognize common terms, warning signs, and/or vulnerabilities for human trafficking in the pharmacy
              • Identify signs/signals of human trafficking red flags to notify pharmacists or law enforcement


              1. Which of the following statements describes the Trafficking Victims Protection Act (TVPA) of 2000?

              a. TVPA was the first law to address child trafficking reporting laws

              b. TVPA offers immigration relief for victims and survivors of human trafficking

              c. TVPA created the US Advisory Council on Human Trafficking


              *


              2. Which of the following is a component of both federal- and state-specific laws that addresses healthcare providers’ responsibilities regarding human trafficking?

              a. Reporting of human trafficking victims 17 years old or younger

              b. Differing definitions concerning who is a “child” or a “minor”

              c. Mandated human trafficking training for healthcare workers


              *


              3. Which act included increased individuals’ criminal liability if they buy commercial sex from victims?

              a. The Child Abuse Prevention and Treatment Act (CAPTA)

              b. The Stop, Observe, Act, and Respond (SOAR) to Health and Wellness Act

              c. The Justice for Victims of Trafficking Act (JVTA)


              *


              4. Which of the following is a pre-trafficking vulnerability for victims?

              a. Natural disasters

              b. High insurance copays

              c. Well-paying occupation


              *


              5. Which of the following types of trafficking matches its definition below?

              a. Forced Labor: involuntary servitude, often from industries with large numbers of workers and little regulation

              b. Domestic servitude: begins with debt that cannot be paid immediately; employer exploits the victim by adding additional expenses to increase debt

              c. Debt bondage: forcing someone to sell sex; more commonly affects women but often happens to children of both sexes

              *


              6. Which of the following OTC products are human trafficking victims most likely to use or misuse?

              a. Esomeprazole (Nexium)

              b. Oxymetazoline (Sinex)

              c. Acetaminophen (Tylenol)

              *


              7. Which statement below is a common myth regarding human trafficking in the United States?

              a. Public health officials less often report labor trafficking compared to sex trafficking

              b. All commercial sex is human trafficking

              c. Human trafficking rarely uses physical force such as kidnapping


              *


              8. Which patient interaction should prompt you to inform your pharmacist of potential human trafficking?

              a. A young adult patient who hands you a handwritten list of their prescriptions and medical history

              b. An adolescent whose breath smells of alcohol and is dressed in shorts and a tank top for 10⁰F weather in January

              c. A female patient asking to fill her birth control 2 days earlier than her insurance will cover because she’s going on vacation to Miami tomorrow


              *


              9. Three patients confirm that they are human trafficking victims but state that they are not in imminent danger and ask you not to contact authorities. You MUST contact the authorities for one patient under federal law. Which one is it?

              a. An 18-year-old patient who has not showered in 3 weeks

              b. An 11-year-old patient accompanied by her father

              c. A 23-year-old patient taking medications for his anxiety disorder


              *


              10. Upon suspicion of human trafficking, which of the following is an appropriate intervention for pharmacy technicians?

              a. Directly confront the individual accompanying the victim and tell them to stay where they are while you get the pharmacist

              b. When alone with the patient, start a discussion with in-depth questions about their trauma for a more detailed background

              c. Prioritize everyone’s safety, inform the pharmacy team of the situation, and call the authorities when safe to do so


              References

              Full List of References

              1. Jessica L. Peck, Jordan Greenbaum & Hanni Stoklosa (2021): Mandated Continuing Education Requirements for Health Care Professional State Licensure: The Texas Model. J Human Traf. 2024;10(1):168-173. doi: 10.1080/23322705.2021.1981708
              2. Hunt J, Witkin R, Katona C. Identifying human trafficking in adults. BMJ. 2020; 371 doi:10.1136/bmj.m4683 [Epub ahead of print]
              3. Robles F. WRITTEN TESTIMONY, United States House of Representatives Committee on the Judiciary Subcommittee on Crime and Federal Government Surveillance. September 13, 2023. Accessed April 25, 2026. https://www.congress.gov/118/meeting/house/116344/documents/HHRG-118-JU08-20230913-SD009.pdf
              4. Chen S. FBI locates 121 minors, 141 adults in nationwide human trafficking bust. Axios. Published August 15, 2022. Accessed April 25, 2026. https://www.axios.com/2022/08/15/fbi-human-trafficking-operation-recovery
              5. Gaps in Reporting Human trafficking incidents result in significant undercounting. National Institute of Justice. August 4, 2020. Accessed April 25, 2026. https://nij.ojp.gov/topics/articles/gaps-reporting-human-trafficking-incidents-result-significant-undercounting
              6. The Trafficking Victims Protection Act of 2000. U.S. Department of Health & Human Services, Office on Trafficking in Persons. Accessed April 25, 2026. https://www.congress.gov/bill/106th-congress/house-bill/3244
              7. Van Steenwyk J. Human trafficking: What landlords & property managers must know. All Property Management web site. Accessed April 25, 2026. https://www.allpropertymanagement.com/blog/post/human-trafficking-facts-for-landlords/
              8. Landlords Coercing Tenants Unable to Pay Rent to Provide Sex: Sex Trafficking or Not? Polaris web site. Accessed April 25, 2026. https://polarisproject.org/blog/2020/05/landlords-coercing-tenants-unable-to-pay-rent-to-provide-sex-sex-trafficking-or-not/
              9. Where does human trafficking happen? DeliverFund. Published June 9, 2022. Accessed April 25, 2026. https://deliverfund.org/the-human-trafficking-problem-in-america/where-does-human-trafficking-happen/
              10. Mapped: U.S. States with the Most Human Trafficking Victims. Voroni. November 4, 2024. Accessed April 25, 2026. https://www.voronoiapp.com/crime/Mapped-US-States-With-the-Most-Human-Trafficking-Victims-2908
              11. Datta M. Sex trafficking in the US: Four questions answered. Phys.org. March 8, 2019. Accessed April 25, 2026. https://phys.org/news/2019-03-sex-trafficking.html
              12. The Polaris Project. About Us. Accessed April 25, 2026. https://polarisproject.org/about-us/.
              13. Dovydaitis T. Human trafficking: the role of the health care provider. J Midwifery Womens Health. 2010;55(5):462-467.
              14. Feingold D. Human trafficking. Foreign Policy. 2005;150:26-30.
              15. Zimmerman C, Borland R. Caring for Trafficked Persons: Guidance for Health Providers. International Organization for Migration. 2009. Accessed April 25, 2026. https://www.iom.int/caring-trafficked-persons-guide-health-providers
              16. Polaris. Human Trafficking Trends in 2020 An analysis of data from the U.S. National Human Trafficking Hotline. Accessed April 25, 2026. https://polarisproject.org/wp-content/uploads/2022/01/Human-Trafficking-Trends-in-2020-by-Polaris.pdf
              17. Clark MC. Questioning the Notion of Financial Gain as the Primary Motivation of Human Traffickers. Anti-Trafficking Rev. 2022;18:180-184.
              18. Leslie J. Human trafficking: Clinical assessment guideline. J Trauma Nursing. 2018;25(5):282-289.
              19. Human trafficking vs human smuggling. US Immigration and Customs Enforcement. Published Summer 2017. Accessed April 25, 2026. www.ice.gov/sites/default/files/documents/Report/2017/CSReport-13-1.pdf
              20. Stoklosa H, Showalter E, Melnick A, Rothman EF. Health Care Providers’ experience with a protocol for the identification, treatment, and referral of human-trafficking victims. J Human Trafficking. 2016;3(3):182-192.
              21. Armstrong S, Greenbaum VJ. Using Survivors' Voices to Guide the Identification and Care of Trafficked Persons by U.S. Health Care Professionals: A Systematic Review. Adv Emerg Nurs J. 2019;41(3):244-260. doi:10.1097/TME.0000000000000257
              22. Lederer LJ, Wetzel CA. The health consequences of sex trafficking and their implications for identifying victims in healthcare facilities. Ann Health Law. 2014;23(1);61-87.
              23. Wallace C, Lavina I, Mollen C. Share our stories: An exploration of the healthcare experiences of child sex trafficking survivors. Child Abuse Negl. 2021;112:104896. doi:10.1016/j.chiabu.2020.104896
              24. McAmis NE, Mirabella AC, McCarthy EM, et al. Assessing healthcare provider knowledge of human trafficking. PLoS One. 2022;17(3):e0264338. doi: 10.1371/journal.pone.0264338
              25. Recknor FH, Gemeinhardt G, Selwyn BJ. Health care provider challenges to the identification of human trafficking in health care settings: a qualitative study. J Human Trafficking. 2018;4(3):1-18. doi: 10.1080/23322705.2017.1348740
              26. Jones Day White Paper. Human Trafficking and Health Care Providers: Legal Requirements for Reporting and Education. Published August 2020. Accessed April 25, 2026. https://www.jonesday.com/en/insights/2021/09/human-trafficking-and-health-care-providers
              27. Child Abuse Reporting Requirements. Texas Health and Human Services. Accessed June 10, 2026. https://www.dshs.texas.gov/dshs-ems-trauma-systems/links-resources-references/child-abuse-reporting-requirements
              28. Connecticut General Statutes Title 17A. Social and Human Services and Resources § 17a-101b. Report by mandated reporter. Notification of law enforcement agency when allegation of sexual abuse or serious physical abuse. Notification of person in charge of institution, facility or school when staff member suspected of abuse or neglect. FindLAw. Accessed June 10, 2026. https://codes.findlaw.com/ct/title-17a-social-and-human-services-and-resources/ct-gen-st-sect-17a-101b/?utm_source=chatgpt.com
              29. 22VAC40-705-40. Complaints and reports of suspected child abuse or neglect. Accessed June 10, 2026. https://law.lis.virginia.gov/admincode/title22/agency40/chapter705/section40/?utm_source=chatgpt.com
              30. Mass. General Laws c.119 § 51A. Accessed June 10, 2026. https://www.mass.gov/info-details/mass-general-laws-c119-ss-51a?utm_source=chatgpt.com
              31. New York Consolidated Laws, Social Services Law - SOS § 415. Reporting procedure. FindLAw. Accessed June 10, 2026. https://codes.findlaw.com/ny/social-services-law/sos-sect-415/?utm_source=chatgpt.com
              32. Human Trafficking and Health Care Providers: Legal Requirements for Reporting and Education. Jonesday.com. Accessed April 25, 2026. https://www.jonesday.com/-/media/files/publications/2021/09/50-state-survey--human-trafficking-reporting-chart153902279491.pdf?rev=699b80bfd94d4663924bb7bb7a0c5d9c&hash=C8B67EA109FD42BA57B1629DEA4057AE
              33. Federal law. National Human Trafficking Hotline. Accessed April 25, 2026. https://humantraffickinghotline.org/what-human-trafficking/federal-law.
              34. Trafficking Victims Protection Reauthorization Act of 2022. Trafficking Victims Protection Reauthorization Act of 2022. Pub L No. 117-348. Enacted January 5, 2023.
              35. Delgado A. The trafficking victims protection act is signed into law. January 9, 2023. Accessed April 25, 2026. https://www.ecpatusa.org/blog/2023/1/4/trafficking-victims-protection-act-signed-into-law
              36. Next Steps: Congress Must Protect All Human Trafficking Victims. Alliance to End Slavery and trafficking. November 19, 2025. Accessed April 25, 2026. https://endslaveryandtrafficking.org/next-steps-congress-must-protect-all-human-trafficking-victims/?utm_source=chatgpt.com
              37. The SOAR to Health and Wellness Act of 2018, Pub L. No. 115-398 § 132 Stat. 5329 (2018).
              38. Human trafficking laws & regulations. US Department of Homeland Security. Accessed April 25, 2026. https://www.dhs.gov/human-trafficking-laws-regulations.
              39. Nordstrom B. Multidisciplinary Human Trafficking Education: Inpatient and Outpatient Healthcare Settings. J Human Trafficking. 2020;8(2):184-194
              40. Indicators of Human Trafficking. Homeland Security Blue Campaign. Accessed January 5, 2023. https://www.dhs.gov/blue-campaign/indicators-human-trafficking
              41. Terrie Y. Promote the Safe and Proper Use of OTC Drugs. Pharmacy Times. 2019;85(4).
              42. Trygstad T, DiMaggio T, Ogurchak J, Arakelians S, Gallagher A, James D. 2022 Survey of Pharmacists' OTC Recommendations. OTC Guide. (2022):3-60. Accessed April 25, 2026. https://cdn.sanity.io/files/0vv8moc6/pharmacytimes/86326ebdabcad93c75193a50a94fb30cf4e10661.pdf/2022OTCGuide_EditorialPagesOnly-R1%20(2).pdf
              43. Myths & Facts. National Human Trafficking Hotline. Published May 3, 2019.Accessed April 25, 2026. https://humantraffickinghotline.org/what-human-trafficking/myths-misconceptions
              44. Baldwin SB, Eisenman DP, Sayles JN, Ryan G, Chuang KS. Identification of human trafficking victims in health care settings. Health Hum Rights. 2011;13(1):E36-E49.
              45. Stoklosa H, MacGibbon M, Stoklosa J. Human Trafficking, Mental Illness, and Addiction: Avoiding Diagnostic Overshadowing. AMA J Ethics. 2017;19(1):23-34. Published 2017 Jan 1. doi:10.1001/journalofethics.2017.19.1.ecas3-1701
              46. Resources for Child Trauma-Informed Care. Substance Abuse and Mental Health Services Administration. Accessed January 5, 2023. https://www.samhsa.gov/childrens-awareness-day/child-traumatic-stress-resources
              47. Zarnello L. Implementing trauma-informed care across the lifespan to acknowledge childhood adverse event prevalence: best clinical practices. Nurse Pract. 2023;48(2):14-21. doi:10.1097/01.NPR.0000000000000002
              48. Workowski K, Bachmann L, Chan P, et.al. STI treatment guidelines. Centers for Disease Control and Prevention. Published July 22, 2021. Accessed April 25, 2026. https://www.cdc.gov/std/treatment-guidelines/default.htm
              49. Caring for Patients with Monkeypox. Centers for Disease Control and Prevention. Accessed April 25, 2026. https://www.cdc.gov/poxvirus/monkeypox/index.html
              50. World Health Organization. Emergency contraception. November 9, 2021. Accessed April 25, 2026. https://www.who.int/news-room/fact-sheets/detail/emergency-contraception
              51. Michigan attorney general. Human trafficking “Red Flags” for health care professionals. Accessed April 25, 2026. https://www.michigan.gov/ag/-/media/Project/Websites/AG/human-trafficking/Updated-Red-Flags-for-Responders/Red-Flags-Healthcare-Professionals-2025.pdf?rev=b88f6c0338c54852b5f8c990fd6cb7fd
              52. Juckett G, Unger K. Appropriate use of medical interpreters. Am Fam Physician. 2014;90(7):476-480.
              53. Karliner LS, Jacobs EA, Chen AH, Mutha S. Do professional interpreters improve clinical care for patients with limited English proficiency? A systematic review of the literature. Health Serv Res. 2007;42:727-754.
              54. Flores G, Laws MB, Mayo SJ, et al. Errors in medical interpretation and their potential clinical consequences in pediatric encounters. Pediatrics. 2003;111:6-14.
              55. Jacobs EA, Lauderdale DS, Meltzer D, Shorey JM, Levinson W, Thisted RA. Impact of interpreter services on delivery of health care to limited-English-proficient patients. J Gen Intern Med. 2001;16:468-474.
              56. What's in a Word? A Guide to Understanding Interpreting and Translation in Healthcare. Los Angeles, CA: National Health Law Program; 2010. Accessed April 25, 2026. https://www.ncihc.org/assets/documents/publications/Whats_in_a_Word_Guide.pdf
              57. Jackson JC, Nguyen D, Hu N, Harris R, Terasaki GS. Alterations in medical interpretation during routine primary care. J Gen Intern Med. 2011;26:259-264.
              58. Nápoles A, Santoyo-Olsson J, Karliner L, Gregorich SE, Pérez-Stable EJ. Inaccurate language interpretation and its clinical significance in the medical encounters of Spanish-speaking Latinos. Med Care. 2015;53:940-947.
              59. Scott M. Doctors asking about domestic violence is important, but daunting. December 16, 2015. Accessed April 25, 2026. https://whyy.org/segments/doctors-asking-about-domestic-violence-is-important-but-daunting/
              60. Palombi L, Ochten H, Patz C. The Pharmacists’ Role in Identifying and Supporting Victims of Human Trafficking. Human Trafficking. 2019;5(3):255-266.
              61. Dahlia's Hope. Accessed April 25, 2026. https://www.dahliashope.org/

              Roughage Gets Rougher: Clinical Clues to Cyclosporiasis

              Learning Objectives

              At the completion of this activity, pharmacists will be able to:

              • EXPLAIN why Cyclospora cayetanensis' unique life cycle makes person-to-person transmission uncommon and fresh produce a common source of infection
              • RECOGNIZE cyclosporiasis' signs and symptoms and identify patients who should be referred for medical evaluation
              • SUMMARIZE the diagnosis, treatment, and supportive care of cyclosporiasis and identify opportunities to reinforce hydration recommendations or refer for treatment
              • COUNSEL patients on food safety practices and preventive measures to reduce the risk of cyclosporiasis

              At the completion of this activity, the pharmacy technician will be able to:

              • DESCRIBE the epidemiology, transmission, and life cycle of Cyclospora cayetanensis and explain how these characteristics influence disease transmission and prevention
              • RECOGNIZE cyclosporiasis' signs and symptoms and identify patients who should be referred to the pharmacist or another healthcare provider
              • SUMMARIZE the diagnosis, treatment, and supportive care of cyclosporiasis, including hydration strategies and key patient counseling points
              • REINFORCE food safety recommendations and other preventive measures discussed by the pharmacist to help reduce the risk of cyclosporiasis

              a cartoon of a blue gloved hand is holding up a petri dish with a few red and orange dots representing parasites.

               Release Date

              Release Date: July 16, 2026

              Expiration Date: July 16, 2029

              Course Fee

              FREE

              There is no funding for this CE.

              ACPE UANs

              Pharmacist: 0009-0000-26-041-H01-P

              Pharmacy Technician: 0009-0000-26-041-H01-T

              Session Codes

              Pharmacist: 26YC41-RGR63

              Pharmacy Technician: 26YC41-GRG36

              Accreditation Hours

              1 hour of CE   (0.1 CEU)

              Accreditation Statements

              The University of Connecticut School of Pharmacy and Pharmaceutical Sciences is accredited by the Accreditation Council for Pharmacy Education as a provider of continuing pharmacy education.  Statements of credit for the online activity ACPE UAN 0009-0000-26-041-H01-P/T will be awarded when the post test and evaluation have been completed and passed with a 70% or better. Your CE credits will be uploaded to your CPE monitor profile within 2 weeks of completion of the program.


              Disclosure of Discussions of Off-label and Investigational Drug Use

              The material presented here does not necessarily reflect the views of The University of Connecticut School of Pharmacy and Pharmaceutical Sciences or its co-sponsor affiliates. These materials may discuss uses and dosages for therapeutic products, processes, procedures and inferred diagnoses that have not been approved by the United States Food and Drug Administration. A qualified health care professional should be consulted before using any therapeutic product discussed. All readers and continuing education participants should verify all information and data before treating patients or employing any therapies described in this continuing education activity.

              Faculty

              Jeannette Y. Wick, RPh, MBA

              Director Office of Professional Pharmacy Development

              UConn School of Pharmacy and Pharmaceutical Sciences

              Storrs, CT

              Faculty Disclosure

              In accordance with the Accreditation Council for Pharmacy Education (ACPE) Criteria for Quality and Interpretive Guidelines, The University of Connecticut School of Pharmacy and Pharmaceutical Sciences requires that faculty disclose any relationship that the faculty may have with commercial entities whose products or services may be mentioned in the activity.

              Jeannette Wick RPh, has no relationships with ineligible companies.


              ABSTRACT

              Cyclosporiasis is a foodborne diarrheal illness caused by the protozoan parasite Cyclospora cayetanensis. Cases occur each year, often during spring and summer in association with contaminated fresh produce. In 2026, what is different, is that multiple states reported a quick increase in numbers of cases, underscoring the importance of prompt recognition and referral by pharmacy personnel. Patients frequently present to community pharmacies seeking relief from persistent watery diarrhea before seeking medical care. Unlike viral gastroenteritis, cyclosporiasis typically lasts for weeks if untreated, and routine stool cultures do not detect the parasite. This continuing education activity reviews the epidemiology, transmission, life cycle, clinical presentation, diagnosis, treatment, and prevention of cyclosporiasis. Participants will learn to distinguish cyclosporiasis from more common causes of acute gastroenteritis, recognize patients who require medical evaluation, and reinforce appropriate hydration strategies. They will identify trimethoprim-sulfamethoxazole as first-line therapy. The activity also examines food safety practices, common sources of contamination, and practical counseling points that pharmacists can provide and pharmacy technicians can reinforce during patient interactions. Through a patient case and evidence-based discussion, participants will strengthen their ability to identify this increasingly recognized foodborne illness and support timely, appropriate patient care.

              CONTENT

              Content

              INTRODUCTION

              On a busy July afternoon, Jillian, a woman in her mid-40s, approaches the pharmacy counter looking tired and jittery. She glances toward the back of the store, as though making sure she knows where the restroom is.  When the pharmacist asks how she can help, she says quietly, "I started having diarrhea more than a week ago." At first, she assumed she had a stomach virus and expected it to resolve in a day or two. Instead, the diarrhea has become more frequent. "It's explosive," she says. "When I have to go, I have to go right now. I haven't been more than a few minutes from a bathroom in days."

              She reports having six to eight episodes of watery diarrhea each day, accompanied by cramping, bloating, nausea, and profound fatigue. She has missed three days of work because she is afraid she won't make it to a bathroom in time. She has been drinking plenty of fluids, but feels weak and has little appetite.

              She has tried bismuth subsalicylate without relief and wonders whether a stronger over-the-counter medication might finally stop the diarrhea. As the pharmacist asks additional questions, she mentions that she and her husband have been trying to eat healthier. Over the past two weeks, they have eaten several prepackaged salad kits, fresh berries, and homemade smoothies made with fresh basil from a neighborhood farm stand.

              The pharmacist considers this history. Acute viral gastroenteritis usually resolves within a few days. Persistent, profuse watery diarrhea during the summer months suggests another possibility.

              PAUSE and PONDER: What additional questions should the pharmacy team ask? Which features of this patient's illness warrant referral for medical evaluation?

              Seasonal Spotlight: Cyclosporiasis

              Cyclosporiasis is a seasonal intestinal infection caused by the microscopic parasite Cyclospora cayetanensis.1,2 (Table 1 explains how parasites differ from bacteria or viruses.) Although cases occur every year, infections increase during the spring and summer when contaminated fresh produce enters the food supply.3 In 2026, the United States (U.S.) is experiencing a substantial multistate increase in reported cases, prompting investigations by the Centers for Disease Control and Prevention (CDC), the U.S. Food and Drug Administration (FDA), and multiple state health departments.2-6 The SIDEBAR lists facts every pharmacy employee needs to know.


              Table 1. Microbiology Minute: What's the Difference?8

              Foodborne illnesses can be caused by viruses, bacteria, or parasites, but these organisms behave differently

              Type Examples Key characteristics
              Viruses Norovirus, rotavirus Require living cells to reproduce. Illness is often abrupt and resolves within a few days to a week. Antibiotics are ineffective.
              Bacteria Salmonella, Campylobacter, Escherichia coli Organisms that multiply on their own. Some infections respond to antibiotics, while others do not.
              Parasites Cyclospora cayetanensis, Giardia duodenalis, Cryptosporidium parvum Organisms that live in a host’s intestine and often have complex life cycles (with oocyst/cyst stages). Often require antiparasitic medications. Symptoms  persist for weeks if untreated.


              SIDEBAR: Fast Facts about Cyclosporiasis1,7-9

              • Cause: Infection with the protozoan parasite Cyclospora cayetanensis.
              • Transmission: Consumption of food or water contaminated with Cyclospora oocysts—most often in the US via fresh produce.
              • Person-to-person spread: Unlike many diarrheal illnesses, freshly shed Cyclospora oocysts require days to weeks in the environment before they become infectious, making direct transmission unlikely.
              • Incubation period: Typically about one week (range, two days to two weeks).
              • Hallmark symptom: Profuse, watery diarrhea that is often described as explosive.
              • Other symptoms: Abdominal cramping, bloating, nausea, fatigue, loss of appetite, weight loss, and low-grade fever. Symptoms may persist for weeks or relapse if untreated.
              • Diagnosis: Stool testing specifically ordered to detect Cyclospora. Most commercial laboratories have this as part of their multiplex PCR testing.  Additionally, up to three days of testing is recommended after negative tests, as oocysts shed inconsistently.
              • Treatment: Trimethoprim-sulfamethoxazole (TMP-SMX) for 7 to 10 days is the first line treatment. Supportive care includes aggressive fluid replacement. Patients with sulfonamide allergy require alternative management because no highly effective substitute has been established.


              This Outbreak Is Different

              As of early July 2026, the CDC confirmed domestically acquired cases in at least 37 states, while several affected states reported substantially larger numbers through their own surveillance systems. Michigan has experienced an especially large outbreak, and investigations to identify the contaminated food source remain ongoing. No single food item had been implicated as of July 11, 2026.7 Many cyclosporiasis outbreaks are never linked to a single food source because traceback investigations and testing of fresh produce are often difficult.

              Although the source of the current outbreak has not been identified, previous U.S. outbreaks have been associated with fresh produce, including10-12

              • Bagged salad mixes
              • Cilantro
              • Fresh basil
              • Raspberries and blackberries
              • Romaine and mesclun lettuce
              • Snow peas

              Identifying Possible Cyclospora Infection

              Patients often mistake cyclosporiasis for viral gastroenteritis. The difference is time.1 Most cases of norovirus, the most common form of viral gastroenteritis, improve within 24 to 72 hours. In contrast, patients with cyclosporiasis often report that their diarrhea has persisted for a week or longer and may even improve briefly before returning. Why? Cyclospora cayetanensis has an unusual life cycle, described in Figure 1, that explains many of the infection's clinical characteristics and public health challenges.

              A pictograph of the life cycle of cyclosporiasis

              Although first recognized in humans in 1977, scientists spent more than a decade debating this parasite’s identity.13-15  At various times, the organism was referred to as "coccidia-like bodies," reflecting its resemblance to coccidial parasites, or "cyanobacterium-like bodies," and some investigators even suspected it was a blue-green alga before it was formally identified as Cyclospora cayetanensis in 1993.  Large multistate outbreaks linked to imported Guatemalan raspberries in 1996 transformed Cyclospora from an obscure tropical parasite into a major foodborne pathogen of international public health importance.13-15

              PAUSE and PONDER: Why is person-to-person transmission of Cyclospora cayetanensis not possible?

              People become infected by swallowing sporulated oocysts—the environmentally mature form of the parasite—on contaminated food or in contaminated water.16,17 After ingestion, the parasite infects cells lining the small intestine, where it multiplies and causes inflammation that leads to watery diarrhea and other gastrointestinal symptoms. Infected individuals shed unsporulated (immature) oocysts in the stool.16,17 Freshly passed oocysts are not immediately infectious. Instead, they must remain in the environment for one to two weeks under favorable conditions before they mature (sporulate) and become capable of infecting another person.3,16

              This delay explains two important features of cyclosporiasis1,3:

              • Person-to-person transmission is uncommon because freshly shed oocysts cannot immediately infect another individual.
              • Fresh produce is a common vehicle for infection because fruits, vegetables, and herbs can become contaminated in the field or during irrigation, allowing oocysts time to mature before the food is harvested and consumed.


              Jillian seems relieved to have a possible diagnosis and a plan to see her primary care provider. Suddenly, she looks worried again. She says, “I feed some raw fruits and vegetables to my dogs! Will they get this?”

              Here’s a not-so-fun fact: humans are the only known host for Cyclospora cayetanensis.16 Jillian’s dogs will not become ill from Cyclospora cayetanensis. Contamination of food or water occurs through exposure to human feces rather than infected animals.16 How does human fecal contamination get onto produce? See the SIDEBAR.


              SIDEBAR: How Does Human Fecal Material End Up on Fresh Produce?5,6

              Most people picture an obvious sanitation failure, but contamination is usually much less dramatic.6,18 Fresh produce can become contaminated when irrigation or wash water is contaminated with sewage, when an infected worker harvests or packs produce without adequate hand hygiene, or when toilet or handwashing facilities are unavailable or improperly maintained. Contamination may also occur during harvesting, packing, or processing if proper hygiene and sanitation practices are not followed.6,18 Food safety is ultimately about human behavior and infrastructure, not just microorganisms.

              Because humans are the only known host for Cyclospora cayetanensis, preventing contamination depends on worker health and hygiene, safe water sources, proper sewage disposal, and field sanitation.6,18 The FDA's Produce Safety Rule requires covered farms to provide toilet facilities, handwashing stations, employee hygiene training, and procedures designed to prevent produce contamination.6,18


              Recognizing Cyclosporiasis: Symptoms and Patient Clues

              Jillian’s case is classic. Cyclosporiasis’s hallmark symptom is profuse, watery diarrhea, often described as explosive.8,19 Patients frequently report an overwhelming urgency to reach a restroom and may avoid work, social activities, or travel because they cannot predict when another episode will occur. Other symptoms commonly include abdominal cramping, bloating, nausea, loss of appetite, fatigue, low-grade fever, and weight loss. Vomiting is less common than diarrhea.8,19

              The illness’s prolonged nature places patients—particularly older adults and individuals with underlying medical conditions—at risk for dehydration and electrolyte abnormalities. Although healthy adults usually recover without long-term complications, prolonged diarrhea can lead to dehydration, electrolyte disturbances, and weight loss, particularly in older adults, young children, and individuals who are immunocompromised.8,19

              When a patient asks for help finding an antidiarrheal, ask a few simple questions:

              • How long have the symptoms lasted?
              • How many episodes do you experience each day?
              • Is the diarrhea watery or bloody?
              • Have over-the-counter medications helped?
              • Have you recently eaten fresh berries, salad, herbs, or other raw produce?
              • Have you traveled recently or attended a large gathering where food was served?

              A patient like Jillian who says, "I thought it was a stomach bug, but it's been over a week and I'm still having explosive diarrhea," should be referred for medical evaluation.

              Pharmacy personnel should encourage patients to seek prompt medical evaluation if they experience

              • Watery diarrhea lasting more than 3 to 5 days
              • Severe or persistent diarrhea accompanied by dehydration
              • Inability to maintain adequate fluid intake
              • Fever, bloody stools, or severe abdominal pain
              • Significant weight loss
              • Symptoms in an immunocompromised patient or other individual at high risk for complications

              Diagnosis and Treatment

              Diagnosing cyclosporiasis can be challenging because routine bacterial stool cultures do not detect Cyclospora cayetanensis, and many commonly ordered gastrointestinal multiplex PCR panels do not include this parasite. Healthcare providers should ensure that the selected diagnostic test specifically includes Cyclospora when the infection is suspected.1,8,20 Patients with persistent diarrhea should inform their healthcare provider about the duration of symptoms, recent travel, and consumption of fresh produce. If they don’t, healthcare providers need to ask.

              Diagnosis may be made by identifying the characteristic round Cyclospora oocysts (which are round and a size equivalent to one-tenth the width of a human hair) in stool specimens or, more commonly, by using molecular methods such as PCR when the selected test panel includes Cyclospora. Because infected individuals may shed relatively few oocysts—and may not shed them consistently—a single negative stool specimen does not rule out infection. Sometimes, symptomatic patients do not shed a sufficient quantity of oocysts in their stool; these patients, called low level shedders, might need to submit several specimens collected on different days.5,20 When clinical suspicion remains high, healthcare providers may request stool samples collected on multiple days.

              PAUSE and PONDER: A patient fills a prescription for TMP-SMX and says the prescriber told him to use “supportive care.” He doesn’t really know what that means. What would you say?


              Treatment

              The treatment of choice is trimethoprim-sulfamethoxazole (TMP-SMX).8,9 For immunocompetent adults, the recommended adult regimen is one double-strength tablet (TMP 160 mg/SMX 800 mg) orally twice daily for seven to 10 days.  The pediatric dose for children older than two months is 8 to 10 mg/kg TMP and 40 to 50 mg/kg SMX per day, orally, in two divided doses for seven to 10 days. Both Bactrim and ciprofloxacin work similarly on the protozoan parasite as they do on bacteria. Bactrim inhibits its ability for folate synthesis it needs for survival, while ciprofloxacin inhibits its DNA replication. Importantly, it needs a functional immune system for cure; those with immunocompromise, it may result in stasis and secondary prophylaxis is generally recommended.8,9

              Fluid replacement is an essential component of treatment because prolonged watery diarrhea can lead to dehydration and electrolyte imbalances. The pharmacy team should encourage patients to8

              • Drink small, frequent amounts of fluid rather than large volumes at one time if nausea is present.
              • Use an oral rehydration solution (ORS) (e.g., Pedialyte or other commercially available ORS) when diarrhea is moderate to severe or prolonged. ORS products contain an appropriate balance of water, sugar, and electrolytes to promote intestinal absorption.
              • Consume clear fluids such as water, broth, or diluted sports drinks if an ORS is unavailable. (ORS remains the preferred option.)


              Some beverages may worsen diarrhea or contribute to dehydration and should be avoided, including21-23

              • Alcohol
              • Excessive caffeine (coffee, energy drinks)
              • Sugar-sweetened beverages such as regular soda or undiluted fruit juice, which can increase osmotic diarrhea
              • Sugar-free beverages containing poorly absorbed sugar alcohols (e.g., sorbitol or mannitol), which may also worsen osmotic diarrhea
              • Patients should be recommended to have ORS available at home.

              Patients who are unable to keep fluids down, experience dizziness or fainting, produce very little urine, or develop signs of severe dehydration should seek immediate medical attention. Pediatric patients with any level of dehydration should seek medical attention. Patients with diabetes should monitor blood glucose more frequently during diarrheal illness because dehydration and changes in food intake may affect glycemic control. Patients who continue to have diarrhea after completing treatment—or whose symptoms recur—should contact their healthcare provider.3  Relapses are part of the disease.12

              Over-the-counter antidiarrheal medications, may provide temporary symptomatic relief in otherwise healthy adults but do not eradicate Cyclospora cayetanensis.20 (And note that Cyclospora typically does not cause bloody diarrhea; if a patient has bloody stools or high fever, they may have an invasive bacterial infection rather than cyclosporiasis.) Patients with persistent watery diarrhea lasting more than several days should be referred for medical evaluation rather than repeatedly self-treating with over-the-counter products.20 Antidiarrheals should be avoided in patients with bloody diarrhea or high fever unless directed by a healthcare provider.8,20

              Management becomes more complicated in patients with sulfonamide allergies. Research has yet to identify a highly effective alternative to TMP-SMX.8 Depending on the severity of the illness and the nature of the allergy, clinicians may recommend symptomatic treatment, consider an alternative antimicrobial  such as ciprofloxacin, supported by limited evidence, or pursue TMP-SMX desensitization in carefully selected patients.+


              Food Safety and Prevention

              Fresh produce is the most common source of infection because people often eat it raw. Previous U.S. outbreaks have been linked to cilantro, basil, raspberries, blackberries, and leafy greens.10-12 However, any fresh fruit or vegetable exposed to contaminated irrigation water or poor sanitation practices may become contaminated. The 1996 raspberry outbreak was so large that it fundamentally changed how public health agencies investigate produce-associated outbreaks. Before then, most people associated foodborne illness with meat, eggs, or dairy—not fresh berries.13-15

              Rinsing produce under running water is recommended because it removes dirt and may reduce contamination, but it cannot be relied upon to remove or eliminate all Cyclospora oocysts.6 The parasite's hardy outer shell allows it to survive under environmental conditions that would eliminate many bacteria and viruses. Experts don’t recommend soap, bleach, or commercial produce washes because they have not been shown to eliminate Cyclospora and may leave harmful residues on food. Refrigeration does not kill the parasite. Freezing may reduce viability but should not be relied upon to prevent infection.6

              PAUSE and PONDER: If washing doesn't work, why bother?

              In short, washing reduces contamination, even though it doesn't guarantee safety.

              Jillian listens to the information about washing vegetables, and she sighs, “We were eating better. Now we can’t even have a salad.” The pharmacist says, "I understand why you feel that way," and continues, "But I don't want this experience to keep you from eating healthy foods. The answer isn't to avoid salads forever. It's to pay attention to food recalls and practice good food safety." He also tells her, “In otherwise healthy individuals this is not fun, but it is important to continue eating healthy foods.”


              Reducing Infection Risk

              Although no method completely eliminates the risk of cyclosporiasis, patients can reduce their risk by24

              • Washing hands with soap and water before preparing or eating food.
              • Rinsing fresh fruits and vegetables under running water before eating, cutting, or cooking them.
              • Scrubbing firm produce (e.g., melons, cucumbers, potatoes) with a clean produce brush.
              • Refrigerating perishable produce promptly.
              • Separating fresh produce from raw meat, poultry, seafood, and their juices to prevent cross-contamination.
              • Following FDA recalls and public health advisories during foodborne illness outbreaks.

              For most healthy adults, cyclosporiasis is unpleasant but rarely life-threatening. The health benefits of eating fresh fruits and vegetables continue to outweigh the relatively low risk of infection. Patients should follow recommended food safety practices, remain aware of food recalls, and seek medical evaluation promptly if persistent watery diarrhea develops. Individuals who are severely immunocompromised should discuss additional food safety precautions—including avoiding raw produce—with their healthcare providers.


              CONCLUSION

              Remember Jillian? She didn't come to the pharmacy looking for an antiparasitic medication. She came looking for an antidiarrheal. The pharmacy team's greatest contribution wasn't recommending a product—it was recognizing that her symptoms didn't fit the pattern of a routine stomach virus and ensuring she received appropriate medical evaluation. Tackling outbreaks of this parasitic diarrhea is about recognizing patterns, asking the right questions, and understanding that food safety begins long before food reaches the pharmacy—or the patient.

              Pharmacist Post Test (for viewing only)

              Roughage Gets Rougher: Clinical Clues to Cyclosporiasis

              26-041 Pharmacist Post-test

              LEARNING OBJECTIVES

              At the completion of this activity, pharmacists will be able to

              • EXPLAIN why Cyclospora cayetanensis’ unique life cycle makes person-to-person transmission uncommon and fresh produce a common source of infection
              • RECOGNIZE cyclosporiasis’ signs and symptoms and identify patients who should be referred for medical evaluation
              • SUMMARIZE the diagnosis, treatment, and supportive care of cyclosporiasis and identify opportunities to reinforce hydration recommendations or refer for treatment
              • COUNSEL patients on food safety practices and preventive measures to reduce the risk of cyclosporiasis


              1. Jillian says, "My husband has been taking care of me all week and he is fine. Is he likely to catch this from me?" Which response is most appropriate?

              a. Yes, because the parasite spreads easily between household members.

              b. No, because freshly passed oocysts must mature to be infectious.

              c. No, because adults are naturally immune to the parasite.


              *


              2. A patient asks why outbreaks of cyclosporiasis are often linked to fresh produce. Which explanation is most accurate?

              a. People often do not cook their produce before eating.

              b. The parasite multiplies rapidly during refrigeration.

              c. Fresh vegetables naturally harbor dormant parasites.


              *


              3. Which statement best explains why Cyclospora differs from many causes of infectious diarrhea?

              a. It spreads mainly through respiratory droplets and coughing.

              b. It requires environmental maturation before becoming infectious.

              c. It survives only in untreated drinking water.


              *


              4. Which patient should a pharmacist refer for medical evaluation?

              a. Hannah has no idea why she has had watery diarrhea for eight days.

              b. Toby experiences nausea and burping after a greasy restaurant meal.

              c. Spencer and her husband had diarrhea for two days after eating fast food.


              *


              5. Which finding most strongly suggests cyclosporiasis rather than viral gastroenteritis?

              a. Mild abdominal bloating after dinner.

              b. Diarrhea that resolved within 48 hours.

              c. Persistent watery diarrhea lasting one week.


              *


              6. Jillian says, "I've had diarrhea for nine days and have taken bismuth subsalicylate for three days, but nothing has changed." What is the pharmacist's best response?

              a. Switch to loperamide for at least another week.

              b. Seek medical evaluation for persistent diarrhea.

              c. Eat bananas, rice, apples, and toast until it resolves.


              *


              7. Which statement about diagnosing cyclosporiasis is correct?

              a. Routine stool cultures detect the parasite.

              b. Blood cultures confirm the diagnosis.

              c. Stool PCR testing must include Cyclospora.


              *


              8. Pharmacist Ezra is kind of pompous. He tells a patient to take the TMP/SMX and include supportive care. The patient says, “What does THAT mean?” Which description is the MOST appropriate?

              a. Replace lost fluids with an oral rehydration solution.

              b. Drink 16 ounces of a sports drink every two hours.

              c. Use sorbitol-containing liquids to flush out the bug.


              *


              9. Which medication treats the underlying infection?

              a. Loperamide

              b. Metronidazole

              c. Trimethoprim-sulfamethoxazole


              *


              10. Jillian sighs, "I guess I can't eat salads anymore." Which response is most appropriate?

              a. Just avoid fresh produce during the summer-that’s the risky time.

              b. Continue eating produce and follow food safety recommendations.

              c. Of course you can! Purchase only prewashed salad mixes!


              Pharmacy Technician Post Test (for viewing only)

              Roughage Gets Rougher: Clinical Clues to Cyclosporiasis

              26-041 Pharmacy technician Post-test

              LEARNING OBJECTIVES

              At the completion of this activity, pharmacy technicians will be able to

              • DESCRIBE the epidemiology, transmission, and life cycle of Cyclospora cayetanensis and explain how these characteristics influence disease transmission and prevention
              • RECOGNIZE cyclosporiasis’ signs and symptoms and identify patients who should be referred to the pharmacist or another healthcare provider
              • SUMMARIZE the diagnosis, treatment, and supportive care of cyclosporiasis, including hydration strategies and key patient counseling points
              • REINFORCE food safety recommendations and other preventive measures discussed by the pharmacist to help reduce the risk of cyclosporiasis


              1. Jillian says, "My husband has been taking care of me all week and he is fine. Is he likely to catch this from me?" Which response is most appropriate?

              a. Yes, because the parasite spreads easily between household members.

              b. No, because freshly passed oocysts must mature to be infectious.

              c. No, because adults are naturally immune to the parasite.


              *


              2. A patient asks why outbreaks of cyclosporiasis are often linked to fresh produce. Which explanation is most accurate?

              a. People often eat contaminated produce raw.

              b. The parasite multiplies rapidly during refrigeration.

              c. Fresh vegetables naturally harbor dormant parasites.


              *


              3. Which statement best explains why Cyclospora differs from many causes of infectious diarrhea?

              a. Household pets commonly spread the parasite.

              b. Respiratory droplets spread the infection.

              c. Contaminated food and water are common sources.


              *


              4. Which patient should a pharmacy technician refer to the pharmacist?

              a. Hannah reports having watery diarrhea for eight days.

              b. Toby experiences nausea after a greasy restaurant meal.

              c. Spencer ate spicy food and had loose stool after.


              *


              5.  Which symptom most strongly suggests cyclosporiasis?

              a. Mild stomach bloating after dinner.

              b. Diarrhea that resolved within 48 hours.

              c. Persistent watery diarrhea lasting one week.


              *


              6. Pharmacist Ezra always uses big words for everything. He tells a patient to take the TMP/SMX and drink oral rehydration solution. The patient asks you, “What does THAT mean?” Which product would you help the patient find?

              a. Pedialyte

              b. Gatorade

              c. Ginger ale


              *


              7. Which statement about diagnosing cyclosporiasis is correct?

              a. Routine stool cultures detect the parasite.

              b. Blood cultures confirm the diagnosis.

              c. Testing must specifically include Cyclospora.


              *


              8. Which medication treats the underlying infection?

              a. Loperamide

              b. Bismuth subsalicylate

              c. Trimethoprim-sulfamethoxazole


              *


              9. A patient asks whether washing lettuce completely removes Cyclospora. Which response is BEST?

              a. Washing reduces contamination but cannot eliminate all oocysts.

              b. Soaking vegetables with soap in a dishpan eliminates the parasite.

              c. Refrigerating raw produce after rinsing it destroys infectious oocysts.


              *


              10. Your distract manager asks you to create a poster about cyclosporiasis. She reviews the draft poster. Which sentence does she ask them to remove or correct?

              a. Always soak raw produce in one gallon of water with one tablespoon of bleach.

              b. Separate fresh produce from raw meat, poultry, and seafood to prevent cross-contamination.

              c. Follow announcements in the media about outbreaks and follow safe food handling practices.


              References

              Full List of References

              1. About Cyclosporiasis. U.S. Centers for Disease Control and Prevention. September 4, 2024. Accessed July 10, 2026. https://www.cdc.gov/cyclosporiasis/about/index.html
              2. Investigations of Foodborne Illness Outbreaks. U.S. Food and Drug Administration. Accessed July 10, 2026. https://www.fda.gov/food/outbreaks-foodborne-illness/investigations-foodborne-illness-outbreaks?utm_source=chatgpt.com
              3. Clinical Overview of Cyclosporiasis. U.S. Centers for Disease Control and Prevention. March 4, 2024. Accessed July 10, 2026. https://www.cdc.gov/cyclosporiasis/hcp/clinical-overview/index.html
              4. Surveillance of Cyclosporiasis. U.S. Centers for Disease Control and Prevention. July 1, 2026. Accessed July 10, 2026. https://www.cdc.gov/cyclosporiasis/php/surveillance/index.html?utm_source
              5. Guidance for Industry: Guide to Minimize Microbial Food Safety Hazards of Fresh-cut Fruits and Vegetables. U.S. Food and Drug Administration. February 2008. Accessed July 10, 2026. https://www.fda.gov/regulatory-information/search-fda-guidance-documents/guidance-industry-guide-minimize-microbial-food-safety-hazards-fresh-cut-fruits-and-vegetables
              6. Cyclosporiasis and Fresh Produce; An Overview of Cyclospora cayetanensis for Farmers. U.S. Food and Drug Administration. November 18, 2022. Accessed July 10, 2026. https://www.fda.gov/food/foodborne-pathogens/cyclosporiasis-and-fresh-produce?utm
              7. Outbreak of cyclosporiasis occurring in Michigan. Michigan Department of Health and Human Services. July 1, 2026. Accessed July 10, 2026. https://www.michigan.gov/mdhhs/inside-mdhhs/newsroom/2026/07/01/cyclosporiasis?utm_source=chatgpt.com
              8. IDSA 2017 Clinical Practice Guidelines for the Diagnosis and Management of Infectious Diarrhea. Infectious Disease Society of America. October 19, 2017. https://www.idsociety.org/practice-guideline/infectious-diarrhea/
              9. La Hoz RM, Morris MI; AST Infectious Diseases Community of Practice. Intestinal parasites including Cryptosporidium, Cyclospora, Giardia, and Microsporidia, Entamoeba histolytica, Strongyloides, Schistosomiasis, and Echinococcus: Guidelines from the American Society of Transplantation Infectious Diseases Community of Practice. Clin Transplant. 2019;33(9):e13618. doi:10.1111/ctr.13618
              10. Division of Parasitic Diseases and Malaria. U.S. Foodborne Outbreaks of Cyclosporiasis—2000–2017. Atlanta, GA: Centers for Disease Control and Prevention; 2021.
              11. Casillas SM, Bennett C, Straily A. Notes from the Field: Multiple Cyclosporiasis Outbreaks—United States, 2018. MMWR Morb Mortal Wkly Rep. 2018;67:1101-1102.
              12. FDA Releases Cyclospora Prevention, Response and Research Action Plan. US Food and Drug Administration. July 21, 2026. Accessed July 11, 2026. https://content.govdelivery.com/accounts/USFDA/bulletins/2e6751b?utm_source=chatgpt.com
              13. Sterling CR, Ortega YR. Cyclospora: An Enigma Worth Unraveling. Emerging Infectious Diseases. 1999;5(1):48-57.
              14. Ortega YR, Sterling CR, Gilman RH, Cama VA, Díaz F. Cyclospora species—A New Protozoan Pathogen of Humans. N Engl J Med. 1993;328:1308-1312.
              15. Herwaldt BL, Ackers M-L, Cyclospora Working Group. An Outbreak in 1996 of Cyclosporiasis Associated with Imported Raspberries. N Engl J Med. 1997;336:1548-1556.
              16. Cyclosporiasis. U.S. Centers for Disease Control and Prevention. March 4, 2024. Accessed July 10, 2026. https://www.cdc.gov/dpdx/cyclosporiasis/?utm_source=chatgpt.com
              17. Ortega YR, Sanchez R. Update on Cyclospora cayetanensis, a Food-Borne and Waterborne Parasite. Clinical Microbiology Reviews. 2010;23(1):218-234.
              18. FSMA Final Rule on Produce Safety: Standards for the Growing, Harvesting, Packing, and Holding of Produce for Human Consumption. US Food and Drug Administration. Accessed July 11, 2026. https://www.fda.gov/food/food-safety-modernization-act-fsma/fsma-final-rule-produce-safety?utm_source=chatgpt.com
              19. Clinical Care of Cyclosporiasis. U.S. Centers for Disease Control and Prevention. March 8, 2024. Accessed July 10, 2026. https://www.cdc.gov/cyclosporiasis/hcp/clinical-care/index.html
              20. Clinical Guidance for Cyclosporiasis. U.S. Centers for Disease Control and Prevention. March 4, 2024. Accessed July 10, 2026. https://www.cdc.gov/cyclosporiasis/hcp/clinical-guidance/index.html?utm
              21. Fine KD, Schiller LR. AGA technical review on the evaluation and management of chronic diarrhea. Gastroenterology. 1999;116(6):1464-1486. doi:10.1016/s0016-5085(99)70513-5
              22. Centers for Disease Control and Prevention. Treating and Preventing Dehydration. Reviewed May 15, 2024. Accessed July 11, 2026. https://www.cdc.gov/healthywater/emergency/diarrhea-and-dehydration.html
              23. Schiller LR. Diarrhea. In: Merck Manual Professional Version. Merck Sharp & Dohme LLC. Accessed July 11, 2026. https://www.merckmanuals.com/professional/gastrointestinal-disorders/symptoms-of-gastrointestinal-disorders/diarrhea
              24. Preventing Cyclosporiasis. U.S. Centers for Disease Control and Prevention. February 29, 2024. Accessed July 10, 2026. https://www.cdc.gov/cyclosporiasis/prevention/index.html

              High Stakes, High Pressure: Managing Hypertensive Crisis

              Learning Objectives

                After completing this application-based continuing education activity, pharmacists will be able to
              •       DESCRIBE the key differences between severe hypertension and hypertensive emergency
              •       RECOGNIZE the appropriate treatment strategies for those with a hypertensive crisis
              •       IDENTIFY the importance comorbidities play in hypertensive emergency and their corresponding preferred treatment
              After completing this application-based continuing education activity, pharmacy technicians will be able to:
              •       DESCRIBE the key differences between severe hypertension and hypertensive emergency
              •       IDENTIFY strategies to reduce dispensing and preparation errors with high-risk antihypertensive medications
              •       RECOGNIZE common dosing ranges and administration routes for medications used in severe hypertension and hypertensive emergencies

              Release Date:

              Release Date:  May 14, 2026

              Expiration Date: May 14, 2029

              Course Fee

              Pharmacist $7

              Pharmacy Technician $4

              There is no funding for this CPE activity.

              ACPE UANs

              Pharmacist: 0009-9999-26-014-H01-P

              Pharmacy Technician: 0009-9999-26-014-H01-T

              Session Codes

              Pharmacist: 26UC14-AMS49

              Pharmacy Technician: 26UC14-SAM94

              Accreditation Hours

              0.05 CEU    (0.5 Contact Hours)

              Accreditation Statements

              The University of Connecticut School of Pharmacy and Pharmaceutical Sciences is accredited by the Accreditation Council for Pharmacy Education as a provider of continuing pharmacy education.  Statements of credit for the online activity ACPE UAN 0009-9999-26-014-H01-P/T  will be awarded when the post test and evaluation have been completed and passed with a 70% or better. Your CE credits will be uploaded to your CPE monitor profile within 2 weeks of completion of the program.


              Disclosure of Discussions of Off-label and Investigational Drug Use

              The material presented here does not necessarily reflect the views of The University of Connecticut School of Pharmacy and Pharmaceutical Sciences or its co-sponsor affiliates. These materials may discuss uses and dosages for therapeutic products, processes, procedures and inferred diagnoses that have not been approved by the United States Food and Drug Administration. A qualified health care professional should be consulted before using any therapeutic product discussed. All readers and continuing education participants should verify all information and data before treating patients or employing any therapies described in this continuing education activity.

              Faculty

              Aryanna LeBron PharmD

              PGY-1 Pharmacy Resident, UConn Health

              Farmington, CT


              Matthew Mastropietro PharmD

              PGY1 Pharmacy Resident, UConn Health

              Farmington, CT


              Sean J. Johnston, RPH

              Pharmacy Clinical Coordinator, Critical Care, UConn Health

              Farmington, CT


              Faculty Disclosure

              In accordance with the Accreditation Council for Pharmacy Education (ACPE) Criteria for Quality and Interpretive Guidelines, The University of Connecticut School of Pharmacy and Pharmaceutical Sciences requires that faculty disclose any relationship that the faculty may have with commercial entities whose products or services may be mentioned in the activity.

              Aryanna LeBron, PharmD, Matthew Mastropietro, PharmD, and Sean Johnston, RPH have no financial relationships with ineligible companies.

              CONTENT

              Content

              Pharmacist Post Test (for viewing only)

              CE title: High Stakes, High Pressure: Managing Hypertensive Crisis
              26-014 Pharmacist Post-Test

              Learning Objectives:
              1. Describe the key differences between severe hypertension and hypertensive emergency
              2. Recognize the appropriate treatment strategies for those with a hypertensive crisis
              3. Identify the importance comorbidities play in hypertensive emergency and their corresponding preferred treatment

              1) Which of the following distinguishes hypertensive emergencies from severe hypertension?
              a) Systolic blood pressure > 180 mmHg
              b) Diastolic blood pressure > 120 mmHg
              c) Presence of acute organ damage

              *

              2) Which of the following IV mediation is recommended as the initial therapy for a hypertensive emergency in acute aortic dissection?
              a) Hydralazine 10 mg IV push
              b) Nitroprusside 0.3 mcg/kg/min IV infusion
              c) Esmolol 500 mcg/kg loading dose, followed by 50 mcg/kg/min IV infusion

              *

              3) Which antihypertensive would you recommend to reduce BP in a patient who is a candidate for reperfusion therapy in an acute ischemic stroke?
              a) Nitroglycerin 5 mcg/min IV infusion
              b) Nicardipine 5 mg/hour IV infusion
              c) Enalaprilat 1.25 mg IV push

              *

              4) Which of the following medications can be used for hypertensive emergencies induced by catecholamine excess?
              a) Phentolamine
              b) Hydralazine
              c) Esmolol

              *

              5) Which IV antihypertensive therapy requires lipid monitoring due to its formulation being made as a lipid emulsion?
              a) Nicardipine
              b) Clevidipine
              c) Nitroprusside

              *

              6) Which IV antihypertensive therapy can cause cyanide and thiocyanate toxicity in patients with liver dysfunction or chronic kidney disease?
              a) Sodium nitroprusside
              b) Nitroglycerin
              c) Labetalol

              Pharmacy Technician Post Test (for viewing only)

              CE title: High Stakes, High Pressure: Managing Hypertensive Crisis
              26-014 Pharmacy Technician Post-Test

              Learning Objectives:
              1. Describe the key differences between severe hypertension and hypertensive emergency
              2. Recognize common dosing ranges and administration routes for medications used in severe hypertension and hypertensive emergencies
              3. Identify strategies to reduce dispensing and preparation errors with high-risk antihypertensive medications

              1. A patient has BP 210/118 mmHg and no signs of organ injury. How should this be classified?
              A. Hypertensive emergency
              B. Severe hypertension without organ damage
              C. Stroke requiring thrombolysis

              *

              2. Which medication route is appropriate for initial treatment of hypertensive emergency in the ICU?
              A. Oral immediate-release capsule
              B. Intravenous infusion
              C. Subcutaneous injection

              *

              3. Why are high-alert labels used on IV antihypertensive infusions?
              A. To improve visual awareness and reduce selection errors
              B. To speed up dispensing workflow
              C. To eliminate the need for double-checks

              *

              4. Why are standardized concentrations recommended for IV antihypertensive infusions?
              A. They reduce variability and decrease dosing errors
              B. They allow technicians to change infusion rates
              C. They increase medication shelf life

              *

              5. Which safeguard helps prevent dispensing the wrong antihypertensive medication formulation?
              A. Barcode verification during dispensing
              B. Memorizing medication shelf placement
              C. Selecting medication by package color

              *

              6. Which of the following symptoms may indicate acute target organ damage in hypertensive emergencies?
              A. Severe chest pain and/or shortness of breath
              B. Nausea
              C. Occasional muscle soreness

              The Gall of it All: Gallbladder Disease

              Learning Objectives

                After completing this application-based continuing education activity, pharmacists will be able to
              1. DESCRIBE the functions of the gallbladder and how it aids digestion
              2. RECOGNIZE gallbladder disease based on various presentations
              3. EXPLAIN gallstone prevalence, risk factors, and pathogenesis
              4. DISCUSS treatment approaches for gallbladder disease and post-cholecystectomy management
              After completing this application-based continuing education activity, pharmacy technicians will be able to:
              1. DESCRIBE the functions of the gallbladder and how it aids digestion
              2.EXPLAIN gallstone prevalence, risk factors, and pathogenesis
              3. LIST over-the-counter medications used by patients with gallbladder disease and post-cholecystectomy
              4. IDENTIFY when to refer patients with questions about gallbladder disease to a pharmacist

              Cartoon image of gallbladder filled with stones

              Release Date:

              Release Date:  June 16, 2026

              Expiration Date: June 16, 2029

              Course Fee

              FREE

              There is no funding for this CPE activity.

              ACPE UANs

              Pharmacist: 0009-0000-26-034-H01-P

              Pharmacy Technician: 0009-0000-26-034-H01-T

              Session Codes

              Pharmacist:  23YC19-ABC92

              Pharmacy Technician:  23YC19-BCA36

              Accreditation Hours

              2.0 hours of CE

              Accreditation Statements

              The University of Connecticut School of Pharmacy and Pharmaceutical Sciences is accredited by the Accreditation Council for Pharmacy Education as a provider of continuing pharmacy education.  Statements of credit for the online activity ACPE UAN 0009-0000-26-034-H01-P/T  will be awarded when the post test and evaluation have been completed and passed with a 70% or better. Your CE credits will be uploaded to your CPE monitor profile within 2 weeks of completion of the program.


              Disclosure of Discussions of Off-label and Investigational Drug Use

              The material presented here does not necessarily reflect the views of The University of Connecticut School of Pharmacy and Pharmaceutical Sciences or its co-sponsor affiliates. These materials may discuss uses and dosages for therapeutic products, processes, procedures and inferred diagnoses that have not been approved by the United States Food and Drug Administration. A qualified health care professional should be consulted before using any therapeutic product discussed. All readers and continuing education participants should verify all information and data before treating patients or employing any therapies described in this continuing education activity.

              Faculty

              Sara L. Tolliday, PharmD
              Pharmacy Team Lead
              Wentworth-Douglass Hospital
              Outpatient Pharmacy
              Dover, NH


              Faculty Disclosure

              In accordance with the Accreditation Council for Pharmacy Education (ACPE) Criteria for Quality and Interpretive Guidelines, The University of Connecticut School of Pharmacy and Pharmaceutical Sciences requires that faculty disclose any relationship that the faculty may have with commercial entities whose products or services may be mentioned in the activity.

              Dr. Tolliday has no financial relationships with ineligible companies.

              ABSTRACT

              The gallbladder—a member of the biliary system—is responsible for bile secretion into the digestive tract. It was more useful centuries ago when the human diet was allegedly carnivorous and high in fat, its role in digestion today is less essential. This makes removal of the organ to treat gallbladder disease (GBD) quite commonplace. Although surgery is first line GBD treatment, pharmacy teams should remain involved in care for patients with this condition. Pharmacy involvement is especially important post-gallbladder removal. This continuing education activity describes the function of the gallbladder, risk factors for and pathogenesis of GBD, treatment approaches for GBD, and how to optimize care for patients with the disease and post-gallbladder removal.

              CONTENT

              Content

              INTRODUCTION

              Gallbladder disease (GBD; see Sidebar: Types of Gallbladder Disease) is the most common surgical emergency, responsible for 600,000 surgeries per year in the United States.1 Cholelithiasis, or gallstones, is one of the most common and costly gastrointestinal diseases, affecting more than 20 million Americans annually.2 An estimated 115 of every 100,000 of the world’s population will undergo gallbladder removal surgery every year.3

              GBD is influenced by genetic and environmental factors, diet, physical activity, and nutrition. The healthcare team should encourage patients to incorporate healthy habits into their lifestyles to reduce the risk of GBD. This continuing education activity will discuss GBD pathology, risk factors, treatment, considerations post-cholecystectomy, and the pharmacy team’s role.


              GALLBLADDER DISEASE

              The Gallbladder

              The gallbladder is the small pear-shaped organ located in the right upper quadrant (RUQ) of the abdomen beneath the liver. It is part of the biliary system, which is a series of ducts in the liver, gallbladder, and pancreas that drain into the small intestine.4 The gallbladder acts as a storage pouch for up to 50 mL of bile, also known as “gall.”5 Gall became a synonym for bile in the Middle Ages and also meant “embittered spirit.”5 In the late 19th century, gall was used to describe a person having boldness or insolence.4

              Bile is a yellowish-brown alkaline surfactant (substance that decreases surface tension) continuously produced by the liver.1,2 It is composed of cholesterol, bilirubin, water, bile salts, phospholipids, and ions. The common bile duct carries bile from the liver to the gallbladder. Fatty foods and proteins released from the stomach into the small intestine stimulate the gallbladder to empty bile into the duodenum via the sphincter of Oddi, which facilitates digestion. Bile salts emulsify lipids in the intestines allowing absorption of dietary fats such as cholesterol and fat-soluble vitamins. Unused bile salts return to the gallbladder through the distal ileum and portal circulation.1,2

              The gallbladder was probably more valuable centuries ago.5 Some scientists believe that primitive humans were carnivorous hunters; meals were large, few, and far between.5 The gallbladder would have been crucial for digestion of large, high fat meals. The organ wasn’t considered nonessential until the late 1600s, after two Italian doctors discovered that animals could thrive without it.1 This discovery was forgotten until a German physician successfully performed the first cholecystectomy (surgical removal of the gallbladder) in a human in 1878.1,6 Figure 1 describes a brief history of the gallbladder, gallstones, and cholecystectomy beginning in the 15th century.

              Today, the gallbladder assists in digestion of fat-soluble vitamins, proving important even for vegetarians.5 People can still live a healthy life after gallbladder removal; however, the risk of hepatic problems increases due to impaired fat digestion.5


              Timeline of gall bladder surgical history from the 1400's to 1992

              Sidebar: Types of Gallbladder Disease2,8

              • Biliary dyskinesia: gallbladder motility disorder caused by scarring or spasm of sphincter of Oddi, the valve that controls the flow of biliary and pancreatic secretions into the duodenum
              • Cholangitis: inflammation of the biliary system
              • Cholecystitis: inflammation of the gallbladder
              • Choledocholithiasis: common bile duct stones
              • Cholelithiasis: gallstones
              • Gallbladder empyma: severe acute cholecystitis, a surgical emergency
              • Gallbladder pancreatitis: inflammation of the pancreas caused by pancreatic duct obstruction by a gallstone
              • Gallbladder perforation: a hole in the gallbladder wall
                • Acute: generalized biliary peritonitis
                • Subacute: acute plus pericholecystic abscess
                • Chronic: cholecystoenteric fistula
              • Gallbladder polyps: overgrowths or lesions in the gallbladder wall

              This continuing education activity will focus on gallstones and their complications, which may include cholecystitis, choledocholithiasis, and cholangitis. Cholecystectomy (gallbladder removal) is the treatment mainstay for gallstones and pharmacist intervention is most valuable post-cholecystectomy.


              Gallstones and Acute Cholecystitis

              The most common gallbladder disease is gallstones.7 Gallstones commonly form from imbalances in bile constituents and biliary sludge (solids precipitated from bile) caused by slowed gallbladder motility or altered hepatic cholesterol metabolism. Hardened cholesterol or bilirubin become saturated in bile and crystalize, like rock candy, and can lodge in the common bile duct.7 Gallbladder hypomotility leads to delayed emptying, resulting in the formation of biliary sludge and consequently, gallstones.7

              Bilirubin is a substance found in bile resulting from red blood cell breakdown in the liver. It is normally eliminated through the feces. Gallstones caused by bilirubin, or “pigment stones”, are rare and only account for approximately 10% of all gallstones.8 Pigment stones are commonly seen in individuals with blood disorders, such as sickle-cell anemia.8 Approximately 75% of gallstones in Western countries contain cholesterol as their major component.9

              The presence of stones in the gallbladder is called cholelithiasis. Most patients with gallstones are asymptomatic and may not have any attributable symptoms during their lifetime.8 Asymptomatic cholelithiasis does not require treatment as the risk of symptom development is only about 10% at five years.8

              Cholelithiasis becomes acute cholecystitis when gallstones block the cystic duct, causing the gallbladder to become inflamed and patients to become symptomatic. Biliary pain—also known as biliary colic—is the most common symptom of cholecystitis. Epigastric (upper-middle abdomen) pain lasting from 30 minutes to several hours radiates around or through the back and may be accompanied by heartburn, bloating, nausea, and/or vomiting. The sharp, stabbing pain generally follows food intake and peaks after the first hour. It is characteristically steady and is severe enough to interfere with activities of daily living. The pain is not relieved with a bowel movement. Women often describe biliary pain as being worse than childbirth.2,8

              Cholecystitis pain from an acute episode usually subsides over one to five hours as the stone dislodges.3,10 The likelihood that patients experience repeated symptomatic episodes from their gallstones is approximately 38% to 50% annually.8 More than 90% of patients presenting with a single episode of biliary colic have recurrent pain within 10 years.13

              Ultrasound is the best test for diagnosing gallstones and finds most patients with an average of two to 20 stones. The record-setting number of stones was found in England in 1987; a female patient had 23,530 stones removed.5 Computerized tomography (CT) can also be used for diagnosis, but it is less accurate than other imaging methods, detecting approximately 75% of gallstones.2 Providers can also diagnose by the presence of Murphy’s sign, or pain upon inhalation when the inflamed gallbladder meets the examiner’s hand.8 Other diagnostic markers include elevated liver function tests, white cell count, erythrocyte sedimentation rate, and C-reactive protein.8 Patients presenting with acute cholecystitis may have experienced several bouts of biliary colic before diagnosis.

              Acute cholecystitis diagnosis typically requires admission for pain management and intravenous (IV) fluid rehydration. Nonsteroidal anti-inflammatory drugs (NSAIDS) like ketorolac, diclofenac or indomethacin combat inflammation and promote speedy recovery.8 NSAIDS are generally preferred to narcotic analgesics as they are equally effective with fewer adverse effects.2 A study of 324 patients given IV ketorolac or meperidine showed both drugs offered similar pain relief but patients in the NSAID group reported fewer adverse effects.2 Patients receive broad-spectrum antibiotics (e.g., ciprofloxacin, cefuroxime) to prevent or treat bacterial infection.8

              Failure to properly treat cholecystitis can lead to severe inflammation, gangrene, sepsis, and life-threatening gallbladder perforation. Cholecystitis can also lead to gallstone pancreatitis if stones in the sphincter of Oddi are not cleared and block the pancreatic duct.2

              Chronic Cholecystitis

              Repeated episodes of cholecystitis or chronic irritation from gallstones can lead to chronic cholecystitis.11 Chronic cholecystitis more often presents with cholelithiasis (calculous) but can also exist without gallstones (acalculous). Symptomatic patients usually present with dull RUQ pain that radiates around the waist to the middle back. Most patients are afebrile.11

              While acute cholecystitis symptoms are sharp and abrupt, chronic cholecystitis symptoms usually develop and worsen over weeks to months.11 Lab values normally elevated in acute disease may not be in chronic disease and therefore cannot be used in diagnosis. Ultrasound of the RUQ is the best diagnostic tool to evaluate the gallbladder for wall thickening and inflammation. Elective cholecystectomy is the preferred treatment for chronic cholecystitis. Patients who are not eligible for or who prefer not to undergo surgery should be closely monitored. A low-fat diet and other lifestyle modifications can help reduce symptom frequency.11

              Pharmacists should recognize the differences between presentations of acute versus chronic cholecystitis and refer patients to the nearest emergency department if symptoms are severe.

              Choledocholithiasis and Cholangitis

              Choledocholithiasis, or common duct stones, are gallstones that have migrated from the gallbladder to the common bile duct via the cystic duct. Approximately 8% to 16% of patients with symptomatic gallstones will also have common bile duct stones.8 Common duct stones can be asymptomatic or may lead to complications such as gallstone pancreatitis or acute cholangitis. Cholangitis is inflammation of the biliary system that causes fever, jaundice, and abdominal pain (Charcot triad).8 Charcot triad becomes Reynolds pentad when hypotension and altered mental state are also present.8 These symptoms develop due to bile stasis and bacterial infection in the biliary tract.

              Cholangitis is most commonly caused by gram-negative (Escherichia coli [25% to 50%], Klebsiella spp. [15% to 20%], Enterobacter spp. [5% to 10%]) intestinal bacteria, and less often by gram-positive bacteria (Enterococcus spp. [10% to 20%]).8 Patients require prompt treatment with IV antibiotics such as a broad-spectrum cephalosporin or ciprofloxacin.8 Pharmaceutical intervention should be followed by stone removal to prevent septicemia (systemic blood infection), which can be fatal.  Most clinicians recommend that common bile duct stones be removed once discovered, even when asymptomatic.8

              Risk Factors

              Several genetic and environmental factors contribute to gallstone development. Patients with first-degree relatives with history of cholelithiasis are at a three times higher risk of gallstones.8 Approximately 60% of patients with acute cholecystitis are female, but the illness is generally more severe in males.2 Women experience a higher prevalence because of estrogen’s effects on cholesterol metabolism.12 Estrogen increases cholesterol synthesis and decreases bile acid production.12 Progesterone in pregnancy decreases gallbladder contractility leading to stasis, making gallstones 10 to 15 times more common in women who have been pregnant.8,12 Women with history of biliary colic, gallstones, and the like should be aware of how hormones may affect their risk for recurrence. This is valuable information for pharmacists to consider and an appropriate place to intervene and educate.

              European and American populations are more likely to develop gallstones, and Black people of African descent are least likely. Prevalence is highest in Native American populations, with 60% incidence in the Pima Indian populace of southern Arizona.8 Table 1 summarizes risk factors for GBD.2,8,13


              Table 1. Risk Factors for Developing Gallbladder Disease2,8,14-16
              Demographics

              ·       Ethnicity (American Indians, Chilean and Mexican Hispanics)

              ·       Family history

              ·       Female gender (10:1 female:male)

              ·       Older age


              Diet

              ·       High fat, calorie, and refined carbohydrate intake

              ·       Low fiber and unsaturated fat intake

              ·       Total parenteral nutrition


              Lifestyle

              ·       Pregnancy and multiple pregnancies

              ·       Persistent fasting or very low-calorie diet

              ·       Rapid weight loss (i.e., bariatric surgery)

              ·       Sedentary


              Medications

              ·       Estrogen therapy or oral contraceptives

              ·       Some hypoglycemic medications (GLP-1RAs)

              ·       Chronic use of gastric acid suppressants (H2RAs, PPIs)

              ·       Ketamine abuse


              Heath Conditions & Other Factors

              ·       Alcoholic liver cirrhosis

              ·       Dyslipidemia (elevated triglycerides and low HDL)

              ·       Gallbladder motor dysfunction

              ·       Gastrointestinal surgery

              ·       Metabolic syndrome, gallbladder, or intestinal stasis

              ·       Short bowel syndrome

              ·       Type 2 diabetes mellitus


              GLP-1RAs, glucagon-like peptide 1 receptor agonists; H2RAs, histamine-2-receptor antagonists; HDL, high-density lipoprotein; PPIs, proton-pump inhibitors.


              Glucagon-like peptide 1 (GLP1) receptor agonists (GLP-1RAs) are notable for their glucose control and cardiovascular risk reduction for patients with type 2 diabetes mellitus and more recently, for weight loss. Their link to GBD is controversial as GLP1 inhibits gallbladder motility and delays gallbladder emptying.14 A recent systematic review and meta-analysis of 76 randomized clinical trials shows an association between GLP-1RA use and elevated GBD risk. The risk for gallbladder or biliary diseases were more prominent with higher doses, longer duration, and when used for weight loss.14 Clinicians should discuss the benefits of using these hypoglycemics for type 2 diabetes or weight loss and whether they outweigh the risk for GBD. Pharmacists can educate patients initiating GLP-1RAs about their benefits, risks, and implications with past medical history of or additional risk factors for GBD. Multiple GLP-1RAs are available in varying doses and pharmacists should continue to counsel patients as doses are increased over time.

              Chronic use of gastric acid suppressants may cause cholelithiasis.15 These drugs impact gut microbiome and may slow gallbladder motility leading to delayed gallbladder emptying. A recent prospective cohort of 0.47 million participants found that regular use of proton-pump inhibitors (PPIs) and histamine-2-receptor antagonists (H2RAs) resulted in increased cholelithiasis risk.15 Physicians should be aware of this association when prescribing these medications, especially for patients requiring long-term use or those already at high risk for gallstones. Pharmacists should keep these risks in mind when filling prescriptions for their patients on long-term or high-dose H2RAs and PPIs.

              Ketamine abuse has been associated with chronic biliary colic. Ketamine was developed in 1962 as an anesthetic.16 “Street ketamine”, a close analogue of ketamine, is commonly used for its euphoric effects. Ketamine’s onset of action after oral ingestion is about ten minutes and its hallucinogenic effects are short acting, lasting up to two hours. The most common signs of ketamine abuse are hypertension, tachycardia, and abdominal tenderness. Ketamine abuse is also associated with impaired consciousness, dizziness, abdominal pain, and lower urinary tract symptoms.16 Case reports have shown ketamine abusers presenting with severe bladder dysfunction and recurrent episodes of epigastric pain due to a dilated common bile duct not associated with gallstones.16 Clinicians should collect detailed drug histories for patients presenting with recurrent abdominal pain, namely biliary colic.

              Diets characterized by increased caloric intake with highly refined sugars, high fructose, low fiber, high fat, and consumption of fast food increase the risk of gallstone formation.9 Nutrition and lifestyle changes may be beneficial in the prevention of gallstones. Increased physical activity, consuming smaller more frequent meals, and “heart healthy” diets low in cholesterol and fat and high in fiber can reduce risk of cholelithiasis.7 Fat should not be completely cut out of the diet as too little fat can also precipitate gallstone formation.

              Weight loss can reduce gallstone risk, but rapid weight loss achieved by low-calorie diets (less than 800 kcal/day) or bariatric surgery can cause gallstones.2,9 Patients should seek professional advice before starting diets promoting very low caloric or high fat intake to achieve rapid weight loss (i.e., Atkins, ketogenic). Pharmacists should be aware of patients who have recently undergone bariatric surgery or are taking drugs or supplements for weight loss. These patients may be at a higher risk for gallstones, especially those with past medical histories of GBD or abdominal colic symptoms.

              Some foods and medications seem to be associated with a reduced risk of gallstones:

              • Statins alter bile cholesterol and thus affect gallstone formation, suggesting a role in prevention. While the relationship between statins and gallstone formation is conflicting, studies report reduction in symptomatic gallstone disease with statin use.17
              • Ezetimibe, a selective NPC1L1 inhibitor, has been associated with a reduced incidence of cholesterol gallstones in animal studies. The mechanism involves reduced amounts of absorbed cholesterol, decreasing biliary cholesterol saturation, and in turn, reduced rate of cholesterol gallstone formation.12
              • Vitamin C supplementation has been shown to reduce gallstone prevalence. Researchers have studied vitamin C supplementation’s effects in gallstone formation in guinea pigs; those deficient in vitamin C more often develop gallstones. An observational study of a randomly selected population in Germany (n = 2129) showed a positive correlation between regular vitamin C intake and a reduced gallstone incidence.18
              • Coffee consumption may also offer a protective effect against gallstone formation. Studies suggest coffee stimulates cholecystokinin release, enhancing gallbladder contractility, thereby reducing bile cholesterol crystallization. A 2019 observational analysis published in the Journal of Internal Medicine found a 23% decrease in gallstone formation in subjects consuming six or more cups of coffee daily.19
              • A small study conducted in Spain shows that regular consumption of olive oil containing monounsaturated and polyunsaturated omega-6 fatty acids may prevent gallstones. Similarly, fish (omega-3 fatty acids) and fish oil may reduce triglycerides and prevent gallstones. A group of participants with hypertriglyceridemia taking fish oil supplements for a seven-week study in the Netherlands experienced improved gallbladder motility and a decrease in triglycerides.10

              TREATING GALLBLADDER DISEASE

              Endoscopic retrograde cholangiopancreatography (ERCP) is the most common way to identify and remove common duct stones. ERCP is minimally invasive and carries the risk of acute pancreatitis.8 This diagnostic tool may also identify duct strictures at which time stents are placed to reduce obstruction and improve biliary flow.8,10 Timely stent removal (within three to six months) is crucial to prevent occlusion, stent migration, or cholangitis.22 Cholecystectomy is the definitive treatment for symptomatic gallstones and should commence within 48 hours of symptom onset during the acute inflammatory process, before tissue thickening or scarring develops.8,10

              Surgical Intervention: Cholecystectomy

              The first gallstone removal surgery was a coincidence. In the mid-19th century, a physician was performing investigative surgery on a female patient, and when he cut into her gallbladder, several bullet-like objects spilled out.5 The first planned gallbladder removal was performed 15 years later.5 Before the early 1900s, the surgery was performed through an incision in the RUQ (Kocher’s incision, named after Emil Theodor Kocher, a Swiss physician and medical researcher who performed the first successful cholecystectomy in 1878).6,8 This invasive procedure was outmoded a few years after Erich Muhe, a German surgeon, performed the first laparoscopic cholecystectomy in 1985.8 Today, surgeons perform more than 98% of cholecystectomies laparoscopically, over 70% of which are outpatient day surgeries.8

              Cholecystectomy is associated with fewer gallbladder-specific complications and shorter length of hospital stay when surgery is elective or performed as a single emergency visit without previous surgical admissions.3 A population-based cohort study of outcomes following surgery for benign GBD showed poorer outcomes and risk of readmissions with delayed cholecystectomy. Many studies define emergency or early surgical intervention as operations performed within 48 to 72 hours of symptom onset. A study of 14,200 patients in Canada discovered patients experienced fewer complications when surgery was performed within seven days of hospital admission.3 These studies show value in offering emergency surgery over delaying cholecystectomy for patients presenting with benign GBD.3

              Antibiotic prophylaxis is not routinely recommended for low-risk patients undergoing elective laparoscopic cholecystectomy.13 High-risk patients (age older than 60, type 2 diabetes, acute colic within 30 days of surgery, jaundice, acute cholecystitis, or cholangitis) may benefit. Providers should limit prophylaxis to IV cefazolin 1 g as a single dose one hour prior to surgery.13

              Several studies suggest that pain management before or during, and after laparoscopic cholecystectomy can reduce post-operative pain. A 2018 review of 258 randomized control trials recommended a basic analgesia technique: acetaminophen plus an NSAID or cyclooxygenase-2 inhibitor with local anesthetic infiltration.21 Opioids are reserved for breakthrough pain.21

              Patients are generally discharged a few hours after surgery. Surgeons should be on alert for early signs of complications if there is divergence from the usual course of rapid recovery post-op. Extreme pain shortly after surgery may indicate intra-peritoneal leakage of bile or bowel contents.8 Persistent hypotension (low blood pressure) and pain can suggest bleeding. Re-laparoscopy may be necessary to identify and repair these problems and is preferred to diagnostic imaging.8

              Removal of the gallbladder will not cause weight loss/gain or vitamin deficiencies. Patients should be able to tolerate foods they couldn’t before surgery, but providers should advise them to add those foods back into their diet very slowly. Following gallbladder removal, the liver will continue to make bile, but instead of storing it in the gallbladder, it will drain into the stomach and small intestines. Patients might experience three to five days of soreness post-op and are expected to fully heal within four to six weeks.7

              Diarrhea and bloating due to alternation of biliary flow are common short-term occurrences after surgery.22 A small percentage (1% to 2%) of patients will have loose stools each time they eat greasy or high-fat meals.7 A cystic duct remnant is also possible, potentially leading to stone formation, causing Mirizzi syndrome. Mirizzi syndrome is characterized by fever, jaundice, and RUQ pain due to common hepatic duct obstruction caused by compression from the impacted stone in the remnant cystic duct.22 Endoscopic removal of the stone may be adequate. In rarer cases, surgical excision of the remnant duct may be necessary to prevent further complications.22

              Pharmacologic and Other Non-Surgical Interventions

              Nonoperative methods exist for patients unwilling or unable to undergo surgical intervention. Contraindications for laparoscopic cholecystectomy include10,13

              • Absolute: gallbladder cancer (see Sidebar: Gallbladder Cancer), general anesthesia intolerance, giant gallstones, morbid obesity, uncontrolled bleeding disorder
              • Relative: advanced cirrhosis/liver failure, bleeding disorder, peritonitis, previous upper abdominal surgeries, septic shock

              Gallbladder Cancer20

              Gallbladder cancer is a rare malignancy but accounts for almost 50% of biliary cancers. Biliary cancers have a poor five-year survival rate and a high recurrence rate. Factors affecting prognosis are stage at discovery, tumor location, operability, response to chemotherapy, and presence and location of metastases. Early-stage gallbladder cancer may be curable with surgical resection.


              Oral bile acid dissolution drugs include ursodeoxycholic acid (ursodiol) and chenodeoxycholic acid (chenodiol).23 Table 2 lists dosing and adverse effects of these medications. Smaller gallstones (0.5 to 1 cm) may be better suited for pharmaceutical intervention but may take up to 24 months to dissolve.2 Ursodiol is preferred over chenodiol due to its safer adverse effect profile. Use-limiting adverse effects of chenodiol include dose-dependent diarrhea, hypercholesterolemia, hepatotoxicity, and leukopenia.2 Recurrence rate is more than 50% and fewer than 10% of patients with symptomatic gallstones are candidates for this treatment.13


              Table 2. Oral Bile Acids2,23,24

              Drug Dosage Duration Adverse Effects
              Ursodiol

              (Actigall)

              8-10 mg/kg/day given in 2-3 divided doses Symptom relief after 3-6 weeks, results may take 6-24 months, continue for 3 months after documented dissolution Dyspepsia (>10%), nausea, vomiting, pruritis, headache, diarrhea, dizziness, constipation
              Chenodiol (Chenodal) 250 mg twice daily for 2 weeks, increase dose by 250 mg/day weekly until maximum tolerable dose reached (13-16 mg/kg/day in 2 divided doses) Discontinue if no response by 18 months, safety not established beyond 24 months Dose-dependent diarrhea* (>10%), hypercholesterolemia, leukopenia, increased serum aminotransferase

              * If diarrhea occurs, reduce dose and restart at previous dose when symptoms resolve.


              Extracorporeal shock wave lithotripsy is a noninvasive option for symptomatic patients.13 Complications such as biliary pancreatitis and liver hematoma are rare, however stone recurrence is common. Recent studies show this procedure is beneficial for large pancreatic and common bile duct stones with similar pain relief and duct clearance outcomes compared to surgery.13

              The initial approach for pregnant women with symptomatic gallstones is supportive care.13 Meperidine is the choice agent for pain control as NSAIDs are not recommended in pregnancy.13 Chenodiol is contraindicated in pregnancy.24 Ursodiol has been used in pregnant patients for intrahepatic cholestasis; safety and efficacy of use for gallstones has not been studied.13,23 Laparoscopic cholecystectomy, when indicated, is safe in all trimesters.13

              POST-OPERATIVE CONSIDERATIONS AND THE PHARMACY TEAM

              Post-Cholecystectomy Syndrome

              Persistent or delayed onset abdominal pain after laparoscopic cholecystectomy may indicate post-cholecystectomy syndrome (PCS).22 Additional PCS symptoms include fatty food intolerance, nausea, vomiting, diarrhea, heartburn, indigestion, flatulence, and jaundice. PCS often occurs in the post-operative period but can present months or years after surgery.22 Cholecystectomy carries a low mortality risk, but approximately 10% of patients undergoing cholecystectomy each year develop PCS.22 The risk increases with urgent surgeries and 20% of patients will develop PCS regardless of choledochotomy (surgical incision of common bile duct).22

              PCS etiologies can be extra-biliary (pancreatitis, pancreatic tumors, hepatitis, esophageal diseases, mesenteric ischemia, diverticulitis, peptic ulcer disease) or biliary (bile salt induced diarrhea, retained calculi, bile leak, biliary strictures, stenosis, sphincter dyskinesia) in nature.22 Pathophysiology is related to alterations in bile flow and bile is the main trigger for patients with gastroduodenal symptoms or diarrhea.

              The likelihood of diarrhea post-cholecystectomy ranges from 2% to 50% according to various studies.25 Diarrhea usually improves or resolves over the course of weeks to months. As discussed, in the gallbladder’s absence, bile flows straight from the liver into the small intestine continuously. This redirection of bile flow can overwhelm the ileum’s capacity for reabsorption, leading to increased bile acids in the colon and subsequently cholerheic diarrhea (also known as bile acid diarrhea).25 Patients may respond to treatment with bile acid sequestrants, including cholestyramine and colestipol.25

              Bile acid sequestrants release chloride and bind bile acid in the intestines, preventing bile acid reabsorption. The drugs do not leave the gastrointestinal tract and are eliminated in the feces. They are indicated for hypercholesterolemia but patients use them off-label for chronic diarrhea due to malabsorption (Table 3). The most common adverse effect of bile acid sequestrants is constipation, which occurs in more than 10% of patients.26,27 Clinicians should instruct patients to drink plenty of fluid and increase dietary fiber. Most adverse effects are gastrointestinal-related (e.g., abdominal pain, flatulence, bloating, anorexia, nausea, vomiting, dysphagia), and others include26,27

              • Cholestasis and cholecystitis (with colestipol only)
              • Dental bleeding and caries
              • Diuresis, dysuria, and burnt odor to urine
              • Edema
              • Worsened hemorrhoids

              Bile acid sequestrants bind vitamin K and folate so prescribers should monitor for deficiencies of both. Patients should supplement with folate. Patients may supplement with vitamin K; however preexisting coagulopathy is a contraindication. These drugs should be used with caution in patients with renal insufficiency.26,27


              Table 3. Bile Acid Sequestrants26,27

              Drug Dosage Administration
              Cholestyramine

              (Prevalite, Questran)

              2-4 g daily as a single dose or divided, increase by 4 g weekly based on response and tolerability, maximum 24 g/day Mix dose in 60-180 mL of any beverage, soup, or pulpy fruit, should not be sipped or held in mouth for long periods*


              Take with meals, administer oral medications ≥1 hour before or 4-6 hours after dose

              Colestipol (Colestid) Granules: 5 g once or twice daily, increase by 5 g in 1-2 month intervals, maintenance dose 5-30 g once daily or in divided doses


              Tablets: 2 g once or twice daily, increase by 2 g in 1-2 month intervals, maintenance dose 2-16 g once daily or in divided doses

              Administer other medications ≥1 hour before or 4 hours after dose


              Granules: do not administer in dry form to avoid GI distress or accidental inhalation, should be added to at least 90 mL of any beverage, soup, or pulpy fruit


              Tablets: administer one at a time; swallow whole; do not cut, crush, or chew

              *May cause tooth discoloration or enamel decay. GI, gastrointestinal.


              PCS is a temporary diagnosis until further investigation establishes organic or functional diagnosis.22 Misdiagnosis of preexisting conditions is possible. The healthcare team should order a complete blood count and consider patients re-presenting with ongoing or new-onset abdominal pain post-cholecystectomy for CT scan.8 Presence of gas and fluid in the gallbladder bed may be normal but fluid or gas build-up elsewhere may indicate a bile leak. Elevated liver function tests may also suggest a bile leak or retained common bile duct stone. The most common cause of PCS is the presence of stones in the biliary tree.10 ERCP, both diagnostic and therapeutic, is the most common procedural approach to PCS.22

              Medication: Treatment Goals

              Pharmacologic treatment goals in GBD are to prevent complications and reduce morbidity.22 Administration of bulking agents like psyllium fiber can help patients with symptoms of irritable bowel syndrome (IBS) and/or diarrhea. Psyllium husk (Metamucil, Benefiber) is an over-the-counter (OTC) option for patients looking to increase fiber intake. It is usually used to treat constipation and works by stimulating intestinal contractility, speeding up the movement of stool through the colon.28 Psyllium can also treat diarrhea by soaking up excess water from the intestines, bulking stool, and promoting regularity.28 Psyllium may reduce absorption and effectiveness of many medications; it is important that patients seek pharmacist counseling before initiating a psyllium fiber regimen.

              Antispasmodics (e.g., loperamide) may help patients with IBS symptoms like cramping. Cholestyramine may help symptoms of diarrhea alone. Antacids (Maalox, Mylanta, Tums), H2RAs (e.g., famotidine), and PPIs (e.g., esomeprazole, lansoprazole, omeprazole) can improve gastritis or gastric reflux symptoms by reducing acid production.22 One study showed a correlation between dyspeptic symptoms and gastric bile salt; these patients may benefit from bile acid sequestrants.22 Patients should consult their gastroenterologist for recommended dosing of these drugs, as they may vary depending on clinical presentation and severity of symptoms.

              The Pharmacy Team’s Role

              Pharmacists and pharmacy technicians are integral members of the healthcare team. Pharmacists can educate patients about GBDs, the risk factors for their development, and how to mitigate them with a proper diet and exercise.

              Pharmacy technicians can help by directing patients in the right direction when looking for OTC antacids, fiber supplements, or anti-diarrheal agents. Many patients may not ask questions about OTC products before purchase. Pharmacy technicians are often the patients’ first point of contact in the pharmacy and should ask open-ended questions at the register before or during the transaction.

              Patients should use the products as directed by their gastroenterologists. Pharmacy technicians should refer patient questions relating to administration, dosing, adverse effects, and drug interactions to the pharmacist on duty. Consider possible scenarios that may arise in the pharmacy and how pharmacy technicians and pharmacists should approach them:

              • Mark is a pharmacy technician at XYZ Pharmacy. Jaclyn enters the pharmacy, approaches the pick-up window, and places several OTC items on the counter. She states she would like to pick up a prescription her doctor called in today. Mark retrieves Jaclyn’s prescription and notices it is for omeprazole 40mg. The items on the counter include Tums, famotidine 20mg, docusate sodium 100mg, and lansoprazole 30mg. Mark knows that omeprazole and lansoprazole are in the same drug class. What questions can Mark ask Jaclyn? Should Mark involve the pharmacist?
              • Jaclyn comes back to the pharmacy a week later to pick up a prescription for cholestyramine. She wants to know if she can take this with omeprazole and famotidine. Mark refers Jaclyn’s question to the pharmacist. How should the pharmacist respond to Jaclyn’s question and what counseling points are important to include?

              CONCLUSION

              Gallbladder diseases typically occur secondary to cholelithiasis. Most gallstone cases are asymptomatic, but some develop into symptomatic disease. Factors that may increase GBD risk include gender, age, family history, ethnicity, diet, and medical conditions. Surgical gallbladder removal is the most common treatment, but many nonsurgical alternatives exist when surgery is nonpreferred or contraindicated. Additionally, PCS can occur months to years after surgery and treatment should be directed based on specific diagnosis post-examination. Healthcare providers should collaborate to develop the best procedural and/or pharmaceutical treatment plan as each patient’s clinical presentation and symptoms will vary.

              The pharmacy team should take an active role in GBD management, especially following cholecystectomy. Pharmacy technicians should be wary when patients complain of abdominal pain or attempt to purchase multiple OTC products to treat their symptoms; they should relay specific disease- and drug-related questions to the pharmacist on duty. GBD is a common and highly manageable condition, and patients can live normal and healthy lives once symptoms are properly controlled and treated.


              Pharmacist Post Test (for viewing only)

              The Gall of it All: Gallbladder Disease
              26-034 Pharmacist Posttest

              After completing this continuing education activity, pharmacists will be able to
              • DESCRIBE the functions of the gallbladder and how it aids digestion
              • RECOGNIZE gallbladder disease based on various presentations
              • EXPLAIN gallstone prevalence, risk factors, and pathogenesis
              • DISCUSS treatment approaches for gallbladder disease and post-cholecystectomy management

              1. How do gallstones form?
              A. Fat soluble vitamin deficiency
              B. Gallbladder hypermotility
              C. Imbalances in bile components

              *

              2. Which of the following are risk factors for GBD?
              A. Female gender; high fat, high calorie, low fiber diet; and type 2 diabetes
              B. Female gender; low fat, high calorie, high fiber diet; and rapid weight loss
              C. Male gender; high fat, high calorie, low fiber diet; and type 2 diabetes

              *

              3. MB is a 44-year-old female who presents to the emergency department with severe RUQ pain and nausea. She states this is the third time this year that she has presented to the ED with these symptoms. MB is admitted and the hospitalist starts her on IV fluids, acetaminophen, and ketorolac. Which of the following interventions is most appropriate?
              A. MB should also receive meperidine to manage her pain
              B. MB should undergo cholecystectomy within 72 hours of admission
              C. MB is at high risk for infection and should be given IV cefazolin for prophylaxis

              *

              4. Gallstone recurrence is common with which of the following?
              A. Oral bile acid dissolution drugs
              B. Endoscopic retrograde cholangiopancreatography
              C. Asymptomatic cholelithiasis

              *

              5. Which of the following is FALSE about gallbladder removal surgery?
              A. Patients should have higher tolerability for foods they could not tolerate before surgery
              B. Patients should supplement with fat soluble vitamins post-cholecystectomy
              C. Up to 50% of patients may experience diarrhea following cholecystectomy

              *

              6. Why is diarrhea a common complication post-cholecystectomy?
              A. Overproduction of bile
              B. Vitamin deficiencies
              C. Altered biliary flow

              *

              7. Which of the following statements is TRUE regarding the use of oral bile acid dissolution agents?
              A. They can cause vitamin K and folate deficiencies
              B. Chenodiol is preferred in pregnant women due to its safer adverse effect profile
              C. Fewer than 10% of symptomatic patients are candidates for treatment

              *

              8. AP is a 37-year-old female, weighing 80 kg with symptomatic gallstones. She is not a candidate for laparoscopic cholecystectomy due to previous anesthesia intolerance. AP brings a prescription to the pharmacy for ursodiol 250 mg TID. How long will AP most likely need to take this medication?
              A. 3 to 6 weeks
              B. 6 months to 2 years
              C. 1 to 3 years

              *

              9. KM is a 42-year-old female whose gastroenterologist recommends she try psyllium husk twice daily for her chronic diarrhea post-cholecystectomy. She seems confused when you hand her Metamucil because she thought it was used for constipation. What should you tell KM?
              A. Psyllium husk treats diarrhea by binding bile acids in the gut and excreting them in the stool
              B. Psyllium husk treats diarrhea by soaking up excess water in the intestines to bulk the stool
              C. Psyllium husk treats diarrhea by increasing intestinal contractility

              *

              10. Which of the following is an appropriate counseling point for bile acid sequestrants?
              A. Their most common adverse effects are diarrhea and edema
              B. They are contraindicated in patients with uncontrolled bleeding disorders
              C. Take other oral medications at least 1 hour before or 4 hours after dose

              Pharmacy Technician Post Test (for viewing only)

              The Gall of it All: Gallbladder Disease
              26-034 Pharmacy Technician Posttest

              After completing this continuing education activity, pharmacy technicians will be able to
              • DESCRIBE the functions of the gallbladder and how it aids digestion.
              • EXPLAIN gallstone prevalence, risk factors, and pathogenesis.
              • LIST over the counter medications used often by patients with gallbladder disease and post-cholecystectomy.
              • IDENTIFY patient questions that need to be referred to a pharmacist.

              1. How do gallstones form?
              A. Fat soluble vitamin deficiency
              B. Gallbladder hypermotility
              C. Imbalances in bile components

              *

              2. Which of the following are risk factors for GBD?
              A. Female gender; high fat, high calorie, low fiber diet; and type 2 diabetes
              B. Female gender; low fat, high calorie, high fiber diet; and rapid weight loss
              C. Male gender; high fat, high calorie, low fiber diet; and type 2 diabetes

              *

              3. Gallstone recurrence is common with which of the following?
              A. Oral bile acid dissolution agents
              B. Endoscopic retrograde cholangiopancreatography
              C. Asymptomatic cholelithiasis

              *

              4. Which of the following may reduce the risk of developing gallstones?
              A. Statins
              B. Oral contraceptives
              C. Ketogenic diet

              *

              5. Why was the gallbladder more essential centuries ago?
              A. Humans consumed smaller meals containing less fat
              B. Humans consumed larger meals containing more fat
              C. Humans consumed meals containing more protein

              *

              6. What is cholelithiasis?
              A. Gallstones caused by bilirubin
              B. The presence of stones in the gallbladder
              C. The presence of gallstones in the cystic duct

              *

              7. Which of the following statements is TRUE regarding the use of oral bile acid dissolution agents?
              A. They can cause vitamin K and folate deficiencies
              B. Chenodiol is preferred in pregnant women due to its safer adverse effect profile
              C. Fewer than 10% of symptomatic patients are candidates for treatment

              *

              8. How does psyllium husk help patients with diarrhea?
              A. Psyllium husk treats diarrhea by binding bile acids in the gut and excreting them in the stool
              B. Psyllium husk treats diarrhea by soaking up excess water in the intestines to bulk the stool
              C. Psyllium husk treats diarrhea by increasing intestinal contractility

              *

              9. Which of the following patients should pharmacy technicians refer to a pharmacist?
              A. A patient holding a container of Metamucil and Fibercon fiber capsules and wants to know which contains psyllium
              B. A patient asking for help locating famotidine, which their gastroenterologist recommended for acid indigestion
              C. A patient who has failed several OTC therapies wants to know what to try for persistent diarrhea post-cholecystectomy

              *

              10. Which of the following statements is TRUE regarding OTC products for patients with GBD and/or PCS?
              A. Antispasmodics like loperamide may help patients’ gastritis symptoms
              B. Famotidine can relieve gastritis symptoms by reducing acid production
              C. Patients can take an antacid like omeprazole to calm IBS symptoms

              References

              Full List of References

              1. Division of General Surgery. History of Medicine: The Galling Gallbladder. Columbia University Irving Medical Center, New York, NY; 1999-2022. Accessed April 26, 2022. https://columbiasurgery.org/news/2015/06/11/history-medicine-galling-gallbladder
              2. Afamefuna S, Allen SN. Gallbladder disease: Pathophysiology, diagnosis, and treatment. US Pharm.2013;38(3):33-41. https://www.uspharmacist.com/article/gallbladder-disease-pathophysiology-diagnosis-and-treatment
              3. CholeS Study Group, West Midlands Research Collaborative, et al. Population‐based cohort study of outcomes following cholecystectomy for benign gallbladder diseases. [published correction appears in Br J Surg. 2018 Aug;105(9):1222]. Br J Surg. 2016;103(12):1704-1715. doi:10.1002/bjs.10287
              4. Jones MW, Small K, Kashyap S, Deppen JG. Physiology, Gallbladder. In: StatPearls. Treasure Island (FL): StatPearls Publishing; May 8, 2022.
              5. 5 surprising truths about the gallbladder. Surgical Consultants of Northern Virginia; Reston, VA. 2023. PatientPopInc. Accessed September 21, 2022. https://www.scnv.com/blog/5-surprising-truths-about-the-gallbladder
              6. De U. Evolution of cholecystectomy: A tribute to Carl August Langenbuch. Indian J Surg. 2004;66(2):97-100.
              7. Haelle T. 10 essential facts about your gallbladder. Everyday Health. August 15, 2015. Accessed September 21, 2022. https://www.everydayhealth.com/news/essential-facts-about-your-gallbladder/
              8. Beckingham IJ. Gallstones. Surgery (Oxford). 2020;38(8):453-462. doi:10.1016/j.mpsur.2020.06.002
              9. Di Ciaula A, Garruti G, Frühbeck G, et al. The role of diet in the pathogenesis of cholesterol gallstones. Curr Med Chem. 2019;26(19):3620-3638. doi:10.2174/0929867324666170530080636
              10. Ahmed A, Cheung RC, Keeffe EB. Management of gallstones and their complications. Am Fam Physician. 2000;61(6):1673-1688.
              11. Jones MW, Gnanapandithan K, Panneerselvam D, Ferguson T. Chronic Cholecystitis. In: StatPearls. Treasure Island, FL: StatPearls Publishing; October 24, 2022. Accessed March 29, 2023. https://www.ncbi.nlm.nih.gov/books/NBK470236/
              12. Di Ciaula A, Portincasa P. Recent advances in understanding and managing cholesterol gallstones. F1000Res. 2018;7:F1000 Faculty Rev-1529. doi:10.12688/f1000research.15505.1
              13. Abraham S, Rivero HG, Erlikh IV, Griffith LF, Kondamudi VK. Surgical and nonsurgical management of gallstones. Am Fam Physician. 2014;89(10):795-802.
              14. He L, Wang J, Ping F, et al. Association of glucagon-like peptide-1 receptor agonist use with risk of gallbladder and biliary diseasesA systematic review and meta-analysis of randomized clinical trialsJAMA Intern Med.2022;182(5):513–519. doi:10.1001/jamainternmed.2022.0338
              15. Yang M, Xia B, Lu Y, et al. Association between regular use of gastric acid suppressants and subsequent risk of cholelithiasis: A prospective cohort study of 0.47 million participants. Front Pharmacol. 2022;12:813587. Published 2022 Jan 28. doi:10.3389/fphar.2021.813587
              16. Al-Nowfal A, Al-Abed YA. Chronic biliary colic associated with ketamine abuse. Int Med Case Rep J. 2016;9:135-137. Published 2016 Jun 2. doi:10.2147/IMCRJ.S100648
              17. Pulkkinen J, Eskelinen M, Kiviniemi V, et al. Effect of statin use on outcome of symptomatic cholelithiasis: a case-control study. BMC Gastroenterol. 2014;14:119. Published 2014 Jul 3. doi:10.1186/1471-230X-14-119
              18. Walcher T, Haenle MM, Kron, M, et al. Vitamin C supplement use may protect against gallstones: An observational study on a randomly selected population. BMC Gastroenterol. 2009;9:74. doi:10.1186/1471-230X-9-74
              19. Nordestgaard AT, Stender S, Nordestgaard BG, et al. Coffee intake protects against symptomatic gallstone disease in the general population: a Mendelian randomization study. J Intern Med. 2020;287(1):42-53. doi:10.1111/joim.12970
              20. Mukkamalla SKR, Kashyap S, Recio-Boiles A, et al. Gallbladder Cancer. In: StatPearls. Treasure Island, FL: StatPearls Publishing; July 10, 2022. Accessed December 20, 2022. https://www.ncbi.nlm.nih.gov/books/NBK442002/
              21. Barazanchi AWH, MacFater WS, Rahiri JL, et al. Evidence-based management of pain after laparoscopic cholecystectomy: a PROSPECT review update. Br J Anaesth. 2018;121(4):787-803. doi:10.1016/j.bja.2018.06.023
              22. Zackria R, Lopez RA. Postcholecystectomy Syndrome. In: StatPearls. Treasure Island, FL: StatPearls Publishing; August 29, 2022. Accessed November 21, 2022. https://www.ncbi.nlm.nih.gov/books/NBK539902/
              23. Ursodeoxycholic Acid, Ursodiol. Clinical Pharmacology. New York, NY: Elsevier Inc.; 1960. Updated August 6, 2018. Accessed October 25, 2022. Available from: http://www.clinicalkey.com
              24. Chenodiol. Clinical Pharmacology. New York, NY: Elsevier Inc; 1960. Updated September, 29 2015. Accessed October 25, 2022. Available from: http://www.clinicalkey.com
              25. Bonis PA, Lamont JT. Approach to the adult with chronic diarrhea in resource-abundant settings. UpToDate. UpToDate Inc.; 1978-2022. Last Updated May 2, 2022. Accessed November 28, 2022. https://www.uptodate.com/contents/approach-to-the-adult-with-chronic-diarrhea-in-resource-abundant-settings
              26. Cholestyramine Resin. Lexicomp. UpToDate Inc.; 1978-2022. Updated November 25, 2022. Accessed November 29, 2022. Available from: https://online.lexi.com
              27. Colestipol. Lexicomp. UpToDate Inc., 1978-2022. Updated October 22, 2022. Accessed November 29, 2022. Available from: https://online.lexi.com
              28. Sruthi M. What does psyllium husk do? MedicineNet. Updated October 7, 2021. Accessed November 29, 2022. https://www.medicinenet.com/what_does_psyllium_husk_do/article.htm


              The ABCs of ABCD: Updates from the 2025 AACE Consensus Statement for the Evaluation and Treatment of Adults with Obesity and Adiposity-Based Chronic Disease

              Learning Objectives

                After completing this application-based continuing education activity, pharmacists will be able to
              •       EXPLAIN prevalence of obesity and adiposity-based chronic disease and the associated clinical risks
              •       DESCRIBE the care model for diagnosing, screening, and classifying obesity and ABCD
              •       REVIEW treatment options and goals for individuals with obesity and ABCD
              After completing this application-based continuing education activity, pharmacy technicians will be able to:
              •       EXPLAIN prevalence of obesity and adiposity-based chronic disease and the associated clinical risks
              •       DESCRIBE the diagnosis, screening, and classifications of obesity and ABCD
              •       REVIEW treatment options and goals for individuals with obesity and ABCD

              Release Date:

              Release Date:  June 18, 2026

              Expiration Date: June 18, 2029

              Course Fee

              Pharmacist $7

              Pharmacy Technician $4

              There is no funding for this CPE activity.

              ACPE UANs

              Pharmacist: 0009-9999-26-015-H01-P

              Pharmacy Technician: 0009-9999-26-015-H01-T

              Session Codes

              Pharmacist: 26UC15-HMJ87

              Pharmacy Technician: 26UC15-MJH78

              Accreditation Hours

              0.05 CEU    (0.5 Contact Hours)

              Accreditation Statements

              The University of Connecticut School of Pharmacy and Pharmaceutical Sciences is accredited by the Accreditation Council for Pharmacy Education as a provider of continuing pharmacy education.  Statements of credit for the online activity ACPE UAN 0009-9999-26-015-H01-P/T  will be awarded when the post test and evaluation have been completed and passed with a 70% or better. Your CE credits will be uploaded to your CPE monitor profile within 2 weeks of completion of the program.


              Disclosure of Discussions of Off-label and Investigational Drug Use

              The material presented here does not necessarily reflect the views of The University of Connecticut School of Pharmacy and Pharmaceutical Sciences or its co-sponsor affiliates. These materials may discuss uses and dosages for therapeutic products, processes, procedures and inferred diagnoses that have not been approved by the United States Food and Drug Administration. A qualified health care professional should be consulted before using any therapeutic product discussed. All readers and continuing education participants should verify all information and data before treating patients or employing any therapies described in this continuing education activity.

              Faculty

              Hazel Billings-Chiu, PharmD

              PGY-2 Ambulatory Care Pharmacy Resident, UConn Health

              Farmington, CT


              Mariam A. Zedan, PharmD, 

              PGY-2 Ambulatory Care Pharmacy Resident, UConn Health

              Farmington, CT


              Jillian Carey, PharmD, BCACP

              Pharmacy Clinical Coordinator, Primary Care

              PGY2 Ambulatory Care Residency Program Director, UConn Health

              Farmington, CT

              Faculty Disclosure

              In accordance with the Accreditation Council for Pharmacy Education (ACPE) Criteria for Quality and Interpretive Guidelines, The University of Connecticut School of Pharmacy and Pharmaceutical Sciences requires that faculty disclose any relationship that the faculty may have with commercial entities whose products or services may be mentioned in the activity.

              Hazel Billings-Chiu, PharmD, Marian Zedan, PharmD, and Jillian Carey, PharmD have no financial relationships with ineligible companies.

              CONTENT

              Content

              Pharmacist Post Test (for viewing only)

              The ABCs of ABCD: Updates from the 2025 AACE Consensus Statement for the Evaluation and Treatment of Adults with Obesity and Adiposity-Based Chronic Disease
              26-015 Pharmacist Post-Test

              Pharmacist Learning Objectives:
              1. EXPLAIN prevalence of obesity and adiposity-based chronic disease (ABCD) and the associated clinical risks
              2. DESCRIBE the care model for diagnosing, screening, and classifying obesity and ABCD
              3. REVIEW treatment options and goals for individuals with obesity and ABCD

              *

              1. Which of the following is considered an obesity-related disease?

              a. Osteoarthritis

              b. Type 2 Diabetes

              c. Gastroesophageal reflux disease


              *


              2. According to CDC data, how many adults in the United States were classified as having obesity in 2024?

              a. 1 out of 10 adults

              b. 1 out of 5 adults

              c. 1 out of 4 adults


              *


              3. What stage of ABCD would a 31-year-old female patient (height 62”, weight 93.2 kg, BMI 37.5 kg/m2) with no past medication history be considered to have?

              a. Stage 0

              b. Stage 1

              c. Stage 2


              *


              4. Patient AH is a 64-year-old male (height 70”, weight 109 kg, BMI 34.4) with a history of type 2 diabetes. What is the minimum weight loss target that should be achieved for clinically meaningful benefit?

              a. ≥ 10%

              b. ≥ 12.5%

              c. ≥ 15%


              *


              5. Which of the following is a contraindication to starting naltrexone/bupropion?

              a. History of bulimia or anorexia nervosa

              b. History of glaucoma

              c. History of cholestasis


              *


              6. Which of the following is an evidence-based lifestyle recommendation to include in a treatment plan for a patient interested in losing weight?

              a. Focus solely on aerobic exercise without resistance training

              b. Adopt a reduced-calorie, nutrient dense eating pattern such as a Mediterranean-style diet

              c. Prioritize intermittent fasting and sleep reduction to maximize energy expenditure


              Pharmacy Technician Post Test (for viewing only)

              The ABCs of ABCD: Updates from the 2025 AACE Consensus Statement for the Evaluation and Treatment of Adults with Obesity and Adiposity-Based Chronic Disease

              26-015 Pharmacy Technician Post-Test

              Pharmacy Technician Learning Objectives:
              1. EXPLAIN prevalence of obesity and adiposity-based chronic disease (ABCD) and the associated clinical risks
              2. DESCRIBE the diagnosing, screening, and classifying obesity and ABCD
              3. REVIEW treatment options and goals for individuals with obesity and ABCD


              *


              1. Which of the following factors can impact obesity prevalence?
              a. Technological advancements
              b. Rates of routine laboratory screening
              c. Healthcare access


              *


              2. According to CDC data, how many adults in the United States were classified as having obesity in 2024?

              a. 1 out of 10 adults

              b. 1 out of 5 adults

              c. 1 out of 4 adults


              *


              3. Which of the following BMI’s would be classified as “Class I Obesity?”

              a. 32 kg/m2

              b. 37 kg/m2

              c. 41 kg/m2


              *


              4. Which of the following weight loss medications is available as both an injection and an oral tablet?

              a. Phentermine/Topiramate ER (Qsymia)

              b. Semaglutide (Wegovy)

              c. Liraglutide (Saxenda)


              *


              5. How much weight reduction is considered a “good” response to weight loss medication 3 months after initiation?

              a. ≤ 5% weight reduction

              b. >5% to <15% weight reduction

              c. ≥ 15% weight reduction


              *


              6. Which of the following is an evidence-based lifestyle recommendation to include in a treatment plan for a patient interested in losing weight?

              a. Focus solely on aerobic exercise without resistance training

              b. Adopt a reduced-calorie, nutrient dense eating pattern such as a Mediterranean-style diet

              c. Prioritize intermittent fasting and sleep reduction to maximize energy expenditure